
Inbrengen van perifeer veneuze katheters
Uitgangsvraag
Welke infectiepreventiemaatregelen dienen genomen te worden bij het inbrengen van een perifeer veneuze katheter?
Deelvraag 1
Wat is de optimale locatie voor het inbrengen van een perifeer veneuze katheter om katheter-gerelateerde infecties te voorkomen?
Deelvraag 2
Welke overige infectiepreventiemaatregelen dienen genomen te worden tijdens het inbrengen van een perifeer veneuze katheter?
Aanbeveling
Aanbeveling 1 - Inbrenglocatie
- Baseer de keuze voor inbrenglocatie voor een (korte of lange) perifeer veneuze katheter niet op infectiepreventieoverwegingen.
- Baseer de keuze voor de inbrenglocatie voor een (korte of lange) perifeer veneuze katheter op de indicatie voor katheterplaatsing, de benodigde diameter van de katheter, en individuele patiëntkarakteristieken, zoals succes en complicaties van eerdere plaatsing, toegankelijkheid van de vene, de noodzaak tot vaatpreservatie, de noodzaak tot echogeleid inbrengen van de katheter, de mogelijkheid om de katheter goed te fixeren, en de bewegingsvrijheid van de patiënt.
- Bespreek de keuze voor de inbrenglocatie voor een (korte of lange) perifeer veneuze katheter met de patiënt. Bespreek hierbij de voor- en nadelen van de verschillende inbrenglocaties en beslis samen welke inbrenglocatie in de specifieke situatie van de patiënt het meest geschikt is.
Aanbeveling 2 - Overige infectiepreventiemaatregelen
Alle typen perifeer veneuze katheter
- Laat een perifeer veneuze katheter alleen inbrengen door een zorgverlener die bevoegd en bekwaam is om deze risicovolle en voorbehouden handeling uit te voeren (zie de Wet op de beroepen in de individuele gezondheidszorg (Wet BIG)).
Korte of lange perifeer veneuze katheter
- Pas bij het inbrengen van een perifeer veneuze katheter de algemene voorzorgsmaatregelen toe conform de richtlijn Handhygiëne en persoonlijke hygiëne medewerker, de richtlijn Persoonlijke beschermingsmiddelen, en de richtlijn Accidenteel bloedcontact.
- Verwijder haar alleen wanneer het in de weg zit voor het inbrengen of afplakken van een perifeer veneuze katheter.
- Verwijder haar met een (medische) tondeuse met wegwerp tondeusekop.
- Verwijder haar niet met een scheermes.
- Desinfecteer de huid voorafgaand aan het inbrengen van een perifeer veneuze katheter.
- Breng de katheter pas in als de huid volledig aan de lucht gedroogd is.
- Baseer de keuze van het desinfectans en de methode van desinfecteren op de aanbevelingen in de richtlijn Desinfectie huid en slijmvliezen plus puncties.
- Zorg dat de katheter en de gedesinfecteerde huid van de insteekplaats niet in contact komen met niet-steriele materialen.
- Neem bij het echogeleid inbrengen van een perifeer veneuze katheter aanvullend de volgende maatregelen:
- Gebruik een ‘low-level’ gedesinfecteerde echokop.
- Gebruik niet-steriele echogel tussen de echokop en de huid.
- Zorg dat de ‘low-level’ gedesinfecteerde echokop en de niet-steriele echogel niet in contact komen de katheter en de gedesinfecteerde huid van de insteekplaats.
- Gebruik geen 70% alcohol als alternatief voor niet-steriele echogel.
- Reinig de echokop na gebruik handmatig en pas 'low-level’ desinfectie van de echokop toe, tenzij de echokop verontreinigd is met bloed van de patiënt. Pas in dat geval ‘high-level’ desinfectie van de echokop toe.
- Houd bij het reinigen en desinfecteren van de echokop rekening met het gebruiksvoorschrift van de fabrikant en de randvoorwaarden voor reinigen en desinfecteren van medische hulpmiddelen die zijn beschreven in de richtlijn Reiniging, desinfectie en sterilisatie (herbruikbare) medische hulpmiddelen.
- Gebruik echoapparatuur en echogel die voldoen aan Europese wetgeving op het gebied van medische hulpmiddelen, waaronder de Verordening (EU) 2017/745, en de REACH-verordening (EG) 1907/2006.
- Gebruik voor elke inbrengpoging een nieuwe katheter.
- Gebruik geen antibiotica-bevattende zalf op de insteekplaats van een perifeer veneuze katheter.
‘Midline’ katheter
Pas bij het inbrengen van een ‘midline’ katheter de infectiepreventiemaatregelen toe zoals aanbevolen voor het inbrengen van een centraal veneuze katheter in module Inbrengen van centraal veneuze katheters.
Overwegingen
Voor- en nadelen van de interventie en de kwaliteit van het bewijs
Deelvraag 1 – Inbrenglocatie
Er is literatuuronderzoek verricht naar het effect van de inbrenglocatie voor korte (tot 5 cm) of lange (6 tot 10 cm) perifeer veneuze katheters op katheter-gerelateerde infecties bij volwassen patiënten en kinderen (geen neonaten) in de medisch specialistische zorg. ‘Midline’ katheters (vanaf 10 cm) zijn hierbij buiten beschouwing gelaten. Katheter-gerelateerde bloedbaaninfectie (KRBBI) en katheter-geassocieerde bloedbaaninfectie (KABBI) werden als cruciale uitkomstmaten gedefinieerd. Infecties van de insteekplaats, (trombo)flebitis, mortaliteit door alle oorzaken, KRBBI/KABBI-gerelateerde mortaliteit, falen van eerste inbrengpoging, en katheterfalen door alle oorzaken werden als belangrijke uitkomstmaten gedefinieerd. Een relatief risico kleiner dan 0.8 of groter dan 1.25 werd als klinisch relevant beschouwd voor alle uitkomstmaten, met uitzondering van mortaliteit. Voor mortaliteit werd een relatief risico kleiner dan 0.95 of groter dan 1.05 als klinisch relevant beschouwd.
De resultaten worden afzonderlijk gepresenteerd voor volwassenen en kinderen, omdat de optimale inbrenglocatie voor een perifeer veneuze katheter mogelijk anders is voor volwassenen en kinderen.
A. Volwassenen
Er werden één gerandomiseerde klinische studie en 30 observationele studies geïncludeerd die het effect van inbrenglocatie voor (korte) perifeer veneuze katheters vergeleken bij volwassen patiënten in het ziekenhuis.
Rug van de hand
Eén gerandomiseerde klinische studie en 29 observationele studies vergeleken inbrengen op de rug van de hand met inbrengen in de onderarm.
- In observationele studies werd de cruciale uitkomstmaat KRBBI gerapporteerd, maar het effect van inbrengen op de rug van de hand kon niet worden geschat (1 studie; bewijskracht zeer laag).
- In observationele studies werd de belangrijke uitkomstmaat infectie van de insteekplaats gerapporteerd, maar het effect van inbrengen op de rug van de hand kon niet worden geschat (1 studie; bewijskracht zeer laag).
- In observationele studies was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat (trombo)flebitis (22 studies; bewijskracht zeer laag).
- In de gerandomiseerde klinische studie was er een klinisch relevant verschil voor de belangrijke uitkomstmaat falen van eerste inbrengpoging in het voordeel van inbrengen op de rug van de hand (RR 0.50; 95% CI 0.24 tot 1.03; 1 studie; bewijskracht laag). In observationele studies was er een vergelijkbaar klinisch relevant verschil voor deze uitkomstmaat (RR 0.52; 95% CI 0.27 tot 1.02; 1 studie; bewijskracht zeer laag).
- In observationele studies was er een klinisch relevant verschil voor de belangrijke uitkomstmaat moeilijke veneuze toegang in het voordeel van inbrengen in de onderarm (RR 1.92; 95% CI 1.35 tot 2.72; 1 studie; bewijskracht zeer laag).
- In de gerandomiseerde klinische studie was er een niet klinisch relevant verschil voor de belangrijke uitkomstmaat katheterfalen door alle oorzaken (1 studie; bewijskracht zeer laag). Ook in observationele studies was er een niet klinisch relevant verschil voor deze uitkomstmaat (6 studies; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Pols
Vijftien observationele studies vergeleken inbrengen in de pols met inbrengen in de onderarm.
- In observationele studies werd de cruciale uitkomstmaat KRBBI gerapporteerd, maar het effect van inbrengen in de pols kon niet worden geschat (1 studie; bewijskracht zeer laag).
- In observationele studies werd de belangrijke uitkomstmaat infectie van de insteekplaats gerapporteerd, maar het effect van inbrengen in de pols kon niet worden geschat (1 studie; bewijskracht zeer laag).
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat (trombo)flebitis (13 studies; bewijskracht zeer laag).
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat katheterfalen door alle oorzaken (4 studies; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Elleboogplooi
Vijfentwintig observationele studies vergeleken inbrengen in de elleboogplooi met inbrengen in de onderarm.
- In observationele studies werd de cruciale uitkomstmaat KRBBI gerapporteerd, maar het effect van inbrengen in de elleboogplooi kon niet worden geschat (1 studie; bewijskracht zeer laag).
- In observationele studies werd de belangrijke uitkomstmaat infectie van de insteekplaats gerapporteerd, maar het effect van inbrengen in de elleboogplooi kon niet worden geschat (1 studie; bewijskracht zeer laag).
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat (trombo)flebitis (17 studies; bewijskracht zeer laag).
- Er was er een klinisch relevant verschil voor de belangrijk uitkomstmaat falen van eerste inbrengpoging in het voordeel van inbrengen in de elleboogplooi (RR 0.53; 95% CI 0.31 tot 0.91; 1 studie; bewijskracht zeer laag).
- Er was er een klinisch relevant verschil voor de belangrijk uitkomstmaat moeilijke veneuze toegang in het voordeel van inbrengen in de onderarm (RR 3.15; 95% CI 2.23 tot 4.44; 1 studie; bewijskracht zeer laag).
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat katheterfalen door alle oorzaken (5 studies; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Bovenarm
Zeven observationele studies vergeleken inbrengen in de bovenarm met inbrengen in de onderarm.
- De cruciale uitkomstmaat KRBBI/KABBI werd niet gerapporteerd.
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat (trombo)flebitis (7 studies; bewijskracht zeer laag).
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat katheterfalen door alle oorzaken (2 studies; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Onderste extremiteit
Vijf observationele studies vergeleken inbrengen in de onderste extremiteit met inbrengen in de onderarm.
- De cruciale uitkomstmaat KRBBI/KABBI werd niet gerapporteerd.
- Er was er een niet klinisch relevant verschil voor de belangrijk uitkomstmaat (trombo)flebitis (4 studies; bewijskracht zeer laag).
- Er was er een klinisch relevant verschil voor de belangrijk uitkomstmaat katheterfalen door alle oorzaken in het voordeel van inbrengen in de onderarm (RR 1.46; 95% CI 1.11 tot 1.92 (2 studies; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Bij het bepalen van de bewijskracht is, naast imprecisie, voor de observationele studies rekening gehouden met mogelijke ‘confounding by indication’. De overall bewijskracht, gebaseerd op de cruciale uitkomstmaat KRBBI/KABBI, kon niet worden bepaald.
We concluderen dat er voor volwassen patiënten in het ziekenhuis met een perifeer veneuze katheter het bewijs voor een effect van inbrenglocatie op KRBBI ontbreekt of zeer onzeker; dat inbrengen op de rug van de hand met lage zekerheid resulteert in minder falen van de eerste inbrengpoging; dat het bewijs voor een effect van inbrenglocatie op infectie van de insteekplaats, (trombo)flebitis, moeilijke veneuze toegang, en katheterfalen door alle oorzaken zeer onzeker is; en dat er geen bewijs is gevonden voor een effect van inbrenglocatie op de andere uitkomstmaten.
B. Kinderen
Er werd één observationele studie geïncludeerd die het effect van inbrenglocatie voor (korte) perifeer veneuze katheters vergeleek bij pediatrische patiënten in het ziekenhuis.
Rug van de hand
Eén observationele studie vergeleek inbrengen in de rug van de hand met inbrengen in de onderarm.
- De cruciale uitkomstmaat KRBBI/KABBI werd niet gerapporteerd.
- Er was een klinisch relevant verschil voor de belangrijke uitkomstmaat moeilijke veneuze toegang in het voordeel van inbrengen in de onderarm (RR 4.13; 95% CI 0.53 tot 32.06; 1 studie; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Pols
Eén observationele studie vergeleek inbrengen in de pols met inbrengen in de onderarm.
- De cruciale uitkomstmaat KRBBI/KABBI werd niet gerapporteerd.
- Er was een klinisch relevant verschil voor de belangrijke uitkomstmaat moeilijke veneuze toegang in het voordeel van inbrengen in de onderarm (RR 3.44; 95% CI 0.37 tot 37.79; 1 studie; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Elleboogplooi
Eén observationele studie vergeleek inbrengen in de elleboogplooi met inbrengen in de onderarm.
- De cruciale uitkomstmaat KRBBI/KABBI werd niet gerapporteerd.
- Er was er een klinisch relevant verschil voor de belangrijk uitkomstmaat moeilijke veneuze toegang in het voordeel van inbrengen in de onderarm (RR 1.46; 95% CI 0.18 tot 11.55; 1 studie; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Bovenarm
Er werden geen studies gevonden die inbrengen in de bovenarm vergeleken met inbrengen in de onderarm.
Onderste extremiteit
Eén observationele studie vergeleek inbrengen in de onderste extremiteit met inbrengen in de onderarm.
- De cruciale uitkomstmaat KRBBI/KABBI werd niet gerapporteerd.
- Er was er een klinisch relevant verschil voor de belangrijk uitkomstmaat moeilijke veneuze toegang in het voordeel van inbrengen in de onderarm (RR 9.40; 95% CI 1.16 tot 76.11; 1 studie; bewijskracht zeer laag).
- De andere belangrijke uitkomstmaten werden niet gerapporteerd.
Bij het bepalen van de bewijskracht is, naast imprecisie, voor de observationele studies rekening gehouden met mogelijke ‘confounding by indication’. De overall bewijskracht, gebaseerd op de cruciale uitkomstmaat KRBBI/KABBI, kon niet worden bepaald.
We concluderen dat er voor pediatrische patiënten in het ziekenhuis met een perifeer veneuze katheter geen bewijs is gevonden voor een effect van inbrenglocatie op KRBBI/KABBI; dat het bewijs voor een effect van inbrenglocatie op moeilijke veneuze toegang zeer onzeker is; en dat er geen bewijs is gevonden voor een effect van inbrenglocatie op de andere uitkomstmaten.
Deelvraag 2 – Overige infectiepreventiemaatregelen
Er is geen systematisch literatuuronderzoek verricht naar overige infectiepreventiemaatregelen bij het inbrengen van perifeer veneuze katheters bij volwassen patiënten en kinderen (geen neonaten) in de medisch specialistische zorg.
Voor aanbevelingen baseert de werkgroep zich op de eerdere WIP-richtlijn Flebitis en bloedbaaninfecties door intraveneuze infuuskatheters, internationale richtlijnen, ondersteunende literatuur, en expert opinie.
Overige overwegingen bij de keuze van inbrenglocatie
Naast infectiepreventieoverwegingen zijn ook andere factoren van belang bij de keuze voor een bepaalde inbrenglocatie voor een perifeer veneuze katheter, zoals de indicatie voor katheterplaatsing, de benodigde diameter van de katheter, en individuele patiëntkarakteristieken, zoals succes en complicaties van eerdere plaatsing, de toegankelijkheid van de vene, de noodzaak tot vaatpreservatie bij patiënten met ernstige chronische nierschade of darmfalen (zie ook richtlijn Zorg bij eindstadium nierfalen), de noodzaak tot echogeleid inbrengen van de katheter, en de mogelijkheid om de katheter goed te fixeren. Deze aspecten kunnen een grotere impact hebben op de gezondheid van de patiënt dan eventuele infectiepreventieoverwegingen.
Overige infectiepreventiemaatregelen
Overige infectiepreventiemaatregelen zijn afhankelijk van het type perifeer veneuze katheter dat wordt ingebracht.
Voor het inbrengen van een korte of lange perifeer veneuze katheter worden de volgende infectiepreventiemaatregelen aanbevolen:
- Pas bij het inbrengen van de katheter de algemene voorzorgsmaatregelen toe conform de richtlijn Handhygiëne en persoonlijke hygiëne medewerker, de richtlijn Persoonlijke beschermingsmiddelen, en de richtlijn Accidenteel bloedcontact.
- Het gebruik van een scheermes om haar te verwijderen kan resulteren in (micro)beschadigingen van de huid en daarmee het risico op infectie van de huid vergroten. Verwijder haar daarom alleen wanneer het in de weg zit voor het inbrengen of afplakken van de katheter. Verwijder haar met een (medische) tondeuse met wegwerp tondeusekop, niet met een scheermes.
- Desinfecteer de huid voorafgaand aan het inbrengen van de katheter. Breng de katheter pas in als de huid volledig aan de lucht gedroogd is. Als de katheter wordt ingebracht terwijl de huid nog nat is van het desinfectans, kan het desinfectans de insteekplaats irriteren en kan het afdekmateriaal minder goed hechten.
- Baseer de keuze voor het desinfectans en de methode van desinfecteren op de aanbevelingen in de richtlijn Desinfectie huid en slijmvliezen plus puncties.
- Zorg dat de katheter en de gedesinfecteerde huid van de insteekplaats niet in contact komen met niet-steriele materialen, zoals niet-steriele handschoenen.
- Gebruik voor elke inbrengpoging een nieuwe katheter.
- Gebruik geen antibiotica-bevattende zalf op de insteekplaats van de katheter.
Voor het echogeleid inbrengen van een korte of lange perifeer veneuze katheter worden aanvullend de volgende infectiepreventiemaatregelen aanbevolen:
- Gebruik een ‘low-level’ gedesinfecteerde echokop. De werkgroep is van mening dat in het geval van een zorgvuldige echogeleide procedure, waarbij de echokop niet in aanraking komt met de katheter en de gedesinfecteerde huid van de insteekplaats, kan worden volstaan met gebruik van een ‘low-level’ gedesinfecteerde echokop.
- Gebruik niet-steriele echogel tussen de echokop en de huid. De werkgroep is van mening dat in het geval van een zorgvuldige echogeleide procedure, waarbij de echogel niet in aanraking komt met de katheter en de gedesinfecteerde huid van de insteekplaats, kan worden volstaan met gebruik van niet-steriele echogel. Het is onduidelijk wat de meerwaarde is van het gebruik van steriele echogel tussen de echokop en de huid bij de preventie van katheter-gerelateerde infecties. Hier ligt een kennisvraag.
- Gebruik geen 70% alcohol als alternatief voor niet-steriele echogel. Het gebruik van 70% alcohol als echomedium wordt ontraden vanwege de kans op huidirritatie bij langer durend huidcontact, en de kans op irritatie van de insteekplaats wanneer deze bij het inbrengen van de katheter in contact komt met de alcohol.
- Reinig de echokop na gebruik handmatig en pas ‘low-level’ desinfectie van de echokop toe, tenzij de echokop verontreinigd is met bloed van de patiënt. Pas in dat geval ‘high-level’ desinfectie van de echokop toe.
- Houd bij het reinigen en desinfecteren van de echokop rekening met het gebruiksvoorschrift van de fabrikant en de randvoorwaarden voor reiniging en desinfectie van medische hulpmiddelen die zijn beschreven in de richtlijn Reiniging, desinfectie en sterilisatie (herbruikbare) medische hulpmiddelen.
Voor de plaats van het echogeleid inbrengen van perifeer veneuze katheters wordt verwezen naar de module Echogeleid aanprikken.
Voor het inbrengen van een ‘midline’ katheter worden dezelfde infectiepreventiemaatregelen aanbevolen als voor het inbrengen van een centraal veneuze katheter. Hiervoor wordt verwezen naar de module Inbrengen van centraal veneuze katheters. In de module Type perifeer ingebrachte veneuze katheters wordt aanbevolen om het plaatsen van een ‘midline’ katheter te overwegen bij patiënten met een moeilijk veneuze toegang, een beperkt aantal inbrenglocaties of een benodigde duur van veneuze toegang van meer dan zeven dagen. Gezien deze beoogde indicaties adviseert de werkgroep om bij het inbrengen van een ‘midline’ katheter meer voorzorgsmaatregelen te nemen dan bij het inbrengen van een korte of lange perifeer veneuze katheter.
Internationale richtlijnen
De richtlijnen van Centers for Disease Prevention and Control (CDC) (O’Grady, 2017), International Nursing Society (INS) (No authors listed, 2021), en World Health Organization (WHO) (No authors listed, 2024) zijn geraadpleegd (Tabel 1).
CDC beveelt aan om perifeer veneuze katheters in de bovenste extremiteit te plaatsen, vanwege de lagere dichtheid van de huidflora ten opzichte van de onderste extremiteit. INS beveelt aan om korte en lange perifeer veneuze katheters in de onderarm te plaatsen, en ‘midline’ katheters in de bovenarm. WHO geeft voor perifeer veneuze katheters de voorkeur aan de onderarm, maar doet geen aanbeveling voor ‘midline’ katheters. INS en WHO baseren de aanbevelingen op andere dan infectiepreventie overwegingen
CDC, INS, en WHO bevelen aan om een perifeer veneuze katheter met een aseptische ‘no-touch’ techniek in te brengen; voor het inbrengen van ‘midline’ katheters beveelt het CDC aanvullend het dragen van steriele handschoenen aan. WHO doet geen aanbeveling voor ‘midline’ katheters.
CDC, INS en WHO doen geen aanbevelingen voor infectiepreventiemaatregelen rondom het echogeleid inbrengen van perifeer veneuze katheters.
Tabel 1. Internationale richtlijnen voor de preventie van katheter-gerelateerde infecties
|
Richtlijn |
Aanbeveling(en) |
|
CDC (O’Grady, 2017) |
|
|
INS (No authors listed, 2021)1,2 |
|
|
WHO (No authors listed, 2024) |
|
CDC = Centers for Disease Prevention and Control; INS = International Nursing Society; PIVC = peripheral intravenous catheter (NL: perifeer veneuze katheter); WHO = World Health Organization
1 De INS-richtlijn is ontwikkeld met financiële ondersteuning van de industrie; ook waren auteurs niet vrij van persoonlijke financiële belangen.
2 Er wordt niet verwezen naar de in 2024 verschenen update van de INS-richtlijn, omdat deze niet publiek beschikbaar is.
Wettelijke kaders
Het inbrengen van een perifeer veneuze katheter is een risicovolle en voorbehouden handeling onder de Wet op de beroepen in de individuele gezondheidszorg (Wet BIG) die alleen mag worden uitgevoerd door een zorgverlener die daarvoor bevoegd en bekwaam is.
Echoapparatuur en echogel zijn medische hulpmiddelen en moeten als zodanig voldoen aan Europese wetgeving op het gebied van medische hulpmiddelen, waaronder de Verordening (EU) 2017/745, en de REACH-verordening (EG) 1907/2006.
Waarden en voorkeuren van patiënten (en evt. hun verzorgers)
Er is geen systematisch literatuuronderzoek verricht naar de waarden en voorkeuren van patiënten met betrekking tot infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter.
In het algemeen kan gezegd worden dat de preventie van infecties past binnen de huidige maatstaven voor passende zorg. Standaardisatie en naleving van aanbevelingen over infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter is voor patiënten belangrijk omdat dit de kans op infecties niet wegneemt, maar wel vermindert.
Voor inbrenglocatie laten incidentele studies wisselende resultaten zien als het gaat om pijnbeleving bij de patiënt, waarbij inbrengen van de katheter op de rug van de hand soms wel en soms niet als pijnlijker wordt ervaren dan inbrengen in de onderarm, elleboogplooi of bovenarm (Kaplan, 2023; van Loon, 2018).
Bij de keuze voor een bepaalde inbrenglocatie voor een perifeer veneuze katheter is het belangrijk om rekening te houden met de bewegingsvrijheid van de patiënt.
Het is belangrijk de keuze voor de inbrenglocatie voor een perifeer veneuze katheter met de patiënt te bespreken, hierbij de voor- en nadelen van de verschillende inbrenglocaties te benoemen, en samen te beslissen welke inbrenglocatie in de specifieke situatie van de patiënt het meest geschikt is.
Kosten (middelenbeslag)
Er is geen systematisch literatuuronderzoek verricht naar de kosteneffectiviteit van infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter.
In het algemeen kan gezegd worden dat katheter-gerelateerde infecties gepaard gaan met meer zorgkosten (Drugeon, 2023). Het voorkómen van deze complicaties door standaardisatie en naleving van aanbevelingen over infectiepreventiemaatregelen bij het inbrengen van de katheter resulteert naar verwachting in een vermindering van zorgkosten.
Steriele echogel wordt geleverd in kleine sachets of tubes voor eenmalig gebruik en is daarmee in het algemeen duurder dan niet-steriele echogel die wordt geleverd in grotere verpakkingen.
Gelijkheid ((health) equity)
De werkgroep voorziet voor aanbevelingen over infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter geen effect op de gezondheidsgelijkheid.
Aanvaardbaarheid
Ethische aanvaardbaarheid
De werkgroep voorziet voor aanbevelingen over infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze kathetergeen ethische bezwaren.
Duurzaamheid
Er is geen systematisch literatuuronderzoek verricht naar duurzaamheidsaspecten van de infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter.
In het algemeen kan gezegd worden dat de preventie van katheter-gerelateerde infecties leidt tot minder gebruik van medische hulpmiddelen, minder gebruik van antibiotica en de daarmee gepaard gaande ontwikkeling van antibioticaresistentie.
Steriele echogel wordt geleverd in kleine sachets of tubes voor eenmalig gebruik en is daarmee meer belastend voor het milieu dan niet-steriele echogel die wordt geleverd in grotere verpakkingen.
De werkgroep voorziet voor aanbevelingen over infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze kathetergeen effect op duurzaamheid.
Haalbaarheid
De werkgroep voorziet voor aanbevelingen over infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter geen belemmeringen voor de uitvoerbaarheid.
Rationale van de aanbeveling: weging van argumenten voor en tegen de interventies
Aanbeveling 1 – Inbrenglocatie
De aanbevelingen over de optimale locatie voor het inbrengen van een perifeer veneuze katheter bij volwassen patiënten en kinderen (geen neonaten) in de medisch specialistische zorg zijn gebaseerd op het systematisch literatuuronderzoek, de eerdere WIP-richtlijn Flebitis en bloedbaaninfecties door intraveneuze infuuskatheters, internationale richtlijnen, ondersteunende literatuur, en expert opinie.
Het literatuuronderzoek heeft zicht beperkt tot de korte (tot 5 cm) en lange (6 tot 10 cm) perifeer veneuze katheters. ‘Midline’ katheters (vanaf 10 cm) zijn buiten beschouwing gelaten.
Voor volwassen patiënten met een perifeer veneuze katheter is er onvoldoende bewijs gevonden voor een belangrijk effect van inbrenglocatie op katheter-gerelateerde infecties en katheterfalen door alle oorzaken. Voor kinderen met een perifeer veneuze katheter zijn er geen studies gevonden die het effect van inbrenglocatie op katheter-gerelateerde infecties of katheterfalen door alle oorzaken hebben onderzocht.
Voor volwassen patiënten met een perifeer veneuze katheter is er bewijs van lage kwaliteit dat inbrengen op de rug van de hand resulteert in minder falen van de eerste inbrengpoging. Voor kinderen met een perifeer veneuze katheter is er onvoldoende bewijs voor een belangrijk effect van katheter inbrenglocatie op falen van de eerste inbrengpoging of moeilijke veneuze toegang.
In de eerdere WIP-richtlijn Flebitis en bloedbaaninfecties door intraveneuze infuuskatheters en vigerende internationale richtlijnen wordt op basis van infectiepreventieoverwegingen geen voorkeur uitgesproken voor een specifieke inbrenglocatie voor lange perifeer veneuze katheters en ‘midline’ katheters.
Naast infectiepreventieoverwegingen zijn de indicatie voor katheterplaatsing, de benodigde diameter van de katheter, en individuele patiëntkarakteristieken, zoals succes en complicaties van eerdere plaatsing, toegankelijkheid van de vene, de noodzaak tot vaatpreservatie, de noodzaak tot echogeleid inbrengen van de katheter, en de mogelijkheid om de katheter goed te fixeren van belang bij het bepalen van de inbrenglocatie voor een perifeer veneuze katheter. Tot slot is het belangrijk om bij de keuze voor een bepaalde inbrenglocatie rekening te houden met de bewegingsvrijheid van de patiënt. Het effect van inbrenglocatie op de pijnbeleving van de patiënt is in incidentele studies onderzocht, maar de resultaten waren niet eenduidig.
Gezien de onzekerheid van het bewijs voor een effect van inbrenglocatie op katheter-gerelateerde infecties is de werkgroep van mening dat er geen infectiepreventieoverwegingen zijn voor of tegen een bepaalde inbrenglocatie en adviseert daarom om de keuze voor inbrenglocatie voor een perifeer veneuze katheter niet te baseren op infectiepreventieoverwegingen. De werkgroep is van mening dat de indicatie voor katheterplaatsing, de benodigde diameter van de katheter en individuele patiëntkarakteristieken bepalend moeten zijn bij de keuze voor inbrenglocatie voor een perifeer veneuze katheter, en dat de overwegingen voor het maken van een keuze voor de inbrenglocatie met de patiënt besproken moet worden (Samen beslissen). De werkgroep maakt hierbij geen onderscheid tussen korte en lange perifeer veneuze katheters of tussen volwassenen en kinderen.
Aanbeveling 2 – Overige infectiepreventiemaatregelen
Er is geen systematisch literatuuronderzoek verricht naar overige infectiepreventiemaatregelen bij het inbrengen van een perifeer veneuze katheter op katheter-gerelateerde infecties bij volwassen patiënten en kinderen (geen neonaten) in de medisch specialistische zorg. De aanbevelingen zijn gebaseerd op de eerdere WIP-richtlijn Flebitis en bloedbaaninfecties door intraveneuze infuuskatheters, internationale richtlijnen, ondersteunende literatuur, en expert opinie. De werkgroep maakt hierbij geen onderscheid tussen verschillende typen perifeer veneuze katheters of tussen volwassenen en kinderen.
Het inbrengen van een perifeer veneuze katheter is een risicovolle en voorbehouden handeling onder de Wet op de beroepen in de individuele gezondheidszorg (Wet BIG) die alleen mag worden uitgevoerd door een zorgverlener die daarvoor bevoegd en bekwaam is.
Overige infectiepreventiemaatregelen zijn afhankelijk van het type perifeer veneuze katheter dat wordt ingebracht.
(Korte of lange) perifeer veneuze katheter
Om besmetting van de katheter te voorkomen dienen bij het inbrengen van een korte of lange perifeer veneuze katheter de algemene voorzorgsmaatregelen te worden toegepast conform de richtlijn Handhygiëne en persoonlijke hygiëne medewerker, de richtlijn Persoonlijke beschermingsmiddelen, en de richtlijn Accidenteel bloedcontact.
Om (micro)beschadigingen van de huid en daarmee de kans op infecties te voorkomen is het advies om haar alleen te verwijderen wanneer het in de weg zit voor het inbrengen of afplakken van de katheter en hierbij geen scheermes maar een (medische) tondeuse met wegwerptondeusekop te gebruiken.
De werkgroep adviseert om de huid te desinfecteren voorafgaand aan het inbrengen van de katheter. Het is hierbij van belang de katheter pas in te brengen als de huid volledig aan de lucht gedroogd is. Voor de keuze van het desinfectans en de methode van desinfecteren wordt verwezen naar de richtlijn Desinfectie huid en slijmvliezen plus puncties. Het is belangrijk dat de katheter en de gedesinfecteerde huid van de insteekplaats niet in contact komen met niet-steriele materialen, zoals niet-steriele handschoenen.
Aanvullend is het advies om bij het echogeleid inbrengen van de katheter een ‘low-level’ gedesinfecteerde echokop te gebruiken, en de echokop na gebruik handmatig te reinigen en ‘low-level’ te desinfecteren (‘high-level’ bij verontreiniging van de echokop met bloed van de patiënt), rekening houdend met het gebruiksvoorschrift van de fabrikant en de randvoorwaarden voor reinigen en desinfecteren van medische hulpmiddelen die zijn beschreven in de richtlijn Reiniging, desinfectie en sterilisatie (herbruikbare) medische hulpmiddelen. Daarnaast is het advies om niet-steriele echogel te gebruiken tussen de echokop en de huid. Het is onduidelijk wat de meerwaarde is van het gebruik van steriele echogel tussen de echokop en de huid bij de preventie van katheter-gerelateerde infecties. Hier ligt een kennisvraag. Het is belangrijk dat de ‘low-level’ gedesinfecteerde echokop en de niet-steriele echogel niet in aanraking komen met de katheter en de gedesinfecteerde huid van de insteekplaats. Het gebruik van 70% alcohol als alternatief voor niet-steriele echogel wordt ontraden. Echoapparatuur en echogel moeten voldoen aan Europese wetgeving op het gebied van medische hulpmiddelen, waaronder de Verordening (EU) 2017/745, en de REACH-verordening (EG) 1907/2006.
Tot slot adviseert de werkgroep om voor elke inbrengpoging voor een perifeer veneuze katheter een nieuwe katheter te gebruiken en geen antibiotica-bevattende zalf te gebruiken op de insteekplaats van de katheter.
‘Midline’ katheter
Voor het inbrengen van een ‘midline’ katheter worden dezelfde infectiepreventiemaatregelen aanbevolen als voor het inbrengen van een centraal veneuze katheter. Zie hiervoor module Inbrengen van centraal veneuze katheters.
Voor de plaats van het echogeleid inbrengen van perifeer veneuze katheters wordt verwezen naar de module Echogeleid aanprikken.
Onderbouwing
Een perifeer veneuze katheter wordt ingebracht in een perifere vene en reikt niet verder dan de perifere venen.
Een perifeer veneuze katheter wordt gebruikt om (kortdurend) toegang te verkrijgen tot de bloedbaan voor het toedienen van medicatie, vloeistoffen en bloedproducten, en in uitzonderlijke gevallen voor het afnemen van bloed en het toedienen van parenterale voeding.
Er zijn verschillende typen perifeer veneuze katheters: 1) een korte perifeer veneuze katheter (tot 5 cm), die meestal wordt ingebracht in een vene in de hand, onderarm of elleboogplooi, ook wel bekend als ‘perifeer infuus’; 2) een lange perifeer veneuze katheter (6 tot 10 cm), die wordt ingebracht in een vene in de onderarm, elleboogplooi of bovenarm; en 3) een ‘midline’ katheter (vanaf 10 cm), die wordt ingebracht in een grote vene in de bovenarm.
Het gebruik van een perifeer veneuze katheter kan gepaard gaan met infectieuze en niet-infectieuze complicaties, zoals een bloedbaaninfectie en trombose. Deze complicaties kunnen belastend zijn voor de patiënt en kunnen resulteren in een afname van de kwaliteit van leven en een toename in zorgkosten.
Deze module beschrijft de optimale locatie voor het inbrengen van een perifeer veneuze katheter om katheter-gerelateerde infecties te voorkomen, en de overige infectiepreventiemaatregelen die bij het inbrengen van de katheter genomen dienen te worden voor volwassen patiënten en kinderen (geen neonaten) in de medisch specialistische zorg.
In de huidige klinische praktijk wordt een (korte of lange) perifeer veneuze katheter meestal ingebracht in een perifere vene in de onderarm, maar soms ook in de hand, elleboogplooi, bovenarm, enkel of voet. Het is onduidelijk wat het effect is van de inbrenglocatie op katheter-gerelateerde infecties; het literatuuronderzoek richt zich op dit aspect. De ‘midline’ katheter is voor deze vraag buiten beschouwing gelaten.
Table 1a. Summary of findings - back of the hand versus forearm - adults
P: Adult patients requiring a peripheral venous catheter
I: Insertion in the back of the hand
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI (critical) |
Observational studies 1,017 (1 study)
|
Observational studies RR not estimable |
Observational studies RD not estimable |
Very low1 |
The evidence is very uncertain about the effect of catheter insertion in the back of the hand on CRBSI compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Liu, 2022) |
|
Insertion site infection (important) |
Observational studies 1,017 (1 study)
|
Observational studies RR not estimable |
Observational studies RD not estimable |
Very low1 |
No evidence was found regarding the effect of catheter insertion in the back of the hand on insertion site infection compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Liu, 2022) |
|
(Thrombo)phlebitis (important) |
Observational studies 68,735 (20 studies) |
Observational studies RR 0.0.90 (95% CI 0.78 to 1.03)
Not clinically relevant |
Observational studies Back of the hand: 50 per 1,000 Forearm: 55 per 1,000
RD 6 fewer (95% CI 12 fewer to 2 more) |
Observational studies Very low2 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the back of the hand on (thrombo)phlebitis compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Bregenzer, 1998; Buzatto, 2016; Cicolini, 2009; Cicolini, 2014; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Kaur, 2011; Liu, 2022; Lulie, 2021; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Saini, 2011; Simin, 2019; Simões, 2022; Singh, 2008; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022) |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on all-cause mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important)
|
RCTs 307 (1 study) |
RCTs RR 0.50 95% CI 0.24 to 1.03)
Clinically relevant In favor of back of the hand |
RCTs Back of the hand: 65 per 1,000 Forearm: 131 per 1,000
RD 65 fewer (95% CI 99 fewer to 4 more) |
RCTs Low3
|
RCTs Catheter insertion in the back of the hand may reduce first-attempt insertion failure compared with insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Tan, 2016) |
|
Observational studies 208 (1 study) |
Observational studies RR 0.52 (95% CI 0.27 to 1.02)
Clinically relevant In favor of back of the hand |
Observational studies Back of the hand: 105 per 1,000 Forearm: 202 per 1,000
RD 97 fewer (95% CI 148 fewer to 4 more) |
Observational studies Very low4 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the back of the hand on first-attempt insertion failure compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2016) |
|
|
Difficult venous access (important) |
Observational studies 2,057 (1 study) |
Observational studies RR 1.92 (95% CI 1.35 to 2.72)
Clinically relevant In favor of forearm |
Observational studies Back of the hand: 82 per 1,000 Forearm: 43 per 1,000
RD 39 more (95% CI 15 more to 74 more) |
Observational studies Very low5 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the back of the hand on difficult venous access compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Rodriguez-Calero, 2020) |
|
Catheter failure for any reason (important) |
RCTs 307 (1 study) |
RCTs RR 1.08 95% CI 0.49 to 2.38)
Not clinically relevant |
RCTs Back of the hand: 78 per 1,000 Forearm: 72 per 1,000
RD 6 more (95% CI 37 fewer to 99 more) |
RCTs Very low6
|
Observational studies The evidence is very uncertain about the effect of catheter insertion in the back of the hand on catheter failure for any reason compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2018; Chen, 2022; Marsh, 2021; Shimoni, 2023; Wei, 2019; Zhu, 2016) |
|
Observational studies 6,797 (6 studies) |
Observational studies RR 0.98 (95% CI 0.88 to 1.10)
Not clinically relevant
|
Observational studies Back of the hand: 416 per 1,000 Forearm: 425 per 1,000
RD 8 fewer (95% CI 51 fewer to 42 more) |
Observational studies Very low7 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the back of the hand on catheter failure for any reason compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2018; Chen, 2022; Marsh, 2021; Shimoni, 2023; Wei, 2019; Zhu, 2016) |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio or rate ratio
* The risk in the back of the hand group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence started at high for RCTs and low for observational studies.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and zero events in both study groups with a total sample size <4,000 (imprecision; -2).
2 Downgraded by one level due to the use of catheters as the unit of analysis, exclusion of patients with incomplete exposure and/or confounding data, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the lower threshold for clinical relevance (imprecision; -1).
3 Downgraded by two levels due to lack of blinding (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the lower threshold for clinical relevance (imprecision; -1).
4 Downgraded by one level due to enrolment dependent on day of the week and hour of the day, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the lower threshold for clinical relevance (imprecision; -1).
5 Downgraded by one level due to potential confounding by indication (risk of bias; -1).
6 Downgraded by three levels due to lack of blinding (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing both thresholds for clinical relevance (imprecision; -2).
7 Downgraded by one level due to the use of catheters as the unit of analysis, enrolment dependent on day of the week and hour of the day, and potential confounding by indication (risk of bias; -1).
Table 1b. Summary of findings - back of the hand versus forearm – children
P: Pediatric patients requiring a peripheral venous catheter
I: Insertion in the back of the hand
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI/CABSI (critical) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on CRBSI/CABSI compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Insertion site infection (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on insertion site infection compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
(Thrombo)phlebitis (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on (thrombo)phlebitis compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on all-cause mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on first-attempt failure compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
Observational studies 138 (1 study) |
Observational studies RR 4.13 (95% CI 0.53 to 32.06)
Clinically relevant In favor of forearm |
Observational studies Back of the hand: 88 per 1,000 Forearm: 21 per 1,000
RD 67 more (95% CI 10 fewer to 661 more) |
Observational studies Very low1 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the back of the hand on difficult venous access compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter.
(Petroski, 2015) |
|
Catheter failure for any reason (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the back of the hand on catheter failure for any reason compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the back of the hand group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing both thresholds for clinical relevance (imprecision; -2).
Table 2a. Summary of findings - wrist versus forearm - adults
P: Adult patients requiring a peripheral venous catheter
I: Insertion in the wrist
C: Insertion in the forearm
S: hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI (critical) |
Observational studies 530 (1 study)
|
Observational studies RR not estimable |
Observational studies RD not estimable |
Very low1 |
The evidence is very uncertain about the effect of catheter insertion in the wrist on CRBSI compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Liu, 2022) |
|
Insertion site infection (important) |
Observational studies 530 (1 study)
|
Observational studies RR not estimable |
Observational studies RD not estimable |
Very low1 |
No evidence was found regarding the effect of catheter insertion in the wrist on insertion site infection compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Liu, 2022) |
|
(Thrombo)phlebitis (important) |
Observational studies 57,781 (15 studies) |
Observational studies RR 0.99 (95% CI 0.86 to 1.13)
Not clinically relevant |
Observational studies Wrist: 46 per 1,000 Forearm: 46 per 1,000
RD 0 fewer (95% CI 6 fewer to 6 more) |
Observational studies Very low2 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the wrist on (thrombo)phlebitis compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Kaur, 2011; Liu, 2022; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Simin, 2019; Simões, 2022; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022) |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on all-cause mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on first-attempt insertion failure compared with catheter insertion in the forearm in adult in-hospital patients with a requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on difficult venous access compared with catheter insertion in the forearm in adult in-hospital patients with a requiring a peripheral venous catheter. |
|
Catheter failure for any reason (important) |
Observational studies 9,513 (4 studies) |
Observational studies RR 0.93 (95% CI 0.87 to 1.00)
Not clinically relevant
|
Observational studies Wrist: 380 per 1,000 Forearm: 408 per 1,000
RD 29 fewer (95% CI 53 fewer to 0 fewer) |
Observational studies Very low3 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the wrist on catheter failure for any reason compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2018; Chen, 2022; Marsh, 2021; Zhu, 2016) |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the wrist group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and zero events in both study groups with a total sample size <4,000 (imprecision; -2).
2 Downgraded by one level due to the use of catheters as the unit of analysis, exclusion of patients with incomplete exposure and/or confounding data, and potential confounding by indication (risk of bias; -1).
3 Downgraded by one level due to enrolment dependent on day of the week and hour of the day, and potential confounding by indication (risk of bias; -1).
Table 2b. Summary of findings - wrist versus forearm - children
P: Pediatric patients requiring a peripheral venous catheter
I: Insertion in the wrist
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI/CABSI (critical) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on CRBSI/CABSI compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Insertion site infection (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on insertion site infection compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
(Thrombo)phlebitis (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on (thrombo)phlebitis compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on all-cause mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on first-attempt failure compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
Observational studies 88 (1 study) |
Observational studies RR 3.44 (95% CI 0.37 to 37.79)
Clinically relevant In favor of forearm |
Observational studies Wrist: 73 per 1,000 Forearm: 21 per 1,000
RD 52 more (95% CI 13 fewer to 783 more) |
Observational studies Very low1 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the wrist on difficult venous access compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter.
(Petroski, 2015) |
|
Catheter failure for any reason (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the wrist on catheter failure for any reason compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the wrist group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing both thresholds for clinical relevance (imprecision; -2).
Table 3a. Summary of findings - antecubital fossa versus forearm - adults
P: Adult patients requiring a peripheral venous catheter
I: Insertion in the antecubital fossa
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI (critical) |
Observational studies 514 (1 study)
|
Observational studies RR not estimable |
Observational studies RD not estimable |
Very low1 |
The evidence is very uncertain about the effect of catheter insertion in the wrist on CRBSI compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Liu, 2022) |
|
Insertion site infection (important) |
Observational studies 514 (1 study)
|
Observational studies RR not estimable |
Observational studies RD not estimable |
Very low1 |
No evidence was found regarding the effect of catheter insertion in the wrist on insertion site infection compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Liu, 2022) |
|
(Thrombo)phlebitis (important) |
Observational studies 78,920 (17 studies) |
Observational studies RR 0.99 (95% CI 0.85 to 1.16)
Not clinically relevant |
Observational studies Antecubital fossa: 53 per 1,000 Forearm: 53 per 1,000
RD 0.5 fewer (95% CI 8 fewer to 9 more) |
Observational studies Very low2 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the antecubital fossa on (thrombo)phlebitis compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Buzatto, 2016; Cicolini, 2009; Cicolini, 2014; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Liu, 2022; Lulie, 2021; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Simin, 2019; Simões, 2022; Singh, 2008; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022) |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on all-cause mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
Observational studies 346 (1 study) |
Observational studies RR 0.53 (95% CI 0.31 to 0.91)
Clinically relevant In favor of antecubital fossa
|
Observational studies Antecubital fossa: 107 per 1,000 Forearm: 202 per 1,000
RD 95 fewer (95% CI 139 fewer to 18 fewer) |
Observational studies Very low3 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the antecubital fossa on first-attempt insertion failure compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2016) |
|
Difficult venous access (important) |
Observational studies 1,729 (1 study) |
Observational studies RR 3.15 (95% CI 2.23 to 4.44)
Clinically relevant In favor of forearm |
Observational studies Antecubital fossa: 135 per 1,000 Forearm: 43 per 1,000
RD 92 more (95% CI 53 more to 147 more) |
Observational studies Very low4 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the antecubital fossa on difficult venous access compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Rodriguez-Calero, 2020) |
|
Catheter failure for any reason (important) |
Observational studies 10,377 (5 studies) |
Observational studies RR 1.03 (95% CI 0.97 to 1.10)
Not clinically relevant
|
Observational studies Antecubital fossa: 420 per 1,000 Forearm: 407 per 1,000
RD 12 more (95% CI 12 fewer to 41 more) |
Observational studies Very low5
|
Observational studies The evidence is very uncertain about the effect of catheter insertion in the antecubital fossa on catheter failure for any reason compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2018; Chen, 2022; Marsh, 2021; Shimoni, 2023; Zhu, 2016) |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio or rate ratio
* The risk in the antecubital fossa group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and zero events in both study groups with a total sample size <4,000 (imprecision; -2).
2 Downgraded by one level due to the use of catheters as the unit of analysis, exclusion of patients with incomplete exposure and/or confounding data, and potential confounding by indication (risk of bias; -1).
3 Downgraded by one level due to enrolment dependent on day of the week and hour of the day, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the lower threshold for clinical relevance (imprecision; -1).
4 Downgraded by one level due to potential confounding by indication (risk of bias; -1).
5 Downgraded by one level due to the use of catheters as the unit of analysis, exclusion of patients with incomplete exposure and/or confounding data, and potential confounding by indication (risk of bias; -1).
Table 3b. Summary of findings - antecubital fossa versus forearm - children
P: Pediatric patients requiring a peripheral venous catheter
I: Insertion in the antecubital fossa
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI/CABSI (critical) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on CRBSI/CABSI compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Insertion site infection (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on insertion site infection compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
(Thrombo)phlebitis (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on (thrombo)phlebitis compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on all-cause mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on first-attempt failure compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
Observational studies 273 (1 study) |
Observational studies RR 1.46 (95% CI 0.18 to 11.55)
Clinically relevant In favor of forearm |
Observational studies Antecubital fossa: 31 per 1,000 Forearm: 21 per 1,000
RD 10 more (95% CI 17 fewer to 224 more) |
Observational studies Very low1 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the antecubital fossa on difficult venous access compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter.
(Petroski, 2015) |
|
Catheter failure for any reason (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the antecubital fossa on catheter failure for any reason compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the antecubital fossa group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing both thresholds for clinical relevance (imprecision; -2).
Table 4a. Summary of findings - upper arm versus forearm - adults
P: Adult patients requiring a peripheral venous catheter
I: Insertion in the upper arm
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI/CABSI (critical) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the upper arm on CRBSI/CABSI compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
Insertion site infection (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the upper arm on insertion site infection compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
(Thrombo)phlebitis (important) |
Observational studies 9,800 (7 studies) |
Observational studies RR 0.82 (95% CI 0.66 to 1.01)
Not clinically relevant |
Observational studies Upper arm: 100 per 1,000 Forearm: 122 per 1,000
RD 22 fewer (95% CI 42 fewer to 1 more) |
Observational studies Very low1 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the upper arm on (thrombo)phlebitis compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Buzatto, 2016; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Simões, 2022; Urbanetto, 2017; Yasuda, 2022) |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the upper arm on all-cause mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the upper arm on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the upper arm on first-attempt insertion failure compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the upper arm on difficult venous access compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
Catheter failure for any reason (important) |
Observational studies 6,359 (2 studies) |
Observational studies RR 0.82 (95% CI 0.31 to 2.15)
Not clinically relevant
|
Observational studies Upper arm: 288 per 1,000 Forearm: 352 per 1,000
RD 63 fewer (95% CI 243 fewer to 404 more) |
Observational studies Very low2 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the upper arm on catheter failure for any reason compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Carr, 2018; Marsh, 2021) |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the upper arm group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to the use of catheters as the unit of analysis, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the lower threshold for clinical relevance (imprecision; -1).
2 Downgraded by one level due to enrolment dependent on day of the week and hour of the day, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing both thresholds for clinical relevance (imprecision; -2).
Table 5a. Summary of findings - lower limb versus forearm - adults
P: Adult patients requiring a peripheral venous catheter
I: Insertion in the lower limb
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI/CABSI (critical) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on CRBSI/CABSI compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
Insertion site infection (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on insertion site infection compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
(Thrombo)phlebitis (important) |
Observational studies 8,987 (4 studies) |
Observational studies RR 1.01 (95% CI 0.60 to 1.70)
Not clinically relevant |
Observational studies Lower limb: 142 per 1,000 Forearm: 140 per 1,000
RD 1 more (95% CI 56 fewer to 98 more) |
Observational studies Very low1 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the lower limb on (thrombo)phlebitis compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Marsh, 2021; Simin, 2019; Urbanetto, 2017; Yasuda, 2022) |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on all-cause mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on first-attempt insertion failure compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on difficult venous access compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. |
|
Catheter failure for any reason (important) |
Observational studies 6,075 (2 studies) |
Observational studies RR 1.46 (95% CI 1.11 to 1.92)
Clinically relevant In favor of forearm
|
Observational studies Lower limb: 520 per 1,000 Forearm: 356 per 1,000
RD 164 more (95% CI 39 more to 328 more) |
Observational studies Very low2 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the lower limb on catheter failure for any reason compared with catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter.
(Marsh, 2021; Zhu, 2016) |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the lower limb group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to the use of catheters as the unit of analysis, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing both thresholds for clinical relevance (imprecision; -2).
2 Downgraded by one level due to the use of catheters as the unit of analysis, and potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the upper threshold for clinical relevance (imprecision; -1).
Table 5b. Summary of findings - lower limb versus forearm - children
P: Pediatric patients requiring a peripheral venous catheter
I: Insertion in the lower limb
C: Insertion in the forearm
S: Hospital
|
Outcome |
Number of patients (studies) |
Relative effect (95% CI) |
Absolute effect estimate (95% CI)* |
Certainty of the evidence** |
Conclusions |
|
CRBSI/CABSI (critical) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on CRBSI/CABSI compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Insertion site infection (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on insertion site infection compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
(Thrombo)phlebitis (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on (thrombo)phlebitis compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
All-cause mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on all-cause mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
CRBSI/CABSI-related mortality (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on CRBSI/CABSI-related mortality compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
First-attempt insertion failure (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on first-attempt failure compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
|
Difficult venous access (important) |
Observational studies 72 (1 study) |
Observational studies RR 9.40 (95% CI 1.16 to 76.11)
Clinically relevant In favor of forearm |
Observational studies Lower limb: 200 per 1,000 Forearm: 21 per 1,000
RD 179 more (95% CI 3 more to 1,598 more) |
Observational studies Very low1 |
Observational studies The evidence is very uncertain about the effect of catheter insertion in the lower limb on difficult venous access compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter.
(Petroski, 2015) |
|
Catheter failure for any reason (important) |
- |
- |
- |
No GRADE |
No evidence was found regarding the effect of catheter insertion in the lower limb on catheter failure for any reason compared with catheter insertion in the forearm in pediatric in-hospital patients requiring a peripheral venous catheter. |
CABSI = catheter-associated bloodstream infection; CI = confidence interval; CRBSI = catheter-related bloodstream infection; RCT = randomized clinical trial; RD = risk difference; RR = risk ratio
* The risk in the lower limb group was based on the assumed risk in the forearm group and the relative effect of the intervention.
** The level of evidence for observational studies started at low.
1 Downgraded by one level due to potential confounding by indication (risk of bias; -1), and the 95% confidence interval of the risk ratio crossing the upper threshold for clinical relevance (imprecision; -1).
Summary of literature – description of studies
Subquestion 1 – Catheter insertion site
Two SRs, describing a total number of 28 studies, and eleven studies that were not described in these SRs were included in the literature summary. Although an RCT was available, observational studies were included as well. The RCT did not report any of the catheter-related infectious outcomes of interest and optimal information size was not met. The quality assessment of the SRs is summarized in the Quality assessment table.
The review by Comparcini (2017) is a systematic review on the effects of peripheral venous catheter insertion site on the incidence of catheter-related phlebitis. MEDLINE and CINAHL were searched for studies from inception until January 31, 2017. Criteria for inclusion of studies were: 1) the study was published in English; 2) RCT or observational study; 3) study in adult patients who required a peripheral venous catheter for the administration of medication, intermittent or continuous fluid infusion; and 4) the study reported phlebitis as an outcome. In total, nine studies were included in the review. The Scottish Intercollegiate Guidelines Network (SIGN) checklist was used to assess the overall methodological quality of the RCTs (Harbour, 2001). The Quality assessment checklist for observational studies (QATSO score) was used to assess the methodological quality of observational studies for the following items: external validity, reporting, bias and confounding (Wong, 2008).
All nine studies were considered eligible to answer the search question of the current module.
The review by Fan (2022) is a systematic review comparing the incidence of catheter-related complications between peripheral venous catheters in the forearm and back of the hand in adult patients. MEDLINE, CINAHL, Cochrane, and EMBASE were searched for studies from inception to July 2021. Criteria for inclusion of studies were: 1) study in adult patients requiring a peripheral venous catheter; 2) the peripheral venous catheter was placed in the forearm or at the back of the hand; 3) the study reported the incidence of catheter-related complications, including abnormal removal/failure, phlebitis, infiltration/extravasation, occlusion, dislodgment and catheter-related infection with the diagnosis based on current or internationally recognized clinical diagnostic criteria; 4) the full text was available. In total, 24 studies were included in the review. The Newcastle-Ottawa Scale was used to assess the quality of cohort and case-control studies for the following domains: selection, comparability, and outcome/exposure (Stang, 2010).
Seventeen of 24 studies were considered eligible to answer the search question of the current module. Seven studies were excluded; one was published in Spanish (Fernández-García, 2017), one was performed in a pre-hospital setting (Göransson, 2012), one did not report outcome data for the overall study population (Kishihara, 2022); one did not report any of the predefined outcomes (Lee, 2009), one did not report the forearm as insertion site (Lee, 2019), one partially duplicated another study (Marsh, 2018), and for one study, published by Garcia et al. (2017) no reference was provided.
Important study characteristics of the individual studies, including those not described in the SRs, are summarized in the Characteristics of included studies table. The assessment of the risk of bias for the individual studies is summarized in the Risk of bias table.
Subquestion 2 – Other infection control measures
Not applicable.
Summary of literature - results
Subquestion 1 – Catheter insertion site
The summary of literature is presented separately for children and adults because the optimal insertion site may differ between children and adults.
Comparison 1: Back of the hand versus forearm
P: Patients requiring a peripheral venous catheter
I: Insertion in the back of the hand
C: Insertion in the forearm
S: Hospital
One RCT (Tan, 2016) and 30 observational studies (Bregenzer, 1998; Buzatto, 2016; Carr, 2016; Carr, 2018; Chen, 2022; Cicolini, 2009; Cicolini, 2014; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Kaur, 2011; Liu, 2022; Lulie, 2021; Maki, 1991; Marsh, 2021; Petroski, 2015; Rego Furtado, 2011 A; Rego Furtado, 2011 B; Rodriguez-Calero, 2020; Saini, 2011; Shimoni, 2023; Simin, 2019; Simões, 2022; Singh, 2008; Urbanetto, 2017; Uslusoy, 2008; Wallis, 2014; Wei, 2019; Yasuda, 2022; Zhu, 2016) compared catheter insertion in the back of the hand to catheter insertion in the forearm in in-hospital patients requiring a peripheral venous catheter. One observational study included children (Petroski, 2015); one observational study included both adults and children, but data were not presented by age (Marsh, 2021); all other studies included adults only.
Adults
1. CRBSI/CABSI (critical)
One observational study reported CRBSI as an outcome (Liu, 2022). The incidence of CRBSI was 0/521 (not estimable) in the back of the hand group, compared to 0/496 (not estimable) in the forearm group. The risk ratio could not be estimated.
2. Insertion site infection (important)
One observational study reported insertion site infection as an outcome (Liu, 2022). The incidence of insertion site infection was 0/521 (not estimable) in the back of the hand group, compared to 0/496 (not estimable) in the forearm group. The risk ratio could not be estimated.
3. (Thrombo)phlebitis (important)
Twenty-two observational studies reported (thrombo)phlebitis as an outcome. For twenty studies, the results were pooled in a meta-analysis comparing insertion in the back of the hand to insertion in the forearm (Bregenzer, 1998; Buzatto, 2016; Cicolini, 2009; Cicolini, 2014; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Kaur, 2011; Liu, 2022; Lulie, 2021; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Saini, 2011; Simin, 2019; Simões, 2022; Singh, 2008; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022) (Figure 1a.3). The pooled incidence of (thrombo)phlebitis was 1,154/19,212 (6.0%) in the back of the hand group, compared to 2,778/49,523 (5.6%) in the forearm group. This resulted in a pooled 10% relative risk reduction in favor of insertion in the back of the hand (RRpooled 0.90; 95% CI 0.78 to 1.03). The relative risk reduction was considered not clinically relevant. A funnel plot was not drawn because of inconsistent results.
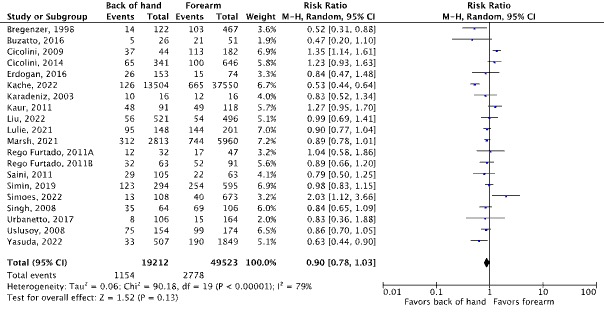
Figure 1a.3 Forest plot of (thrombo)phlebitis for catheter insertion in the back of the hand versus catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Two observational studies comparing insertion in the back of the hand to insertion in the forearm did not report the absolute numbers of events and patients (or catheter days) per insertion site (Maki, 1991; Wallis, 2014). Therefore, the results could not be included in the meta-analysis. Wallis (2014) reported a (thrombo)phlebitis rate ratio consistent with the meta-analysis’s results (RR 1.00; 95% CI 0.71 to 1.39). Maki (1991), however, reported a clinically relevant 29% relative risk reduction in favor of insertion in the back of the hand (RR 0.71; 95% CI 0.50 to 1.00).
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
One RCT reported first-attempt insertion failure as an outcome (Tan, 2016). The incidence of first-attempt insertion failure was 10/154 (6.4%) in the back of the hand group, compared to 20/153 (13.1%) in the forearm group. This resulted in a 50% relative risk reduction in favor of insertion in the back of the hand (RR 0.50; 95% CI 0.24 to 1.03). The relative risk reduction was considered clinically relevant.
One observational study reported first-attempt insertion failure as an outcome (Carr, 2016). The incidence of first-attempt insertion failure was 12/114 (10.5%) in the back of the hand group, compared to 19/94 (20.2%) in the forearm group (Carr, 2016). This resulted in a 48% relative risk reduction in favor of insertion in the back of the hand (RR 0.52; 95% CI 0.27 to 1.02). The relative risk reduction was considered clinically relevant.
7. Difficult venous access (important)
One observational study reported difficult venous access as an outcome (Rodriguez-Calero, 2020). The incidence of difficult venous access was 69/841 (8.2%) in the back of the hand group, compared to 52/1,216 (4.3%) in the forearm group. This resulted in a 92% relative risk increase in favor of insertion in the forearm (RR 1.92; 95% CI 1.35 to 2.72). The relative risk increase was considered clinically relevant.
8. Catheter failure for any reason (important)
One RCT reported catheter failure for any reason as an outcome (Tan, 2016). The incidence of catheter failure for any reason was 12/154 (7.8%) in the back of the hand group, compared to 11/153 (7.2%) in the forearm group. This resulted in an 8% relative risk increase in favor of insertion in the forearm (RR 1.08; 95% CI 0.49 to 2.38). The relative risk increase was considered not clinically relevant.
Six observational studies reported catheter failure for any reason as an outcome (Carr, 2018; Chen, 2022; Marsh, 2021; Shimoni, 2023; Wei, 2019; Zhu, 2016). The results were pooled in a meta-analysis (Figure 1a.8). The pooled incidence of catheter failure for any reason was 2,998/6,745 (44.4%) in the back of the hand group, compared to 3,799/8,940 (42.5%) in the forearm group. This resulted in a pooled 2% relative risk reduction in favor of insertion in the back of the hand (RRpooled 0.98; 95% CI 0.88 to 1.10). The relative risk reduction was considered not clinically relevant.
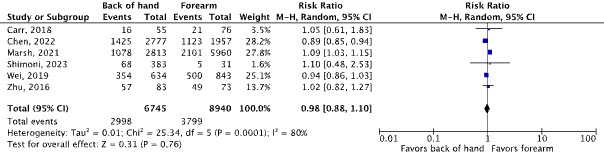
Figure 1a.8 Forest plot of catheter failure for any reason for insertion in the back of the hand versus insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Children
1. CRBSI/CABSI (critical)
None of the studies reported CRBSI/CABSI as an outcome.
2. Insertion site infection (important)
None of the studies reported insertion site infection as an outcome.
3. (Thrombo)phlebitis (important)
None of the studies reported (thrombo)phlebitis as an outcome.
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
One observational study reported difficult venous access as an outcome (Petroski, 2015). The incidence of difficult venous access was 8/91 (8.8%) in the back of the hand group, compared to 1/47 (2.1%) in the forearm group. This resulted in a 313% relative risk increase in favor of insertion in the forearm (RR 4.13; 95% CI 0.53 to 32.06). The relative risk reduction was considered clinically relevant.
8. Catheter failure for any reason (important)
None of the studies reported first-attempt insertion failure as an outcome.
Comparison 2: Wrist versus forearm
P: Patients requiring a peripheral venous catheter
I: Insertion in the wrist
C: Insertion in the forearm
S: Hospital
Nineteen observational studies (Carr, 2018; Chen, 2022; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Kaur, 2011; Liu, 2022; Maki, 1991; Marsh, 2021; Petroski, 2015; Rego Furtado, 2011 A; Rego Furtado, 2011 B; Simin, 2019; Simões, 2022; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022; Wallis, 2014; Zhu, 2016) compared catheter insertion in the wrist to catheter insertion in the forearm in in-hospital patients requiring a peripheral venous catheter. One observational study included children (Petroski, 2015); one observational study included both adults and children, but data were not presented by age (Marsh, 2021); all other studies included adults only.
Adults
1. CRBSI/CABSI (critical)
One observational study reported CRBSI as an outcome (Liu, 2022). The incidence of CRBSI was 0/34 (not estimable) in the wrist group, compared to 0/496 (not estimable) in the forearm group. The risk ratio could not be estimated.
2. Insertion site infection (important)
One observational study reported insertion site infection as an outcome (Liu, 2022). The incidence of insertion site infection was 0/34 (not estimable) in the wrist group, compared to 0/496 (not estimable) in the forearm group. The risk ratio could not be estimated.
3. (Thrombo)phlebitis (important)
Fifteen observational studies reported (thrombo)phlebitis as an outcome. For thirteen studies, the results were pooled in a meta-analysis comparing insertion in the wrist to insertion in the forearm (Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Kaur, 2011; Liu, 2022; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Simin, 2019; Simões, 2022; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022) (Figure 2a.3). The pooled incidence of (thrombo)phlebitis was 538/9,974 (5.4%) in the wrist group, compared to 2,206/47,807 (4.6%) in the forearm group. This resulted in a pooled 1% relative risk reduction in favor of insertion in the wrist (RRpooled 0.99; 95% CI 0.86 to 1.13). The relative risk reduction was considered not clinically relevant.
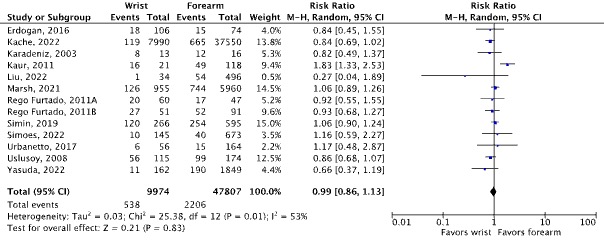
Figure 2a.3 Forest plot of (thrombo)phlebitis for catheter insertion in the wrist versus catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Two observational studies comparing insertion in the wrist to insertion in the forearm did not report the absolute numbers of events and patients (or catheter days) per insertion site (Maki, 1991; Wallis, 2014). Therefore, the results could not be included in the meta-analysis. Wallis (2014) reported a (thrombo)phlebitis rate ratio consistent with the meta-analysis’s results (RR 1.15; 95% CI 0.63 to 1.96). Maki (1991), however, reported a clinically relevant 40% relative risk reduction in favor of insertion in the wrist (RR 0.60; 95% CI 0.41 to 0.88).
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
None of the studies reported difficult venous access as an outcome.
8. Catheter failure for any reason (important)
Four observational studies reported catheter failure for any reason as an outcome (Carr, 2018; Chen, 2022; Marsh, 2021; Zhu, 2016). The results were pooled in a meta-analysis (Figure 2a.8). The pooled incidence of catheter failure for any reason was 567/1,447 (39.2%) in the wrist group, compared to 3,294/8,066 (40.8%) in the forearm group. This resulted in a pooled 7% relative risk reduction in favor of insertion in the wrist (RRpooled 0.93; 95% CI 0.87 to 1.00). The relative risk reduction was considered not clinically relevant.
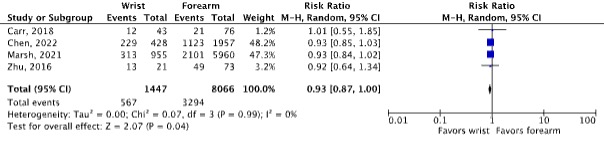
Figure 2a.8 Forest plot of catheter failure for any reason for insertion in the wrist versus insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Children
1. CRBSI/CABSI (critical)
None of the studies reported CRBSI/CABSI as an outcome.
2. Insertion site infection (important)
None of the studies reported insertion site infection as an outcome.
3. (Thrombo)phlebitis (important)
None of the studies reported (thrombo)phlebitis as an outcome.
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
One observational study reported difficult venous access as an outcome (Petroski, 2015). The incidence of difficult venous access was 3/41 (7.3%) in the wrist group, compared to 1/47 (2.1%) in the forearm group. This resulted in a 244% relative risk increase in favor of insertion in the forearm (RR 3.44; 95% CI 0.37 to 37.79). The relative risk increase was considered clinically relevant.
8. Catheter failure for any reason (important)
None of the studies reported first-attempt insertion failure as an outcome.
Comparison 3: Antecubital fossa versus forearm
P: Patients requiring a peripheral venous catheter
I: Insertion in the antecubital fossa
C: Insertion in the forearm
S: Hospital
Twenty-five observational studies (Buzatto, 2016; Carr, 2016; Carr, 2018; Chen, 2022; Cicolini, 2009; Cicolini, 2014; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Liu, 2022; Lulie, 2021; Marsh, 2021; Petroski, 2015; Rego Furtado, 2011 A; Rego Furtado, 2011 B; Rodriguez-Calero, 2020; Simin, 2019; Simões, 2022; Singh, 2008; Shimoni, 2023; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022; Wallis, 2014; Zhu, 2016) compared catheter insertion in the antecubital fossa to catheter insertion in the forearm in in-hospital patients requiring a peripheral venous catheter. One observational study included children (Petroski, 2015); one observational study included both adults and children, but data were not presented by age (Marsh, 2021); all other studies included adults only.
Adults
1. CRBSI/CABSI (critical)
One observational study reported CRBSI as an outcome (Liu, 2022). The incidence of CRBSI was 0/18 (not estimable) in the antecubital fossa group, compared to 0/496 (not estimable) in the forearm group. The risk ratio could not be estimated.
2. Insertion site infection (important)
One observational study reported insertion site infection as an outcome (Liu, 2022). The incidence of insertion site infection was 0/18 (not estimable) in the antecubital fossa group, compared to 0/496 (not estimable) in the forearm group. The risk ratio could not be estimated.
3. (Thrombo)phlebitis (important)
Eighteen observational studies reported (thrombo)phlebitis as an outcome. For seventeen studies, the results were pooled in a meta-analysis comparing insertion in the antecubital fossa to insertion in the forearm (Buzatto, 2016; Cicolini, 2009; Cicolini, 2014; Erdogan, 2016; Kache, 2022; Karadeniz, 2003; Liu, 2022; Lulie, 2021; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Simin, 2019; Simões, 2022; Singh, 2008; Urbanetto, 2017; Uslusoy, 2008; Yasuda, 2022) (Figure 3a.3). The pooled incidence of (thrombo)phlebitis was 1,082/30,045 (3.6%) in the antecubital fossa group, compared to 2,604/48,875 (5.3%) in the forearm group. This resulted in a pooled 1% relative risk reduction in favor of insertion in the antecubital fossa (RRpooled 0.99; 95% CI 0.85 to 1.16). The relative risk reduction was considered not clinically relevant.
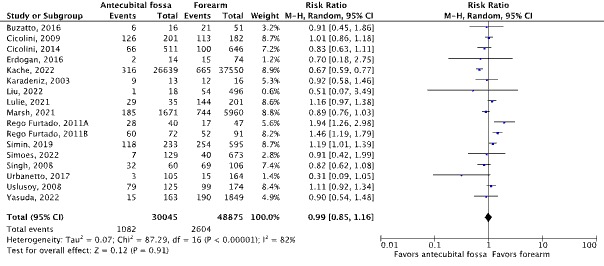
Figure 3a.3 Forest plot of (thrombo)phlebitis for catheter insertion in the antecubital fossa versus catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
One observational study comparing insertion in the antecubital fossa to insertion in the forearm did not report the absolute numbers of events and patients (or catheter days) per insertion site (Wallis, 2014). Therefore, the results could not be included in the meta-analysis. The reported (thrombo)phlebitis rate ratio (RR 1.05; 95% CI 0.70 to 1.55) is consistent with the meta-analysis’s results.
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
One observational study reported first-attempt insertion failure as an outcome (Carr, 2016). The incidence of first-attempt insertion failure was 27/252 (10.7%) in the antecubital fossa group, compared to 19/94 (20.2%) in the forearm group. This resulted in a 47% relative risk reduction in favor of insertion in the antecubital fossa (RR 0.53; 95% CI 0.31 to 0.91). The relative risk reduction was considered clinically relevant.
7. Difficult venous access (important)
One observational study reported difficult venous access as an outcome (Rodriguez-Calero, 2020). The incidence of difficult venous access was 69/513 (13.5%) in the antecubital fossa group, compared to 52/1,216 (4.3%) in the forearm group. This resulted in a 315% relative risk increase in favor of insertion in the forearm (RR 3.15; 95% CI 2.23 to 4.44). The relative risk increase was considered clinically relevant.
8. Catheter failure for any reason (important)
Five observational studies reported catheter failure for any reason as an outcome (Carr, 2018; Chen, 2022; Marsh, 2021; Shimoni, 2023; Zhu, 2016). The results were pooled in a meta-analysis (Figure 3a.8). The pooled incidence of catheter failure for any reason was 804/2,280 (35.3%) in the antecubital fossa group, compared to 3,299/8,097 (40.7%) in the forearm group. This resulted in a pooled 3% relative risk increase in favor of insertion in the forearm (RRpooled 1.03; 95% CI 0.97 to 1.10). The relative risk increase was considered not clinically relevant.
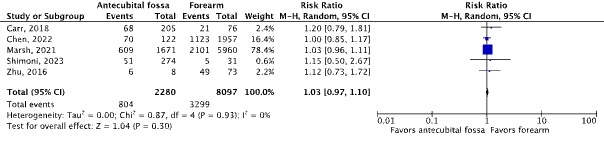
Figure 3a.8 Forest plot of catheter failure for any reason for insertion in the antecubital fossa versus insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Children
1. CRBSI/CABSI (critical)
None of the studies reported CRBSI/CABSI as an outcome.
2. Insertion site infection (important)
None of the studies reported insertion site infection as an outcome.
3. (Thrombo)phlebitis (important)
None of the studies reported (thrombo)phlebitis as an outcome.
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
One observational study reported difficult venous access as an outcome (Petroski, 2015). The incidence of difficult venous access was 7/226 (3.1%) in the antecubital fossa group, compared to 1/47 (2.1%) in the forearm group. This resulted in a 46% relative risk increase in favor of insertion in the forearm (RR 1.46; 95% CI 0.18 to 11.55). The relative risk reduction was considered clinically relevant.
8. Catheter failure for any reason (important)
None of the studies reported first-attempt insertion failure as an outcome.
Comparison 4: Upper arm versus forearm
P: Patients requiring a peripheral venous catheter
I: Insertion in the upper arm
C: Insertion in the forearm
S: Hospital
Ten observational studies (Buzatto, 2016; Carr, 2018; Marsh, 2021; Pérez-Granda, 2024; Rego Furtado, 2011 A; Rego Furtado, 2011 B; Simões, 2022; Urbanetto, 2017; Yasuda, 2022; Wallis, 2014) compared catheter insertion in the upper arm to catheter insertion in the forearm in in-hospital patients requiring a peripheral venous catheter. One observational study included both adults and children, but data were not presented by age (Marsh, 2021); all other studies included adults only.
Adults
1. CRBSI/CABSI (critical)
None of the studies reported CRBSI/CABSI as an outcome.
2. Insertion site infection (important)
None of the studies reported insertion site infection as an outcome.
3. (Thrombo)phlebitis (important)
Nine observational studies reported (thrombo)phlebitis as an outcome. For seven studies, the results were pooled in a meta-analysis comparing insertion in the upper arm to insertion in the forearm (Buzatto, 2016; Marsh, 2021; Rego Furtado, 2011A; Rego Furtado, 2011B; Simões, 2022; Urbanetto, 2017; Yasuda, 2022) (Figure 4a.3). The pooled incidence of (thrombo)phlebitis was 79/965 (8.2%) in the upper arm group, compared to 1,079/8,835 (12.2%) in the forearm group. This resulted in a pooled 18% relative risk reduction in favor of insertion in the upper arm (RRpooled0.82; 95% CI 0.66 to 1.01). The relative risk reduction was considered not clinically relevant.
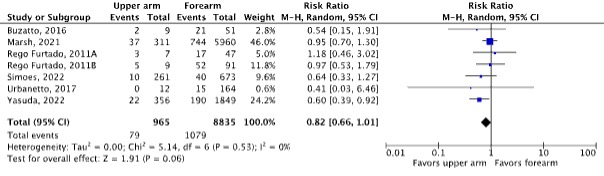
Figure 4a.3 Forest plot of (thrombo)phlebitis for catheter insertion in the upper arm versus catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Two observational studies comparing insertion in the upper arm to insertion in the forearm did not report the absolute numbers of events and patients (or catheter days) per insertion site (Pérez-Granda, 2024; Wallis, 2014). Therefore, the results could not be included in the meta-analysis. For (thrombo)phlebitis, both studies reported a clinically relevant relative risk increase in favor of insertion in the forearm (Pérez-Granda: 39% (OR 1.39; 95% CI 0.57 to 3.42); Wallis: 34% (RR 1.34; 95% CI 0.86 to 2.01)).
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
None of the studies reported difficult venous access as an outcome.
8. Catheter failure for any reason (important)
Two observational studies reported catheter failure for any reason as an outcome (Carr, 2018; Marsh, 2021). The results were pooled in a meta-analysis (Figure 4a.8). The pooled incidence of catheter failure for any reason was 115/323 (35.6%) in the upper arm group, compared to 2,122/6,036 (35.2%) in the forearm group. This resulted in a pooled 18% relative risk reduction in favor of insertion in the upper arm (RRpooled 0.82; 95% CI 0.31 to 2.15). The relative risk reduction was considered not clinically relevant.
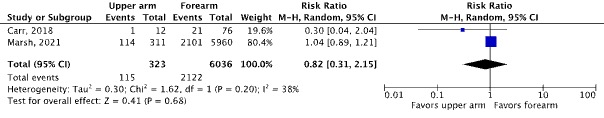
Figure 4a.8 Forest plot of catheter failure for any reason for insertion in the upper arm versus insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Children
None of the studies compared insertion in the upper arm to insertion in the forearm in in-hospital pediatric patients requiring a peripheral venous catheter.
Comparison 5: Lower limb versus forearm
P: Patients requiring a peripheral venous catheter
I: Insertion in the lower limb
C: Insertion in the forearm
S: Hospital
Six observational studies (Marsh, 2021; Petroski, 2015; Simin, 2019; Urbanetto, 2017; Yasuda, 2022; Zhu, 2016) compared catheter insertion in the lower limb to catheter insertion in the forearm in in-hospital patients requiring a peripheral venous catheter. One observational study included children (Petroski, 2015); one observational study included both adults and children, but data were not presented by age (Marsh, 2021); all other studies included adults only.
Adults
1. CRBSI/CABSI (critical)
None of the studies reported CRBSI/CABSI as an outcome.
2. Insertion site infection (important)
None of the studies reported insertion site infection as an outcome.
3. (Thrombo)phlebitis (important)
The results of four observational studies were pooled in a meta-analysis comparing insertion in the lower limb to insertion in the forearm (Marsh, 2021; Simin, 2019; Urbanetto, 2017; Yasuda, 2022) (Figure 5a.3). The pooled incidence of (thrombo)phlebitis was 49/419 (11.7%) in the lower limb group, compared to 1,203/8,568 (14.0%) in the forearm group. This resulted in a pooled 1% relative risk increase in favor of insertion in the forearm (RRpooled 1.01; 95% CI 0.60 to 1.70). The relative risk increase was considered not clinically relevant.
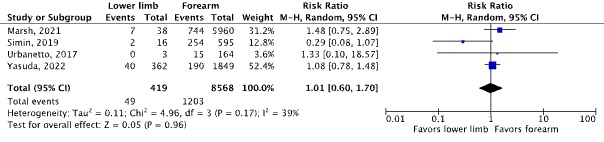
Figure 5a.3 Forest plot of (thrombo)phlebitis for catheter insertion in the lower limb versus catheter insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
None of the studies reported difficult venous access as an outcome.
8. Catheter failure for any reason (important)
Two observational studies reported catheter failure for any reason as an outcome (Marsh, 2021; Zhu, 2016). The results were pooled in a meta-analysis (Figure 5a.8). The pooled incidence of catheter failure for any reason was 24/42 (57.1%) in the lower limb group, compared to 2,150/6,033 (35.6%) in the forearm group. This resulted in a pooled 46% relative risk increase in favor of insertion in the forearm (RRpooled 1.46; 95% CI 1.11 to 1.92). The relative risk increase was considered clinically relevant.
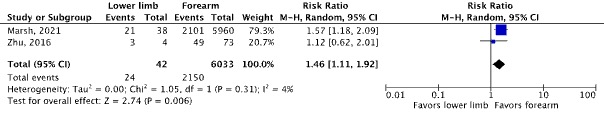
Figure 5a.8 Forest plot of catheter failure for any reason for insertion in the lower limb versus insertion in the forearm in adult in-hospital patients requiring a peripheral venous catheter. Pooled risk ratio, random effects model.
Children
1. CRBSI/CABSI (critical)
None of the studies reported CRBSI/CABSI as an outcome.
2. Insertion site infection (important)
None of the studies reported insertion site infection as an outcome.
3. (Thrombo)phlebitis (important)
None of the studies reported (thrombo)phlebitis as an outcome.
4. All-cause mortality (important)
None of the studies reported all-cause mortality as an outcome.
5. CRBSI/CABSI-related mortality (important)
None of the studies reported CRBSI/CABSI-related mortality as an outcome.
6. First-attempt insertion failure (important)
None of the studies reported first-attempt insertion failure as an outcome.
7. Difficult venous access (important)
One observational study reported difficult venous access as an outcome (Petroski, 2015). The incidence of difficult venous access was 5/25 (20.0%) in the lower limb group, compared to 1/47 (2.1%) in the forearm group. This resulted in a 840% relative risk increase in favor of insertion in the forearm (RR 9.40; 95% CI 1.16 to 76.11). The relative risk increase was considered clinically relevant.
8. Catheter failure for any reason (important)
None of the studies reported first-attempt insertion failure as an outcome.
Subquestion 1 – Catheter insertion site
A systematic review of the literature was performed to answer the following (search)question:
What is the effect of the catheter insertion site on catheter-related infections for in-hospital patients requiring a peripheral venous catheter?
Table 1. PICOS
|
Patients |
Patients (non-neonates) requiring a peripheral venous catheter |
|
Intervention |
Peripheral venous catheter inserted in other than forearm
|
|
Control |
Peripheral venous catheter inserted in forearm |
|
Outcomes* |
CRBSI CABSI** Insertion site infection (Thrombo)phlebitis All-cause mortality CRBSI/CABSI-related mortality Insertion failure Catheter failure for any reason (e.g., phlebitis, infiltration, accidental removal, occlusion) |
|
Setting |
Hospital |
|
Other selection criteria |
Study design: systematic review, randomized controlled trial, or comparative observational study |
CABSI = catheter-associated bloodstream infection; CRBSI = catheter-related bloodstream infection
* Per patient and, if reported, per 1,000 catheter days
**If CRBSI is not reported in any of the included studies
Relevant outcome measures
The guideline panel considered catheter-related bloodstream infection (CRBSI) and catheter-associated bloodstream infection (CABSI)* as critical outcome measures for decision-making; and insertion site infection, (thrombo)phlebitis, all-cause mortality, CRBSI (CABSI)-related mortality, insertion failure, and catheter failure for any reason as importantoutcome measures for decision-making.
* If CRBSI is not reported in any of the included studies
For CRBSI and CABSI, the guideline panel decided to use the definitions as described previously (Maki, 2006; Mermel, 2009; O’Grady, 2011). CRBSI was defined as a primary bloodstream infection with laboratory confirmation of the catheter as the source of the infection. CABSI was defined as a laboratory-confirmed primary bloodstream infection with the catheter in situ or within 48 hours of removal. For all other outcome measures, the guideline panel decided to use the definitions used by the authors of the individual studies.
The guideline panel defined the following thresholds for clinical relevance:
- Mortality: risk ratios of 0.95 and 1.05 (RR<0.95 or RR>1.05)
- Other dichotomous outcomes: risk ratios of 0.8 and 1.25 (RR<0.8 or RR>1.25)
Methods
Embase.com and Ovid/Medline databases were systematically searched with relevant search terms from 2000 until February 26, 2024. See Verantwoording for the detailed search strategy. The systematic literature search resulted in 445 unique hits.
Studies were selected based on the following eligibility criteria:
- Systematic review (SR) of randomized controlled trials (RCT) (at least two databases searched, detailed search strategy with search date, in- and exclusion criteria, description of individual study results, risk of bias assessment per study), or RCT; if an SR of RCTs or RCTs were not available, comparative observational studies were selected;
- SR describes at least one RCT that is not described in another selected SR;
- The research question includes all elements of the PICOS;
- The study population is not limited to hemodialysis patients;
- Full paper (i.e., no conference abstract, editorial, letter, or note);
- Full text is available;
- Full text is written in English or Dutch.
The reference lists of excluded systematic reviews were checked for studies that fulfilled the eligibility criteria and were not retrieved in the systematic literature search.
Based on title and abstract screening, 55 studies were initially selected. After reading the full text, 34 studies were excluded (Table of excluded studies), and 21 were included. Reference checking of excluded systematic reviews did not result in additional eligible studies.
Subquestion 2 – Other infection control measures
For other infection control measures related to the insertion of peripheral venous catheters, no systematic literature search was performed.
The recommendations were based on the previous WIP-guideline Flebitis en bloedbaaninfecties door intraveneuze infuuskatheters, international guidelines, supporting literature, and expert opinion.
- •Systematic reviews
- Comparcini D, Simonetti V, Blot S, Tomietto M, Cicolini G. Relationship between peripheral insertion site and catheter-related phlebitis in adult hospitalized patients: a systematic review. Prof Inferm. 2017 Jan-Mar;70(1):51-60. English. doi: 10.7429/pi.2017.701051. PMID: 28485909.
- Fan XW, Xu L, Wei WS, Chen YM, Yang YQ. Relationship between indwelling site and peripheral venous catheter-related complications in adult hospitalized patients: A systematic review and meta-analysis. J Clin Nurs. 2023 Apr;32(7-8):1014-1024. doi: 10.1111/jocn.16241. Epub 2022 Feb 28. PMID: 35229381.
- - Randomized controlled trials
- Tan PC, Mackeen A, Khong SY, Omar SZ, Noor Azmi MA. Peripheral Intravenous Catheterisation in Obstetric Patients in the Hand or Forearm Vein: A Randomised Trial. Sci Rep. 2016 Mar 18;6:23223. doi: 10.1038/srep23223. PMID: 26987593; PMCID: PMC4796788.
- •Observational studies
- Bregenzer T, Conen D, Sakmann P, Widmer AF. Is routine replacement of peripheral intravenous catheters necessary? Arch Intern Med. 1998 Jan 26;158(2):151-6. doi: 10.1001/archinte.158.2.151. PMID: 9448553.
- Buzatto LL, Massa GP, Peterlini MAS, Whitaker IY. Factors associated with phlebitis in elderly patients with amiodarone intravenous infusion. Acta Paulista Enferm. 2016;29:260-266. doi:10.1590/1982-0194201600037.
- Carr PJ, Rippey JC, Budgeon CA, Cooke ML, Higgins N, Rickard CM. Insertion of peripheral intravenous cannulae in the Emergency Department: factors associated with first-time insertion success. J Vasc Access. 2016 Mar-Apr;17(2):182-90. doi: 10.5301/jva.5000487. Epub 2015 Dec 4. PMID: 26660037.
- Carr PJ, Rippey JCR, Cooke ML, Higgins NS, Trevenen M, Foale A, Rickard CM. From insertion to removal: A multicenter survival analysis of an admitted cohort with peripheral intravenous catheters inserted in the emergency department. Infect Control Hosp Epidemiol. 2018 Oct;39(10):1216-1221. doi: 10.1017/ice.2018.190. Epub 2018 Sep 10. PMID: 30196798.
- Chen YM, Fan XW, Liu MH, Wang J, Yang YQ, Su YF. Risk factors for peripheral venous catheter failure: A prospective cohort study of 5345 patients. J Vasc Access. 2022 Nov;23(6):911-921. doi: 10.1177/11297298211015035. Epub 2021 May 13. PMID: 33985394; PMCID: PMC9585540.
- Cicolini G, Bonghi AP, Di Labio L, Di Mascio R. Position of peripheral venous cannulae and the incidence of thrombophlebitis: an observational study. J Adv Nurs. 2009 Jun;65(6):1268-73. doi: 10.1111/j.1365-2648.2009.04980.x. Epub 2009 Apr 3. PMID: 19374679.
- Cicolini G, Manzoli L, Simonetti V, Flacco ME, Comparcini D, Capasso L, Di Baldassarre A, Eltaji Elfarouki G. Phlebitis risk varies by peripheral venous catheter site and increases after 96 hours: a large multi-centre prospective study. J Adv Nurs. 2014 Nov;70(11):2539-49. doi: 10.1111/jan.12403. Epub 2014 Mar 31. PMID: 24684163.
- Erdogan BC, Denat Y. The development of phlebitis and infiltration in patients with peripheral intravenous catheters in the neurosurgery clinic and affecting factors. Int J Caring Sci 2016;9:619–629.
- Kache S, Patel S, Chen NW, Qu L, Bahl A. Doomed peripheral intravenous catheters: Bad Outcomes are similar for emergency department and inpatient placed catheters: A retrospective medical record review. J Vasc Access. 2022 Jan;23(1):50-56. doi: 10.1177/1129729820974259. Epub 2020 Nov 24. PMID: 33234001.
- Karadeniz G, Kutlu N, Tatlisumak E, Ozbakkaloğlu B. Nurses' knowledge regarding patients with intravenous catheters and phlebitis interventions. J Vasc Nurs. 2003 Jun;21(2):44-7; quiz 48-9. doi: 10.1016/s1062-0303(03)00034-7. PMID: 12813411.
- Kaur P, Thakur R, Kaur S, Bhalla A. Assessment of risk factors of phlebitis amongst intravenous cannulated patients. Nursing Midwifery Res J. 2011;7:106-114. doi:10.1177/0974150X20110302.
- Liu C, Chen L, Kong D, Lyu F, Luan L, Yang L. Incidence, risk factors and medical cost of peripheral intravenous catheter-related complications in hospitalised adult patients. J Vasc Access. 2022 Jan;23(1):57-66. doi: 10.1177/1129729820978124. Epub 2020 Dec 10. PMID: 33302797.
- Lulie M, Tadesse A, Tsegaye T, Yesuf T, Silamsaw M. Incidence of peripheral intravenous catheter phlebitis and its associated factors among patients admitted to University of Gondar hospital, Northwest Ethiopia: a prospective, observational study. Thromb J. 2021 Jul 13;19(1):48. doi: 10.1186/s12959-021-00301-x. PMID: 34256784; PMCID: PMC8276507.
- Maki DG, Ringer M. Risk factors for infusion-related phlebitis with small peripheral venous catheters. A randomized controlled trial. Ann Intern Med. 1991 May 15;114(10):845-54. doi: 10.7326/0003-4819-114-10-845. PMID: 2014945.
- Marsh N, Larsen EN, Takashima M, Kleidon T, Keogh S, Ullman AJ, Mihala G, Chopra V, Rickard CM. Peripheral intravenous catheter failure: A secondary analysis of risks from 11,830 catheters. Int J Nurs Stud. 2021 Dec;124:104095. doi: 10.1016/j.ijnurstu.2021.104095. Epub 2021 Sep 26. PMID: 34689013.
- Pérez-Granda MJ, Irigoyen-von-Sierakowski Á, Toledo N, Rodríguez E, Cruz ML, Hernanz G, Serra JA, Kestler M, Muñoz P, Guembe M. Impact of an interventional bundle on complications associated with peripheral venous catheters in elderly patients. Eur J Clin Microbiol Infect Dis. 2024 Apr;43(4):703-712. doi: 10.1007/s10096-024-04771-5. Epub 2024 Feb 8. PMID: 38326546.
- Petroski A, Frisch A, Joseph N, Carlson JN. Predictors of difficult pediatric intravenous access in a community Emergency Department. J Vasc Access. 2015 Nov-Dec;16(6):521-6. doi: 10.5301/jva.5000411. Epub 2015 Jun 20. PMID: 26109542.
- Rego Furtado LC. Maintenance of peripheral venous access and its impact on the development of phlebitis: a survey of 186 catheters in a general surgery department in Portugal. J Infus Nurs. 2011 Nov-Dec;34(6):382-90. doi: 10.1097/NAN.0b013e318230636b. PMID: 22101632. A
- Rego Furtado LC. Incidence and predisposing factors of phlebitis in a surgery department. Br J Nurs. 2011 Jul 28-Aug 4;20(14):S16-8, S20, S22 passim. doi: 10.12968/bjon.2011.20.sup7.s16. PMID: 21841668. B
- Rodriguez-Calero MA, de Pedro-Gomez JE, Molero-Ballester LJ, Fernandez-Fernandez I, Matamalas-Massanet C, Moreno-Mejias L, Blanco-Mavillard I, Moya-Suarez AB, Personat-Labrador C, Morales-Asencio JM. Risk Factors for Difficult Peripheral Intravenous Cannulation. The PIVV2 Multicentre Case-Control Study. J Clin Med. 2020 Mar 15;9(3):799. doi: 10.3390/jcm9030799. PMID: 32183475; PMCID: PMC7141318.
- Saini R, Agnihotri M, Gupta A, Walia I. Epidemiology of infiltration and phlebitis. Nursing Midwifery Research J 2011;7:22-33.
- Shimoni Z, Houdhoud N, Isaacs Y, Froom P. Observational study of peripheral intravenous catheter outcomes in an internal medicine department. Intern Med J. 2023 Feb;53(2):221-227. doi: 10.1111/imj.15963. Epub 2022 Nov 15. PMID: 36346286.
- Simin D, Milutinović D, Turkulov V, Brkić S. Incidence, severity and risk factors of peripheral intravenous cannula-induced complications: An observational prospective study. J Clin Nurs. 2019 May;28(9-10):1585-1599. doi: 10.1111/jocn.14760. Epub 2019 Jan 17. PMID: 30589945.
- Simões AMN, Vendramim P, Pedreira MLG. Risk factors for peripheral intravenous catheter-related phlebitis in adult patients. Rev Esc Enferm USP. 2022 Jun 10;56:e20210398. doi: 10.1590/1980-220X-REEUSP-2021-0398en. PMID: 35724261; PMCID: PMC10111391.
- Singh R, Bhandary S, Pun KD. Peripheral intravenous catheter related phlebitis and its contributing factors among adult population at KU Teaching Hospital. Kathmandu Univ Med J (KUMJ). 2008 Oct-Dec;6(24):443-7. doi: 10.3126/kumj.v6i4.1732. PMID: 19483423.
- Urbanetto JS, Muniz FOM, Silva RMD, Freitas APC, Oliveira APR, Santos JCRD. Incidence of phlebitis and post-infusion phlebitis in hospitalised adults. Rev Gaucha Enferm. 2017 Jun 29;38(2):e58793. Portuguese, English. doi: 10.1590/1983-1447.2017.02.58793. PMID: 28678899.
- Uslusoy E, Mete S. Predisposing factors to phlebitis in patients with peripheral intravenous catheters: a descriptive study. J Am Acad Nurse Pract. 2008 Apr;20(4):172-80. doi: 10.1111/j.1745-7599.2008.00305.x. PMID: 18387013.
- Wallis MC, McGrail M, Webster J, Marsh N, Gowardman J, Playford EG, Rickard CM. Risk factors for peripheral intravenous catheter failure: a multivariate analysis of data from a randomized controlled trial. Infect Control Hosp Epidemiol. 2014 Jan;35(1):63-8. doi: 10.1086/674398. Epub 2013 Dec 2. PMID: 24334800.
- Wei T, Li XY, Yue ZP, Chen YY, Wang YR, Yuan Z, Lin Q, Tan Y, Peng SY, Li XF. Catheter dwell time and risk of catheter failure in adult patients with peripheral venous catheters. J Clin Nurs. 2019 Dec;28(23-24):4488-4495. doi: 10.1111/jocn.15035. Epub 2019 Sep 15. PMID: 31410906.
- Yasuda H, Rickard CM, Marsh N, Yamamoto R, Kotani Y, Kishihara Y, Kondo N, Sekine K, Shime N, Morikane K, Abe T; AMOR-NUS study group. Risk factors for peripheral intravascular catheter-related phlebitis in critically ill patients: analysis of 3429 catheters from 23 Japanese intensive care units. Ann Intensive Care. 2022 Apr 8;12(1):33. doi: 10.1186/s13613-022-01009-5. PMID: 35394571; PMCID: PMC8994002.
- Zhu A, Wang T, Wen S. Peripheral intravenous catheters in situ for more than 96 h in adults: What factors affect removal? Int J Nurs Pract. 2016 Dec;22(6):529-537. doi: 10.1111/ijn.12492. Epub 2016 Oct 10. PMID: 27723177.
- •Overig
- Drugeon B, Guenezan J, Pichon M, Devos A, Fouassin X, Neveu A, Boinot L, Pratt V, Mimoz O. Incidence, complications, and costs of peripheral venous catheter-related bacteraemia: a retrospective, single-centre study. J Hosp Infect. 2023 May;135:67-73. doi: 10.1016/j.jhin.2023.02.012. Epub 2023 Mar 12. PMID: 36918069.
- Harbour R, Miller J. A new system for grading recommendations in evidence based guidelines. BMJ. 2001 Aug 11;323(7308):334-6. doi: 10.1136/bmj.323.7308.334. PMID: 11498496; PMCID: PMC1120936.
- Kaplan A, Korkut S, Avsarogullari OL. Comparison of procedure-related pain and patient satisfaction according to catheter size and insertion site in peripheral intravenous catheterization. J Vasc Access. 2023 Aug 3:11297298231190250. doi: 10.1177/11297298231190250. Epub ahead of print. PMID: 37537996.
- Maki DG, Kluger DM, Crnich CJ. The risk of bloodstream infection in adults with different intravascular devices: a systematic review of 200 published prospective studies. Mayo Clin Proc. 2006 Sep;81(9):1159-71. doi: 10.4065/81.9.1159. PMID: 16970212.
- Mermel LA, Allon M, Bouza E, Craven DE, Flynn P, O'Grady NP, Raad II, Rijnders BJ, Sherertz RJ, Warren DK. Clinical practice guidelines for the diagnosis and management of intravascular catheter-related infection: 2009 Update by the Infectious Diseases Society of America. Clin Infect Dis. 2009 Jul 1;49(1):1-45. doi: 10.1086/599376. Erratum in: Clin Infect Dis. 2010 Apr 1;50(7):1079. Dosage error in article text. Erratum in: Clin Infect Dis. 2010 Feb 1;50(3):457. PMID: 19489710; PMCID: PMC4039170.
- O'Grady NP, Alexander M, Burns LA, Dellinger EP, Garland J, Heard SO, Lipsett PA, Masur H, Mermel LA, Pearson ML, Raad II, Randolph AG, Rupp ME, Saint S; Healthcare Infection Control Practices Advisory Committee (HICPAC). Guidelines for the prevention of intravascular catheter-related infections. Clin Infect Dis. 2011 May;52(9):e162-93. doi: 10.1093/cid/cir257. Epub 2011 Apr 1. PMID: 21460264; PMCID: PMC3106269.
- O'Grady NP, Alexander M, Burns LA, Dellinger EP, Garland J, Heard SO, Lipsett PA, Masur H, Mermel LA, Pearson ML, Raad II, Randolph AG, Rupp ME, Saint S; Healthcare Infection Control Practices Advisory Committee (HICPAC). Guidelines for the prevention of intravascular catheter-related infections, 2011. Update 2017. 2017. (https://www.cdc.gov/infection-control/media/pdfs/Guideline-BSI-H.pdf, accessed November 1, 2024).
- Stang A. Critical evaluation of the Newcastle-Ottawa scale for the assessment of the quality of nonrandomized studies in meta-analyses. Eur J Epidemiol. 2010 Sep;25(9):603-5. doi: 10.1007/s10654-010-9491-z. Epub 2010 Jul 22. PMID: 20652370.
- van Loon FH, Puijn LA, van Aarle WH, Dierick-van Daele AT, Bouwman AR. Pain upon inserting a peripheral intravenous catheter: Size does not matter. J Vasc Access. 2018 May;19(3):258-265. doi: 10.1177/1129729817747531. Epub 2018 Mar 4. PMID: 29772984.
- Wong WC, Cheung CS, Hart GJ. Development of a quality assessment tool for systematic reviews of observational studies (QATSO) of HIV prevalence in men having sex with men and associated risk behaviours. Emerg Themes Epidemiol. 2008 Nov 17;5:23. doi: 10.1186/1742-7622-5-23. PMID: 19014686; PMCID: PMC2603000.
- No authors listed. 2021 Infusion Therapy Standards of Practice Updates. J Infus Nurs. 2021 Jul-Aug 01;44(4):189-190. doi: 10.1097/NAN.0000000000000436. PMID: 34197345.
- No authors listed. Guidelines for the prevention of bloodstream infections and other infections associated with the use of intravascular catheters: Part 1: peripheral catheters [Internet]. Geneva: World Health Organization; 2024. PMID: 38810002.
|
Author, year Country Single- or multicenter
|
Catheter insertion site
|
N patients (baseline); catheters; catheter days Population Ward / procedure Follow-up |
Outcomes |
Remarks
|
|
|
Studies included in SRs (Comparcini, 2017; Fan, 2022) – observational studies |
|||||
|
Bregenzer, 1998
Switzerland
Single-center |
Back of hand Forearm
|
T: 451; 665*; NR
Adults
Medical ward ICU
Until catheter removal
* No outcome data available: 56 |
Phlebitis7 |
Unit of analysis: catheters |
|
|
Buzatto, 2016
Brazil
Single-center |
Back of hand Forearm Upper arm |
T: 102; 102; NR
Adults
CCU / receiving amiodarone MCU / receiving amiodarone
NR |
Phlebitis2 |
- |
|
|
Carr, 2018
Australia
Multicenter |
Back of hand Wrist Forearm Antecubital fossa Upper arm |
T: 391; 391; NR
Adults
ED
Until catheter removal |
Catheter failure |
Enrolment dependent on day of the week and hour of the day |
|
|
Chen, 2022
China
Multicenter |
Back of hand Wrist Forearm Antecubital fossa
|
T: 5,345; 5,345; NR
Adults
Medical ward Surgical ward Obstetric and gynecology ward ED
Until catheter removal |
Catheter failure |
- |
|
|
Cicolini, 2009
Italy
Single-center |
Back of hand Forearm Antecubital fossa |
T: 427; 427; NR
Adults
Medical ward Surgical ward
12-96 hours (until removal) |
Thrombophlebitis3 |
- |
|
|
Cicolini, 2014
Italy
Multicenter |
Back of hand Forearm Antecubital fossa |
T: 1,498; 1,498; NR
Adults
Medical ward Surgical ward
Until 96 hours after insertion |
Phlebitis2 |
Multivariable analysis not considered |
|
|
Erdogan, 2016
Turkey
Single-center |
Back of hand Wrist Forearm Antecubital fossa |
T: 325; 347; NR
Adults
Neurosurgery ward
Until 24 hours after catheter removal |
Phlebitis2 |
Unit of analysis: catheters |
|
|
Karadeniz, 2003
Turkey
Single-center |
Back of hand Wrist Forearm Antecubital fossa
|
T: 58; 58; NR
Adults
NR
Cross-sectional data |
Phlebitis8 |
- |
|
|
Kaur, 2011
India
Single-center |
Back of hand Wrist Forearm
|
T: 349*; 230; NR
Adults
ED
Until catheter removal
* Excluded for early catheter removal: 149 |
Phlebitis5 |
Unit of analysis: catheter |
|
|
Liu, 2022
China
Single-center |
Back of hand Wrist Forearm Antecubital fossa |
T: 1,069; 1,069; NR
Adults
Medical ward Surgical ward
Until catheter removal |
CRBSI Insertion site infection Phlebitis2 |
- |
|
|
Lulie, 2021
Ethiopia
Single-center |
Back of hand Forearm Antecubital fossa |
T: 384; 384; NR
Adults
ED Medical ward Surgical ward
Until catheter removal |
Phlebitis4 |
- |
|
|
Maki, 1991
United States
Single-center |
Back of hand Wrist Forearm |
T: 714; 1,054; NR
Adults
All wards, patients with granulocytopenia
Until 3 days after catheter removal |
Phlebitis6 |
Post-hoc analysis of RCT on the effect of catheter material
Unit of analysis: catheter
|
|
|
Rego Furtado, 2011 A
Portugal (Azores)
Single-center |
Back of hand Wrist Forearm Antecubital fossa Arm |
T: 186; 186; NR
Adults
General surgery ward
Cross-sectional data |
Phlebitis5 |
- |
|
|
Rego Furtado, 2011 B
Portugal (Azores)
Single-center |
Back of hand Wrist Forearm Antecubital fossa Arm |
T: 171; 286; NR
Adults
General surgery ward
Until catheter removal |
Phlebitis5 |
Unit of analysis: catheter |
|
|
Saini, 2011
India
Single-center |
Back of hand Forearm |
T: 168; 168; NR
Adults
ED
Until catheter removal |
Phlebitis5 |
Each day the first five patients admitted were enrolled |
|
|
Simin, 2019
Serbia
Single-center |
Back of hand Wrist Forearm Antecubital fossa Lower limb |
T: 368; 1,428*; NR
Adults
Infectious disease wards
Until catheter removal
* Missing outcome data: 6 |
Phlebitis4 |
Unit of analysis: catheter |
|
|
Singh, 2008
Nepal
Single-center |
Back of hand Forearm Antecubital fossa |
T: 230; 230; NR
Adults
ICU Medical ward Surgical ward Obstetrics/gynecology ward
Until discharge or 2 days after catheter removal |
Phlebitis5 |
- |
|
|
Urbanetto, 2017
Brazil
Single-center |
Back of hand Wrist Forearm Antecubital fossa Upper arm Lower limb |
T: 165; 447; NR
Adults
Medical ward Surgical ward
Until 96 hours after catheter removal |
Phlebitis1 |
Unit of analysis: catheters |
|
|
Uslusoy, 2008
Turkey
Single-center |
Back of Hand Wrist Forearm Antecubital fossa |
T: 355; 568; NR
Adults
General surgery ward
Until 48 hours after catheter removal |
Phlebitis2 |
Unit of analysis: catheters |
|
|
Wallis, 2014
Australia
Multicenter |
Back of hand Wrist Forearm Antecubital fossa Upper arm |
T: 3,283; 5,907; NR
Adults
Medical ward Surgical ward
NR |
Phlebitis6 |
Post-hoc analysis of RCT on the effect of different regimens of catheter replacement
Unit of analysis: catheters |
|
|
Wei, 2019
China
Multicenter |
Back of hand Forearm |
T: 1,509*; 1,509; NR
Adults
All wards
Until catheter removal
* Incomplete outcome data: 32 |
Catheter failure |
- |
|
|
Zhu, 2016
China
Single-center |
Back of hand Wrist Forearm Antecubital fossa Lower limb |
T: 209*; 209; NR
Adults
ED
Cross-sectional data
* Incomplete outcome data: 20 |
Catheter failure |
- |
|
|
Additional studies – randomized controlled trials |
|||||
|
Tan, 2016
Japan
Single-center |
Back of hand Forearm
|
T: 307; 307; NR
Adults
Delivery suite and postnatal ward
Until removal |
Insertion failure |
‘- |
|
|
Additional studies – observational studies |
|||||
|
Carr, 2016
Australia
Single-center |
Back of hand Forearm Antecubital fossa |
T: NR; 734*; NA
Adults
ED
NA (insertion failure)
* Not included for analysis: 294 |
Insertion failure |
- |
|
|
Kache, 2022
United States
Single-center |
Back of hand Wrist Forearm Antecubital fossa |
T: 47,766*; 91,301**; NR
Adults
All wards
NR
* Excluded for incomplete data: 2,017 * Excluded for incomplete data: 2,130 |
Phlebitis1 |
Exclusion of patients with incomplete exposure or confounding data
Unit of analysis: catheters |
|
|
Marsh, 2021
Australia
Multicenter |
Back of hand Wrist Forearm Antecubital fossa Upper arm Lower limb |
T: 8,197; 11,839; NR
Adults and children
All wards
Until catheter removal |
Phlebitis9 Catheter failure |
Secondary analysis of 12 prospective studies
Unit of analysis: catheters |
|
|
Pérez-Granda, 2024
Spain
Single-center |
Forearm Upper arm |
T: 344; 475; NR
Adults
Geriatric ward
Until discharge |
Phlebitis10 |
Before-after study
Unit of analysis: catheters |
|
|
Petroski, 2015
United States
Single-center |
Back of hand Wrist Forearm Antecubital fossa Lower limb |
T: 652*; 652; NA
Children (<18 years)
ED
NA (difficult venous access)
* Exposure data not available: no insertion failure: 201; insertion failure: 21 |
Difficult venous access
|
-
|
|
|
Rodriguez-Calero, 2020
Spain
Multicenter |
Back of hand Forearm Antecubital fossa |
T: 2,686*; 2,686; NR
Adults
All wards
NA (difficult venous access)
* Excluded for incomplete data: 24 |
Difficult venous access
|
Case-control study |
|
|
Shimoni, 2023
Israel
Single-center |
Back of hand Forearm Antecubital fossa |
T: 500*; 709; 2,467
Adults
Medical ward
NR
* No data reported: 1 |
Catheter failure |
Unit of analysis: catheters |
|
|
Simões, 2022
Brazil
Single-center |
Back of hand Wrist Forearm Antecubital fossa Lower limb |
T: 1,319*; 1,319; NR
Adults
Medical ward Surgical ward ICU OR
NR
* Missing data on exposure: 3 |
Phlebitis2 |
Post-hoc analysis of RCT on catheter replacement |
|
|
Yasuda, 2022
Japan
Multicenter |
Back of hand Wrist Forearm Antecubital fossa Upper arm Lower limb |
T: 1,359; 3,429; NR
Adults
ICU
NR |
Phlebitis2 |
Post-hoc analysis of RCT on catheter replacement |
|
CCU = coronary care unit; ED = emergency department; ICU = intensive care unit; MCU = medium care unit; NA = not applicable; NR = not reported; OR = operating room; RCT = randomized controlled trial; SR = systematic review; T = total number
1 Criteria were not reported
2 Infusion Nurses Society (INS) phlebitis scale
3 Lundgren checklist
4 Visual infusion phlebitis scale (Jackson/Gallant, 2006)
5 Jackson standard visual phlebitis scale (1998)
6 At least two of: pain and/or tenderness, erythema, swelling, purulent discharge, palpable venous cord
7 At least two of: redness, swelling, palpable venous cord, tenderness, pain
8 At least one of: pain, red spots, sensitivity near the catheter area, harness along the vein, swelling
9 From medical record (criteria unknown) or two or more of: pain or tenderness, redness, swelling, palpable cord, purulence
10 At least one of: redness, swelling, tenderness, inflammation
Based on Cochrane risk of bias tool and suggestions by the CLARITY Group at McMaster University)
Randomized controlled trials
|
Author, year |
Random sequence generation
Was the allocation sequence adequately generated? |
Allocation concealment
Was the allocation adequately concealed? |
Blinding
Was knowledge of the allocated interventions adequately prevented?
Were patients, healthcare providers, data collectors, outcome assessors, data analysts blinded? |
Incomplete outcome data
Was loss to follow-up (missing outcome data) infrequent? |
Selective outcome reporting
Are reports of the study free of selective outcome reporting? |
Other bias
Was the study apparently free of other problems that could put it at a risk of bias? |
Overall risk of bias
|
|
Tan, 2016 |
Definitely yesA1
|
Probably yesB1
|
Definitely noC1
|
Probably yesD1
|
Probably yesE1
|
Probably yesF1, F2 |
High (all outcomes) |
A1 Randomization using computer-generated random numbers
B1 Randomization using sealed envelopes prepared by an employee not involved in enrolment, but sealing and opacity not reported
C1 Blinding of patients, clinicians or outcome assessors not feasible; blinding of data analysts was not reported
D1 No or infrequent missing outcome data (<5%)
E1 All outcomes described in the Methods section were reported
F1 Funding by industry or conflict of interest were not reported
F2 Follow-up was adequate
Observational studies
|
Author, year |
Selection of participants
Was selection of exposed and non-exposed cohorts drawn from the same population? |
Exposure
Can we be confident in the assessment of exposure? |
Outcome of interest
Can we be confident that the outcome of interest was not present at start of study? |
Confounding-assessment
Can we be confident in the assessment of confounding factors? |
Confounding-analysis
Did the study match exposed and unexposed for all variables that are associated with the outcome of interest or did the statistical analysis adjust for these confounding variables? |
Assessment of outcome
Can we be confident in the assessment of outcome? |
Follow-up
Was the follow up of cohorts adequate? In particular, was an outcome data complete or imputed?
|
Co-interventions
Were co-interventions similar between groups? |
Other bias
Was the study apparently free of other problems that could put it at a risk of bias? |
Overall risk of bias
|
|
Bregenzer, 1998 |
Definitely yesA1 |
Definitely yesB1 |
Definitely noC6 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF3 |
Definitely noG2,6 |
Probably yesH1 |
Definitely noI2,4,5 |
High (all outcomes) |
|
Buzatto, 2016 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Probably noG5 |
Probably yesH1 |
Definitely noI2,5 |
High (all outcomes) |
|
Carr, 2016 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC3 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF4 |
Definitely noG2,6 |
Probably yesH1 |
Definitely noI3,5 |
High (all outcomes) |
|
Carr, 2018 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI3,5,6 |
High (all outcomes) |
|
Chen, 2022 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC2 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Cicolini, 2009 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Cicolini, 2014 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Erdogan, 2016 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,4,5 |
High (all outcomes) |
|
Kache, 2022 |
Definitely yesA1 |
Probably noB4 |
Definitely noC6 |
Probably noD4 |
Definitely noE2 |
Definitely noF1 |
ProbablyG1,3 |
Probably yesH1 |
Definitely noI1,4,5,8 |
High (all outcomes) |
|
Karadeniz, 2003 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF3 |
Definitely noG1,4 |
Probably yesH1 |
Definitely noI2,5 |
High (all outcomes) |
|
Kaur, 2011 |
Definitely yesA1 |
Definitely yesB1 |
Definitely noC6 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely noG2,6 |
Probably yesH1 |
Definitely noI2,4,5 |
High (all outcomes) |
|
Liu, 2022 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC1 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Lulie, 2021 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Maki, 2009 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI3,4,5 |
High (all outcomes) |
|
Marsh, 2021 |
Definitely yesA1 |
Probably yesB3 |
Probably yesC5 |
Probably yesD3 |
Definitely yesE1 |
Definitely noF1 |
Probably yesG2,3 |
Probably noH2 |
Definitely noI3,4,5 |
High (all outcomes) |
|
Pérez-Granda, 2024 |
Definitely noA2 |
Definitely yesB1 |
Definitely noC6 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably noH2 |
Definitely noI1,4,5 |
High (all outcomes) |
|
Petroski, 2015 |
Definitely yesA1 |
Definitely noB5 |
Probably yesC2 |
Definitely noD5 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Rego Furtado, 2011 A |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely noG1,4 |
Probably yesH1 |
Definitely noI2,5 |
High (all outcomes) |
|
Rego Furtado, 2011 B |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC2 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,4,5 |
High (all outcomes) |
|
Rodriguez-Calero, 2020 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC3 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Saini, 2011 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI2,5,7 |
High (all outcomes) |
|
Shimoni, 2023 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,3 |
Probably yesH1 |
Definitely noI1,4,5 |
High (all outcomes) |
|
Simin, 2019 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC2 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,4,5 |
High (all outcomes) |
|
Simões, 2022 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,3 |
Probably noH2 |
Definitely noI2,5 |
High (all outcomes) |
|
Singh, 2008 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC2 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI2,5 |
High (all outcomes) |
|
Urbanetto, 2017 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI2,4,5 |
High (all outcomes) |
|
Uslusoy, 2008 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC5 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI2,4,5 |
High (all outcomes) |
|
Wallis, 2014 |
Definitely yesA1 |
Definitely yesB1 |
Definitely noC6 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF1 |
Probably yesG1,3 |
Probably yesH1 |
Definitely noI3,4,5 |
High (all outcomes) |
|
Wei, 2019 |
Definitely yesA1 |
Definitely yesB1 |
Definitely yesC1 |
Definitely yesD1 |
Definitely noE2 |
Definitely noF1 |
Definitely yesG1,2 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Yasuda, 2022 |
Definitely yesA1 |
Definitely yesB1 |
Probably yesC4 |
Definitely yesD1 |
Definitely yesE1 |
Definitely noF2 |
Probably yesG1,3 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
|
Zhu, 2016 |
Definitely yesA1 |
Probably yesB2 |
Probably yesC4 |
Probably yesD2 |
Definitely yesE1 |
Definitely noF1 |
Definitely noG4,6 |
Probably yesH1 |
Definitely noI1,5 |
High (all outcomes) |
A1 Patients were selected from the same population within the same time frame
A2 Patients were selected from different time frame
B1 Structured data collection
B2 Review of medical record
B3 Structured data collection in combination with review of medical record
B4 Exclusion of patients with incomplete exposure data (<5%)
B5 Exposure data were not available for a substantial part of the cohort
C1 Patients with previous PVC or damaged skin at the insertion site were excluded
C2 Presence of the outcome at PVC insertion was excluded
C3 Presence of the outcome (first attempt insertion failure/difficult venous access) at insertion was not possible
C4 Patients enrolled required a (new) peripheral venous catheter, but presence of the outcome at PVC insertion was not reported as exclusion criterium
C5 Presence of the outcome at PVC insertion was not reported as exclusion criterium
C6 Patients could be enrolled more than once
D1 Structured data collection
D2 Review of medical and nursing notes (reproducibility not reported)
D3 Structured data collection in combination with review of medical record
D4 Exclusion of patients with incomplete confounding data (<5%)
D5 Missing data on confounding variables was reported (>5%)
E1 Results were adjusted for confounding variables
E2 No adjustment for confounding variables
F1 Blinding of outcome assessment was not reported, but blinding was considered not feasible
F2 Blinding of outcome assessment was reported for the primary RCT, but blinding was considered not feasible for the comparison of insertion sites
F3 Outcome assessment was not blinded
F4 Outcome data were self-reported
G1 No or infrequent (<5%) missing outcome data were reported
G2 Follow-up was adequate
G3 Follow-up was not reported
G4 Cross-sectional data
G5 No event was assumed for patients transferred to other ward
G6 Frequent (>=5%) missing outcome data
H1 No co-interventions were reported
H2 Co-interventions were reported, but the distribution between groups was not reported
I1 No funding by industry or conflict of interest was reported
I2 Funding by industry and conflict of interest were not reported
I3 Funding by industry
I4 Catheters were used as unit of analysis
I5 Potential confounding by indication
I6 Enrolment was dependent on day of the week and hour of the day
I7 Each day the first five patients admitted were enrolled
I8 Exclusion of patients with incomplete exposure and/or confounding data
Tables of excluded studies
Systematic search – full text assessment
|
Reference |
Reason for exclusion |
|
Abolfotouh MA, Salam M, Bani-Mustafa A, White D, Balkhy HH. Prospective study of incidence and predictors of peripheral intravenous catheter-induced complications. Ther Clin Risk Manag. 2014 Dec 8;10:993-1001. doi: 10.2147/TCRM.S74685. PMID: 25525365; PMCID: PMC4266329. |
I/C didn’t meet PICOS |
|
Abusafia BM, Boztepe H. Evaluation of Peripheral Intravenous Catheter-Induced Local Complications in Pediatrics. J Clin Nurs. 2017 Jan 19. doi: 10.1111/jocn.13730. Epub ahead of print. PMID: 28102920. |
Retracted |
|
Benaya A, Schwartz Y, Kory R, Yinnon AM, Ben-Chetrit E. Relative incidence of phlebitis associated with peripheral intravenous catheters in the lower versus upper extremities. Eur J Clin Microbiol Infect Dis. 2015 May;34(5):913-6. doi: 10.1007/s10096-014-2304-7. Epub 2015 Jan 7. PMID: 25563209. |
I/C didn’t meet PICOS |
|
Birhane E, Kidanu K, Kassa M, Gerezgiher D, Tsegay L, Weldu B, Kidane G, Gerensea H. Lifespan and associated factors of peripheral intravenous Cannula among infants admitted in public hospitals of Mekelle City, Tigray, Ethiopia, 2016. BMC Nurs. 2017 Jun 15;16:33. doi: 10.1186/s12912-017-0227-1. PMID: 28638278; PMCID: PMC5472887. |
Relevant outcome data were not reported by patient type (neonate/infant) |
|
Buetti N, Abbas M, Pittet D, Chraiti MN, Sauvan V, De Kraker MEA, Boisson M, Teixeira D, Zingg W, Harbarth S. Lower risk of peripheral venous catheter-related bloodstream infection by hand insertion. Antimicrob Resist Infect Control. 2022 Jun 3;11(1):80. doi: 10.1186/s13756-022-01117-8. PMID: 35659775; PMCID: PMC9164319. |
I/C didn’t meet PICOS |
|
Chang WP, Peng YX. Occurrence of Phlebitis: A Systematic Review and Meta-analysis. Nurs Res. 2018 May/Jun;67(3):252-260. doi: 10.1097/NNR.0000000000000279. PMID: 29698331. |
Selection criteria for systematic reviews were not fulfilled |
|
Cornely OA, Bethe U, Pauls R, Waldschmidt D. Peripheral Teflon catheters: factors determining incidence of phlebitis and duration of cannulation. Infect Control Hosp Epidemiol. 2002 May;23(5):249-53. doi: 10.1086/502044. PMID: 12026149. |
Relevant outcome data were not reported by insertion site |
|
de Lima Jacinto AK, Avelar AF, Pedreira ML. Predisposing factors for infiltration in children submitted to peripheral venous catheterization. J Infus Nurs. 2011 Nov-Dec;34(6):391-8. doi: 10.1097/NAN.0b013e3182306491. PMID: 22101633. |
O didn’t meet PICOS |
|
Juhlin D, Hammarskjöld F, Mernelius S, Taxbro K, Berg S. Microbiological colonization of peripheral venous catheters: a prospective observational study in a Swedish county hospital. Infect Prev Pract. 2021 Jun 7;3(3):100152. doi: 10.1016/j.infpip.2021.100152. PMID: 34458717; PMCID: PMC8379694. |
O didn’t meet PICOS |
|
Kaplan A, Korkut S, Avsarogullari OL. Comparison of procedure-related pain and patient satisfaction according to catheter size and insertion site in peripheral intravenous catheterization. J Vasc Access. 2023 Aug 3:11297298231190250. doi: 10.1177/11297298231190250. Epub ahead of print. PMID: 37537996. |
O didn’t meet PICOS |
|
Karaoğlan N, Sarı HY, Devrim İ. Complications of peripheral intravenous catheters and risk factors for infiltration and phlebitis in children. Br J Nurs. 2022 Apr 21;31(8):S14-S23. doi: 10.12968/bjon.2022.31.8.S14. PMID: 35439080. |
I/C didn’t meet PICOS |
|
Kishihara Y, Yasuda H, Moriya T, Kashiura M, Koike M, Kotani Y, Kondo N, Sekine K, Shime N, Morikane K, Abe T. A study of the risk factors for phlebitis in patients stratified using the acute physiology and chronic health evaluation II score and admitted to the intensive care unit: A post hoc analysis of the AMOR-VENUS study. Front Med (Lausanne). 2022 Dec 5;9:965706. doi: 10.3389/fmed.2022.965706. PMID: 36544499; PMCID: PMC9760669. |
Relevant outcome data were not reported for the overall study population |
|
Kollar C. Optimizing the Effectiveness of Short Peripheral Catheters. J Infus Nurs. 2021 May-Jun 01;44(3):163-175. doi: 10.1097/NAN.0000000000000426. PMID: 33935251. |
Relevant outcome data were not reported by insertion site |
|
Lee WL, Liao SF, Lee WC, Huang CH, Fang CT. Soft tissue infections related to peripheral intravenous catheters in hospitalised patients: a case-control study. J Hosp Infect. 2010 Oct;76(2):124-9. doi: 10.1016/j.jhin.2010.05.012. Epub 2010 Jul 8. PMID: 20619497. |
I/C didn’t meet PICOS |
|
Lee SU, Jung JY, Ham EM, Wang SW, Park JW, Hwang S, Kim DK, Kwak YH. Factors associated with difficult intravenous access in the pediatric emergency department. J Vasc Access. 2020 Mar;21(2):180-185. doi: 10.1177/1129729819865709. Epub 2019 Aug 3. PMID: 31379251. |
I/C didn’t meet PICOS |
|
Li HM, Wan LL, Jin CX, Zhang GY, Yang H, Zhang XY. Risk factors of peripheral venous catheter-related complication and infection in children with bronchopneumonia. BMC Infect Dis. 2023 Sep 15;23(1):603. doi: 10.1186/s12879-023-08540-1. PMID: 37715150; PMCID: PMC10503115. |
I/C didn’t meet PICOS |
|
Lundberg JD, Crawford BS, Phillips G, Berger MJ, Wesolowski R. Incidence of infusion-site reactions associated with peripheral intravenous administration of fosaprepitant. Support Care Cancer. 2014 Jun;22(6):1461-6. doi: 10.1007/s00520-013-2106-y. Epub 2014 Jan 9. PMID: 24402412; PMCID: PMC4277851. |
O didn’t meet PICOS |
|
Malyon L, Ullman AJ, Phillips N, Young J, Kleidon T, Murfield J, Rickard CM. Peripheral intravenous catheter duration and failure in paediatric acute care: A prospective cohort study. Emerg Med Australas. 2014 Dec;26(6):602-8. doi: 10.1111/1742-6723.12305. Epub 2014 Oct 23. PMID: 25346034. |
I/C didn’t meet PICOS |
|
Marsh N, Webster J, Larson E, Cooke M, Mihala G, Rickard CM. Observational Study of Peripheral Intravenous Catheter Outcomes in Adult Hospitalized Patients: A Multivariable Analysis of Peripheral Intravenous Catheter Failure. J Hosp Med. 2018 Feb 1;13(2):83-89. doi: 10.12788/jhm.2867. Epub 2017 Oct 18. PMID: 29073316. |
Data included in Marsh (2021) |
|
Mermel LA. Prevention of intravascular catheter-related infections. Ann Intern Med. 2000 Mar 7;132(5):391-402. doi: 10.7326/0003-4819-132-5-200003070-00009. Erratum in: Ann Intern Med 2000 Sep 5;133(5):395. PMID: 10691590. |
Narrative review |
|
Murayama R, Abe-Doi M, Masamoto Y, Kashiwabara K, Komiyama C, Sanada H, Kurokawa M. Verification study on the catheterization of an upper arm vein using the new long peripheral intravenous catheter to reduce catheter failure incidence: A randomized controlled trial. Drug Discov Ther. 2023 Mar 11;17(1):52-59. doi: 10.5582/ddt.2022.01108. Epub 2023 Feb 28. PMID: 36858623. |
I/C didn’t meet PICOS |
|
Sabri A, Szalas J, Holmes KS, Labib L, Mussivand T. Failed attempts and improvement strategies in peripheral intravenous catheterization. Biomed Mater Eng. 2013;23(1-2):93-108. doi: 10.3233/BME-120735. PMID: 23442240. |
Selection criteria for systematic reviews were not fulfilled |
|
Resnick O, Abu Ahmad W, Bancovsky D, Rogachev S, Ashash A, Ohana Sarna Cahan L, Rekhtman D, Hashavya S, Gross I. Predicting factors for complications in peripheral intravenous catheters in the pediatric population. Acta Paediatr. 2021 May;110(5):1639-1644. doi: 10.1111/apa.15687. Epub 2020 Dec 2. PMID: 33226669. |
P didn’t meet PICOS I/C didn't meet PICOS Reported outcome data not suitable for data extraction |
|
Rickard CM, Larsen E, Walker RM, Mihala G, Byrnes J, Saiyed M, Cooke M, Finucane J, Carr PJ, Marsh N. Integrated versus nonintegrated peripheral intravenous catheter in hospitalized adults (OPTIMUM): A randomized controlled trial. J Hosp Med. 2023 Jan;18(1):21-32. doi: 10.1002/jhm.12995. Epub 2022 Nov 13. PMID: 36372995; PMCID: PMC10099685. |
Relevant outcome data were not reported by insertion site |
|
Shenoy S, Karunakar BP. Factors influencing the peripheral venous catheter survival in critically ill children in a pediatric intensive care unit. Indian J Pediatr. 2014 Dec;81(12):1293-6. doi: 10.1007/s12098-014-1430-7. Epub 2014 May 6. PMID: 24796410. |
Relevant outcome data were not reported by insertion site |
|
Stuart RL, Cameron DR, Scott C, Kotsanas D, Grayson ML, Korman TM, Gillespie EE, Johnson PD. Peripheral intravenous catheter-associated Staphylococcus aureus bacteraemia: more than 5 years of prospective data from two tertiary health services. Med J Aust. 2013 Jun 3;198(10):551-3. doi: 10.5694/mja12.11699. PMID: 23725270. |
I/C didn’t meet PICOS |
|
Subha Rao SD, Joseph MP, Lavi R, Macaden R. Infections related to vascular catheters in a pediatric intensive care unit. Indian Pediatr. 2005 Jul;42(7):667-72. PMID: 16085967. |
I/C didn’t meet PICOS |
|
Suliman M, Saleh W, Al-Shiekh H, Taan W, AlBashtawy M. The Incidence of Peripheral Intravenous Catheter Phlebitis and Risk Factors among Pediatric Patients. J Pediatr Nurs. 2020 Jan-Feb;50:89-93. doi: 10.1016/j.pedn.2019.11.006. Epub 2019 Nov 27. PMID: 31785409. |
P didn't meet PICOS I/C didn't meet PICOS |
|
Sweeny A, Archer-Jones A, Watkins S, Johnson L, Gunter A, Rickard C. The experience of patients at high risk of difficult peripheral intravenous cannulation: An Australian prospective observational study. Australas Emerg Care. 2022 Jun;25(2):140-146. doi: 10.1016/j.auec.2021.07.003. Epub 2021 Aug 27. PMID: 34456181. |
O didn’t meet PICOS |
|
Takahashi T, Murayama R, Abe-Doi M, Miyahara M, Kanno C, Nakagami G, Sanada H. Catheter failure in the administration of hyperosmotic drugs through a peripheral vein and vascular selection: A retrospective cohort study. Drug Discov Ther. 2021 Nov 21;15(5):236-240. doi: 10.5582/ddt.2021.01080. Epub 2021 Oct 29. PMID: 34719604. |
I/C didn’t meet PICOS |
|
Trinh TT, Chan PA, Edwards O, Hollenbeck B, Huang B, Burdick N, Jefferson JA, Mermel LA. Peripheral venous catheter-related Staphylococcus aureus bacteremia. Infect Control Hosp Epidemiol. 2011 Jun;32(6):579-83. doi: 10.1086/660099. Erratum in: Infect Control Hosp Epidemiol. 2011 Jul;32(7):735. PMID: 21558770. |
Non-comparative study |
|
Tripathi S, Gladfelter T. Peripheral intravenous catheters in hospitalized patients: Practice, Dwell times, and factors impacting the dwell times: A single center retrospective study. J Vasc Access. 2022 Jul;23(4):581-588. doi: 10.1177/11297298211000874. Epub 2021 Mar 30. PMID: 33784876.. |
P didn't meet PICOS
|
|
Ullman AJ, Takashima M, Kleidon T, Ray-Barruel G, Alexandrou E, Rickard CM. Global Pediatric Peripheral Intravenous Catheter Practice and Performance: A Secondary Analysis of 4206 Catheters. J Pediatr Nurs. 2020 Jan-Feb;50:e18-e25. doi: 10.1016/j.pedn.2019.09.023. Epub 2019 Oct 21. PMID: 31648879. |
O didn’t meet PICOS |
|
Wienbeck S, Fischbach R, Kloska SP, Seidensticker P, Osada N, Heindel W, Juergens KU. Prospective study of access site complications of automated contrast injection with peripheral venous access in MDCT. AJR Am J Roentgenol. 2010 Oct;195(4):825-9. doi: 10.2214/AJR.09.3739. PMID: 20858804. |
O didn’t meet PICOS |
|
No authors listed. Comparing short peripheral cannula insertion sites. Nursing. 2008 May;38(5):60. doi: 10.1097/01.NURSE.0000317692.52600.d0. PMID: 18431212. |
Educational note |
C = comparator; I = intervention; O = outcome; P = population; S = setting.
In- and excluded systematic reviews – reference lists
|
Reference |
Reason for exclusion |
|
Fernández-García C, Mata-Peón E, Avanzas-Fernández S. Related factors with extravasation of non-cytostatic agents in peripheral vein catheters. Enferm Clin. 2017 Mar-Apr;27(2):71-78. English, Spanish. doi: 10.1016/j.enfcli.2016.09.007. Epub 2016 Nov 16. PMID: 27865648. |
Foreign language (Spanish) |
|
Göransson KE, Johansson E. Prehospital peripheral venous catheters: a prospective study of patient complications. J Vasc Access. 2012 Jan-Mar;13(1):16-21. doi: 10.5301/JVA.2011.8418. PMID: 21725949. |
S didn’t meet PICOS |
|
Jacobson AF, Winslow EH. Variables influencing intravenous catheter insertion difficulty and failure: an analysis of 339 intravenous catheter insertions. Heart Lung. 2005 Sep-Oct;34(5):345-59. doi: 10.1016/j.hrtlng.2005.04.002. PMID: 16157191. |
Relevant outcome data were not reported by insertion site |
|
Lapostolle F, Catineau J, Garrigue B, Monmarteau V, Houssaye T, Vecci I, Tréoux V, Hospital B, Crocheton N, Adnet F. Prospective evaluation of peripheral venous access difficulty in emergency care. Intensive Care Med. 2007 Aug;33(8):1452-7. doi: 10.1007/s00134-007-0634-y. Epub 2007 Jun 7. PMID: 17554524. |
S didn’t meet PICOS |
|
Lee WL, Chen HL, Tsai TY, Lai IC, Chang WC, Huang CH, Fang CT. Risk factors for peripheral intravenous catheter infection in hospitalized patients: a prospective study of 3165 patients. Am J Infect Control. 2009 Oct;37(8):683-6. doi: 10.1016/j.ajic.2009.02.009. Epub 2009 Jun 25. PMID: 19559502. |
O didn’t meet PICOS |
|
Lee S, Kim K, Kim JS. A Model of Phlebitis Associated with Peripheral Intravenous Catheters in Orthopedic Inpatients. Int J Environ Res Public Health. 2019 Sep 14;16(18):3412. doi: 10.3390/ijerph16183412. PMID: 31540024; PMCID: PMC6765841. |
I/C didn’t meet PICOS |
C = comparator; I = intervention; O = outcome; P = population; S = setting.
Beoordelingsdatum en geldigheid
Publicatiedatum : 09-10-2026
Beoordeeld op geldigheid : 09-10-2026
Algemene gegevens
De ontwikkeling/herziening van deze richtlijnmodule werd ondersteund door het Kennisinstituut van de Federatie Medisch Specialisten (www.demedischspecialist.nl/kennisinstituut) en werd gefinancierd door het ministerie van VWS. De financier heeft geen enkele invloed gehad op de inhoud van de richtlijnmodule.
Samenstelling werkgroep
Werkgroep
- S. (Selma) Bons, Nederlandse Vereniging voor Anesthesiologie (NVA), voorzitter
- Dr. M. (Michelle) Gompelman, Nederlandse Internisten Vereniging (NIV), Nederlandse Vereniging van Internist-Infectiologen (NVII)
- R. (Renze) Jongstra, Verpleegkundigen & Verzorgenden Nederland (V&VN)
- H. (Heidy) Koene, Vereniging voor Hygiëne & Infectiepreventie in de Gezondheidszorg (VHIG)
- M.H.H. (Marc) Königs, Nederlandse Vereniging voor Intensive Care (NVIC)
- Dr. B.J. (Bart) Laan (AIOS), Nederlandse Internisten Vereniging (NIV), Nederlandse Vereniging van Internist-Infectiologen (NVII)
- K. (Kelly) Niggebrugge-Mentink, Nederlandse Vereniging van Ziekenhuisapothekers (NVZA)
- Dr. J.H. (Jan) van Zeijl, Nederlandse Vereniging voor Medische Microbiologie (NVMM)
Klankbordgroep
- Dr. J.R.A. (Jeetindra) Balak, Nederlandse Internisten Vereniging (NIV), Nederlandse Federatie voor Nefrologie (NFN)
- Werkgroep richtlijn Centraal veneuze toegang (NVvH)
- Werkgroep leidraad Infusietechnologie (NVKF)
Met ondersteuning van
- Mw. A. (Alies) Oost, informatiespecialist, Kennisinstituut van Federatie Medisch Specialisten
- Dr. H. (Haitske) Graveland, senior adviseur, Kennisinstituut van Federatie Medisch Specialisten
- Dr. M.F.Q. (Marjolein) Kluijtmans-van den Bergh, senior adviseur, Kennisinstituut van Federatie Medisch Specialisten
Belangenverklaringen
De Code ter voorkoming van oneigenlijke beïnvloeding door belangenverstrengeling is gevolgd. Alle werkgroepleden hebben schriftelijk verklaard of zij in de laatste drie jaar directe financiële belangen (betrekking bij een commercieel bedrijf, persoonlijke financiële belangen, onderzoeksfinanciering) of indirecte belangen (persoonlijke relaties, reputatiemanagement) hebben gehad. Gedurende de ontwikkeling of herziening van een module worden wijzigingen in belangen aan de voorzitter doorgegeven. De belangenverklaring wordt opnieuw bevestigd tijdens de commentaarfase.
Een overzicht van de belangen van werkgroepleden en het oordeel over het omgaan met eventuele belangen vindt u in onderstaande tabel. De ondertekende belangenverklaringen zijn op te vragen bij het secretariaat van het Kennisinstituut van de Federatie Medisch Specialisten.
|
Werkgroeplid |
Functie |
Nevenfuncties |
Gemelde belangen |
Ondernomen actie |
|
S. (Selma) Bons |
Anesthesioloog, Prinses Maxima Centrum voor kinderoncologie, Utrecht |
Lid werkgroep SRI richtlijnen
Lid bestuur sectie kinderanesthesiologie NVA
Lid SRI |
Geen |
Geen restrictie |
|
Dr. M. (Michelle) Gompelman |
Internist-infectioloog, Elkerliek Ziekenhuis, Helmond |
Lid werkgroep FMS-richtlijn Centraal veneuze toegang
|
Geen |
Geen restrictie |
|
A. (Renze) Jongstra |
Intensive care verpleegkundige |
Vicevoorzitter V&VN afdeling IC (onbetaald)
|
Geen |
Geen restrictie |
|
H. (Heidy) Koene |
Deskundige infectiepreventie, Erasmus MC, Rotterdam |
Geen |
Geen |
Geen restrictie |
|
M.H.H. (Marc) Königs |
Intensivist, Maxima Medisch Centrum. Eindhoven/Veldhoven (100%) |
Duikerarts / duikclubarts
Waarnemer intensivist Aruba en via IC (max. 200 uur/jaar) In het verleden voordrachten op congressen voor 3M en BD (betaald) - ESAIC ( Milaan / München) - WOCOVA ( Athene) - Nordic congres for vasculary acces |
Geen |
Geen restrictie (adviseurschap 3M onbetaald) |
|
Dr. B.J. (Bart) Laan |
AIOS Interne Geneeskunde, Amsterdam UMC, Amsterdam |
Geen |
Geen |
Geen restrictie |
|
K. (Kelly) Niggebrugge-Mentink |
Ziekenhuisapotheker, Hagaziekenhuis, Den Haag |
Gastdocent Fontys Hogeschool (verpleegkundig specialistenopleiding); betaald Gastspreker congres Stichting Vascular Infusion Technology; onbetaald |
Geen |
Geen restrictie |
|
Dr. J.H. (Jan) van Zeijl |
Arts-microbioloog, Certe Medische Diagnostiek & Advies, afdeling Medische Microbiologie (tot april 2024)
Waarnemend arts-microbioloog, Certe Medische Diagnostiek & Advies, afdeling Medische Microbiologie (september t/m december 2025) |
Bestuurslid (sinds januari 2024 voorzitter) Vasculitis Stichting met portefeuille vrijwilligersbeleid en Zorg, Research en Belangenbehartiging; onbetaald |
Geen |
Geen restrictie |
|
Klankbordgroeplid |
Functie |
Nevenfuncties |
Gemelde belangen |
Ondernomen actie |
|
Dr. J.R.A. (Jeetindra) Balak |
Internist, Leids UMC, Leiden |
Geen |
Geen |
Geen restrictie |
Inbreng patiëntenperspectief
Er werd aandacht besteed aan het patiëntenperspectief door het uitnodigen van Patiëntenfederatie Nederland (PFNL) voor de schriftelijke knelpunteninventarisatie. De verkregen input is meegenomen bij het opstellen van de uitgangsvragen, de keuze voor de uitkomstmaten en bij het opstellen van de overwegingen. De conceptrichtlijn is tevens voor commentaar voorgelegd aan PFNL en de eventueel aangeleverde commentaren zijn bekeken en verwerkt.
Kwalitatieve raming van mogelijke financiële gevolgen in het kader van de Wkkgz
Bij de richtlijn is conform de Wet kwaliteit, klachten en geschillen zorg (Wkkgz) een kwalitatieve raming uitgevoerd of de aanbevelingen mogelijk leiden tot substantiële financiële gevolgen. Bij het uitvoeren van deze beoordeling zijn richtlijnmodules op verschillende domeinen getoetst (zie het stroomschema op de Richtlijnendatabase).
Uit de kwalitatieve raming blijkt dat er geen substantiële financiële gevolgen zijn, zie onderstaande tabel.
|
Module |
Uitkomst raming |
Toelichting |
|
Inbrengen van perifeer veneuze katheters |
Geen substantiële financiële gevolgen |
Hoewel uit de toetsing volgt dat de aanbevelingen breed toepasbaar zijn (>40.000 patiënten), volgt ook uit de toetsing dat het overgrote deel (±90%) van de zorgaanbieders en zorgverleners al aan de norm voldoet. Er worden daarom geen substantiële financiële gevolgen verwacht. |
Werkwijze
AGREE
Deze richtlijnmodule is opgesteld conform de eisen vermeld in het rapport Medisch Specialistische Richtlijnen 3.0 van de adviescommissie Richtlijnen van de Raad Kwaliteit. Dit rapport is gebaseerd op het AGREE II-instrument (Appraisal of Guidelines for Research & Evaluation II; Brouwers, 2010).
Knelpuntenanalyse en uitgangsvragen
Tijdens de voorbereidende fase inventariseerde de werkgroep de knelpunten met betrekking tot infectiepreventiemaatregelen rondom intravasculaire katheters. De werkgroep beoordeelde de aanbeveling(en) uit de eerdere WIP-richtlijn Arteriële kathetersen de WIP-richtlijn Flebitis en bloedbaaninfecties door intraveneuze infuuskatheters. Tevens zijn er in de schriftelijke knelpunteninventarisatie knelpunten aangedragen door Inspectie Gezondheidszorg en Jeugd (IGJ), Landelijke Vereniging van Operatieassistenten (LVO), Nederlandse Vereniging van Anesthesiemedewerkers (NVAM), Nederlandse Vereniging van Revalidatieartsen (VRA), Nederlandse Vereniging van Ziekenhuizen (NVZ), Nederlandse Vereniging voor Heelkunde (NVvH), Nederlandse Vereniging voor Medische Microbiologie (NVMM), Rijksinstituut voor Volksgezondheid en Milieu (RIVM), Stichting Kind en Ziekenhuis, Vereniging voor Hygiëne & Infectiepreventie in de Gezondheidszorg (VHIG), Verpleegkundigen & Verzorgenden Nederland (V&VN). Een verslag hiervan is opgenomen onder Verslag schriftelijke knelpunteninventarisatie.
Op basis van de uitkomsten van de knelpuntenanalyse zijn door de werkgroep concept uitgangsvragen opgesteld en definitief vastgesteld.
Uitkomstmaten
Na het opstellen van de zoekvragen behorende bij de uitgangsvragen inventariseerde de werkgroep welke uitkomstmaten voor de patiënt relevant zijn, waarbij zowel naar gewenste als ongewenste effecten werd gekeken. Hierbij werd een maximum van acht uitkomstmaten gehanteerd. De werkgroep waardeerde deze uitkomstmaten volgens hun relatieve belang bij de besluitvorming rondom aanbevelingen, als cruciaal (kritiek voor de besluitvorming), belangrijk (maar niet cruciaal) en onbelangrijk. Ook definieerde de werkgroep tenminste voor de cruciale uitkomstmaten welke verschillen zij klinisch (patiënt) relevant vonden.
Methode literatuursamenvatting
Een uitgebreide beschrijving van de strategie voor zoeken en selecteren van literatuur is te vinden onder Zoekverantwoording. Indien mogelijk werden de gegevens uit verschillende studies gepoold in een random-effects-model. Review Manager 5.4 werd gebruikt voor de statistische analyses. De beoordeling van de wetenschappelijke bewijskracht wordt hieronder toegelicht.
Beoordelen van de kracht van het wetenschappelijke bewijs
De kracht van het wetenschappelijke bewijs werd bepaald volgens de GRADE-methode. GRADE staat voor ‘Grading Recommendations Assessment, Development and Evaluation’ (zie https://www.gradeworkinggroup.org/). De basisprincipes van de GRADE-methodiek zijn: het benoemen en prioriteren van de klinisch (patiënt) relevante uitkomstmaten, een systematische review per uitkomstmaat, en een beoordeling van de bewijskracht per uitkomstmaat op basis van de acht GRADE-domeinen (domeinen voor downgraden: risk of bias, inconsistentie, indirectheid, imprecisie, en publicatiebias; domeinen voor upgraden: dosis-effect relatie, groot effect, en residuele plausibele confounding).
GRADE onderscheidt vier gradaties voor de kwaliteit van het wetenschappelijk bewijs: hoog, redelijk, laag en zeer laag. Deze gradaties verwijzen naar de mate van zekerheid die er bestaat over de literatuurconclusie, in het bijzonder de mate van zekerheid dat de literatuurconclusie de aanbeveling adequaat ondersteunt (Schünemann, 2013; Hultcrantz, 2017).
|
GRADE |
Definitie |
|
Hoog |
|
|
Redelijk |
|
|
Laag |
|
|
Zeer laag |
|
Bij het beoordelen (graderen) van de kracht van het wetenschappelijk bewijs in richtlijnen volgens de GRADE-methodiek spelen grenzen voor klinische besluitvorming een belangrijke rol (Hultcrantz, 2017). Dit zijn de grenzen die bij overschrijding aanleiding zouden geven tot een aanpassing van de aanbeveling. Om de grenzen voor klinische besluitvorming te bepalen moeten alle relevante uitkomstmaten en overwegingen worden meegewogen. De grenzen voor klinische besluitvorming zijn daarmee niet één op één vergelijkbaar met het minimaal klinisch relevant verschil (Minimal Clinically Important Difference, MCID). Met name in situaties waarin een interventie geen belangrijke nadelen heeft en de kosten relatief laag zijn, kan de grens voor klinische besluitvorming met betrekking tot de effectiviteit van de interventie bij een lagere waarde (dichter bij het nul effect) liggen dan de MCID (Hultcrantz, 2017).
Overwegingen (van bewijs naar aanbeveling)
Om te komen tot een aanbeveling zijn naast (de kwaliteit van) het wetenschappelijke bewijs ook andere aspecten belangrijk en worden meegewogen, zoals aanvullende argumenten uit bijvoorbeeld de biomechanica of fysiologie, waarden en voorkeuren van patiënten, kosten (middelenbeslag), duurzaamheid, aanvaardbaarheid, haalbaarheid en implementatie. Deze aspecten zijn systematisch vermeld en beoordeeld (gewogen) onder het kopje Overwegingen en kunnen (mede) gebaseerd zijn op expert opinion. Hierbij is gebruik gemaakt van een gestructureerd format gebaseerd op het evidence-to-decision framework van de internationale GRADE Working Group (Alonso-Coello, 2016A; Alonso-Coello 2016B). Dit evidence-to-decision framework is een integraal onderdeel van de GRADE-methodiek.
Formuleren van aanbevelingen
De aanbevelingen geven antwoord op de uitgangsvraag en zijn gebaseerd op het beschikbare wetenschappelijke bewijs en de belangrijkste overwegingen, en een weging van de gunstige en ongunstige effecten van de relevante interventies. De kracht van het wetenschappelijk bewijs en het gewicht dat door de werkgroep wordt toegekend aan de overwegingen, bepalen samen de sterkte van de aanbeveling. Conform de GRADE-methodiek sluit een lage bewijskracht van conclusies in de systematische literatuuranalyse een sterke aanbeveling niet a priori uit, en zijn bij een hoge bewijskracht ook zwakke aanbevelingen mogelijk (Agoritsas, 2017; Neumann, 2016). De sterkte van de aanbeveling wordt altijd bepaald door weging van alle relevante argumenten tezamen. De werkgroep heeft bij elke aanbeveling opgenomen hoe zij tot de richting en sterkte van de aanbeveling is gekomen.
In de GRADE-methodiek wordt onderscheid gemaakt tussen sterke en zwakke (of conditionele) aanbevelingen. De sterkte van een aanbeveling verwijst naar de mate van zekerheid dat de voordelen van de interventie opwegen tegen de nadelen (of vice versa), gezien over het hele spectrum van patiënten waarvoor de aanbeveling is bedoeld. De sterkte van een aanbeveling heeft duidelijke implicaties voor patiënten, behandelaars en beleidsmakers (zie onderstaande tabel). Een aanbeveling is geen dictaat, zelfs een sterke aanbeveling gebaseerd op bewijs van hoge kwaliteit (GRADE gradering HOOG) zal niet altijd van toepassing zijn, onder alle mogelijke omstandigheden en voor elke individuele patiënt.
|
Implicaties van sterke en zwakke aanbevelingen voor verschillende richtlijngebruikers |
||
|
|
Sterke aanbeveling |
Zwakke (conditionele) aanbeveling |
|
Voor patiënten |
De meeste patiënten zouden de aanbevolen interventie of aanpak kiezen en slechts een klein aantal niet. |
Een aanzienlijk deel van de patiënten zouden de aanbevolen interventie of aanpak kiezen, maar veel patiënten ook niet. |
|
Voor behandelaars |
De meeste patiënten zouden de aanbevolen interventie of aanpak moeten ontvangen. |
Er zijn meerdere geschikte interventies of aanpakken. De patiënt moet worden ondersteund bij de keuze voor de interventie of aanpak die het beste aansluit bij zijn of haar waarden en voorkeuren. |
|
Voor beleidsmakers |
De aanbevolen interventie of aanpak kan worden gezien als standaardbeleid. |
Beleidsbepaling vereist uitvoerige discussie met betrokkenheid van veel stakeholders. Er is een grotere kans op lokale beleidsverschillen. |
Commentaar- en autorisatiefase
De conceptrichtlijnmodule werd aan de betrokken (wetenschappelijke) verenigingen en (patiënt) organisaties voorgelegd ter commentaar. De commentaren werden verzameld en besproken met de werkgroep. Naar aanleiding van de commentaren werd de conceptrichtlijnmodule aangepast en definitief vastgesteld door de werkgroep. De definitieve richtlijnmodule werd aan de deelnemende (wetenschappelijke) verenigingen en (patiënt) organisaties voorgelegd voor autorisatie en door hen geautoriseerd dan wel geaccordeerd.
Literatuur
Agoritsas T, Merglen A, Heen AF, Kristiansen A, Neumann I, Brito JP, Brignardello-Petersen R, Alexander PE, Rind DM, Vandvik PO, Guyatt GH. UpToDate adherence to GRADE criteria for strong recommendations: an analytical survey. BMJ Open. 2017 Nov 16;7(11):e018593. doi: 10.1136/bmjopen-2017-018593. PubMed PMID: 29150475; PubMed Central PMCID: PMC5701989.
Alonso-Coello P, Schünemann HJ, Moberg J, Brignardello-Petersen R, Akl EA, Davoli M, Treweek S, Mustafa RA, Rada G, Rosenbaum S, Morelli A, Guyatt GH, Oxman AD; GRADE Working Group. GRADE Evidence to Decision (EtD) frameworks: a systematic and transparent approach to making well informed healthcare choices. 1: Introduction. BMJ. 2016 Jun 28;353:i2016. doi: 10.1136/bmj.i2016. PubMed PMID: 27353417. A
Alonso-Coello P, Oxman AD, Moberg J, Brignardello-Petersen R, Akl EA, Davoli M, Treweek S, Mustafa RA, Vandvik PO, Meerpohl J, Guyatt GH, Schünemann HJ; GRADE Working Group. GRADE Evidence to Decision (EtD) frameworks: a systematic and transparent approach to making well informed healthcare choices. 2: Clinical practice guidelines. BMJ. 2016 Jun 30;353:i2089. doi: 10.1136/bmj.i2089. PubMed PMID: 27365494. B
Brouwers MC, Kho ME, Browman GP, Burgers JS, Cluzeau F, Feder G, Fervers B, Graham ID, Grimshaw J, Hanna SE, Littlejohns P, Makarski J, Zitzelsberger L; AGREE Next Steps Consortium. AGREE II: advancing guideline development, reporting and evaluation in health care. CMAJ. 2010 Dec 14;182(18):E839-42. doi: 10.1503/cmaj.090449. Epub 2010 Jul 5. Review. PubMed PMID: 20603348; PubMed Central PMCID: PMC3001530.
Hultcrantz M, Rind D, Akl EA, Treweek S, Mustafa RA, Iorio A, Alper BS, Meerpohl JJ, Murad MH, Ansari MT, Katikireddi SV, Östlund P, Tranæus S, Christensen R, Gartlehner G, Brozek J, Izcovich A, Schünemann H, Guyatt G. The GRADE Working Group clarifies the construct of certainty of evidence. J Clin Epidemiol. 2017 Jul;87:4-13. doi: 10.1016/j.jclinepi.2017.05.006. Epub 2017 May 18. PubMed PMID: 28529184; PubMed Central PMCID: PMC6542664.
Medisch Specialistische Richtlijnen 3.0 (2023). Adviescommissie Richtlijnen van de Raad Kwaliteit. Available from: https://richtlijnendatabase.nl/uploaded/docs/FMS_MedSpecRicht_2023__v04.pdf?u=1bULOR
Neumann I, Santesso N, Akl EA, Rind DM, Vandvik PO, Alonso-Coello P, Agoritsas T, Mustafa RA, Alexander PE, Schünemann H, Guyatt GH. A guide for health professionals to interpret and use recommendations in guidelines developed with the GRADE approach. J Clin Epidemiol. 2016 Apr;72:45-55. doi: 10.1016/j.jclinepi.2015.11.017. Epub 2016 Jan 6. PMID: 26772609.
Schünemann H, Brożek J, Guyatt G, et al. GRADE handbook for grading quality of evidence and strength of recommendations. Updated October 2013. The GRADE Working Group, 2013. Available from: https://gdt.gradepro.org/app/handbook/handbook.html.
Zoekverantwoording
Zoekstrategie
Embase.com
|
No. |
Query |
Results |
|
#1 |
'peripheral venous catheter'/de OR 'peripheral intravenous catheter*':ti,ab,kw OR 'peripheral intra venous catheter*':ti,ab,kw OR 'peripheral venous catheter*':ti,ab,kw OR 'peripheral vascular catheter*':ti,ab,kw OR 'peripheral intravascular catheter*':ti,ab,kw OR 'peripheral intra vascular catheter*':ti,ab,kw OR 'peripheral catheter*':ti,ab,kw OR 'peripheral intravenous cannula*':ti,ab,kw OR 'peripheral intra venous cannula*':ti,ab,kw OR 'peripheral venous cannula*':ti,ab,kw OR 'peripheral vascular cannula*':ti,ab,kw OR 'peripheral intravascular cannula*':ti,ab,kw OR 'peripheral intra vascular cannula*':ti,ab,kw OR 'peripheral cannula*':ti,ab,kw OR 'peripheral intravenous line*':ti,ab,kw OR 'peripheral intra venous line*':ti,ab,kw OR 'peripheral venous line*':ti,ab,kw OR 'peripheral vascular line*':ti,ab,kw OR 'peripheral intravascular line*':ti,ab,kw OR 'peripheral intra vascular line*':ti,ab,kw OR 'peripheral line*':ti,ab,kw OR 'peripheral intravenous access*':ti,ab,kw OR 'peripheral intra venous access*':ti,ab,kw OR 'peripheral venous access*':ti,ab,kw OR 'peripheral vascular access*':ti,ab,kw OR 'peripheral intravascular access*':ti,ab,kw OR 'peripheral intra vascular access*':ti,ab,kw OR ((peripheral* NEAR/2 (iv OR ivs)):ti,ab,kw) OR pivc:ti,ab,kw OR pivcs:ti,ab,kw |
7738 |
|
#2 |
'hand'/exp OR 'antecubital fossa'/exp OR 'upper arm'/exp OR 'elbow'/exp OR 'lower limb'/exp OR ((lower NEAR/3 (limb* OR extremit*)):ti,ab,kw) OR leg:ti,ab,kw OR legs:ti,ab,kw OR thigh:ti,ab,kw OR hand:ti,ab,kw OR 'upper arm*':ti,ab,kw OR elbow*:ti,ab,kw OR 'antecubital fossa*':ti,ab,kw OR 'ante cubital fossa*':ti,ab,kw OR 'cubital fossa*':ti,ab,kw OR (((insert* OR puncture OR indwelling) NEAR/3 (site* OR locat*)):ti,ab,kw) |
1494489 |
|
#3 |
#1 AND #2 NOT ('conference abstract'/it OR 'editorial'/it OR 'letter'/it OR 'note'/it) NOT (('animal'/exp OR 'animal experiment'/exp OR 'animal model'/exp OR 'nonhuman'/exp) NOT 'human'/exp) AND [2000-2024]/py |
547 |
|
#4 |
'meta analysis'/exp OR 'meta analysis (topic)'/exp OR metaanaly*:ti,ab OR 'meta analy*':ti,ab OR metanaly*:ti,ab OR 'systematic review'/de OR 'cochrane database of systematic reviews'/jt OR prisma:ti,ab OR prospero:ti,ab OR (((systemati* OR scoping OR umbrella OR 'structured literature') NEAR/3 (review* OR overview*)):ti,ab) OR ((systemic* NEAR/1 review*):ti,ab) OR (((systemati* OR literature OR database* OR 'data base*') NEAR/10 search*):ti,ab) OR (((structured OR comprehensive* OR systemic*) NEAR/3 search*):ti,ab) OR (((literature NEAR/3 review*):ti,ab) AND (search*:ti,ab OR database*:ti,ab OR 'data base*':ti,ab)) OR (('data extraction':ti,ab OR 'data source*':ti,ab) AND 'study selection':ti,ab) OR ('search strategy':ti,ab AND 'selection criteria':ti,ab) OR ('data source*':ti,ab AND 'data synthesis':ti,ab) OR medline:ab OR pubmed:ab OR embase:ab OR cochrane:ab OR (((critical OR rapid) NEAR/2 (review* OR overview* OR synthes*)):ti) OR ((((critical* OR rapid*) NEAR/3 (review* OR overview* OR synthes*)):ab) AND (search*:ab OR database*:ab OR 'data base*':ab)) OR metasynthes*:ti,ab OR 'meta synthes*':ti,ab |
1003926 |
|
#5 |
'clinical trial'/exp OR 'randomization'/exp OR 'single blind procedure'/exp OR 'double blind procedure'/exp OR 'crossover procedure'/exp OR 'placebo'/exp OR 'prospective study'/exp OR rct:ab,ti OR random*:ab,ti OR 'single blind':ab,ti OR 'randomised controlled trial':ab,ti OR 'randomized controlled trial'/exp OR placebo*:ab,ti |
3976736 |
|
#6 |
'major clinical study'/de OR 'clinical study'/de OR 'case control study'/de OR 'family study'/de OR 'longitudinal study'/de OR 'retrospective study'/de OR 'prospective study'/de OR 'comparative study'/de OR 'cohort analysis'/de OR ((cohort NEAR/1 (study OR studies)):ab,ti) OR (('case control' NEAR/1 (study OR studies)):ab,ti) OR (('follow up' NEAR/1 (study OR studies)):ab,ti) OR (observational NEAR/1 (study OR studies)) OR ((epidemiologic NEAR/1 (study OR studies)):ab,ti) OR (('cross sectional' NEAR/1 (study OR studies)):ab,ti) |
8084646 |
|
#7 |
'case control study'/de OR 'comparative study'/exp OR 'control group'/de OR 'controlled study'/de OR 'controlled clinical trial'/de OR 'crossover procedure'/de OR 'double blind procedure'/de OR 'phase 2 clinical trial'/de OR 'phase 3 clinical trial'/de OR 'phase 4 clinical trial'/de OR 'pretest posttest design'/de OR 'pretest posttest control group design'/de OR 'quasi experimental study'/de OR 'single blind procedure'/de OR 'triple blind procedure'/de OR (((control OR controlled) NEAR/6 trial):ti,ab,kw) OR (((control OR controlled) NEAR/6 (study OR studies)):ti,ab,kw) OR (((control OR controlled) NEAR/1 active):ti,ab,kw) OR 'open label*':ti,ab,kw OR (((double OR two OR three OR multi OR trial) NEAR/1 (arm OR arms)):ti,ab,kw) OR ((allocat* NEAR/10 (arm OR arms)):ti,ab,kw) OR placebo*:ti,ab,kw OR 'sham-control*':ti,ab,kw OR (((single OR double OR triple OR assessor) NEAR/1 (blind* OR masked)):ti,ab,kw) OR nonrandom*:ti,ab,kw OR 'non-random*':ti,ab,kw OR 'quasi-experiment*':ti,ab,kw OR crossover:ti,ab,kw OR 'cross over':ti,ab,kw OR 'parallel group*':ti,ab,kw OR 'factorial trial':ti,ab,kw OR ((phase NEAR/5 (study OR trial)):ti,ab,kw) OR ((case* NEAR/6 (matched OR control*)):ti,ab,kw) OR ((match* NEAR/6 (pair OR pairs OR cohort* OR control* OR group* OR healthy OR age OR sex OR gender OR patient* OR subject* OR participant*)):ti,ab,kw) OR ((propensity NEAR/6 (scor* OR match*)):ti,ab,kw) OR versus:ti OR vs:ti OR compar*:ti OR ((compar* NEAR/1 study):ti,ab,kw) OR (('major clinical study'/de OR 'clinical study'/de OR 'cohort analysis'/de OR 'observational study'/de OR 'cross-sectional study'/de OR 'multicenter study'/de OR 'correlational study'/de OR 'follow up'/de OR cohort*:ti,ab,kw OR 'follow up':ti,ab,kw OR followup:ti,ab,kw OR longitudinal*:ti,ab,kw OR prospective*:ti,ab,kw OR retrospective*:ti,ab,kw OR observational*:ti,ab,kw OR 'cross sectional*':ti,ab,kw OR cross?ectional*:ti,ab,kw OR multicent*:ti,ab,kw OR 'multi-cent*':ti,ab,kw OR consecutive*:ti,ab,kw) AND (group:ti,ab,kw OR groups:ti,ab,kw OR subgroup*:ti,ab,kw OR versus:ti,ab,kw OR vs:ti,ab,kw OR compar*:ti,ab,kw OR 'odds ratio*':ab OR 'relative odds':ab OR 'risk ratio*':ab OR 'relative risk*':ab OR 'rate ratio':ab OR aor:ab OR arr:ab OR rrr:ab OR ((('or' OR 'rr') NEAR/6 ci):ab))) |
14842224 |
|
#8 |
#3 AND #4 - SR |
29 |
|
#9 |
#3 AND #5 NOT #8 - RCT |
177 |
|
#10 |
#3 AND (#6 OR #7) NOT (#8 OR #9) - observationeel |
190 |
|
#11 |
#8 OR #9 OR #10 |
396 |
Ovid/Medline
|
# |
Searches |
Results |
|
1 |
Catheterization, Peripheral/ or ('Peripheral intravenous catheter*' or 'Peripheral intra venous catheter*' or 'Peripheral venous catheter*' or 'peripheral vascular catheter*' or 'peripheral intravascular catheter*' or 'peripheral intra vascular catheter*' or 'Peripheral catheter*' or 'Peripheral intravenous cannula*' or 'Peripheral intra venous cannula*' or 'peripheral venous cannula*' or 'peripheral vascular cannula*' or 'peripheral intravascular cannula*' or 'peripheral intra vascular cannula*' or 'Peripheral cannula*' or 'Peripheral intravenous line*' or 'Peripheral intra venous line*' or 'Peripheral venous line*' or 'Peripheral vascular line*' or 'peripheral intravascular line*' or 'peripheral intra vascular line*' or 'peripheral line*' or 'Peripheral intravenous access*' or 'Peripheral intra venous access*' or 'Peripheral venous access*' or 'Peripheral vascular access*' or 'peripheral intravascular access*' or 'peripheral intra vascular access*' or (peripheral* adj2 (iv or ivs)) or pivc or pivcs).ti,ab,kf. |
4056 |
|
2 |
exp Hand/ or exp Elbow/ or exp Lower Extremity/ or (lower adj3 (limb* or extremit*)).ti,ab,kf. or leg.ti,ab,kf. or legs.ti,ab,kf. or thigh.ti,ab,kf. or hand.ti,ab,kf. or 'upper arm*'.ti,ab,kf. or elbow*.ti,ab,kf. or 'antecubital fossa*'.ti,ab,kf. or 'ante cubital fossa*'.ti,ab,kf. or 'cubital fossa*'.ti,ab,kf. or ((insert* or puncture or indwelling) adj3 (site* or locat*)).ti,ab,kf. |
950138 |
|
3 |
(1 and 2) not (comment/ or editorial/ or letter/) not ((exp animals/ or exp models, animal/) not humans/) |
510 |
|
4 |
limit 3 to yr="2000 -Current" |
457 |
|
5 |
meta-analysis/ or meta-analysis as topic/ or (metaanaly* or meta-analy* or metanaly*).ti,ab,kf. or systematic review/ or cochrane.jw. or (prisma or prospero).ti,ab,kf. or ((systemati* or scoping or umbrella or "structured literature") adj3 (review* or overview*)).ti,ab,kf. or (systemic* adj1 review*).ti,ab,kf. or ((systemati* or literature or database* or data-base*) adj10 search*).ti,ab,kf. or ((structured or comprehensive* or systemic*) adj3 search*).ti,ab,kf. or ((literature adj3 review*) and (search* or database* or data-base*)).ti,ab,kf. or (("data extraction" or "data source*") and "study selection").ti,ab,kf. or ("search strategy" and "selection criteria").ti,ab,kf. or ("data source*" and "data synthesis").ti,ab,kf. or (medline or pubmed or embase or cochrane).ab. or ((critical or rapid) adj2 (review* or overview* or synthes*)).ti. or (((critical* or rapid*) adj3 (review* or overview* or synthes*)) and (search* or database* or data-base*)).ab. or (metasynthes* or meta-synthes*).ti,ab,kf. |
728276 |
|
6 |
exp clinical trial/ or randomized controlled trial/ or exp clinical trials as topic/ or randomized controlled trials as topic/ or Random Allocation/ or Double-Blind Method/ or Single-Blind Method/ or (clinical trial, phase i or clinical trial, phase ii or clinical trial, phase iii or clinical trial, phase iv or controlled clinical trial or randomized controlled trial or multicenter study or clinical trial).pt. or random*.ti,ab. or (clinic* adj trial*).tw. or ((singl* or doubl* or treb* or tripl*) adj (blind$3 or mask$3)).tw. or Placebos/ or placebo*.tw. |
2694188 |
|
7 |
Epidemiologic studies/ or case control studies/ or exp cohort studies/ or Controlled Before-After Studies/ or Case control.tw. or cohort.tw. or Cohort analy$.tw. or (Follow up adj (study or studies)).tw. or (observational adj (study or studies)).tw. or Longitudinal.tw. or Retrospective*.tw. or prospective*.tw. or consecutive*.tw. or Cross sectional.tw. or Cross-sectional studies/ or historically controlled study/ or interrupted time series analysis/ [Onder exp cohort studies vallen ook longitudinale, prospectieve en retrospectieve studies] |
4659587 |
|
8 |
Case-control Studies/ or clinical trial, phase ii/ or clinical trial, phase iii/ or clinical trial, phase iv/ or comparative study/ or control groups/ or controlled before-after studies/ or controlled clinical trial/ or double-blind method/ or historically controlled study/ or matched-pair analysis/ or single-blind method/ or (((control or controlled) adj6 (study or studies or trial)) or (compar* adj (study or studies)) or ((control or controlled) adj1 active) or "open label*" or ((double or two or three or multi or trial) adj (arm or arms)) or (allocat* adj10 (arm or arms)) or placebo* or "sham-control*" or ((single or double or triple or assessor) adj1 (blind* or masked)) or nonrandom* or "non-random*" or "quasi-experiment*" or "parallel group*" or "factorial trial" or "pretest posttest" or (phase adj5 (study or trial)) or (case* adj6 (matched or control*)) or (match* adj6 (pair or pairs or cohort* or control* or group* or healthy or age or sex or gender or patient* or subject* or participant*)) or (propensity adj6 (scor* or match*))).ti,ab,kf. or (confounding adj6 adjust*).ti,ab. or (versus or vs or compar*).ti. or ((exp cohort studies/ or epidemiologic studies/ or multicenter study/ or observational study/ or seroepidemiologic studies/ or (cohort* or 'follow up' or followup or longitudinal* or prospective* or retrospective* or observational* or multicent* or 'multi-cent*' or consecutive*).ti,ab,kf.) and ((group or groups or subgroup* or versus or vs or compar*).ti,ab,kf. or ('odds ratio*' or 'relative odds' or 'risk ratio*' or 'relative risk*' or aor or arr or rrr).ab. or (("OR" or "RR") adj6 CI).ab.)) |
5629016 |
|
9 |
4 and 5 - SR |
21 |
|
10 |
(4 and 6) not 9 - RCT |
103 |
|
11 |
(4 and (7 or 8)) not (9 or 10) - observationeel |
196 |
|
12 |
9 or 10 or 11 |
320 |