
MART bij kinderen met astma
Uitgangsvraag
Wat is de plaats van maintenance and reliever therapy (MART) in de behandeling van astma bij kinderen tussen de 4 en 12 jaar.
Wat is de plaats van maintenance and reliever therapy (MART) in de behandeling van astma bij kinderen tussen de 12-18 jaar.
Aanbeveling
Bespreek, in de derde stap van astma behandeling, samen met ouders van kinderen (4-11 jaar) en met (ouders van) adolescenten (12 jaar en ouder) met persisterend astma om MART als proefbehandeling te starten:
- Beslis samen hoe lang de proefperiode plaatsvindt (3-6 maanden).
- Bij blijvende klachten: controleer eerst op veelvoorkomende problemen, zoals een onjuiste inhalatietechniek, slechte therapietrouw en blootstelling aan tabaks/vape rook en/of allergene of niet allergene prikkels, overweeg andere diagnosen en behandel eventuele co-morbiditeit (inclusief allergische rhinitis).
- Bij blijvende klachten en bevestiging dat de symptomen het gevolg zijn van astma: overweeg andere medicatie volgens stap 3 van de NVK-richtlijn Astma (bijv. verdubbelen startdosering ICS) en/of overleg met een kinderlongarts.
Bespreek met de patiënt:
- De mogelijk voordelen en nadelen en onzekerheden van het gebruik van (S)MART.
- Geef, in begrijpelijke taal of beeld, goede en herhaalde voorlichting over astma en het gebruik van inhalatoren aan (ouders van) patiënten.
- Geef, volgens NVK-richtlijn Astma, een ingevuld actieplan mee. Kijk voor dosering en het maximum aantal pufs per dag in het farmacotherapeutisch kompas.
Overwegingen
Balans tussen gewenste en ongewenste effecten
Er is een systematische literatuurzoekactie uitgevoerd naar de effecten van ‘Maintenance and Reliever Therapy’ (MART) vergeleken met placebo of de gebruikelijke medicatie bij kinderen (4-11 jaar) en adolescenten (>=12 jaar) met (persisterend) astma. Eén studie heeft data geanalyseerd van kinderen met (persisterend) astma (Bisgaard, 2006). Daarnaast is er een post hoc studie geïncludeerd (Jorup, 2018), die 6 gerandomiseerde studies voor adolescenten met (persisterend) astma heeft geanalyseerd. De 6 studies zijn niet op kwaliteit beoordeeld door Jorup (2018), daarnaast hanteren de studies verschillende follow-up tijden en is er veel heterogeniteit in populatie en gebruikte vergelijkingsgroepen. De studies zijn daarom individueel meegenomen in de GRADING van deze richtlijn en de gepoolde resultaten van Jorup (2018) zijn niet gebruikt. De overall resultaten van Jorup (2018) worden voor de volledigheid kort beschreven in de Overwegingen - Adolescenten >12 jaar.
Kinderen (4-11 jaar jaar)
MART lijkt een borderline klinisch relevant gunstig effect te hebben op het totaal aantal longaanvallen, en een duidelijk klinisch relevant gunstig effect op ernstige longaanvallen vergeleken met de controlegroepen. Het bewijs hiervoor is echter zwak. MART heeft waarschijnlijk geen klinisch relevant effect op de cruciale uitkomstmaat Astma Symptom Score na 12 maanden bij kinderen met astma. Er konden geen conclusies getrokken worden over het effect van MART vergeleken met gebruikelijke medicatie op de cruciale uitkomstmaat ACQ-5 score en longfunctie, alsook belangrijke uitkomstmaten ‘ziekte specifieke kwaliteit van leven’, ‘dosisreductie van corticosteroïden’ en ‘alle bijwerkingen’ omdat deze uitkomstmaten niet of niet volledig gerapporteerd zijn in de geïncludeerde studies. MART lijkt wel een klinisch relevant gunstig effect te hebben op het aantal ernstige bijwerkingen, hoewel het bewijs hiervoor zwak is.
Adolescenten (>12 jaar)
MART lijkt een borderline klinisch relevant gunstig effect te hebben op het aantal ernstige longaanvallen na 6 en 12 maanden vergeleken met placebo. MART heeft geen klinisch relevant effect op de cruciale uitkomstmaten ACQ-5 en Astma Symptom Score na 6 maanden bij adolescenten met astma. Er kan geen conclusie worden getrokken voor ‘alle exacerbaties’ omdat deze uitkomstmaat niet gerapporteerd werd door de geïncludeerde studies. Voor de cruciale uitkomstmaten ACQ-5 is er een klein tot geen verschil tussen MART en placebo na 12 maanden en voor astma symptom score is er wel een klinisch relevant verschil tussen MART en placebo na 12 maanden. Er is een kleine invloed van MART op FEV1 na 12 maanden, hoewel niet klinisch relevant. Na 6 maanden werd dit verschil niet gevonden. Er konden geen conclusies getrokken worden over het effect van MART vergeleken met placebo op de belangrijke uitkomstmaat ‘ziekte specifieke kwaliteit van leven’ en ‘dosisreductie van corticosteroïden’, omdat deze uitkomstmaat niet gerapporteerd is in de geïncludeerde studies. MART lijkt geen effect te hebben op ‘alle bijwerkingen’, maar lijkt wel een gunstig en klinisch relevant effect te hebben op het aantal ernstige bijwerkingen, hoewel bewijs hiervoor zwak is.
In aanvulling op de reeds genoemde individuele studies laat de post-hoc studie van 6 RCT’s (Jorup, 2018) met adolescenten zien dat MART vergelijkbaar is met, of effectiever dan, de vergelijkingsmiddelen in elk van de studies in het verminderen van het risico op een ernstige longaanvallen (hazard ratio's (HR) BUD/FORM MART versus vergelijkingsmiddelen 0,15-1,01; gepoolde HR 0,49, 95% BI 0,34-0,70). Vergelijkbare behandelvoordelen voor MART werden waargenomen voor totaal aantal ernstige longaanvallen, veranderingen in astmagerelateerde symptomen, geforceerd expiratoir volume in 1 seconde (FEV1) bij kliniekbezoeken, en scores op de vijf-item astmacontrole vragenlijst (ACQ-5). Het gebruik van ‘zo nodig medicatie’ was lager met MART dan met vergelijkingsmiddelen.
Tot slot zijn er recente meta-analyses gepubliceerd van RCT’s met adolescenten en volwassenen tezamen welke een gunstig effect laten zien ten aanzien van het risico op ernstige longaanvallen. Echter in deze studies zijn geen subgroep analyses verricht voor adolescenten waarop deze studies niet in deze module zijn meegenomen (Beasly, 2022; Papi ,2022).
Studies zijn gedaan met normale dosering budesonide-formoterol inhalator, echter in de GINA-guideline staat dat ook beclometasone-formoterol kan worden toegepast. In ieder geval mag geen salmeterol worden gebruikt in verband met de langzame werkingsduur.
De expertisegroep wil graag benadrukken dat toekomstige herzieningen van deze richtlijnen gebruik kunnen maken van een gestandaardiseerde set uitkomstmaten voor studies naar MART bij pediatrische patiënten (Khaleva, 2023).
Kwaliteit van bewijs
De kwaliteit van het bewijs is in alle uitkomsten zeer laag vanwege methodologische beperkingen (onvoldoende blindering), onnauwkeurigheid (brede betrouwbaarheidsintervallen) en in sommige gevallen inconsistentie (zoals bij astmasymptomen). Daarnaast is afgewaardeerd op publicatiebias door de grote betrokkenheid van AstraZeneca in de studies, wat de kwaliteit van de uiteindelijke resultaten heeft beïnvloed van gemiddeld en laag naar laag tot zeer laag.
Waarden en voorkeuren van patiënten (en eventueel hun naasten/verzorgers)
In de spreekkamer is het belangrijk om samen met de kinderen en adolescenten met persisterend astma als ook de ouders te bespreken en te beslissen of de mogelijke voordelen van MART, zoals een vermindering van het aantal longaanvallen, opwegen tegen de mogelijke onzekerheden die uit onderzoek naar voren komen. Hierbij moet er aandacht zijn voor de persoonlijke situatie en voorkeuren van het kind of de adolescent. Gewenste effecten, zoals minder longaanvallen, lijken op groepsniveau aanwezig te zijn maar het bewijs is onzeker, terwijl bewijs voor duidelijke verbeteringen in astmasymptomen en longfunctie (FEV1) ontbreken of minimaal zijn. Met name bij adolescenten lijkt MART vergelijkbaar met en op sommige uitkomstmaten mogelijk effectiever dan de vergelijkingsmiddelen. Ongewenste effecten zijn niet overtuigend aangetoond, al is het beschikbare bewijs beperkt. Het gebruiksgemak voor de patiënt is in deze PICO niet als uitkomstmaat meegenomen, echter het enkel gebruiken van één type inhalator kan tot meer gebruiksgemak leiden. Daarnaast kan dit de therapietrouw van de patiënt positief beïnvloeden. De afweging tussen deze gewenste en ongewenste effecten (zoals mogelijke bijwerkingen, onzekerheden over langetermijneffecten en het gebrek aan verbetering van symptomen) verschilt per patiënt. Herhaalde educatie en uitleg door betrokken zorgverleners, o.a. artsen en (long)verpleegkundigen, blijft van belang. Hierbij kan gebruik gemaakt worden van online instructies (inhalatorgebruik.nl) ter ondersteuning.
Kostenaspecten
Mogelijke besparingen door minder longaanvallen en ziekenhuisopnames zijn denkbaar.
Gelijkheid ((health) equity/equitable)
MART vereist gebruik van een combinatiepreparaat dat in Nederland, mits voldaan aan leeftijd en indicatie, aan kinderen vanaf 12 jaar wordt vergoed, en in sommige gevallen al vanaf 6 jaar. Het goed gebruik van de inhalator is afhankelijk van gezondheidsvaardigheden (zoals het begrijpen van de instructie en het juist toepassen), en het geven van juiste instructies wat ongelijkheid in effectiviteit kan veroorzaken (actieve toetsing bijvoorbeeld teach-back demonstratie), zie ook aanvullende voorbeelden via inhalatorgebruik.nl.
Aanvaardbaarheid:
Ethische aanvaardbaarheid
Er zijn geen directe ethische bezwaren tegen het gebruik van MART bij kinderen en adolescenten, mits de behandeling goed wordt uitgelegd.
Duurzaamheid
MART maakt gebruik van één combinatiepreparaatwaardoor het gebruik van meerdere inhalatoren kan worden beperkt. Dit zou kunnen leiden tot een vermindering van het totale materiaal- en verpakkingsgebruik. De totale milieu-impact is afhankelijk van meerdere factoren, waaronder het type inhalator (aerosol versus droogpoeder) en het gebruik van grondstoffen tijdens productie en distributie. Voor voorkeuren van type inhalatie medicatie kan zonodig de Leidraad klimaatbewust voorschrijven geraadpleegd worden.
Haalbaarheid
De haalbaarheid wordt positief ingeschat. Hoewel de toepassing van MART technisch uitvoerbaar is, is het nog geen gangbare praktijk binnen de kindergeneeskunde. De uitvoering dient dan ook te worden opgenomen in landelijke richtlijnen. Hierbij dient onder andere aandacht te zijn voor goede instructies met juist inhalatorgebruik, en kennis van de te gebruiken inhalatoren voor deze indicatie.
Rationale van de aanbeveling: weging van argumenten voor en tegen de interventies
Bij (ouders van) kinderen (4 – 11 jaar) en vooral bij adolescenten (12 jaar en ouder) met persisterend astma, kan het gebruik van MART besproken worden. De arts en (ouders van) kinderen (4-11 jaar) en adolescenten (12 jaar en ouder) beslissen samen of er gestart wordt met een proefbehandeling. Deze werkgroep adviseert een proefbehandeling van 3 tot 6 maanden om het klinisch effect en effect op longfunctie te kunnen beoordelen. Daarbij moet de afweging gemaakt worden of de gewenst effecten, zoals behoud van astma controle, behoud van longfunctie, vermindering van (ernstige) longaanvallen als ook een gunstig effect op ernstige bijwerkingen, opwegen tegen de nog bestaande onzekere uitkomstmaten zoals kwaliteit van leven, luchtwegontsteking en langetermijneffecten.
Eindoordeel:
Zwakke aanbeveling voor gebruik van MART bij kinderen (4-11 jaar) en adolescenten (12 jaar en ouder) met persisterend astma. MART kan worden ingezet bij kinderen (4-11 jaar) en adolescenten (12 jaar en ouder) vanaf stap 3 van de NVK richtlijn Astma. Op basis van de huidige literatuur en haar grading is de aanbeveling zwak.
Onderbouwing
Administering a short-acting beta agonist (SABA) alone is strongly associated with higher risks of asthmatic exacerbations in children. Whether children with uncontrolled asthma using daily inhaled corticosteroids (ICS) or ICS in combination with a long-acting beta agonist (LABA) benefit from SABA as needed or ICS/LABA as needed is not fully clear. Recent studies examined the effects of treatment with maintenance and reliever therapy (MART) on the risk of asthmatic exacerbations in children. MART is an asthma management regimen that uses a single, combined inhaler for both daily maintenance and as-needed symptom relief, instead of requiring separate maintenance (control with inhaled corticosteroids) and reliever (bronchodilator) inhalers. MART ensures that any increase in long-acting reliever use in response to asthma symptoms is matched by an increase in ICS, ensuring that inflammation is targeted when symptoms increase. From a patient perspective, use of one inhaler may eliminate the confusion of using different devices for rescue and control. However, the current Dutch guideline “asthma in children’ does not yet discuss MART treatment whereas the Global Initiative for Asthma (GINA) report (2024) and BTS/NICE/SIGN Joint Guideline (2024) already include MART treatment as preferred track or option from treatment step 3 onwards (eg. GINA) in children of age 6 years and older.
|
Outcome Timeframe |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
|
|
Comparator |
(S)MART |
||||
|
All excacerbations in 12 months
|
Measured by: number of all exacerbations Based on data from 341 participants in 1 studies
|
|
Very low Due to serious risk of bias, Due to very serious imprecision, Due to serious publication bias1 |
The evidence is very uncertain about the effect of MART on all excacerbation after 12 months when compared with care as usual in pediatric patients with persistent asthma (Bisgaard, 2006) |
|
|
Severe excacerbations in 12 months
|
Measured by: number of severe exacerbations Based on data from 341 participants in 1 study
|
|
Very low Due to serious risk of bias, Due to very serious imprecision, Due to serious publication bias2 |
The evidence is very uncertain about the effect of MART on severe excacerbation frequency after 12 months when compared with care as usual in pediatric patients with persistent asthma (Bisgaard, 2006) |
|
|
Change in asthma symptoms in 12 months
|
Measured by: Patient diary Scale: 0 - 6 Lower better Based on data from 341 participants in 1 study
|
Mean difference Bud/Form MART group versus fixed combination dose of -0.11 (95%CI not reported) |
Very low Due to serious risk of bias, Due to very serious imprecision, Due to serious inconsistency Due to serious publication bias3 |
The evidence is very uncertain about the effect of MART on change in asthma symptoms after 12 months when compared with care as usual in pediatric patients with persistent asthma (Bisgaard, 2006) |
|
|
Change in ACQ 5 score in 12 months
|
-
|
Not reported |
- |
No conclusions could be drawn about the effect of MART on ACQ score, compared with care as usual in pediatric patients who have persistent asthma, because of the absence of data. |
|
|
Disease specific quality of life
|
|
Not reported |
- |
No conclusions could be drawn about the effect of MART on disease specific quality of life, compared with care as usual in pediatric patients who have persistent asthma, because of the absence of data. |
|
|
Corticosteroid dose reduction |
|
Not reported |
- |
No conclusions could be drawn about the effect of MART on corticosteroid dose reduction, compared with care as usual in pediatric patients who have persistent asthma, because of the absence of data. |
|
|
Change in FEV1 score in 12 months
|
Measured by: forced expiratory volume in 1 second Scale: 0 - 100 High better Based on data from 341 participants in 1 study
|
Mean difference Bud/Form MART group versus fixed combination dose of 0.16 (95%CI not reported) |
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious inconsistency, Due to serious publication bias3 |
The evidence is very uncertain about the effect of MART on change in FEV1 after 12 months when compared with care as usual in pediatric patients with persistent asthma (Bisgaard, 2006) |
|
|
All adverse events |
|
Not reported |
|
No conclusions could be drawn about the effect of MART on all adverse events, compared with care as usual in pediatric patients who have persistent asthma, because of the absence of data. |
|
|
Serious adverse events |
Measured by: number of patients presenting with serious adverse events. |
Risk Ratio Bud/Form MART group versus fixed combination dose of 0.12 (95%CI: 0.03 to 0.53) |
Very low Due to serious risk of bias, Due to very serious imprecision, Due to serious publication bias1 |
The evidence is very uncertain about the effect of MART on serious adverse events when compared with care as usual in pediatric patients with persistent asthma (Bisgaard, 2006) |
|
- Risk of Bias: very serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, due to [reason], Imprecision: serious. One study included; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: very serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, due to [reason], Imprecision: very serious. One study included, confidence interval not reported; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: very serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, due to [reason], Imprecision: very serious. One study included, confidence interval not reported; Inconsistency: serious. The direction of the effect is not consistent between the three treatment arms included in the studie. Publication bias: serious. Mostly commercially funded studies;
PICO
Population: adolescents (>12 years) with persistent asthma
Intervention: MART
Comparator: Placebo or other treatment
|
Outcome Timeframe |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
|
|
Comparator |
MART |
||||
|
All excacerbations
|
|
|
- |
No conclusions could be drawn about the effect of MART on all excacerbations, compared with care as usual in adolescent patients who have persistent asthma, because of the absence of data. |
|
|
Severe exacerbations in 6 months (adolescents)
|
Based on data from 1251 participants in 3 studies
|
Rate ratio: 0.56 (CI 95% 0.37 - 0.86)
|
Very low Due to very serious risk of bias, Due to serious imprecision, Due to serious publication bias1 |
The evidence is very uncertain about the effect of MART on severe exacerbation frequency after 6 months when compared with care as usual in adolescent patients with persistent asthma (Rabe, 2006, STEAM trial; Kunna, 2007; Bousquet, 2007) |
|
|
Severe excacerbations in 12 months (adolescents)
|
Based on data from 1011 participants in 3 studies3
|
Rate ratio: 0.38 (CI 95% 0.2 - 0.71)
|
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious publication bias2 |
The evidence is very uncertain about the effect of MART on severe exacerbation frequency in asthma symptom score after 12 months when compared with care as usual in adolescent patients with persistent asthma (Rabe, 2006, SMILE trial; Scichittano, 2004; O’Byrne ,2005) |
|
|
Change in asthma symptoms in 6 months
|
Measured by: Patient diary Scale: 0 - 6 Lower better Based on data from 1251 participants in 3 studies
|
Mean differences |
Very low Due to serious risk of bias, Due to serious inconsistency, Due to serious imprecision, Due to serious publication bias3 |
The evidence is very uncertain about the effect of MART on change in asthma symptom score after 6 months when compared with care as usual in adolescent patients with persistent asthma (Rabe, 2006, STEAM trial; Kunna, 2007; Bousquet, 2007) |
|
|
Change in asthma symptoms in 12 months
|
Measured by: Patient diary Scale: 0 - 6 Lower better Based on data from 1011 participants in 3 studies
|
Mean differences |
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious publication bias4 |
The evidence is very uncertain about the effect of MART on change in asthma symptom score after 12 months when compared with care as usual in adolescent patients with persistent asthma (Rabe, 2006, SMILE trial; Scichittano, 2004; O’Byrne ,2005) |
|
|
Change in ACQ 5 score in 6 months
|
Measured by: ACQ 5 score Scale: 0 - 6 Lower better Based on data from 947 participants in 2 studies
|
Mean differences |
Very low Due to serious risk of bias, Due to serious inconsistency, Due to serious imprecision, Due to serious publication bias5 |
The evidence is very uncertain about the effect of MART on change in ACQ-5 score after 6 months when compared with care as usual in adolescent patients with persistent asthma (Kunna, 2007; Bousquet, 2007) |
|
|
Change in ACQ 5 score in 12 months
|
Measured by: ACQ 5 score Scale: 0 - 6 Lower better Based on data from 354 participants in 1 study
|
Mean differences
0.76 (95%CI 0.43 to 1.32), Rabe (2006) |
Low Due to serious imprecision, Due to serious publication bias6 |
The evidence suggests that MART may result in an improved ACQ 5 score after 12 months when compared to care as usual in adolescent patients with persistent asthma |
|
|
Disease specific quality of life
|
|
Not reported |
- |
No conclusions could be drawn about the effect of MART on disease specific quality of life, compared with care as usual in adolescent patients who have persistent asthma, because of the absence of data. |
|
|
corticosteroid dose reduction |
|
Not reported |
- |
No conclusions could be drawn about the effect of MART on corticosteroid dose reduction, compared with care as usual in adolescent patients who have persistent asthma, because of the absence of data. |
|
|
Change in FEV1 score in 6 months
|
Measured by: forced expiratory volume in 1 second Scale: 0 - 100 High better Based on data from 1251 participants in 3 studies
|
Mean differences
|
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious inconsistency, Due to serious publication bias7 |
The evidence is very uncertain about the effect of MART on change in FEV1 after 6 months when compared with care as usual in adolescent patients with persistent asthma (Rabe, 2006, STEAM trial; Kunna, 2007; Bousquet, 2007) |
|
|
Change in FEV1 score in 12 months
|
Measured by: forced expiratory volume in 1 second Scale: 0 - 100 High better Based on data from 1011 participants in 3 studies
|
Mean differences
|
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious publication bias8 |
The evidence is very uncertain about the effect of MART on change in FEV1 after 12 months when compared with care as ususal in adolescent patients with persistent asthma (Rabe, 2006, SMILE trial; Scichittano, 2004; O’Byrne ,2005) |
|
|
All adverse events |
Measured by: number of patients presenting with serious adverse events. |
Risk ratio’s per treatment group
|
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious publication bias8 |
The evidence is very uncertain about the effect of MART on all adverse events when compared with care as ususal in adolescent patients with persistent asthma (Rabe, 2006, SMILE trial; Scichittano, 2004; O’Byrne ,2005, Rabe, 2006, STEAM trial; Kunna, 2007; Bousquet, 2007) |
|
|
Serious adverse events |
Measured by: number of patients presenting with serious adverse events. |
Risk ratio’s per treatment group
|
Very low Due to serious risk of bias, Due to serious imprecision, Due to serious inconsistency, Due to serious publication bias7 |
The evidence is very uncertain about the effect of MART on serious adverse events when compared with care as ususal in adolescent patients with persistent asthma (Rabe, 2006, SMILE trial; Scichittano, 2004; O’Byrne ,2005, Rabe, 2006, STEAM trial; Kunna, 2007; Bousquet, 2007) |
|
*Data cited from the systematic review of Jorup (2018)
- Risk of Bias: very serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, due to [reason], Inadequate sequence generation/ generation of comparable groups, resulting in potential for selection bias; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: serious. Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate sequence generation/ generation of comparable groups, resulting in potential for selection bias; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, Inadequate/lack of blinding of outcome assessors, resulting in potential for detection bias, Incomplete data and/or large loss to follow up; Inconsistency: serious. The confidence interval of some of the studies do not overlap with those of most included studies/ the point estimate of some of the included studies., The direction of the effect is not consistent between the included studies; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Incomplete data and/or large loss to follow up; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: serious. Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Inadequate/lack of blinding of participants and personnel, resulting in potential for performance bias, Incomplete data and/or large loss to follow up; Inconsistency: serious. The direction of the effect is not consistent between the included studies; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
- Imprecision: serious. Low number of patients, Only data from one study; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: serious. Inadequate/lack of blinding of participants and personnel, resulting in potential for performance bias, Inadequate concealment of allocation during randomization process, resulting in potential for selection bias, Incomplete data and/or large loss to follow up; Inconsistency: serious. The direction of the effect is not consistent between the included studies; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
- Risk of Bias: serious. Inadequate/lack of blinding of participants and personnel, resulting in potential for performance bias, Inadequate concealment of allocation during randomization process, resulting in potential for selection bias; Imprecision: serious. Wide confidence intervals; Publication bias: serious. Mostly commercially funded studies;
Description of studies
Six randomized controlled trials in adolescents aged 12 to 17 years, which are subtracted from one post-hoc analysis (Jorup, 2018), and one randomized controlled trial in pediatrics aged 4 to 11 years (Bisgaard, 2006) reported on the relevant outcome measures and were included in the analysis of the literature.
Pediatric patients: 4-11 years
Bisgaard (2006) is included in our analysis, which performed a prospectively planned sub analysis within the main study of Byrne (2005). Data was obtained from the 12-month randomized double blind and parallel group trial at 41 centers in 12 countries. A total of 341 pediatric patients with an asthma history >= 6 months, ICS at a constant does >= 3 months plus terbutaline as needed, and at least one clinically important asthma exacerbation in the 12 months were included and allocated to fixed-fourfold higher dose BUD plus terbutaline as needed (n=106), fixed combination of BUD/FORM plus terbutaline as needed (n=117) or intervention SMART BUD/FORM maintenance and as needed medication (n=118).
Adolescents: 12-17 years
Jorup, 2018
Jorup (2018) is a post hoc study which collected data through the AstraZeneca database, from six different trials. Studies included were randomized, double blind trials comparing BUD/FORM MART versus active comparator in 12 to 18 years aged patients with persistent asthma (>6 months in duration) according to the ERS/ATS definition. For all studies, patients were enrolled if 1) history of >1 asthma exacerbations prior to study entry 2) used ICS for at least 3 months at constant dose prior to study entry 3) FEV1 in 1 s is a certain percentage (ranging between 50 and 100%) of predicted normal 4) >12% reversibility in increase from baseline FEV1 15 minutes after inhalation of terbutaline.
These studies include the following trials:
- STEP (Scicchitano, 2004)
A randomized, double-blind, double-dummy, active controlled study with a parallel group design conducted at 211 centers in 18 countries (Argentina, Australia, Canada, Czech Republic, Finland, France, Germany, Hungary, Israel, Italy, Mexico, The Netherlands, New Zealand, Norway, Portugal, Russia, South Africa and Turkey). A total of 1890 patients aged 12 to 80 years of age were included. - STAY (O’Byrne, 2005)
A randomized double blind and parallel group trial at 246 centers in 22 countries (not mentioned). A total of (number) patients aged 4 to 80 years were included. Besides the overall inclusion criteria, patients had to have used 12 or more inhalations of as-needed medication for adults and eight or more in children during the last 10 days of run-in. Analysis was done on total group of included patients, however data analysis for the group patients 11 to 17 years of age were performed by Jorup (2018) and analysis for the group patients 4 to 11 years of age were performed by Bisgaard (2006). - SMILE (Rabe, 2006)
A randomized double blind and parallel group trial at 289 centers in 20 countries (mostly in Belgium, Czech Republic, Germany, Hungary, The Netherlands and South Africa). A total of 3394 patients aged 12 years or older were included. - STEAM (Rabe, 2006)
A double blind, randomized, parallel group, active non-controlled study at 77 centers in 9 countries (Argentina, Brazil, China, Denmark, Indonesia, Norway, the Philippines, Spain and Sweden). A total of 697 patients aged 12 to 80 years (but also including patients 11 years of age) were included. - COMPASS (Kuna, 2007)
A randomized, double-blind, double dummy-parallel group conducted at 235 centers in 16 countries (not mentioned). A total of 3172 patients aged >12 years were included. - AHEAD (Bousquet, 2007)
A randomized, double blind, parallel group multinational study conducted in 184 centers in 17 countries. A total of 2309 patients aged >12 years were included, however for only 1056 in the intervention group (budesonide/formoterol) and 1040 patients in the control group, data was available due to discontinuations and loss to follow up.
A separate study search was conducted in PubMed and Cochrane to identify any non-AstraZeneca trials that met the inclusion criteria. However, there were no additional studies identified. Jorup (2018) conducted statistical analysis in subgroup per study (12-17 years). Two analyses were performed: within subgroup analysis (per study) and a meta-analysis of all individual patients’ data (all studies). For the within subgroup analysis, no further stratification analysis was performed since this the number of patients was too low. Analysis of adults aged>18 was done, but the effects could not be compared as the subset of patients was too low. Due to between-studies variations a variation test was conducted, however studies were not GRADED on method. AstraZeneca (sponsor of the studies) developed, funded and performed the analysis (plan) for this study.
Hence, we used the study results of Jorup (2018) since these results could not be abstracted from the six RCT’s. We described the six included RCT’s in Table 2 and outcome measures were GRADED.
Important study characteristics and results are summarized in table 2 per included trial. The assessment of the risk of bias is summarized in the risk of bias tables (under the tab ‘Evidence tabellen’).
Results
Asthma exacerbation frequency:
All exacerbation frequency
Bisgaard (2006) reported the number of pediatrics with all asthma excacerbations, defined as a detoriation in asthma resulting in hospitaltizaiton/emergency department (ED) treatment; treatment with steroids; increase in use of ICS or other additional treatment; morning peak expiratory flow (PEF) <70% of baseline in 2 days. Jorup (2018) did not report on all excacerbations in adolescents.
• Total of all exacerbations (including PEF) in 12 months – pediatrics
Bisgaard (2006) reported that 17 out of 118 patients (14%) in the Bud/Form MART group experienced exacerbations compared to 28 out of 106 (26%) in the fixed dose Budesonide group and 44 out of 117 (38%) in the fixed-dose combination group. Between group differences was reported with a hazard ratio of Bud/Form MART group versus fixed combination dose of 0.34 (95%CI: 0.19 to 0.60) and a hazard ratio of Bud/Form MART group versus fixed dose Budesonide group of 0.49 (95%CI: 0.27 to 0.90).
Severe excacerbation frequency
Bisgaard (2006) reported the number of patients with severe exacerbations in 12 months for pediatric patients (4-11 years). Jorup (2018) reported in six studies total severe exacerbations per total patient years for adolescents. Bisgaard (2006) reported exacerbations requiring medical intervention such as hospitalization/ED treatment, treatment with oral steroids, an increase in ICS via a separate inhaler.
In the study of Jorup (2018), severe exacerbation was defined as the need for OCS (for 3 or more days) and/or hospitalization/ER care. Peak expiratory flow (PEF) was excluded from analysis.
• Total severe exacerbations in 12 months – pediatrics
Bisgaard (2006) reported the number of patients with exacerbations requiring medical intervention. In the Bud/Form MART group 10 out of 118 patients (8%) had experienced exacerbations requiring medical interventions compared to 21 out of 106 (20%) in the fixed dose Budesonide group and 36 out of 117 (31%) in the fixed-dose combination group. Bisgraad reports a reduction in risk by MART of 75% (calculations and 95% CI not reported) versus fixed-dose combinations and 60% (calculations and 95%CI not reported) versus fixed dose budesonide
• Total severe exacerbations per patient years in 6 months - adolescents
Three included studies reported on the number of severe exacerbations (Table 3). The study of Kuna (2007) included two control arms.
Table 3. Total severe exacerbations/total patient-years (n/n) in 6 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud+Terb (control) |
Bud/FORM + TERB (control) |
Sal/FLU + TERB (control) |
Rate ratio (95% CI) |
|
Rabe (2006, STEAM trial) |
2/26 |
12/24 |
- |
- |
0.16 (0.05-0.46) |
|
Kuna (2007) |
7/89 |
- |
10/96 |
- |
0.75 (0.44 – 1.31) |
|
Kuna (2007) |
7/89 |
- |
- |
13/96 |
0.58 (0.34-0.98) |
|
Bousquet (2007) |
11/76 |
- |
- |
17/77 |
0.65 (0.39-1.10) |
Notes: *We reported ratios and CI from Jorup 2018. Different doses of medication are used in the studies. Estimates obtained from Poisson regression models with treatment as a factor, log time as an offset variable and adjusted for overdispersion.
The pooled rate ratio for total severe exacerbations in 6 months was 0.56 (95%CI 0.45 to 0.56) (Figure 1).
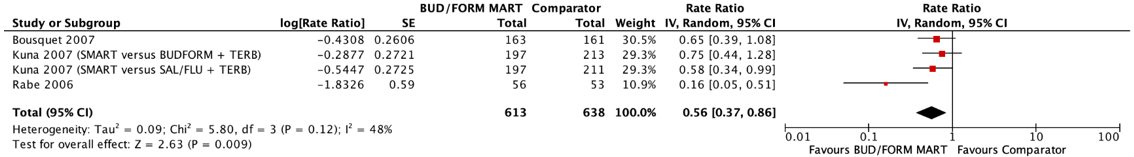
Figure 1. Forrest plot of pooled rate ratio of total severe exacerbations per patient years in 6 months
*Data from Jorup (2018) was used as input for RevMen. Confidence intervals differ slightly from the data as published in Jorup (2018).
• Total severe exacerbations per patient years in 12 months – adolescents
Three included studies reported on the number of severe exacerbations in 12 months (Table 4). The study of Rabe (2006) from the SMILE trial and O’Byrne (2005) included two control arms.
Table 4. Total severe exacerbations/total patient-years (n/n) in 12 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud+Terb (control) |
Bud/FORM + TERB (control) |
Bud/FORM + FORM (control) |
Rate ratio (95% CI) |
|
Rabe (2006) |
15/110 |
- |
21/117 |
- |
0.76 (0.43-1.32) |
|
Rabe (2006) |
15/110 |
- |
- |
22/110 |
0.68 (0.39-1.18) |
|
Scichittano (2004) |
10/48 |
33/61 |
- |
- |
0.39 (0.18-0.82) |
|
O’Byrne (2005) |
6/99 |
40/100 |
- |
- |
0.15 (0.07 – 0.35) |
|
O’Byrne (2005) |
6/99 |
- |
26/90 |
- |
0.21 (0.09-0.49) |
Notes:*We reported ratios and CI from Jorup 2018. Different doses of medication are used in the studies.
The pooled rate ratio for total severe exacerbations in 12 months was 0.38 (95%CI 0.20 to 0.71) (Figure 2).
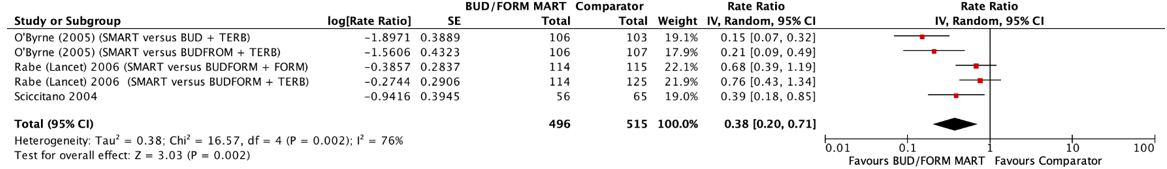
Figure 2. Forrest plot of pooled rate ratio of total severe exacerbations per patient years in 12 months
*Data from Jorup (2018) was used as input for RevMen. Confidence interval differ slightly from the data as published in Jorup (2018).
Changes in asthma symptoms
Asthma symptom score
Bisgaard (2006) reported the number of changes in asthma symptom score in 12 months for pediatric patients (4-11 years). Jorup (2018) included six studies that reported changes in asthma symptom score in 6 and 12 months for adolescents.
• Asthma symptom score in 12 months – pediatrics
Bisgaard (2006) reported only ‘raw’ mean treatment values on asthma symptom score, and no mean differences in asthma symptom score were reported. Calculated mean changes in asthma symptom score resulted in mean differences in a score of -0.50 in the intervention group (Bud/Form MART), compared to the means difference in score of -0.56 in the fixed-Budesonide group and mean difference of score of -0.39 in the fixed dose group. Mean differences between treatments were 0.06 in the intervention group (Bud/Form Mart) versus fixed budesonide and -0.11 between Bud/Form Mart and the fixed-dose combination group.
• Asthma symptom score in 6 months - adolescents
Three included studies reported on the mean asthma symptom score (Table 5). The study of Kuna (2007) included two control arms.
Table 5. Patients with data n/mean (range) in 6 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud+Terb (control) |
Bud/FORM + TERB (control) |
Sal/FLU + TERB (control) |
Mean Difference (95% CI) |
|
Rabe (2006, STEAM trial) |
56/0.39 (0.0-2.8) |
53/0.70 (0.0-3.8) |
- |
- |
0.13 (0.32-0.07) |
|
Kuna (2007) |
197/0.93 (0.0-3.7) |
- |
209/0.89 (0/0-5.1) |
- |
0.05 (–0.09–0.20) |
|
Kuna (2007) |
197/0.93 (0.0-3.7) |
- |
- |
210/0.89 (0.0-4.1) |
0.11 (–0.04–0.25 |
|
Bousquet (2007) |
160/0.90 (0.0-4.1) |
- |
- |
158/1.00 (0.0-4.9) |
–0.09 (–0.27–0.09 |
Notes: *We reported ratios and CI from Jorup 2018. Different doses of medication are used in the studies. Jorup performed an ANCOVA with changes between run-in period mean and treatment period mean as the outcome variable, treatment as a factor and adjusting for the run-in period mean.
• Asthma symptom score in 12 months - adolescents
Three included studies reported on the change of asthma score in 12 months (Table 6). The study of Rabe (2006) from the SMILE trial and O’Byrne (2005) included two control arms.
Table 6. Total exacerbations/total patient-years (n/n) in 12 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud+Terb (control) |
Bud/FORM + TERB (control) |
Bud/FORM + FORM (control) |
Mean difference (95% CI) |
|
Rabe (2006) |
114/0.78 (0.0–2.7) |
- |
124/0.92 (0.0–3.9) |
- |
0.76 (0.43-1.32) |
|
Rabe (2006) |
15/110 |
- |
- |
22/110 |
0.68 (0.39-1.18) |
|
Scichittano (2004) |
10/48 |
33/61 |
- |
- |
0.39 (0.18-0.82) |
|
O’Byrne (2005) |
6/99 |
40/100 |
- |
- |
0.15 (0.07 – 0.35) |
|
O’Byrne (2005) |
6/99 |
26/90 |
26/90 |
- |
0.21 (0.09-0.49) |
Notes: *We reported ratios and CI from Jorup 2018. Different doses of medication are used in the studies.
Jorup performed an ANCOVA with changes between run-in period mean and treatment period mean as the outcome variable, treatment as a factor and adjusting for the run-in period mean.
Asthma control
5-item asthma control questionnaire (ACQ-5) score
Bisgaard (2006) did not report ACQ scores in pediatric patients. Jorup (2018) included three studies reported changes in ACQ score in 6 (n=2) and 12 (n=1) months for adolescents.
• ACQ-5 score in 6 months – adolescents
Two included studies reported on the ACQ score (Table 7). The study of Kuna (2007) included two control arms.
Table 7. Patients with data n/mean (range) in 6 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud/FORM + TERB (control) |
Sal/FLU + TERB (control) |
Mean differences (95% CI)** |
|
Kuna (2007) |
193/0.998 (0.00–3.40 |
212/1.084 (0.00–4.27) |
- |
–0.017 (–0.156–0.123 |
|
Kuna (2007) |
193/0.998 (0.00–3.40 |
- |
206/1.083 (0.00–3.60 |
0.014 (–0.127–0.155) |
|
Bousquet (2007) |
158/1.041 (0.00–3.20) |
- |
156/1.146 (0.00–3.27) |
–0.101 (–0.244–0.042) |
Notes: *We reported ratios and CI from Jorup 2018. Different doses of medication are used in the studies. Jorup performed an ANCOVA with changes between run-in period mean and treatment period mean as the outcome variable, treatment as a factor and adjusting for the run-in period mean.
• ACQ-5 score in 12 months - adolescents
One included studies reported on the ACQ-5 score in 12 months (Table 8). The study of Rabe (2006) from the SMILE trial included two control arms.
Table 8. Patients with data n/mean (range) in 12 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud/FORM + TERB (control) |
Bud/FORM + FORM (control) |
Mean differences (95% CI) |
|
Rabe (2006) |
15/110 |
21/117 |
- |
0.76 (0.43-1.32) |
|
Rabe (2006) |
15/110 |
- |
22/110 |
0.68 (0.39-1.18) |
Notes: *We reported ratios and CI from Jorup 2018. Different doses of medication are used in the studies. Jorup performed an ANCOVA with changes between run-in period mean and treatment period mean as the outcome variable, treatment as a factor and adjusting for the run-in period mean.
Disease specific quality of life
No included studies reported outcomes on quality of life.
Corticosteroid dose reduction
No included studies reported outcomes on corticosteroid dose reduction.
Improvement in lung function
Forced expiratory volume in 1s (FEV1)
Bisgaard (2006) reported the mean change in FEV1 in 12 months for pediatric patients (4-11 years). Jorup (2018) included six studies that reported changes FEV1 in 6 and 12 months for adolescents.
• FEV1 in 12 months – pediatrics
Bisgaard (2006) reported only ‘raw’ mean treatment values on FEV1 score, and no mean differences in FEV1 were reported. Calculated mean FEV1 changes resulted in mean differences of 0.26 FEV1L in both the intervention group (Bud/Form MART) as well as the fixed-dose Budesonide group versus 0.1 FEV1L in the fixed dose combination group. Mean differences between treatments were 0.16 FEV11L in the intervention group (Bud/Form Mart) and there were no differences between Bud/Form MART and the fixed-dose Budesonide group.
• FEV1 in 6 months – adolescents
Three included studies reported on the number of severe exacerbations (Table 9). The study of Kuna (2007) included two control arms.
Table 9. Patients with data n/mean (range) in 7 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud+Terb (control) |
Bud/FORM + TERB (control) |
Sal/FLU + TERB (control) |
Mean differences (95% CI) |
|
Rabe (2006) |
53/2.738 (1.54–3.68) |
51/2.636 (1.43–4.45) |
- |
- |
0.116 (–0.011–0.243) |
|
Kuna (2007) |
196/3.121 (1.58–5.28) |
- |
212/3.149 (1.55–5.82) |
- |
0.012 (–0.063–0.086) |
|
Kuna (2007) |
196/3.121 (1.58–5.28) |
- |
- |
210/3.094 (1.16–5.26) |
0.025 (–0.049–0.100) |
|
Bousquet (2007) |
159/2.953 (1.07–4.98) |
- |
- |
158/2.823 (1.17–4.94) |
0.001 (–0.079–0.081) |
Notes: *We reported mean differences and CI from Jorup 2018. Different doses of medication are used in the studies. Estimates obtained from Poisson regression models with treatment as a factor, log time as an offset variable and adjusted for overdispersion.
• FEV1 in 12 months - adolescents
Three included studies reported on the change of FEV1 in 12 months (Table 10). The study of Rabe (2006) from the SMILE trial and O’Byrne (2005) included two control arms.
Table 10. Patients with data n/mean (range) in 12 months*
|
Study (year) |
Bud/Form MART (intervention)
|
Bud+Terb (control) |
Bud/FORM + TERB (control) |
Bud/FORM + FORM (control) |
Mean Difference (95% CI) |
|
Rabe (2006) |
112/3.118 (1.33–5.40) |
- |
123/3.094 (1.62–5.23) |
- |
0.048 (–0.040–0.137) |
|
Rabe (2006) |
112/3.118 (1.33–5.40) |
- |
- |
114/3.165 (1.53–5.21) |
0.043 (–0.047–0.134) |
|
Scichittano (2004) |
55/2.920 (1.68–4.84) |
65/2.891 (1.39–5.74) |
- |
- |
0.105 (–0.025–0.234) |
|
O’Byrne (2005) |
104/2.805 (1.41–5.03) |
104/2.703 (1.34–4.48) |
- |
- |
0.071 (–0.031–0.173) |
|
O’Byrne (2005) |
104/2.805 (1.41–5.03) |
- |
102/2.901 (1.25–5.19) |
- |
0.055 (–0.048–0.158 |
Notes: *We reported mean differences and CI from Jorup 2018. Different doses of medication are used in the studies. Jorup performed an ANCOVA with changes between run-in period mean and treatment period mean as the outcome variable, treatment as a factor and adjusting for the run-in period mean.
Adverse events
All adverse events
Bisgaard (2006) did not report on all adverse events. Jorup (2018) included six studies that reported all adverse events ongoing during randomized treatment and follow up period if applicable.
• All adverse events in 12 months – pediatrics
Bisgaard (2006) did not report on all adverse events.
• All adverse events in 6 to 12 months – adolescents
All studies included in Jorup (2018) reported on the rate of any adverse event during randomization and follow up period. Results are not reported per follow-up period since Jorup (2018) reported Bud/FORM MART versus treatment comparison pools (see Table 11)
Table 11. All adverse events in BUD/FORM MART group versus treatment comparison pools: all adverse events*/number of patients (%).
|
Study (year) |
Bud/Form MART (intervention) |
Bud+Terb (control) |
Bud/FORM + TERB (control) |
SAL/FLU + TERB (control) |
Risk ratio (95% CI) |
|
Rabe (2006a), Scichittano (2004), O’Byrne (2005) |
114/218 (52.3%) |
123/225 (54.7%) |
- |
- |
0.96 (0.80 to 1.14) |
|
O’Byrne (2005), Rabe (2006b), Kuna (2007) |
195/417 (46.8%) |
- |
180/441 (40.8%) |
- |
1.15 (0.98 to 1.33) |
|
Kuna (2007), Bousquet (2007) |
119/360 (33.1%) |
- |
- |
117/372 (31.5%) |
1.08 (0.79, 1.47)
|
Notes: *Patients with multiple adverse events in the same category were counted as one whereas patients with adverse events in multiple categories were counted in each of those categories.
Serious adverse events
Bisgaard (2006) did report on the rate of serious adverse events Jorup (2018) included six studies that reported all serious adverse events ongoing during randomized treatment and follow up period if applicable.
• Serious adverse events in 12 months – pediatrics
Bisgaard (2006) reported on the rate of serious adverse events. Calculated risk ratio in the intervention group (Bud/Form MART) versus the fixed-dose combination group is 0.12 95%CI: 0.03 to 0.53) and calculated risk ratio of the same intervention group versus fixed budesonide group is 0.36 (95%CI: 0.07 to 1.81).
• Serious adverse events in 6 to 12 months – adolescents
All studies included in Jorup (2018) reported on the rate of serious adverse events during randomization and follow up period. Results are not reported per follow-up period since Jorup (2018) reported Bud/FORM MART versus treatment comparison pools (see Table 12)
Table 12. Serious adverse events in BUD/FORM MART group versus treatment comparison pools: serious adverse events*/number of patients (%).
|
Study (year) |
Bud/Form MART (intervention) |
Bud+Terb (control) |
Bud/FORM + TERB (control) |
SAL/FLU + TERB (control) |
Risk ratio (95% CI) |
|
Rabe (2006a), Scichittano (2004), O’Byrne (2005) |
8/218 (3.7%) |
14/225 (6.2%) |
- |
- |
0.59 (0.25 to 1.38) |
|
O’Byrne (2005), Rabe (2006b), Kuna (2007) |
10/417 (2.4%) |
- |
13/441 (2.8%) |
- |
0.81 (0.36 to 1.84) |
|
Kuna (2007), Bousquet (2007) |
3/360 (0.8%) |
- |
- |
5/372 (1.3%) |
0.62 (0.15, 2/58)
|
Notes: *Patients with multiple adverse events in the same category were counted as one whereas patients with adverse events in multiple categories were counted in each of those categories.
A systematic review of the literature was performed to answer the following question(s):
What are the favourable and unfavourable effects of MART, compared with placebo or care as usual, in children with asthma?
Table 1. PICO
|
Patients |
1. children 4 to 12 years with (persistent) asthma. 2. Children (12-<18 years) with (persistent) asthma |
|
Intervention |
Maintenance and reliever therapy MART, which is usually one inhaler containing both a corticosteroid (ICS) and a rapid long-acting bronchodilitator (formoterol) |
|
Control |
Placebo or care as usual |
|
Outcomes |
Asthma exacerbation frequency, asthma symptoms, asthma control, disease specific quality of life (AQLQ), change/improvement in lung function (FEV1), cumulative dose of inhaled steroids, adverse events. |
|
Other selection criteria |
Study design:
|
Relevant outcome measures
The guideline panel considered improvement in severe exacerbation frequency, asthma symptoms and asthma control (ACQ-5 score) as critical outcome measures for decision making; and disease specific quality of life (AQLQ), improvement in lung function (FEV1), cumulative dose of inhaled steroids and adverse events as important outcome measures for decision making.
A priori, the guideline panel did not define the outcome measures listed above but used the definitions used in the studies. The guideline panel would recommend future guidelines to use the recent published Core Outcome Measures sets for pediatric and adult Severe Asthma (COSMA) as a framework to further harmonize outcome measurements in the future (Khaleva, 2023)The guideline panel focusses on the most important outcomes and defined the following thresholds as a minimal clinically (patient) important difference for each outcome measure:
| 1. |
Asthma exacerbation frequency |
| 2. |
Asthma symptom score (based on patient diary entries, a total score of 6 with 6 being worse) |
| 3. |
Asthma control: |
| 4. |
Disease specific quality of life:
|
| 5. |
Improvement in lung function: |
| 6. |
Inhalation corticosteroid dose reduction: decrease in daily dose of ≥ 50% |
| 7. |
Side effects/ adverse events:
|
Search and select (Methods)
A systematic literature search was performed by a medical information specialist using the following bibliographic databases: Embase.com and Ovid/Medline. Both databases were searched from 01-01-2000 to 7-04-2025 for systematic reviews and RCTs. Systematic searches were completed using a combination of controlled vocabulary/subject headings (e.g., Emtree-terms, MeSH) wherever they were available and natural language keywords. The overall search strategy was derived from two primary search concepts: (1) asthma 2) children and (3) anti-inflammatory reliever therapy (AIR)/single maintenance and reliever therapy (SMART/MART). Duplicates were removed using EndNote software. After deduplication a total of 1115 records were imported for title/abstract screening. Initially, 40 studies were selected based on title and abstract screening based on the PICO criteria. After reading the full text, 38 studies were excluded (see the exclusion table under the tab ‘Evidence tabellen’), and 2 main studies were included. Both studies were post-hoc analysis, of which one study analysed six randomized controlled trials (RCT) and one study analyzed one RCT.
Studies that report on AIR in adolescents and/or pediatrics will be described in a separate module of this guideline.
- Beasley R, Harrison T, Peterson S, Gustafson P, Hamblin A, Bengtsson T, Fagerås M. Evaluation of Budesonide-Formoterol for Maintenance and Reliever Therapy Among Patients With Poorly Controlled Asthma: A Systematic Review and Meta-analysis. JAMA Netw Open. 2022 Mar 1;5(3):e220615. doi: 10.1001/jamanetworkopen.2022.0615. Erratum in: JAMA Netw Open. 2022 May 2;5(5):e2216068. doi: 10.1001/jamanetworkopen.2022.16068. PMID: 35230437; PMCID: PMC8889464.
- Bisgaard H, Le Roux P, Bjåmer D, Dymek A, Vermeulen JH, Hultquist C. Budesonide/formoterol maintenance plus reliever therapy: a new strategy in pediatric asthma. Chest. 2006 Dec;130(6):1733-43. doi: 10.1378/chest.130.6.1733. PMID: 17166990.
- Bonini M, Di Paolo M, Bagnasco D, Baiardini I, Braido F, Caminati M, Carpagnano E, Contoli M, Corsico A, Del Giacco S, Heffler E, Lombardi C, Menichini I, Milanese M, Scichilone N, Senna G, Canonica GW. Minimal clinically important difference for asthma endpoints: an expert consensus report. Eur Respir Rev. 2020 Jun 3;29(156):190137. doi: 10.1183/16000617.0137-2019. PMID: 32499305; PMCID: PMC9488652.
- Bousquet J, Boulet LP, Peters MJ, Magnussen H, Quiralte J, Martinez-Aguilar NE, Carlsheimer A. Budesonide/formoterol for maintenance and relief in uncontrolled asthma vs. high-dose salmeterol/fluticasone. Respir Med. 2007 Dec;101(12):2437-46. doi: 10.1016/j.rmed.2007.07.014. Epub 2007 Oct 1. Erratum in: Respir Med. 2008 Jun;102(6):937-8. PMID: 17905575.
- Corren J, Parnes JR, Wang L, Mo M, Roseti SL, Griffiths JM, van der Merwe R. Tezepelumab in Adults with Uncontrolled Asthma. N Engl J Med. 2017 Sep 7;377(10):936-946. doi: 10.1056/NEJMoa1704064. Erratum in: N Engl J Med. 2019 May 23;380(21):2082. doi: 10.1056/NEJMx180026. PMID: 28877011.
- Donohue JF. Minimal clinically important differences in COPD lung function. COPD. 2005 Mar;2(1):111-24. doi: 10.1081/copd-200053377. PMID: 17136971.
- Global Initiatieve for Asthma. Global Strategy for Asthma Management and Prevention, 2024. Updated May 2024. Available from: www.ginasthma.org
- Jones PW. Interpreting thresholds for a clinically significant change in health status in asthma and COPD. Eur Respir J. 2002 Mar;19(3):398-404. doi: 10.1183/09031936.02.00063702. PMID: 11936514.
- Juniper EF, Guyatt GH, Willan A, Griffith LE. Determining a minimal important change in a disease-specific Quality of Life Questionnaire. J Clin Epidemiol. 1994 Jan;47(1):81-7. doi: 10.1016/0895-4356(94)90036-1. PMID: 8283197
- Jorup C, Lythgoe D, Bisgaard H. Budesonide/formoterol maintenance and reliever therapy in adolescent patients with asthma. Eur Respir J 2018; 51: 1701688 [https://doi.org/10.1183/ 13993003.01688-2017].
- Khaleva E, Rattu A, Brightling C, Bush A, Bossios A, Bourdin A, et al. Development of Core Outcome Measures sets for paediatric and adult Severe Asthma (COMSA). Eur Respir J. 2023 Apr 3;61(4):2200606. doi:10.1183/13993003.00606-2022. PMID: 36229046; PMCID: PMC10069873.
- Kuna P, Peters MJ, Manjra AI, Jorup C, Naya IP, Martínez-Jimenez NE, Buhl R. Effect of budesonide/formoterol maintenance and reliever therapy on asthma exacerbations. Int J Clin Pract. 2007 May;61(5):725-36. doi: 10.1111/j.1742-1241.2007.01338.x. Epub 2007 Mar 16. PMID: 17362472; PMCID: PMC1920547.
- Menzies-Gow A, Corren J, Bourdin A, Chupp G, Israel E, Wechsler ME, Brightling CE, Griffiths JM, Hellqvist Å, Bowen K, Kaur P, Almqvist G, Ponnarambil S, Colice G. Tezepelumab in Adults and Adolescents with Severe, Uncontrolled Asthma. N Engl J Med. 2021 May 13;384(19):1800-1809. doi: 10.1056/NEJMoa2034975. PMID: 33979488.
- O'Byrne PM, Bisgaard H, Godard PP, Pistolesi M, Palmqvist M, Zhu Y, Ekström T, Bateman ED. Budesonide/formoterol combination therapy as both maintenance and reliever medication in asthma. Am J Respir Crit Care Med. 2005 Jan 15;171(2):129-36. doi: 10.1164/rccm.200407-884OC. Epub 2004 Oct 22. PMID: 15502112.
- Papi A, Chipps BE, Beasley R, Panettieri RA Jr, Israel E, Cooper M, Dunsire L, Jeynes-Ellis A, Johnsson E, Rees R, Cappelletti C, Albers FC. Albuterol-Budesonide Fixed-Dose Combination Rescue Inhaler for Asthma. N Engl J Med. 2022 Jun 2;386(22):2071-2083. doi: 10.1056/NEJMoa2203163. Epub 2022 May 15. PMID: 35569035.
- Rabe KF, Atienza T, Magyar P, Larsson P, Jorup C, Lalloo UG. Effect of budesonide in combination with formoterol for reliever therapy in asthma exacerbations: a randomised controlled, double-blind study. Lancet. 2006 Aug 26;368(9537):744-53. doi: 10.1016/S0140-6736(06)69284-2. PMID: 16935685.
- Rabe KF, Pizzichini E, Ställberg B, Romero S, Balanzat AM, Atienza T, Lier PA, Jorup C. Budesonide/formoterol in a single inhaler for maintenance and relief in mild-to-moderate asthma: a randomized, double-blind trial. Chest. 2006 Feb;129(2):246-256. doi: 10.1378/chest.129.2.246. PMID: 16478838.
- Scicchitano R, Aalbers R, Ukena D, Manjra A, Fouquert L, Centanni S, Boulet LP, Naya IP, Hultquist C. Efficacy and safety of budesonide/formoterol single inhaler therapy versus a higher dose of budesonide in moderate to severe asthma. Curr Med Res Opin. 2004 Sep;20(9):1403-18. doi: 10.1185/030079904X2051. PMID: 15383189.
- Stanojevic S, Kaminsky DA, Miller MR, Thompson B, Aliverti A, Barjaktarevic I, Cooper BG, Culver B, Derom E, Hall GL, Hallstrand TS, Leuppi JD, MacIntyre N, McCormack M, Rosenfeld M, Swenson ER. ERS/ATS technical standard on interpretive strategies for routine lung function tests. Eur Respir J. 2022 Jul 13;60(1):2101499. doi: 10.1183/13993003.01499-2021. PMID: 34949706.
- Wechsler ME, Menzies-Gow A, Brightling CE, Kuna P, Korn S, Welte T, Griffiths JM, Sałapa K, Hellqvist Å, Almqvist G, Lal H, Kaur P, Skärby T, Colice G; SOURCE study group. Evaluation of the oral corticosteroid-sparing effect of tezepelumab in adults with oral corticosteroid-dependent asthma (SOURCE): a randomised, placebo-controlled, phase 3 study. Lancet Respir Med. 2022 Jul;10(7):650-660. doi: 10.1016/S2213-2600(21)00537-3. Epub 2022 Mar 29. Erratum in: Lancet Respir Med. 2022 Jul;10(7):e72. doi: 10.1016/S2213-2600(22)00128-X. PMID: 35364018.
- National Institute for Health and Care Excellence (NICE). Asthma: diagnosis, monitoring and chronic asthma management (BTS/NICE/SIGN). NICE Guideline NG245. London: NICE; 2024. Available from: https://www.nice.org.uk/guidance/NG245
- Zorginstituut Nederland. Transmurale leidraad klimaatbewust voorschrijven van inhalatiemedicatie. Diemen: Zorginstituut Nederland; 2025. Available from: https://www.zorginstituutnederland.nl/documenten/2025/04/09/transmurale-leidraad-klimaatbewust-voorschrijven-van-inhalatiemedicatie
Table 2. Characteristics of included studies
|
Study |
Participants* |
Comparison |
Follow-up |
Outcome measures |
Comments |
Risk of bias (per outcome measure)* |
|
Pediatrics (4-12 years) |
||||||
|
Bisgaard 2006 |
N at baseline Intervention: 118
Age (mean, range) Pediatric population |
See O’Byrne (2005) for detailed description of the study using Symbicort |
12 months |
Exacerbation frequency:
-Number of patients with severe exacerbations in 12 months -Asthma symptom score (mean)
Asthma control:
Adverse events -Number of patients with serious adverse events in 12 months
|
- Study was not powered to detect differences in the pediatric subgroup. Initially, 100 patients were included to compare safety and efficacy of each treatment regiment. Analyses were performed on an intention to treat analysis. |
LOW (all other outcomes) |
|
Adolescents (11 – 18 years) |
||||||
|
Jorup, 2018 |
Post hoc analyses of 6 RCTs (Scicchitano, 2004; O’Byrne, 2005; Rabe – SMILE trial, 2006; Rabe – STEAM trial, 2006; Kuna, 2007; Bousquet 2007)
Age (mean, range) Adolescent population |
Intervention BUD/FORM MART |
>6 months |
Results of all included RCT’s are described in this table. |
|
|
|
Scicchitano, 2004
|
N at baseline Intervention:56
Adolescent population |
Intervention
Control: BUD 160 micrograms, 2 inhalations twice daily + terbutaline 0.4 mg as needed
|
12 months |
Results are described in tables or visualized in the forest plot in this guideline. |
|
LOW (all outcomes) |
|
O’Byrne, 2005
|
N at baseline Adolescent population (n=316) Intervention: 106
Age (mean, range) Adolescent population |
Intervention
Control: Control 1: BUD/FORM 80/4.5 micrograms, 1 inhalation twice daily + terbutaline 0.4 mg as needed
|
12 months |
Results are described in tables or visualized in the forest plot in this guideline. |
The funders of the study contributed to the study design and data interpretation |
LOW (all outcomes) |
|
Rabe, 2006 (SMILE trial) |
N at baseline Intervention: 1113 Control 1: 1140 Intervention:114
Adolescent population |
Intervention
Control 1: BUD/FROM 160/4.5 micrograms, 1 inhalation twice daily + FORM 4.5 microgram as needed
|
12 months |
Results are described in tables or visualized in the forest plot in this guideline. |
The funders of the study contributed to the study design and data interpretation |
LOW (all other outcomes) |
|
Rabe, 2006 (STEAM trial)
|
N at baseline Adolescent population (n=109) Intervention:56
Age (mean, range) Adolescent population |
Intervention
Control: BUD 160 micrograms, 2 inhalations once daily + terbutaline 0.4 mg as needed
|
6 months |
Results are described in tables or visualized in the forest plot in this guideline. |
The funders of the study contributed to the study design and data interpretation |
LOW (all other outcomes) |
|
Kuna, 2007 |
N at baseline Adolescent population (n=623) Intervention:197 Age (mean, range) Adolescent population |
Intervention
Control: BUD/FORM 320/9 micrograms, 1 inhalation twice daily + terbutaline 0.4 mg as needed or
|
6 months |
Results are described in tables or visualized in the forest plot in this guideline. |
The funders of the study contributed to the study design and data interpretation |
LOW (all other outcomes) |
|
Bousquet 2007 |
N at baseline Adolescent population (n=324) Intervention:163
Age (mean, range) Adolescent population |
Intervention
Control: Salmeterol/fluticasone 50/500 microgram, 1 inhalation twice daily + terbutaline 0.4 mg as needed.
|
6 months |
Results are described in tables or visualized in the forest plot in this guideline. |
The funders of the study contributed to the study design and data interpretation |
LOW (all other outcomes) |
*For further details, see risk of bias table.
|
Study reference
(first author, publication year) |
Was the allocation sequence adequately generated?
Definitely yes Probably yes Probably no Definitely no |
Was the allocation adequately concealed?
Definitely yes Probably yes Probably no Definitely no |
Blinding: Was knowledge of the allocated interventions adequately prevented?
Were patients blinded?
Were healthcare providers blinded?
Were data collectors blinded?
Were outcome assessors blinded?
Were data analysts blinded?
Definitely yes Probably yes Probably no Definitely no |
Was loss to follow-up (missing outcome data) infrequent?
Definitely yes Probably yes Probably no Definitely no |
Are reports of the study free of selective outcome reporting?
Definitely yes Probably yes Probably no Definitely no |
Was the study apparently free of other problems that could put it at a risk of bias?
Definitely yes Probably yes Probably no Definitely no |
Overall risk of bias If applicable/necessary, per outcome measure
LOW Some concerns HIGH
|
|
Included studies on adolescents |
|||||||
|
Jorup (2018, see following included RCT’s) |
|
|
|
|
|
For all articles appearant that:
|
|
|
Included articles in Jorup (2018) |
|||||||
|
Rabe, 2006 (Chest) |
Not reported
|
Not reported
|
Probably no;
Reason: |
Probably yes;
Reason: 58 patients discontinued the study (e.g. due to adverse events, were not available for follow up, other reasons). Intention to treat analysis was used. |
Definitely yes;
Reason: All relevant outcomes were reported, and patients showed high levels of adherence to maintenance medications in both groups (>97%). |
Probably no ;
See Jorup, 2018 |
High |
|
Sciccitano, 2004 |
Definitely yes;
Reason: a computarised randomisation was conducted using pc program RandLink. Patients were randomized in balanced blocks using the code of enrolment. |
Probably yes;
Reason: the randomisation code was prepared at the sponsor site by person not involved in data analysis |
Probably yes:
Reason: Patients received three identical Turbohalers (labelled as 1,2, or 3). |
Probably yes
Reason: in intervention group n=144 discontinuations occurred (e.g. due to adverse events, lost to follow up and other reasons) and in the control group 173 patients discontinued the study. |
Definitely yes
Reason: All relevant outcomes were reported, and patients showed high levels of adherence to maintenance medications in both groups (>97%). |
Probably no:
Reason:
|
Some concerns |
|
O’Byrne, 2005 |
Definitaly yes:
Reason: assigned according to a computer-generated randomization scheme. Patients were randomized in blocks. |
Not reported |
Probably yes:
Reason: Patients received three identical Turbohalers (labelled as 1,2, or 3). |
Probably yes:
Reason: Some loss to follow up (n=6 in total of 2760). There were 437 patients with one or more protocol deviations, mostly due to randomization in error. Nevertheless, all data was analysed since no violation reported would justify exclusion.
ITT was used for patients who received one dose or more of study drug. |
Probably yes
Reason: All relevant outcomes were reported. Adherence to using the medication was however not measured. |
Probably no:
Reason:
|
High concerns |
|
Rabe, 2006 (Lancet) |
Definitaly yes:
Reason: the randomisation schedule was computer generated at AstraZeneca Research and Development. Thereafter, patients were sequentially assigned a randomisation code by the incestiator from the computer generated list. |
Defintely yes;
Reason: The randomisation was done by a person indepent of the study team |
Probably yes:
Reason Patients received medication via identical inhalers (turbohaler matched Symbicort inhalers). |
Probably yes:
Reason: Some data was not included in analysis due to no treatment/data available (n=12 from a total of 3394). There were 474 patients with one or more protocol deviations. Nevertheless, all data was analysed since no violation reported would justify exclusion.
|
Probably yes |
Definitely no:
Reason:
|
Some concerns |
|
Kuna, 2007 |
Definitely yes:
Reason: The randomisation schedule was computer-generated at AstraZeneca Research and Development, Charnwood, UK |
Definitely yes:
Reason: individual treatments codes and code envelopes. Envelopes were only to be opened in medical emergencies. |
Probably yes:
Reason: patients received medication via identical (number of) inhalers |
Probably yes:
Reason: Some data was not included in analysis due to no treatment/data available (n=163 from a total of 3172). There were 409 protocol deviations in 327 patients. The study did not report what was done (with respect to statistical analysis) with the deviations.
|
Probably yes |
Defintely no:
|
Some concerns |
|
Bousquet, 2007 |
Definitely yes:
Reason: Randomisation codes were sequentially assigned in balanced blocks from a computer-generated list at AstraZeneca R&D, Lund, Sweden |
Not reported |
Probably yes:
Reason: patients received medication via identical (number of) inhalers |
Probably yes:
Reason: Some data was not included in analysis due to no treatment/data available (n=213 from a total of 2309). Full analysis were available for 2304 patients (5 patients lost due to no treatment/data).
No report on strategy for protocol deviations were made. All patients with data after randomisation were included in ITT population.
|
Probably yes |
Defintely no:
|
High concerns |
|
Included studies on children |
|||||||
|
Bisgaard, 2006 (see O’Byrne, 2005) |
see O’Byrne, 2005 |
see O’Byrne, 2005 |
see O’Byrne, 2005 |
Reason:
All data was included in the analysis (while there were n=33 discontinuations from a total of 341). There were 34 patients with one ore more protocol deviations. None of the protocol deviations justified exclusion. |
Probably yes |
Definitely no:
|
High concerns |
|
Reference |
Reason for exclusion |
|
Biener L, Mümmler C, Hinze CA, Suhling H, Korn S, Fisser C, Biener A, Pizarro C, Lenoir A, Hackl C, Skowasch D, Milger K. Real-World Data on Tezepelumab in Patients With Severe Asthma in Germany. J Allergy Clin Immunol Pract. 2024 Sep;12(9):2399-2407.e5. doi: 10.1016/j.jaip.2024.05.052. Epub 2024 Jun 10. PMID: 38866104. |
wrong study design: retrospective, multicenter study |
|
Brightling CE, Caminati M, Llanos JP, Caveney S, Kotalik A, Griffiths JM, Lundahl A, Israel E, Pavord ID, Wechsler ME, Porsbjerg C, Corren J, Gołąbek M, Martin N, Ponnarambil S. Biomarkers and clinical outcomes after tezepelumab cessation: Extended follow-up from the 2-year DESTINATION study. Ann Allergy Asthma Immunol. 2024 Sep;133(3):310-317.e4. doi: 10.1016/j.anai.2024.04.031. Epub 2024 Apr 30. PMID: 38697286. |
sub-analysis of DESTINATION trial, course of biomarkers and outcomes over time after the last dose of tezepelumab |
|
Carr TF, Moore WC, Kraft M, Brusselle G, Castro M, Chupp GL, Wechsler ME, Hunter G, Lindsley AW, Llanos JP, Burke LK, Chandarana S, Ambrose CS. Efficacy of Tezepelumab in Patients with Severe, Uncontrolled Asthma Across Multiple Clinically Relevant Subgroups in the NAVIGATOR Study. Adv Ther. 2024 Jul;41(7):2978-2990. doi: 10.1007/s12325-024-02889-8. Epub 2024 May 27. PMID: 38802635; PMCID: PMC11213736. |
subgroup analysis of NAVIGATOR trial, for 'clinically relevant' subgroups of patients |
|
Chagas GCL, Xavier D, Gomes L, Ferri-Guerra J, Oquet REH. Effects of Tezepelumab on Quality of Life of Patients with Moderate-to-Severe, Uncontrolled Asthma: Systematic Review and Meta-Analysis. Curr Allergy Asthma Rep. 2023 Jun;23(6):287-298. doi: 10.1007/s11882-023-01085-y. Epub 2023 May 16. PMID: 37191902. |
meta-analysis only including QoL outcomes |
|
Corren J, Ambrose CS, Griffiths JM, Hellqvist Å, Lindsley AW, Llanos JP, Colice G, Menzies-Gow A. Efficacy of tezepelumab in patients with evidence of severe allergic asthma: Results from the phase 3 NAVIGATOR study. Clin Exp Allergy. 2023 Apr;53(4):417-428. doi: 10.1111/cea.14256. Epub 2022 Dec 12. PMID: 36507576. |
sub-analysis of the NAVIGATOR trial: patients with allergic asthma |
|
Corren J, Ambrose CS, Sałapa K, Roseti SL, Griffiths JM, Parnes JR, Colice G. Efficacy of Tezepelumab in Patients with Severe, Uncontrolled Asthma and Perennial Allergy. J Allergy Clin Immunol Pract. 2021 Dec;9(12):4334-4342.e6. doi: 10.1016/j.jaip.2021.07.045. Epub 2021 Aug 3. PMID: 34358701. |
wrong P (subgroup): patients with asthma and allergies |
|
Corren J, Garcia Gil E, Griffiths JM, Parnes JR, van der Merwe R, Sałapa K, O'Quinn S. Tezepelumab improves patient-reported outcomes in patients with severe, uncontrolled asthma in PATHWAY. Ann Allergy Asthma Immunol. 2021 Feb;126(2):187-193. doi: 10.1016/j.anai.2020.10.008. Epub 2020 Oct 23. PMID: 33169672. |
wrong comparison: subgroups according to ASC-6 scores |
|
Corren J, Karpefors M, Hellqvist Å, Parnes JR, Colice G. Tezepelumab Reduces Exacerbations Across All Seasons in Patients with Severe, Uncontrolled Asthma: A Post Hoc Analysis of the PATHWAY Phase 2b Study. J Asthma Allergy. 2021 Jan 11;14:1-11. doi: 10.2147/JAA.S286036. PMID: 33469316; PMCID: PMC7810672. |
outcome: asthma exacerbations according to seasons (post hoc analysis of phase 2 trial) |
|
Corren J, Menzies-Gow A, Chupp G, Israel E, Korn S, Cook B, Ambrose CS, Hellqvist Å, Roseti SL, Molfino NA, Llanos JP, Martin N, Bowen K, Griffiths JM, Parnes JR, Colice G. Efficacy of Tezepelumab in Severe, Uncontrolled Asthma: Pooled Analysis of the PATHWAY and NAVIGATOR Clinical Trials. Am J Respir Crit Care Med. 2023 Jul 1;208(1):13-24. doi: 10.1164/rccm.202210-2005OC. PMID: 37015033; PMCID: PMC10870853. |
sub-analysis of PATHWAY and NAVIGATOR trials in 'clinically relevant subgroups' defined by inflammatory biomarker levels or clinical characteristics |
|
Diver S, Khalfaoui L, Emson C, Wenzel SE, Menzies-Gow A, Wechsler ME, Johnston J, Molfino N, Parnes JR, Megally A, Colice G, Brightling CE; CASCADE study investigators. Effect of tezepelumab on airway inflammatory cells, remodelling, and hyperresponsiveness in patients with moderate-to-severe uncontrolled asthma (CASCADE): a double-blind, randomised, placebo-controlled, phase 2 trial. Lancet Respir Med. 2021 Nov;9(11):1299-1312. doi: 10.1016/S2213-2600(21)00226-5. Epub 2021 Jul 10. Erratum in: Lancet Respir Med. 2021 Nov;9(11):e106. doi: 10.1016/S2213-2600(21)00446-X. PMID: 34256031. |
results of CASCADE trial; does not fit the pico: wrong outcome (remodelling, and hyperresponsiveness) |
|
Emson C, Corren J, Sałapa K, Hellqvist Å, Parnes JR, Colice G. Efficacy of Tezepelumab in Patients with Severe, Uncontrolled Asthma with and without Nasal Polyposis: A Post Hoc Analysis of the Phase 2b PATHWAY Study. J Asthma Allergy. 2021 Feb 3;14:91-99. doi: 10.2147/JAA.S288260. PMID: 33568920; PMCID: PMC7868291. |
wrong publication type: study protocol |
|
Emson C, Diver S, Chachi L, Megally A, Small C, Downie J, Parnes JR, Bowen K, Colice G, Brightling CE. CASCADE: a phase 2, randomized, double-blind, placebo-controlled, parallel-group trial to evaluate the effect of tezepelumab on airway inflammation in patients with uncontrolled asthma. Respir Res. 2020 Oct 13;21(1):265. doi: 10.1186/s12931-020-01513-x. PMID: 33050900; PMCID: PMC7550845. |
wrong P: pateints with nasal polyps |
|
Israel E, Castro M, Ambrose CS, Llanos JP, Molfino NA, Martin NL, Ponnarambil SS, Martin N. Efficacy of tezepelumab in patients with severe asthma and persistent airflow obstruction. ERJ Open Res. 2024 Nov 25;10(6):00164-2024. doi: 10.1183/23120541.00164-2024. PMID: 39588080; PMCID: PMC11587167. |
post hoc analysis of PATHWAY and NAVIGATOR trial; subgroup of patients: severe asthma AND persistent airflow obstruction |
|
Korn S, Cook B, Simpson LJ, Llanos JP, Ambrose CS. Efficacy of Biologics in Severe, Uncontrolled Asthma Stratified by Blood Eosinophil Count: A Systematic Review. Adv Ther. 2023 Jul;40(7):2944-2964. doi: 10.1007/s12325-023-02514-0. Epub 2023 May 26. PMID: 37233876; PMCID: PMC10272272. |
wrong comparion: overview of different biologics by baseline blood eosinophil count |
|
Laidlaw TM, Menzies-Gow A, Caveney S, Han JK, Martin N, Israel E, Lee JK, Llanos JP, Martin N, Megally A, Parikh B, Vong S, Welte T, Corren J. Tezepelumab Efficacy in Patients with Severe, Uncontrolled Asthma with Comorbid Nasal Polyps in NAVIGATOR. J Asthma Allergy. 2023 Sep 4;16:915-932. doi: 10.2147/JAA.S413064. Erratum in: J Asthma Allergy. 2023 Sep 27;16:1053-1054. doi: 10.2147/JAA.S441410. PMID: 37692126; PMCID: PMC10488831. |
sub-analysis of NAVIGATOR trial: wrong subgroup of patients: comorbid nasal polyps |
|
Menzies-Gow A, Ambrose CS, Colice G, Hunter G, Cook B, Molfino NA, Llanos JP, Israel E. Effect of Tezepelumab on Lung Function in Patients With Severe, Uncontrolled Asthma in the Phase 3 NAVIGATOR Study. Adv Ther. 2023 Nov;40(11):4957-4971. doi: 10.1007/s12325-023-02659-y. Epub 2023 Sep 19. PMID: 37723356; PMCID: PMC10567907. |
wrong outcome: sub-analysis of NAVIGATOR trial: lung function (additional long F parameters) |
|
Menzies-Gow A, Bourdin A, Chupp G, Israel E, Hellqvist Å, Hunter G, Roseti SL, Ambrose CS, Llanos JP, Cook B, Corren J, Colice G. Effect of tezepelumab on healthcare utilization in patients with severe, uncontrolled asthma: The NAVIGATOR study. Ann Allergy Asthma Immunol. 2023 Sep;131(3):343-348.e2. doi: 10.1016/j.anai.2023.05.028. Epub 2023 May 30. PMID: 37263380. |
does not fit the pico: wrong outcome= asthma-related healthcare utilization |
|
Menzies-Gow A, Colice G, Griffiths JM, Almqvist G, Ponnarambil S, Kaur P, Ruberto G, Bowen K, Hellqvist Å, Mo M, Garcia Gil E. NAVIGATOR: a phase 3 multicentre, randomized, double-blind, placebo-controlled, parallel-group trial to evaluate the efficacy and safety of tezepelumab in adults and adolescents with severe, uncontrolled asthma. Respir Res. 2020 Oct 13;21(1):266. doi: 10.1186/s12931-020-01526-6. PMID: 33050934; PMCID: PMC7550847. |
trial protocol NAVIGATOR |
|
Menzies-Gow A, Ponnarambil S, Downie J, Bowen K, Hellqvist Å, Colice G. DESTINATION: a phase 3, multicentre, randomized, double-blind, placebo-controlled, parallel-group trial to evaluate the long-term safety and tolerability of tezepelumab in adults and adolescents with severe, uncontrolled asthma. Respir Res. 2020 Oct 21;21(1):279. doi: 10.1186/s12931-020-01541-7. PMID: 33087119; PMCID: PMC7576983. |
trial protocol DESTINATION |
|
Menzies-Gow A, Wechsler ME, Brightling CE, Korn S, Corren J, Israel E, Chupp G, Bednarczyk A, Ponnarambil S, Caveney S, Almqvist G, Gołąbek M, Simonsson L, Lawson K, Bowen K, Colice G; DESTINATION study investigators. Long-term safety and efficacy of tezepelumab in people with severe, uncontrolled asthma (DESTINATION): a randomised, placebo-controlled extension study. Lancet Respir Med. 2023 May;11(5):425-438. doi: 10.1016/S2213-2600(22)00492-1. Epub 2023 Jan 23. Erratum in: Lancet Respir Med. 2023 Mar;11(3):e25. doi: 10.1016/S2213-2600(23)00048-6. PMID: 36702146. |
not hypothesis driven, exploratory analysis in an extention trial |
|
Nopsopon T, Lassiter G, Chen ML, Alexander GC, Keet C, Hong H, Akenroye A. Comparative efficacy of tezepelumab to mepolizumab, benralizumab, and dupilumab in eosinophilic asthma: A Bayesian network meta-analysis. J Allergy Clin Immunol. 2023 Mar;151(3):747-755. doi: 10.1016/j.jaci.2022.11.021. Epub 2022 Dec 17. PMID: 36538979; PMCID: PMC9992307. |
does not fit the pico: wrong comparison (Tezepelumab vs Mepolizumab, Benralizumab, and Dupilumab) |
|
Nordenmark LH, Hellqvist Å, Emson C, Diver S, Porsbjerg C, Griffiths JM, Newell JD, Peterson S, Pawlikowska B, Parnes JR, Megally A, Colice G, Brightling CE. Tezepelumab and Mucus Plugs in Patients with Moderate-to-Severe Asthma. NEJM Evid. 2023 Oct;2(10):EVIDoa2300135. doi: 10.1056/EVIDoa2300135. Epub 2023 Sep 20. PMID: 38320181. |
does not fit the pico (wrong O): assessed presence of mucus plugs in CT scans |
|
Pavord ID, Hoyte FCL, Lindsley AW, Ambrose CS, Spahn JD, Roseti SL, Cook B, Griffiths JM, Hellqvist Å, Martin N, Llanos JP, Martin N, Colice G, Corren J. Tezepelumab reduces exacerbations across all seasons in patients with severe, uncontrolled asthma (NAVIGATOR). Ann Allergy Asthma Immunol. 2023 Nov;131(5):587-597.e3. doi: 10.1016/j.anai.2023.08.015. Epub 2023 Aug 23. PMID: 37619779. |
post hoc analysis of NAVIGATOR; wrong outcome: annualized asthma exacerbation rate per season |
|
Shaban Abdelgalil M, Ahmed Elrashedy A, Awad AK, Reda Gad E, Ali MM, Abdelmoez Farahat R, Hassan Shawki B, Abd-ElGawad M. Safety and efficacy of tezepelumab vs. placebo in adult patients with severe uncontrolled asthma: a systematic review and meta-analysis. Sci Rep. 2022 Dec 3;12(1):20905. doi: 10.1038/s41598-022-24763-9. PMID: 36463281; PMCID: PMC9719466. |
not all outcomes chosen by the working group were reported |
|
Shinkai M, Ebisawa M, Fukushima Y, Takeuchi S, Okada H, Tokiyo T, Hayashi N, Takikawa M, Colice G, Almqvist G. One-year safety and tolerability of tezepelumab in Japanese patients with severe uncontrolled asthma: results of the NOZOMI study. J Asthma. 2023 Mar;60(3):616-624. doi: 10.1080/02770903.2022.2082309. Epub 2022 Jun 16. PMID: 35707873. |
wrong study design: single arm tolerability/safety study (n=65) |
|
Sverrild A, Hansen S, Hvidtfeldt M, Clausson CM, Cozzolino O, Cerps S, Uller L, Backer V, Erjefält J, Porsbjerg C. The effect of tezepelumab on airway hyperresponsiveness to mannitol in asthma (UPSTREAM). Eur Respir J. 2021 Dec 31;59(1):2101296. doi: 10.1183/13993003.01296-2021. PMID: 34049943. |
wrong P: patients with asthma and AHR to mannitol (n=40) |
|
Wechsler ME, Brusselle G, Virchow JC, Bourdin A, Kostikas K, Llanos JP, Roseti SL, Ambrose CS, Hunter G, Jackson DJ, Castro M, Lugogo N, Pavord ID, Martin N, Brightling CE. Clinical response and on-treatment clinical remission with tezepelumab in a broad population of patients with severe, uncontrolled asthma: results over 2 years from the NAVIGATOR and DESTINATION studies. Eur Respir J. 2024 Dec 5;64(6):2400316. doi: 10.1183/13993003.00316-2024. PMID: 39326921; PMCID: PMC11618813. |
follow-up explorative analysis of NAVIGATOR and DESTINATION trials; wrong outcome: proportions of patients receiving tezepelumab who responded to treatment and who achieved on-treatment clinical remission |
|
Wechsler ME, Stolz D, Lugogo NL, Caveney S, Almqvist G, Bednarczyk A, Kotalik A, Chandarana S, Ambrose CS. Oral and inhaled corticosteroid dose reductions with tezepelumab versus placebo in patients with severe, uncontrolled asthma from DESTINATION. J Allergy Clin Immunol Pract. 2024 Nov;12(11):3128-3131.e2. doi: 10.1016/j.jaip.2024.08.008. Epub 2024 Aug 8. PMID: 39127103. |
explorative sub analysis of NAVIGATOR and SOURCE trial (using same patients) |
Beoordelingsdatum en geldigheid
Publicatiedatum : 01-10-2026
Beoordeeld op geldigheid : 01-10-2026
Samenstelling werkgroep
Voor het ontwikkelen van de richtlijnmodule is in 2024 een multidisciplinair cluster ingesteld. Het cluster Astma & COPD bestaat uit meerdere richtlijnen (zie hier de actuele clusterindeling). De stuurgroep bewaakt het proces van modulair onderhoud binnen het cluster. De expertisegroepsleden brengen hun expertise in, indien nodig. De volgende personen uit het cluster zijn betrokken geweest bij de herziening van deze module:
Clusterstuurgroepleden
- Dhr. dr. F. (Folkert) Brijker, voorzitter cluster Astma & COPD, longarts, Spaarne Gasthuis te Haarlem, NVALT
- Dhr. dr. G.J. (Gert-Jan) Braunstahl, vicevoorzitter cluster Astma & COPD longarts, Franciscus Gasthuis & Vlietland, NVALT
- Mevr. C.L.Y. (Chantal) Knoops, longarts, VieCuri medisch centrum, NVALT
- Mevr. dr. E. (Eline) bij de Vaate, longarts, Merem medisch revalidatie NVALT
- Mevr. M.C. (Myrthe) van der Burg, longarts, Jeroen Bosch Ziekenhuis, NVALT
- Mevr. drs. P.M.G.A. (Pascale) Lubbers-van Tuynn, beleidsmedewerker, Longfonds
- Mevr. dr. M.C. (Marloes) Minnaard, huisarts/wetenschappelijk medewerker NHG
Betrokken clusterexpertisegroepleden
- Mevr. dr. E.A. (Ellen) Croonen, kinderarts-pulmonoloog, CWZ, NVK
- Dhr. dr. E.P. (Eric) de Groot, kinderarts-pulmonoloog, Zuyderland, NVK
- Mevr. prof. dr. L. (Liesbeth) Duijts, kinderarts-pulmonoloog en epidemioloog, Erasmus MC
Met ondersteuning van
- Mevr. P. (Phylisha) van Heemskerken, junior adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- Mevr. dr. A.N. (Nynke) Kampstra, adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- Mevr. E. (Esther) van der Bijl, medisch informatiespecialist, Kennisinstituut van de Federatie Medisch Specialisten
Belangenverklaringen
Een overzicht van de belangen van de clusterleden en het oordeel over het omgaan met eventuele belangen vindt u in onderstaande tabel. De ondertekende belangenverklaringen zijn op te vragen bij het secretariaat van het Kennisinstituut van de Federatie Medisch Specialisten via secretariaat@kennisinstituut.nl.
Clusterstuurgroepleden
Tabel 7 Gemelde (neven)functies en belangen stuurgroep
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Overige belangen |
Restrictie |
|
dr. Folkert Brijker (vz.) |
Longarts, Spaarne Gasthuis |
Geen |
Laatste 3 jaar adviesraden en presentaties verzorgd voor AstraZeneca, Chiesi, GSK, Sanofi, Sananet |
Geen |
Geen |
Geen |
Geen |
|
dr. Gert-Jan Braunstahl (vicevoorzitter) |
Longarts Franciscus Gasthuis & Vlietland |
Geen |
In laatste 3 jaar advieswerk gedaan voor GSK, Sanofi, AstraZeneca en ALK ABello. |
Geen |
* Astra Zeneca - Studie naar astma-exacerbaties - Projectleider |
Geen |
Geen |
|
Chantal Knoops |
Longarts, VieCuri Medisch Centrum Noord Limburg |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Eline Droppers - bij de Vaate |
Longarts, Merem Medische Revalidatie |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Myrthe van der Burg |
AIOS Longziekten in het Jeroen Bosch Ziekenhuis |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Yvonne Kappe |
Projectleider Longfonds |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Marloes Minnaarrd |
Huisarts en wetenschappelijk medewerker afdeling richtlijnontwikkeling. Nederlands Huisartsen Genootschap (NHG) |
Huisarts-redacteur Thuisarts (8u betaald) |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Pascale Lubbers-van Tuyn |
Beleidsadviseur, Longfonds, betaalde functie |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
Betrokken clusterexpertisegroepleden
Tabel 8 Gemelde (neven)functies en belangen expertisegroep
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Overige belangen |
Restrictie |
|
dr. Ellen Croonen |
Kinderlongarts, Canisius Wilhelmina Ziekenhuis Nijmegen (betaald), lid van Nederlandse Vereniging voor Kindergeneeskunde en sectie Kinderlongziekten (onbetaald). |
Deelname aan beroepsgerelateerde initiatieven, onbetaald. |
Geen |
Geen |
Longfonds - SALSA studie; In vivo efficacy of Salbutamol (Sandoz) versus salbutamol (Ventolin GSK) (Salsa study) - Projectleider |
Geen |
Geen |
|
Eric de Groot |
* Kinderlongarts, Zuyderland medisch centrum; 80% |
* Lid Medische commissie Villa Pardoen, onbetaald |
Geen |
Geen |
Geen |
Geen |
Geen |
|
prof. dr. Liesbeth Duijts |
Hoogleraar Kinderlongziekten (kinderarts - pulmonoloog/epidemioloog), Erasmus MC, Rotterdam |
Past 5 years: |
Geen |
Geen |
Mbt financier 1, European Union's Horizon 2020 research and innovation program ((EUCAN-Connect, grant agreement No 824989, ATHLETE, grant agreement No 874583, ENDOMIX, grant agreement No 101136566), alhier inhoud onderzoek: |
|
|
Inbreng patiëntenperspectief
Het patiëntenperspectief is ingebracht door deelname van Longfonds aan het cluster.
Kwalitatieve raming van mogelijke financiële gevolgen in het kader van de Wkkgz
Bij de richtlijnmodule voerden de clusterleden conform de Wet kwaliteit, klachten en geschillen zorg (Wkkgz) een kwalitatieve raming uit om te beoordelen of de aanbevelingen mogelijk leiden tot substantiële financiële gevolgen. Bij het uitvoeren van deze beoordeling is de richtlijnmodule op verschillende domeinen getoetst (zie het stroomschema bij Werkwijze).
|
Module |
Uitkomst raming |
Toelichting |
|
Module MART behandeling bij astmatische kinderen |
Geen substantiële financiële gevolgen. |
Hoewel uit de toetsing volgt dat de aanbeveling(en) breed toepasbaar zijn (>40.000 patiënten), volgt ook uit de toetsing dat het geen nieuwe manier van zorgverlening of andere organisatie van zorgverlening betreft, het geen toename in het aantal in te zetten voltijdsequivalenten aan zorgverleners betreft en het geen wijziging in het opleidingsniveau van zorgpersoneel betreft. Er worden daarom geen substantiële financiële gevolgen verwacht.
|
Werkwijze
Voor meer details over de gebruikte richtlijnmethodologie verwijzen wij u naar de Werkwijze. Relevante informatie voor de ontwikkeling/herziening van deze richtlijnmodule is hieronder weergegeven.
Zoekverantwoording
Date: 27-01-2025
Embase.com
|
No. |
Query |
Results |
|
#1 |
'asthma'/exp OR 'bronchus hyperreactivity'/exp OR 'airway obstruction'/exp OR (((airway OR airflow OR repirator*) NEAR/2 (obstruct* OR occlusion* OR closure)):ti,ab,kw) OR ((bronch* NEAR/2 (hyperreactiv* OR 'hyper reactiv*' OR hyperrespons* OR 'hyper respons*')):ti,ab,kw) OR asthma*:ti,ab,kw OR wheez*:ti,ab,kw OR breathles*:ti,ab,kw |
454636 |
|
#2 |
'tezepelumab'/exp OR 'amg 157':ti,ab,kw OR 'amg157':ti,ab,kw OR 'medi 9929':ti,ab,kw OR 'medi9929':ti,ab,kw OR 'tezepelumab':ti,ab,kw OR 'tezspire':ti,ab,kw |
1071 |
|
#3 |
#1 AND #2 |
856 |
|
#4 |
#3 NOT ('conference abstract'/it OR 'editorial'/it OR 'letter'/it OR 'note'/it) NOT (('animal'/exp OR 'animal experiment'/exp OR 'animal model'/exp OR 'nonhuman'/exp) NOT 'human'/exp) |
529 |
|
#5 |
'meta analysis'/exp OR 'meta analysis (topic)'/exp OR metaanaly*:ti,ab OR 'meta analy*':ti,ab OR metanaly*:ti,ab OR 'systematic review'/de OR 'cochrane database of systematic reviews'/jt OR prisma:ti,ab OR prospero:ti,ab OR (((systemati* OR scoping OR umbrella OR 'structured literature') NEAR/3 (review* OR overview*)):ti,ab) OR ((systemic* NEAR/1 review*):ti,ab) OR (((systemati* OR literature OR database* OR 'data base*') NEAR/10 search*):ti,ab) OR (((structured OR comprehensive* OR systemic*) NEAR/3 search*):ti,ab) OR (((literature NEAR/3 review*):ti,ab) AND (search*:ti,ab OR database*:ti,ab OR 'data base*':ti,ab)) OR (('data extraction':ti,ab OR 'data source*':ti,ab) AND 'study selection':ti,ab) OR ('search strategy':ti,ab AND 'selection criteria':ti,ab) OR ('data source*':ti,ab AND 'data synthesis':ti,ab) OR medline:ab OR pubmed:ab OR embase:ab OR cochrane:ab OR (((critical OR rapid) NEAR/2 (review* OR overview* OR synthes*)):ti) OR ((((critical* OR rapid*) NEAR/3 (review* OR overview* OR synthes*)):ab) AND (search*:ab OR database*:ab OR 'data base*':ab)) OR metasynthes*:ti,ab OR 'meta synthes*':ti,ab |
733409 |
|
#6 |
'clinical trial'/exp OR 'randomization'/exp OR 'single blind procedure'/exp OR 'double blind procedure'/exp OR 'crossover procedure'/exp OR 'placebo'/exp OR 'prospective study'/exp OR rct:ab,ti OR random*:ab,ti OR 'single blind':ab,ti OR 'randomised controlled trial':ab,ti OR 'randomized controlled trial'/exp OR placebo*:ab,ti |
4192994 |
|
#7 |
#4 AND #5 |
71 |
|
#8 |
#4 AND #6 NOT #7 |
138 |
|
#9 |
#7 OR #8 |
209 |
|
#10 |
'tezepelumab in adults and adolescents with severe, uncontrolled asthma':ti AND 2021 NOT efficacy:ti |
1 |
|
#11 |
#9 AND #10 |
1 |
Ovid/Medline
|
# |
Searches |
Results |
|
1 |
exp Asthma/ or Bronchial Hyperreactivity/ or Airway Obstruction/ or ((airway or airflow or repirator*) adj2 (obstruct* or occlusion* or closure)).ti,ab,kf. or (bronch* adj2 (hyperreactiv* or hyper reactiv* or hyperrespons* or hyper respons*)).ti,ab,kf. or asthma*.ti,ab,kf. or wheez*.ti,ab,kf. or breathles*.ti,ab,kf. |
261244 |
|
2 |
(amg 157 or amg157 or medi 9929 or medi9929 or tezepelumab or tezspire).ti,ab,kf. |
274 |
|
3 |
1 and 2 |
233 |
|
4 |
3 not ((exp animals/ or exp models, animal/) not humans/) not (letter/ or comment/ or editorial/) |
220 |
|
5 |
meta-analysis/ or meta-analysis as topic/ or (metaanaly* or meta-analy* or metanaly*).ti,ab,kf. or systematic review/ or cochrane.jw. or (prisma or prospero).ti,ab,kf. or ((systemati* or scoping or umbrella or "structured literature") adj3 (review* or overview*)).ti,ab,kf. or (systemic* adj1 review*).ti,ab,kf. or ((systemati* or literature or database* or data-base*) adj10 search*).ti,ab,kf. or ((structured or comprehensive* or systemic*) adj3 search*).ti,ab,kf. or ((literature adj3 review*) and (search* or database* or data-base*)).ti,ab,kf. or (("data extraction" or "data source*") and "study selection").ti,ab,kf. or ("search strategy" and "selection criteria").ti,ab,kf. or ("data source*" and "data synthesis").ti,ab,kf. or (medline or pubmed or embase or cochrane).ab. or ((critical or rapid) adj2 (review* or overview* or synthes*)).ti. or (((critical* or rapid*) adj3 (review* or overview* or synthes*)) and (search* or database* or data-base*)).ab. or (metasynthes* or meta-synthes*).ti,ab,kf. |
804506 |
|
6 |
exp clinical trial/ or randomized controlled trial/ or exp clinical trials as topic/ or randomized controlled trials as topic/ or Random Allocation/ or Double-Blind Method/ or Single-Blind Method/ or (clinical trial, phase i or clinical trial, phase ii or clinical trial, phase iii or clinical trial, phase iv or controlled clinical trial or randomized controlled trial or multicenter study or clinical trial).pt. or random*.ti,ab. or (clinic* adj trial*).tw. or ((singl* or doubl* or treb* or tripl*) adj (blind$3 or mask$3)).tw. or Placebos/ or placebo*.tw. |
2835738 |
|
7 |
4 and 5 |
34 |
|
8 |
(3 and 6) not 7 |
93 |
|
9 |
7 or 8 |
127 |