
Immunotherapie
Uitgangsvraag
Wat is de rol van immunotherapie in de behandeling van patiënten met epileptische aanvallen met een (verdenking op) een immuun etiologie?
Aanbeveling
Aanbeveling-1
Behandel epileptische aanvallen bij patiënten met auto-immuun encefalitis veroorzaakt door antilichamen gericht tegen extracellulaire epitopen (zoals LGI1, CASPR2, en NMDAR) primair met intraveneuze methylprednisolon en immunoglobulinen. Start bij onvoldoende respons of ernstige ziekte met tweedelijnstherapie middels rituximab, eventueel gecombineerd met cyclofosfamide.
Aanbeveling-2
Overweeg onderhoudsbehandeling met mycofenolaat mofetil, azathioprine of rituximab bij patiënten met risico op relapse of een recidiverend beloop.
Aanbeveling-3
Behandel epilepsie bij patiënten met hoge titer GAD65 antistoffen primair met periodieke intraveneuze immunoglobulinen (IVIG) kuren. Overweeg om bij onvoldoende aanvalsreductie met tweedelijnsimmunosuppressieve therapie middels rituximab te starten.
Aanbeveling-4
Voor advies t.a.v. diagnostiek- en behandeling is tevens de richtlijn auto-immuun encefalitis te raadplegen en kan laagdrempelig overlegd worden met het expertisecentrum voor auto-immuun encefalitis van het Erasmus MC (per e-mail encefalitis.neurologie@erasmusmc.nl; of telefonisch via de encefalitis overleglijn +31(0)6-29659257).
Overwegingen
Waarom deze aanbeveling?
De medicatie adviezen die worden gegeven in deze richtlijn zijn gebaseerd op één grote, deels prospectieve cohortstudie bij anti-NMDAR encefalitis (Titulaer, 2013), de studie van Dubey (2020), diverse retrospectieve studies, als ook op expert opinion, en clinical trials die verricht zijn bij andere auto-immuun aandoeningen. Aangezien de resultaten van immunomodulerende behandeling uitzonderlijk goed kunnen zijn bij een groot deel van de patiënten, ook wanneer anti-aanvalsmedicatie geen effect heeft, hebben wij deze aanbevelingen zo geformuleerd. We willen echter benadrukken dat er geen grote gecontroleerde trials gedaan zijn naar de behandeling van auto-immuun encefalitis.
De beslissing hoe de individuele patiënt behandeld dient te worden hangt mede af van het type auto-immuun encefalitis, de ernst van de encefalitis, of er al dan niet sprake is van een onderliggende tumor en het recidief risico in samenhang met individuele patiëntkenmerken. Voor advies t.a.v. diagnostiek- en behandeling kan overlegd worden met het expertisecentrum voor auto-immuun encefalitis van het Erasmus MC (per e-mail encefalitis.neurologie@erasmusmc.nl; of telefonisch via de encefalitis overleglijn +31(0)6-29659257 – bereikbaar tussen 10-12 uur en 14-16 uur), daarnaast is de richtlijn auto-immuun encefalitis via deze link te raadplegen waarin het actuele behandeladvies staat beschreven.
Eindoordeel:
Conditionele aanbevelingen voor het gebruik van immunomodulerende therapie bij epileptische aanvallen met een immuun etiologie.
Balans tussen de voor- en nadelen van de interventie
Er is een systematisch literatuuronderzoek uitgevoerd om de rol van immunotherapie in de behandeling van patiënten met epileptische aanvallen met (een verdenking op) een auto-immuun etiologie te onderzoeken. Hierbij werd 1 studie geïncludeerd (Dubey, 2020). De cruciale uitkomstmaten waren aanvalsvrijheid en -reductie. De overige belangrijke uitkomstmaten waren het optreden van bijwerkingen en comorbiditeiten. Uit de literatuursamenvatting lijkt er een mogelijk voordeel te zijn van het gebruik van immunotherapie (IVIG), zowel voor aanvalsvrijheid, aanvalsreductie, als ook voor bijwerkingen. Uit de literatuur wordt onvoldoende duidelijk wat de mogelijke comorbiditeiten zijn, omdat daarover niet is gerapporteerd.
De overall bewijskracht is laag. Dit kwam door het risico op bias, het feit dat de data slechts op één studie gebaseerd is, indirectheid en doordat de betrouwbaarheidsintervallen de grenzen van klinische relevantie doorkruizen.
- Risk of Bias: inclusie werd voortijdig beëindigd na slechts 17 van de geplande 30 deelnemers, waardoor de statistische power beperkt was. De randomisatie resulteerde bovendien in een scheve verdeling (alle CASPR2-positieve patiënten bevonden zich in de placebogroep). De primaire uitkomst was gebaseerd op zelfgerapporteerde aanvalsaantallen (seizure diaries), wat het risico op vertekening vergroot. Daarnaast wordt in de studie vermeld dat sommige uitvallers wel en anderen niet zijn meegenomen in de analyse (attrition bias) en er wordt niet gerapporteerd of de data-analisten geblindeerd waren.
- Inconsistentie: niet beoordeelbaar (slechts één kleine studie beschikbaar).
- Indirectheid: de PICO omvat patiënten met autoimmuun geassocieerde epileptische aanvallen, terwijl de trial uitsluitend anti-LGI1 en anti-CASPR2 patiënten includeerde binnen één centrum. Hierdoor werd op voorhand al een kleine groep van de patienten met autoimmuun geassocieerde epilepstische aanvallen gerepresenteerd. Daarnaast ontvingen alle CASPR2-positieve deelnemers placebo, waardoor de resultaten voornamelijk de LGI1-subgroep weerspiegelen. De korte follow-up duur van vijf weken beperkt bovendien de toepasbaarheid voor de langetermijneffecten op aanvalsvrijheid.
- Imprecisie: de betrouwbaarheidsintervallen zijn breed en doorkruizen de grens voor klinische relevantie, dat duidt op aanzienlijke onzekerheid over de werkelijke effectgrootte.
- Publicatie bias: niet waarschijnlijk.
Aanvullende argumentatie
De resultaten van Dubey (2020) worden ondersteund door een recente, nog niet-gepubliceerde prospectieve open-labelstudie van Crijnen (2026). Dertien patiënten hadden antistoffen tegen een extracellulair antigen (11 anti-LGI1, 1 anti-NMDAR, en 1 anti-CASPR2) en 13 tegen een intracellulair antigen (allen anti-GAD65 >10.000 IU/ml). Alle patiënten kregen twee IVIG-kuren (0,4 g/kg/dag op dagen 1–5 en 22–26). In de weken 6–8 werd een >50% reductie in aanvalsfrequentie gevonden bij 14 van de 26 patiënten (54%) met een duidelijk verschil tussen de twee groepen: 10/13 (77%) in de extracellulaire groep versus 4/13 (31%) in de intracellulairegroep (p=0.024). De mediane aanvalsreductie bedroeg 94% in de extracellulaire groep en 4% in de intracellulaire groep (p=0.002). Aanvalsvrijheid werd bereikt bij 4/13 patiënten in de extracellaire groep, terwijl geen van de anti-GAD65 patiënten aanvalsvrij werd (p=0.048). In de weken 16–18 nam het percentage patiënten met een >50% reductie verder toe tot 92% in de extracellulaire groep en 77% in de intracellaire groep, maar bij een aanzienlijk deel traden recidieven op na het uitwerken van de IVIG. Dit ondersteunt de noodzaak van langduriger immunomodulerende behandeling bij autoimmuun geassocieerde epileptische aanvallen. Bijwerkingen werden niet als hoofdbevinding gerapporteerd.
Zowel in de studie van Dubey (2020) als Crijnen (2026) wordt een aanvullend positief effect van de additonele behandeling met steroiden beschreven. In de studie van Dubey werden 9 van de 12 patienten die nog niet aanvalsvrij waren en deelnamen aan de extensiefase behandeld met hoge dosis intraveneuze methylprednisolon, waarvan 56% aanvalsvrij werd met een mediaan van 1 maand (range 0.5 - 4). In de studie van Crijnen werden 7 patienten in de extracellulaire groep aanvullend behandeld met hoge dosis intraveneuze methylprednisolon vanwege onvoldoende reductie van de aanvalsfrequentie, danwel verdere klinische verslechtering van het encefalitis beeld. Bij deze patiënten leek de frequentie en de ernst van de aanvallen van week 3 t/m week 6-8 sterker af te nemen dan bij patiënten zonder aanvullende immunotherapie (p=0.069). Het positieve effect van behandeling met corticosteroiden wordt ook onderschreven door een retrospective studie bij anti-LGI1 patienten, waarbij monotherapie met corticosteroiden (n=49; 75% aanvalsvrij) effectiever lijkt dan met IVIG (n=21; 21% aanvalsvrij) bij de eerste klinische evaluatie (mediaan 1.4 maand (range 0–20), p <0.001)) (Rodriguez, 2021).
Naast de resultaten uit de gerandomiseerde studie van Dubey (2020) en de open-label studie van Crijnen (2026), is aanvullende informatie beschikbaar uit meerdere observationele studies bij patiënten met auto-immuun encefalitis met epileptische aanvallen. Hoewel deze studies methodologisch beperkter zijn, geven zij een consistent beeld van de effectiviteit van immunotherapie bij patiënten met verschillende type auto-immuun encefalitis weer.
De meeste patiënten met epileptische aanvallen in het kader van auto-immuun encefalitis (AEAS) worden na verloop van tijd aanvalsvrij. Op basis van de beschikbare literatuur lijkt behandeling met immuuntherapie effectiever te zijn dan behandeling met anti-epileptica voor het bereiken van aanvalsvrijheid als het gaat om AEAS.
In de retrospectieve studie van de Bruijn met 153 auto-immuun encefalitis patiënten (53 LGI1, 75 NMDAR, 25 GABABR) had 72% epileptische aanvallen en bereikte 89% aanvalsvrijheid, waarbij meer patiënten (54%) aanvalsvrij werden kort na start van immunotherapie dan na start van alleen anti-epileptica (14%) (p < 0,0001). In deze studie was er slechts 1 van de 86 overlevende patiënten met AEAE (de Bruijn, 2019). De studie van Zhang (2019) onderschrijft deze bevinding, aangezien 27/43 patiënten (63%) aanvalsvrij werden kort na de start van immunotherapie.
In de retrospectieve studie van Rada (2021) met 25 encefalitis patiënten (6 NMDAR, 11 LGI1, 8 CASPR2) werd 88% aanvalsvrij. Bij patiënten met een recidief encefalitis werd aanvalsvrijheid vaker behaald door het opnieuw starten van immunotherapie, waarbij niet altijd de dosering van de anti-aanvalsmedicatie werd opgehoogd (Rada, 2021).
In een volgende studie van Rada (2024) wordt aangetoond dat de meerderheid van de patiënten met AEAS aanvalsvrij zijn na 1 jaar, waarbij de kans het hoogst is voor anti-NMDAR encefalitis en het laagst voor anti- GABABR encefalitis, namelijk 0.89 (95% CI 0.85–0.92) voor anti-NMDAR (n=383), 0.84 (CI 0.80–0.88) voor anti-LGI1 (n=440), 0.82 (CI 0.75–0.90) voor anti-CASPR2 (n=114) en 0.76 (CI 0.62–0.93) voor anti-GABABR encefalitis (n=44) (Rada, 2024). De aanname is dat bijna alle patiënten werden behandeld met immunosuppressiva, waardoor een aanzienlijk aantal patiënten na een jaar aanvalsvrij was, de resultaten werden echter niet vergeleken met het natuurlijke ziekteverloop. De gegevens over het type immunotherapie waarmee de patiënten werden behandeld werd niet meegenomen in de analyse, waardoor er helaas geen conclusies kunnen worden getrokken over de mogelijke effecten van verschillende therapeutische strategieën. Bovendien werd in het onderzoek bij optreden van epileptische aanvallen na periode van > 3 maanden aanvalsvrijheid, geen onderscheid gemaakt tussen AEAS in het kader van een relapse encefalitis, danwel ontwikkelen van AEAE.
Een interessant bevinding omtrent het additionele effect van tweedelijnstherapie op de aanvalsfrequentie is te vinden in de studie van Baumgarter (2025). Deze studie includeerde 271 anti-LGI1 patiënten met epileptische aanvallen, waarbij werd gezien dat aanvullende behandeling met tweedelijnsimmuunmodulerende therapie eerder resulteerde in aanvalsvrijheid in vergelijking met uitsluitend behandeling met eerstelijnstherapie (p = 0.0019) (Baumgarter, 2025).
Anti-CASPR2 encefalitis komt vrijwel uitsluitend voor bij oudere mannen en is zeldzamer dan anti-LGI encefalitis, daarnaast komen epileptische aanvallen minder vaak voor. Dit verklaart waarschijnlijk waarom er minder data gepubliceerd zijn. In een retrospectieve studie van Garrido Snabria (2022) werden 13 van de 20 (65%) patiënten met epileptische aanvallen aanvalsvrij, waarvan 4 na de start van anti-aanvalsmedicatie en 9 na start van een combinatie van immunotherapie en anti-aanvalsmedicatie. Maar gezien de kleine aantallen en het een retrospectieve studie betreft, is het lastig om hier conclusies aan te verbinden. In de studie van Rada (2025), wordt 82% van de in totaal 114 anti-CASPR2 patiënten aanvalsvrij, maar in deze studie worden geen data verstrekt t.a.v. met welk type immunotherapie ze zijn behandeld. In de studie van Brand (2026) waren alle 39 patiënten waarbij data beschikbaar waren bij de laatste follow-up visit (mediane follow-up was 55 maanden (range 8–200) aanvalsvrij. De studie laat zien dat AEAS een belangrijk presenterend symptoom is, namelijk bij 28/44 van de patiënten (64%). Het relapse risico bij anti-CASPR2 is hoog, in deze studie 60%. Bij anti-CASPR2 patiënten met een verhoogd recidief risico lijkt onderhoudsbehandeling met rituximab noodzakelijk om nieuwe recidieven te voorkomen (hazardratio 26,33, p < 0,0005 in de groep na tweedelijnsbehandeling; ARR 0,09 versus 0,81), waarmee het aannemelijk is, dat dit ook het recidiefrisico op AEAS verlaagd (Brand, 2026).
Anti-GAD65-geassocieerde epilepsie
Ondanks de beschikbaarheid van diverse therapeutische opties, blijft de kans op aanvalsvrijheid bij patiënten met anti-GAD65-geassocieerde epilepsie laag, aanvalsvrijheidspercentages variëren tussen de 0%–33% waarbij zowel over de effecten van immunotherapie, als ook anti-aanvalsmedicatie, of een combinatie van beide wordt gerapporteerd (Rada, 2025).
In deze studie resulteerde verschillende therapeutische strategieën, zij het bij een klein aantal patiënten in aanvalsvrijheid: anteromediale temporale kwabresectie (n = 2); immunotherapie zonder aanvankelijk aanvalsvrijheid te bereiken, gevolgd door aanpassing in de anti-aanvalsmedicatie (n=2); hoge dosis prednisolon, intraveneuze immunoglobuline en rituximab, gevolgd door de toevoeging van anti-aanvalsmedicatie (n=1); plasmaferese gevolgd door de start van een anti-aanvalsmedicatie (n=1); en verlate opstart van immunotherapie (ca. 3 jaar na het begin van de ziekte) met intraveneuze immunoglobuline, gevolgd door kortdurende azathioprine en uiteindelijk mycofenolaatmofetil (n = 1). In dit GAD65 cohort van Rada (2025) waren 5 van de 36 patiënten (14%) ten minste 12 maanden aanvalsvrij bij de laatste follow-up. Deze bevinding ondersteunt de hypothese dat aanvallen geassocieerd met hoge anti-GAD65 antistoffen optreden in het kader van AEAE en niet AEAS.
In de studie van Muñoz-Lopetegi (2020) wordt bij 15/17 (70%) behandelde anti-GAD65 patiënten (>10,000 IU/mL in serum) - met verschillende fenotypische uitingen, waarvan 9 patiënten met epilepsie - een positief effect van immunotherapie (waaronder IVIG) beschreven, maar geen een patiënt wordt aanvalsvrij. Een positief effect van immunotherapie binnen de epilepsie groep wordt gedefinieerd als > 50% aanvalsreductie. De patiënten met anti-GAD65 geassocieerde epilepsie werden met name met (periodieke) IVIG-kuren behandeld, alsmede prednison gevolgd door een steroïdspaarder.
In een kleine retrospectieve studie van Malter (2015) bij 13 patiënten met anti-GAD65 geassocieerde epilepsie werd de behandelresponse bekeken, waarbij response was gedefinieerd als aanvalsvrij of aanvalsreductie van >50%). Een positieve behandelresponse werd gezien bij 5/11 patiënten behandeld met corticosteroïden, 1/5 met intraveneuze immunoglobulinen, 1/8 met plasmaferese, 1/1 natalizumab, en 2/3 met een selectieve amygdala-hippocampectomie. Geen van de patiënten bereikte langdurige aanvalsvrijheid met uitzondering van één patiënt. Deze patiënt kreeg anti-epileptica na het stoppen van de immunotherapie. In deze kleine studie lijkt behandeling met corticosteroïden effectiever dan de andere behandelmodaliteiten.
Al met al kan gesteld worden dat de respons op immunotherapie bij patiënten met anti-GAD65 geassocieerde epilepsie beperkt is. Vooral de geringe effecten van plasmaferese ondersteunen het idee dat GAD65-antilichamen niet direct pathogeen zijn. De data laten zien dat het om een chronische epileptische encefalopathie gaat, waarbij er na start van immunotherapie een reductie van de aanvalsfrequentie kan optreden, maar dat de kans klein is dat patiënten langdurige aanvalsvrijheid bereiken.
Waarden en voorkeuren van patiënten (en eventueel hun naasten/verzorgers)
De beslissing/afweging voor het type immunotherapie kan beïnvloed worden door de voorkeuren van de patiënt of hun naasten. Voor deze behandeling is intraveneuze toediening van medicatie noodzakelijk, die ook in een ziekenhuissetting gegeven moet worden vanwege de eventuele infusiegeassocieerde bijwerkingen (IARs) die kunnen optreden.
Een uitzondering hierop vormt IVIG, in het geval er een indicatie is voor herhaalde toedieningen en er eerder geen IARs opgetreden zijn, dan kan dit in de thuissituatie toegediend worden via een specialistische thuiszorgorganisatie. Bij problemen met het aanleggen van infusen kan de IVIG via een porth-a-cath of subcutaan toegediend worden. Indien voldoende bekwaam dan kan de patiënt of mantelzorger zelf de IVIG subcutaan toedienen. Bij het al dan niet starten van onderhoudsbehandeling met immuunmodulerende therapie wordt in samenspraak met de patiënt een keuze gemaakt op basis van het recidiefrisico, het bijwerkingenprofiel, en de belasting van de medicatie inname, danwel subcutane/intraveneuze toediening voor de patiënt. Het is belangrijk de afweging voor de behandeling samen met de patiënt te maken.
Kostenaspecten
De interventie brengt in eerste instantie relatief hogere kosten met zich mee, maar kan op termijn juist zorg- en maatschappelijke kosten besparen. Bij een spoedige start van immunotherapie lijdt dit bij de meerderheid van de patiënten met een auto-immuun encefalitis veroorzaakt door antistoffen gericht tegen een extracellulair antigen tot aanvalsvrijheid binnen dagen tot weken, waardoor dit tot een daling van zorgconsumptie en een hogere maatschappelijke participatie leidt. In geval van auto-immuun encefalitis geassocieerd met antistoffen gericht tegen een intracellulair antigen, in de meeste gevallen GAD65, dient er een afweging gemaakt te worden of de kosten opwegen tegen de gezondheidswinst die behaald wordt.
Gezondheidsgelijkheid ((health) equity/equitable)
De interventie leidt binnen Nederland niet tot een verandering in de gezondheidsgelijkheid. De behandeling is beschikbaar voor alle patiënten in Nederland.
Aanvaardbaarheid:
Ethische aanvaardbaarheid
De interventie lijkt aanvaardbaar voor de betrokkenen. De werkgroep voorziet geen ethische bezwaren, omdat met de behandeling een goed effect wordt nagestreefd tegen acceptabele bijwerkingen, voorts heeft patiënt ook tijdens deze behandeling recht op zelfbeschikking.
Duurzaamheid
Het is niet voldoende onderzocht of de interventie meer of minder milieu-impact heeft ten opzichte van behandeling met uitsluitend anti-epileptica. De behandeling met immunotherapie en bijkomende ziekenhuisopnames brengen een belangrijke ecologische voetafdruk met zich mee. Daarentegen kan het ook zijn dat de milieu-impact als gevolg van de interventie juist vermindert, omdat door effectievere behandeling van de epileptische aanvallen de ligduur in het ziekenhuis afneemt en dit tot een reductie leidt van het aantal reisbewegingen van de patiënt naar het ziekenhuis. Een bijkomend voordeel is dat anti-aanvalsmedicatie sneller afgebouwd kan worden. De patiënten aantallen met een immuun etiologie vormen een minderheid van het totale aantal patiënten met epilepsie, het gaat daarom niet om een grote milieu-impact. De werkgroep/het cluster is derhalve van mening dat de milieu-impact geen doorslaggevende rol speelt bij de aanbeveling.
Haalbaarheid
De interventie is haalbaar. Deze is immers reeds standaardzorg in de gespecialiseerde neurologische praktijk. In instellingen waarbij minder ervaring is met dit type behandelingen, kan samenwerking gezocht worden met bijvoorbeeld de reumatologie, interne-immunologie, danwel nefrologie gezien hun ervaring met behandeling van systemische auto-immuunziekten, waarbij dezelfde immunotherapie gebruikt wordt. Daarmee kunnen behandelaars zo mogelijk gebruikmaken van de infrastructuur, die er lokaal reeds is voor deze behandelingen, indien dit niet gefaciliteerd kan worden, kan doorverwezen worden naar een gespecialiseerd centrum.
Onderbouwing
Epilepsy with a suspected immune etiology includes 1) autoimmune encephalitis-associated seizures (AEAS) secondary to neuronal autoantibodies, occurring either in isolation or in the context of a more pronounced autoimmune encephalitis (de Bruijn, 2019; de Bruijn, 2021; Smith, 2024); and 2) autoimmune encephalitis-associated epilepsy (AEAE), in which seizures persist although there is no active inflammation anymore (Smith, 2024; Steriade, 2020; Steriade, 2025). The entities New-Onset Refractory Status Epilepticus (NORSE) and Fires Febrile Infection-Related Epilepsy Syndrome (FIRES) are beyond the scope of this guideline, although the immunotherapy strategy for these entities largely overlaps with AEAS.
Autoimmune encephalitis-associated seizures (AEAE) can be considered as late symptomatic epilepsy, and should be treated with anti-seizure medication. However, in anti-GAD65 associated epilepsy, which is considered as AEAE, patients seem to benefit from continuing immunotherapy suggesting ongoing chronic inflammation. Unfortunately, they almost never reach seizure freedom (Muñoz-Lopetegi, 2020; Dalakas, 2023).
In AEAS, treatment of the underlying auto-immune encephalitis with immunomodulatory treatment is most important. Whereas most seizures in autoimmune encephalitis caused by antibodies against extracellular epitopes resolve after the acute phase, between 1-20% (de Bruijn, 2019; Liu, 2022; Smith, 2021) of patients continue to have epileptic seizures after the encephalitis has subsided (AEAE). Although the true percentage of AEAE will probably be lower than 20%, due to incomplete or relatively short follow-up in certain studies, and in some studies AEAE could have been mistakenly classified as AEAS in the context of an (undetected) relapse.
In AEAS with neuronal antibodies targeted to extracellular epitopes – e.g. anti-LGI1 and anti-NMDAR encephalitis – generally respond well to immunotherapy as most patients become seizure free after treatment (de Bruijn, 2019; Baumgartner, 2025). Unfortunately, treatment outcome in patients with AEAS with neuronal antibodies targeted to intracellular epitopes – also known as the classical paraneoplastic syndromes – show either no or little response to immunotherapy. As immunological treatment options continue to expand, it is important to understand the effectiveness of these therapies in AEAS and in anti-GAD65 associated epilepsy.
Summary of Findings
|
Outcome |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Conclusions |
|
|
IVIG |
Placebo |
||||
|
Seizure reduction (critical) |
Relative Risk: 3.38 (95% CI: 0.93 – 12.21) Based on data from 17 participants in 1 study |
750 per 1000 |
22 per 1000 |
Low/ 1 |
The evidence is very uncertain about the effect IVIG has on seizure reduction when compared with placebo in patients with) epilepsy with (suspected) immune etiology (Dubey 2020) |
|
Difference: 528 more per 1000 (CI 95% 16 fewer — 2489 more) |
|||||
|
Seizure freedom (critical)
|
Relative Risk: 2.25 (95% CI: 0.25 – 20.38) Based on data from 17 participants in 1 study |
250 per 1000 |
111 per 1000 |
Low/ 1 |
The evidence is very uncertain about the effect IVIG has on seizure freedom when compared with placebo in patients with epilepsy (suspected) with immune etiology (Dubey 2020) |
|
Difference: 139 more per 1000 (CI 95% 83 fewer — 2151 more) |
|||||
|
Adverse events (important) |
Relative Risk: 0.56 (95% CI: 0.06 – 5.09) Based on data from 17 participants in 1 study |
124 per 1000 |
222 per 1000 |
Low/ 1 |
The evidence is very uncertain about the effect IVIG has on the occurrence of adverse events when compared with placebo in patients with epilepsy with (suspected) immune etiology (Dubey 2020) |
|
Difference: 98 fewer per 1000 (CI 95% 209 fewer — 908 more) |
|||||
|
Comorbidity (important)
|
- |
- |
No GRADE (no evidence was found) |
No evidence was found about the effect IVIG on comorbidity when compared with placebo in patients with epilepsy with (suspected) immune etiology. |
|
Description of studies
One study was included in the analysis of the literature. Important study characteristics and results are summarized in table 2. The assessment of the risk of bias is summarized in the risk of bias tables (under the tab ‘Evidence tabellen’).
Dubey (2020) conducted a randomized, double-blind, placebo-controlled trial at a single center (Mayo Clinic, Rochester, Minnesota) to assess the efficacy and safety of intravenous immunoglobulin (IVIG: Gamunex-C: 0.5 g/kg on day 1, 1 g/kg on day 2 followed by 0.6 g/kg at weeks 3 and 5) compared with placebo in adults diagnosed with either anti-LGI1 or anti-CASPR2 encephalitis, who experienced at least two seizures per week. The trial planned to enroll 30 participants but was terminated prematurely after randomization of 17 patients due to recruitment challenges. The primary outcome was a ≥50% reduction in seizure frequency from baseline to week 5. Secondary outcomes included amongst others seizure freedom and treatment-emergent adverse events.
Table 2. Characteristics of included studies
|
Study |
Participants |
Comparison |
Follow-up |
Outcome measures |
Comments |
Risk of bias (per outcome measure)* |
|
Individual studies |
||||||
|
Dubey (2020) |
N at baseline Intervention: 8 Control: 9
Age (year median, range) Intervention: 70 (66-77) Control: 70 (59-77)
Sex (n male, %) Intervention: 6 (75%) Control: 6 (67%) |
Intervention: IVIG**
Control: intravenous normal saline (placebo)
|
5 wk
|
Primary: - seizure frequency reduction of >50% Secondary: - seizure freedom - seizure frequency - adverse events
|
An open-label extension was conducted in non-responders from the placebo group, who subsequently received IVIG. Data from this phase were reported descriptively but were not included in the primary efficacy analysis for this module. |
Seizure frequency/reduction: early termination and small sample size may have led to imprecision and potential selection bias.
Seizure freedom: very few events and limited statistical power increase the likelihood of random error and overestimation.
Adverse events: data were systematically collected, but the small cohort limits detection of less frequent or delayed effects. |
* For further details, see risk of bias table in the appendix
** IVIG = intravenous immunoglobulin 0.5g/kg day 1, 1g/kg day 2, 0.6g/kg weeks 3 and 5
Results
Seizure reduction
Dubey (2020) reported that a ≥50% reduction in seizure frequency at five weeks was achieved in 6 out of 8 patients (75%) in the IVIG group compared with 2 of 9 patients (22%) in the placebo group. The risk ratio (RR) was 3.38 (95% CI 0.93 to 12.21), indicating a clinically relevant difference in favour of IVIG. See Figure 1 for the forest plot.
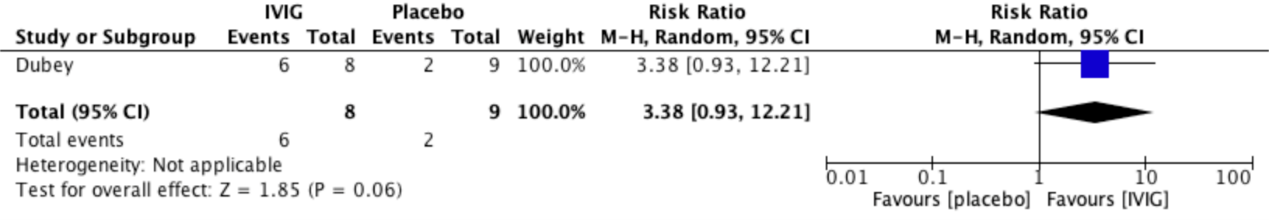
Figure 1. Forest plot on seizure reduction comparing IVIG and placebo
Risk ratio, random effects model. Z: p-value of overall effect; df: degrees of freedom; I2; statistical heterogeneity; CI: confidence interval
Seizure frequency/freedom
Dubey (2020) observed seizure freedom in 2/8 patients (25%) treated with IVIG, compared with 1/9 (11%) in the placebo group. The RR was 2.25 (95% CI 0.25 to 20.38), indicating a clinically relevant difference in favour of IVIG. See Figure 2 for the forest plot.
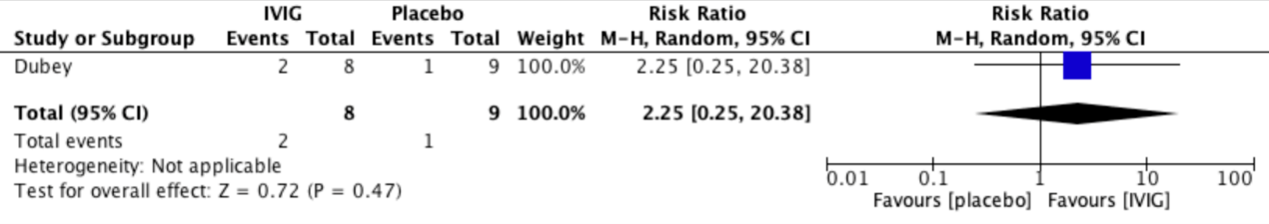
Figure 2. Forest plot on seizure frequency/freedom comparing IVIG and placebo
Risk ratio, random effects model. Z: p-value of overall effect; df: degrees of freedom; I2; statistical heterogeneity; CI: confidence interval
Adverse events
Dubey (2020) reported adverse events in 1/8 (13%) patients in the IVIG group and 2/9 patients (22%) in the placebo group. The RR was 0.56 (95% CI 0.06 to 5.09), indicating a clinically relevant difference in favour of the IVIG group. See Figure 3 for the forest plot.
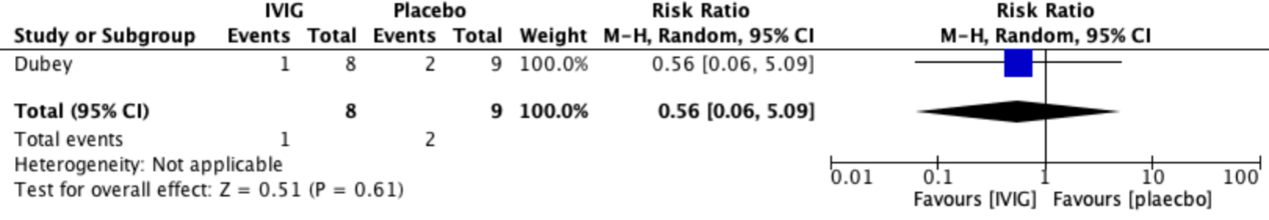
Figure 3. Forest plot on adverse events comparing IVIG and placebo
Risk ratio, random effects model. Z: p-value of overall effect; df: degrees of freedom; I2; statistical heterogeneity; CI: confidence interval
Comorbidity
No data were reported regarding comorbidities.
A systematic review of the literature was performed to answer the following question(s):
What is the efficacy of immunotherapy on seizure frequency (reduction/ freedom) and comorbidity in patients with epilepsy of (suspected) immune etiology?
Table 1. PICO
| Patients | Patients with epilepsy with (suspected) immune etiology |
| Intervention | Immunotherapy |
| Control | Placebo (possibly compare with other medications) |
| Outcomes |
Seizure freedom, seizure reduction, comorbidity and adverse events |
| Other selection criteria | Study design: systematic reviews, randomized controlled trials |
The guideline panel considered seizure freedom and seizure reduction as critical outcome measures for decision making; and comorbidity and adverse events as important outcome measures for decision making.
A priori, the guideline panel did not define the outcome measures listed above but used the definitions used in the studies.
The guideline panel defined the following thresholds as a minimal clinically (patient) important difference.
- Seizure reduction: >50% reduction.
- Comorbidity: Active infection, malignancy, other auto-immune disease.
- The occurrence of serious adverse events: infections, infusion-associated reactions, anaphylaxis and myelosuppression.
Search and select (Methods)
A systematic literature search was performed by a medical information specialist using the following bibliographic databases: Embase.com and Ovid/Medline. Both databases were searched until 05-02-2025 for systematic reviews, RCTs and observational studies. Systematic searches were completed using a combination of controlled vocabulary/subject headings (e.g., Emtree-terms, MeSH) wherever they were available and natural language keywords. The overall search strategy was derived from the primary search concepts: (1) epilepsy of immune etiology), (2) immunotherapy. Duplicates were removed using EndNote software. After deduplication a total of 914 records were imported for title/abstract screening. Initially, seven studies were selected based on title and abstract screening. After reading the full text, six studies were excluded (see the exclusion table under the tab ‘Evidence tabellen’), and one study was included.
- Baumgartner T, Freyberg M, Campetella L, Crijnen Y, Dargvainiene J, Behning C, Bien CG, Rada A, Prüss H, Rössling R, Kovac S, Strippel C, Thaler FS, Eisenhut K, Lewerenz J, Becker F, Reinecke R, Malter MP, Sühs KW, Tauber SC, Von Podewils F, Melzer N, Wandinger KP, Fernandez Ceballos RA, Kuhle J, Berger K, Bauer T, Rüber T, Racz A, Becker AJ, Pitsch J, Kuhlenbäumer G, Muñiz-Castrillo S, Honnorat J, Titulaer MJ, Leypoldt F, Surges R; and the GENERATE study group. Risk of Epilepsy and Factors Associated With Time to Seizure Remission in Anti-LGI1 Encephalitis: Long-Term Outcome in 236 Patients. Neurol Neuroimmunol Neuroinflamm. 2025 Nov;12(6):e200469. doi: 10.1212/NXI.0000000000200469. Epub 2025 Sep 15. PMID: 40953325; PMCID: PMC12440303.
- Brand T, Franken SC, Vermeiren MR, Van Sonderen A, De Bruijn MAAM, Crijnen YS, Brenner J, Kerstens J, Van Steenhoven RW, Sillevis Smitt PAE, Veenbergen S, Roelen DL, Titulaer MJ, de Vries JM. High Relapse Rate in Anti-CASPR2 Disease: Implications for Prolonged Immunotherapy. Neurol Neuroimmunol Neuroinflamm. 2026 Jan;13(1):e200524. doi: 10.1212/NXI.0000000000200524. Epub 2025 Dec 16. PMID: 41401401; PMCID: PMC12712842.
- de Bruijn MAAM, van Sonderen A, van Coevorden-Hameete MH, Bastiaansen AEM, Schreurs MWJ, Rouhl RPW, van Donselaar CA, Majoie MHJM, Neuteboom RF, Sillevis Smitt PAE, Thijs RD, Titulaer MJ. Evaluation of seizure treatment in anti-LGI1, anti-NMDAR, and anti-GABABR encephalitis. Neurology. 2019 May 7;92(19):e2185-e2196. doi: 10.1212/WNL.0000000000007475. Epub 2019 Apr 12. PMID: 30979857; PMCID: PMC6537134.
- de Bruijn MAAM, Bastiaansen AEM, Mojzisova H, van Sonderen A, Thijs RD, Majoie MJM, Rouhl RPW, van Coevorden-Hameete MH, de Vries JM, Muñoz Lopetegi A, Roozenbeek B, Schreurs MWJ, Sillevis Smitt PAE, Titulaer MJ; ACES Study Group. Antibodies Contributing to Focal Epilepsy Signs and Symptoms Score. Ann Neurol. 2021 Apr;89(4):698-710. doi: 10.1002/ana.26013. Epub 2021 Jan 27. PMID: 33427313; PMCID: PMC8048471.
- Dalakas MC. Therapies in Stiff-Person Syndrome: Advances and Future Prospects Based on Disease Pathophysiology. Neurol Neuroimmunol Neuroinflamm. 2023 Apr 14;10(3):e200109. doi: 10.1212/NXI.0000000000200109. PMID: 37059468; PMCID: PMC10119813.
- Dubey D, Britton J, McKeon A, Gadoth A, Zekeridou A, Lopez Chiriboga SA, Devine M, Cerhan JH, Dunlay K, Sagen J, Ramberger M, Waters P, Irani SR, Pittock SJ. Randomized Placebo-Controlled Trial of Intravenous Immunoglobulin in Autoimmune LGI1/CASPR2 Epilepsy. Ann Neurol. 2020 Feb;87(2):313-323. doi: 10.1002/ana.25655. Epub 2019 Dec 14. PMID: 31782181; PMCID: PMC7003900.
- Liu X, Guo K, Lin J, Gong X, Li A, Zhou D, Hong Z. Long-term seizure outcomes in patients with autoimmune encephalitis: A prospective observational registry study update. Epilepsia. 2022 Jul;63(7):1812-1821. doi: 10.1111/epi.17245. Epub 2022 Apr 16. PMID: 35357695.
- Malter MP, Frisch C, Zeitler H, Surges R, Urbach H, Helmstaedter C, Elger CE, Bien CG. Treatment of immune-mediated temporal lobe epilepsy with GAD antibodies. Seizure. 2015 Aug;30:57-63. doi: 10.1016/j.seizure.2015.05.017. Epub 2015 Jun 6. PMID: 26216686.
- Muñoz-Lopetegi A, de Bruijn MAAM, Boukhrissi S, Bastiaansen AEM, Nagtzaam MMP, Hulsenboom ESP, Boon AJW, Neuteboom RF, de Vries JM, Sillevis Smitt PAE, Schreurs MWJ, Titulaer MJ. Neurologic syndromes related to anti-GAD65: Clinical and serologic response to treatment. Neurol Neuroimmunol Neuroinflamm. 2020 Mar 2;7(3):e696. doi: 10.1212/NXI.0000000000000696. Erratum in: Neurol Neuroimmunol Neuroinflamm. 2020 Apr 15;7(4):e733. doi: 10.1212/NXI.0000000000000733. Erratum in: Neurol Neuroimmunol Neuroinflamm. 2024 Mar;11(2):e200215. doi: 10.1212/NXI.0000000000200215. PMID: 32123047; PMCID: PMC7136051.
- Rada A, Birnbacher R, Gobbi C, Kurthen M, Ludolph A, Naumann M, Neirich U, von Oertzen TJ, Ransmayr G, Riepe M, Schimmel M, Schwartz O, Surges R, Bien CG. Seizures associated with antibodies against cell surface antigens are acute symptomatic and not indicative of epilepsy: insights from long-term data. J Neurol. 2021 Mar;268(3):1059-1069. doi: 10.1007/s00415-020-10250-6. Epub 2020 Oct 6. PMID: 33025119; PMCID: PMC7914192.
- Rada A, Hagemann A, Aaberg Poulsen C, Baumgartner T, Berki T, Blaabjerg M, Brenner J, Britton JW, Christiana A, Ciano-Petersen NL, Crijnen Y, Elišák M, Farina A, Friedman AR, Hayden Z, Hébert J, Holtkamp M, Hong Z, Honnorat J, Ilyas-Feldmann M, Irani SR, Kovac S, Marusic P, Muñiz-Castrillo S, Ramanathan S, Smith KM, Steriade C, Strippel C, Surges R, Titulaer MJ, Uy CE, de Vries JM, Bien CG, Specht U. Risk of Seizure Recurrence Due to Autoimmune Encephalitis With NMDAR, LGI1, CASPR2, and GABABR Antibodies: Implications for Return to Driving. Neurol Neuroimmunol Neuroinflamm. 2024 Jul;11(4):e200225. doi: 10.1212/NXI.0000000000200225. Epub 2024 Jun 4. PMID: 38838283; PMCID: PMC11160480.
- Rada A, Reisch LM, Hagemann A, Woermann FG, Bien CG. Temporal Lobe Epilepsy Associated With Glutamic Acid Decarboxylase Antibodies: Defining a Distinct Epilepsy Syndrome. Neurol Neuroimmunol Neuroinflamm. 2025 Jul;12(4):e200422. doi: 10.1212/NXI.0000000000200422. Epub 2025 Jun 12. PMID: 40505070; PMCID: PMC12166559.
- Rodriguez A, Klein CJ, Sechi E, Alden E, Basso MR, Pudumjee S, Pittock SJ, McKeon A, Britton JW, Lopez-Chiriboga AS, Zekeridou A, Zalewski NL, Boeve BF, Day GS, Gadoth A, Burkholder D, Toledano M, Dubey D, Flanagan EP. LGI1 antibody encephalitis: acute treatment comparisons and outcome. J Neurol Neurosurg Psychiatry. 2022 Mar;93(3):309-315. doi: 10.1136/jnnp-2021-327302. Epub 2021 Nov 25. PMID: 34824144; PMCID: PMC8862031.
- Smith KM, Dubey D, Liebo GB, Flanagan EP, Britton JW. Clinical Course and Features of Seizures Associated With LGI1-Antibody Encephalitis. Neurology. 2021 Sep 14;97(11):e1141-e1149. doi: 10.1212/WNL.0000000000012465. Epub 2021 Jul 7. PMID: 34233939.
- Smith KM, Budhram A, Geis C, McKeon A, Steriade C, Stredny CM, Titulaer MJ, Britton JW. Autoimmune-associated seizure disorders. Epileptic Disord. 2024 Aug;26(4):415-434. doi: 10.1002/epd2.20231. Epub 2024 May 31. PMID: 38818801.
- Steriade C, Britton J, Dale RC, Gadoth A, Irani SR, Linnoila J, McKeon A, Shao XQ, Venegas V, Bien CG. Acute symptomatic seizures secondary to autoimmune encephalitis and autoimmune-associated epilepsy: Conceptual definitions. Epilepsia. 2020 Jul;61(7):1341-1351. doi: 10.1111/epi.16571. Epub 2020 Jun 16. PMID: 32544279.
- Steriade C, Bauer J, Bien CG. Autoimmune encephalitis-associated epilepsy. Nat Rev Neurol. 2025 Jun;21(6):312-326. doi: 10.1038/s41582-025-01089-4. Epub 2025 May 2. PMID: 40316743; PMCID: PMC12188692.
- Titulaer MJ, McCracken L, Gabilondo I, Armangué T, Glaser C, Iizuka T, Honig LS, Benseler SM, Kawachi I, Martinez-Hernandez E, Aguilar E, Gresa-Arribas N, Ryan-Florance N, Torrents A, Saiz A, Rosenfeld MR, Balice-Gordon R, Graus F, Dalmau J. Treatment and prognostic factors for long-term outcome in patients with anti-NMDA receptor encephalitis: an observational cohort study. Lancet Neurol. 2013 Feb;12(2):157-65. doi: 10.1016/S1474-4422(12)70310-1. Epub 2013 Jan 3. PMID: 23290630; PMCID: PMC3563251.
- Zhang W, Wang X, Shao N, Ma R, Meng H. Seizure characteristics, treatment, and outcome in autoimmune synaptic encephalitis: A long-term study. Epilepsy Behav. 2019 May;94:198-203. doi: 10.1016/j.yebeh.2018.10.038. Epub 2019 Apr 8. PMID: 30974347.
Risk of Bias tables
Risk of bias table for intervention studies (randomized controlled trials; based on Cochrane risk of bias tool and suggestions by the CLARITY Group at McMaster University)
Research question: What is the efficacy of immunosuppressive or monoclonal antibody treatment on seizure frequency (reduction/ freedom) and comorbidity in patients with (suspected) epilepsy (suspected) of immune etiology?
|
Study reference
(first author, publication year) |
Was the allocation sequence adequately generated?
|
Was the allocation adequately concealed?
|
Blinding: Was knowledge of the allocated interventions adequately prevented? Were patients blinded? Were healthcare providers blinded? Were data collectors blinded? Were outcome assessors blinded? Were data analysts blinded? |
Was loss to follow-up (missing outcome data) infrequent?
|
Are reports of the study free of selective outcome reporting?
|
Was the study apparently free of other problems that could put it at a risk of bias?
|
Overall risk of bias If applicable/necessary, per outcome measure
|
|
Dubey (2020) |
Definitely yes
Patients were randomized into 2 groups (A vs B) in a 1 to 1 ratio using a simple randomization method by utilizing JMP Pro 13 software. |
Definitely yes
The randomization code (A was the active arm and B was the placebo arm) remained sealed until the end of the blinded phase of the study, indicating proper concealment. |
Probably no
The study was described as double-blind for patients and clinicians, but blinding of data collectors and data analysts was not reported, raising some concern for potential detection bias.
|
Probably yes
The study was prematurely terminated before reaching the planned sample size and was therefore underpowered. Data from participants who discontinued early were inconsistently included in the analyses. This introduces attrition bias. |
Definitely yes
All prespecified outcomes were reported. |
Probably no
Early termination, underpowering, and the introduction of an open-label phase after the blinded period may have affected internal validity. |
HIGH
Main issues relate to premature study termination, insufficient power, incomplete blinding, and possible influence of early discontinuation or open-label extension. |
Table of excluded studies
|
Reference |
Reason for exclusion |
|
Geng J, Dong J, Li Y, Ni H, Jiang K, Shi LL, Wang G. Intravenous immunoglobulins for epilepsy. Cochrane Database Syst Rev. 2019 Dec 2;12(12):CD008557. doi: 10.1002/14651858.CD008557.pub4. PMID: 31792946; PMCID: PMC6887830. |
Wrong population |
|
Luo P, Zhong R, Chen Q, Lin W. Seizure outcome-related factors in autoimmune encephalitis: A systematic review and meta-analysis. Front Neurol. 2022 Nov 3;13:991043. doi: 10.3389/fneur.2022.991043. PMID: 36408506; PMCID: PMC9670169. |
No comparison (observational study) |
|
Kong X, Gong X, Li A, Liu Y, Li X, Li J, Zhou D, Hong Z. Efficacy of immunotherapy and prognosis in anti-LGI1 encephalitis patients: A meta-analysis. Ann Clin Transl Neurol. 2023 Sep;10(9):1578-1589. doi: 10.1002/acn3.51847. Epub 2023 Jul 13. PMID: 37443415; PMCID: PMC10502619. |
No comparison (observational study) |
|
El-Haggar SM, Hegazy SK, Mustafa W, Khrieba MO. Possible immuno-modulatory effects of tocilizumab in patients with refractory status epilepticus. Eur Rev Med Pharmacol Sci. 2023 Feb;27(4):1512-1521. doi: 10.26355/eurrev_202302_31392. PMID: 36876691. |
Wrong population |
|
Zhang D, Li B, Li J, Tong L, Yang L. Efficacy and Safety of Rituximab Treatment for Anti-N-Methyl-d-Aspartate Receptor Encephalitis Without Tumor in Children. Pediatr Neurol. 2024 Dec;161:85-90. doi: 10.1016/j.pediatrneurol.2024.09.001. Epub 2024 Sep 6. PMID: 39332075. |
No comparison (observational study) |
|
Blackburn KM, Denney DA, Hopkins SC, Vernino SA. Low Recruitment in a Double-Blind, Placebo-Controlled Trial of Ocrelizumab for Autoimmune Encephalitis: A Case Series and Review of Lessons Learned. Neurol Ther. 2022 Jun;11(2):893-903. doi: 10.1007/s40120-022-00327-x. Epub 2022 Feb 7. PMID: 35129803; PMCID: PMC9095811. |
Wrong outcome |
Beoordelingsdatum en geldigheid
Publicatiedatum : 12-11-2026
Beoordeeld op geldigheid : 12-11-2026
Samenstelling werkgroep
Voor het ontwikkelen van de richtlijnmodule is in 2020 een multidisciplinair cluster ingesteld. Het cluster Epilepsie bestaat uit meerdere richtlijnen (zie hier de actuele clusterindeling). De stuurgroep bewaakt het proces van modulair onderhoud binnen het cluster. De expertisegroepsleden brengen hun expertise in, indien nodig. De volgende personen uit het cluster zijn betrokken geweest bij de herziening van deze module:
Cluster- stuurgroepleden
- Prof. dr. H.J.M. Majoie (voorzitter), neuroloog, Academisch Centrum voor Epileptologie Kempenhaeghe/ Maastricht UMC+, Heeze en Maastricht
- Dr. P. Klarenbeek, neuroloog, Zuyderland Medisch Centrum, Heerlen/ Sittard
- Drs. M.H.G. Dremmen, radioloog, Erasmus MC Rotterdam
- Dr. C.M. Delsman-van Gelder, kinderneuroloog, MMC Veldhoven, Veldhoven
- Dr. P. van Vliet, intensivist, Haaglanden Medisch Centrum, Den Haag
- Dr. L. M’Rabet, patiëntvertegenwoordiger, EpilepsieNL, Houten
Betrokken cluster- expertisegroepleden
- Dr. M. Vlooswijk, neuroloog, Maastricht UMC+/ Academisch Centrum voor Epileptologie, Maastricht
- Dr. R. Rouhl, neuroloog, Maastricht UMC+, Maastricht
- Drs. R. Lamberts, neuroloog, Academisch Centrum voor Epileptologie Kempenhaeghe/ Maastricht UMC+, Heeze en Maastricht
- Dr. J.M. de Vries, neuroloog, ErasmusMC, Rotterdam
Met ondersteuning van
- Dr. I. Blokland, adviseur Kennisinstituut van de Federatie Medisch Specialisten, Utrecht
- Dr. M. Wassenaar, adviseur Kennisinstituut van de Federatie Medisch Specialisten, Utrecht
- Dr. L. Weijdijk, adviseur Kennisinstituut van de Federatie Medisch Specialisten, Utrecht
- Mw. A. Dorhout, junior adviseur Kennisinstituut van de Federatie Medisch Specialisten, Utrecht
- Mw. I. Gijselhart, medisch informatiespecialist, Academisch Centrum voor Epileptologie Kempenhaeghe, Heeze
Belangenverklaringen
Een overzicht van de belangen van de clusterleden en het oordeel over het omgaan met eventuele belangen vindt u in onderstaande tabel. De ondertekende belangenverklaringen zijn op te vragen bij het secretariaat van het Kennisinstituut van de Federatie Medisch Specialisten via secretariaat@kennisinstituut.nl.
Tabel Gemelde (neven)functies en belangen stuurgroepleden
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Intellectuele belangen en reputatie |
Overige belangen |
Datum |
Restrictie |
|
Majoie |
Staflid neurologie Academisch Centrum voor Epileptologie Kempenhaeghe Maastricht UMC+ Voorzitter werkgroep |
- Coördinator landelijk research-, en opleidingsnetwerk epilepsie. - Lid commissie richtlijnen van de Nederlandse Vereniging voor Neurologie. - Voorzitter landelijke werkgroep richtlijn Epilepsie van de Nederlandse Vereniging voor Neurologie. - Lid commissie Zorgevaluatie van de Nederlandse Vereniging voor Neurologie en van de Commissie wetenschap van de Nederlandse Vereniging voor Neurologie. - Lid kernredactie kwartaalblad "Epilepsie, periodiek voor Professionals" van de Nederlandse Liga tegen Epilepsie. - Voorzitter bestuur van de Nederlandse Liga tegen Epilepsie/ Voorzitter bestuur werkgroep Epilepsie van de Nederlandse Vereniging voor Neurologie. - Voorzitter bestuur landelijke scholing aios kindergeneeskunde & neurologie SepiON. - Initiator en coördinator van het 'European partnership on high value cost conscious care and guideline development training program' en initiator en coördinator van eenzelfde project op nationale basis. - Lid stuurgroep van het Landelijke Leerhuis Epilepsie (Kempenhaeghe Maastricht UMC+ & SEIN). - Lid wetenschappelijke adviesraad (WAR) epilepsiefonds EpilepsieNL. - Extern adviseur College ter Beoordeling van Geneesmiddelen. |
Geen |
Geen |
ZonMW dossiernummer 10310012210006 (2024-2028) Kosteneffectieve toepassing van aanvalsdetectie hulpmiddelen voor risicovolle nachtelijke epileptische aanvallen. Rol: aanvrager en mede-projectlid.
ZonMW transnational research: dossiernummer 04460162210008 (2023-2024). Titel: Aanvalsdetectie, op weg naar betere bekendheid en veiligere zorg. Rol: aanvrager en mede-projectlid.
Kwaliteitsgelden ZonMW: dossiernummer 859002001 ( 2021-2025). Titel: Leerplatform richtlijnontwikkeling. Rol: aanvrager en project coördinator.
Stichting vrienden van Kempenhaeghe (2022-2023). Titel: Leerplatform Epilepsie en slaap scholingen. Rol: aanvrager en project coördinator.
Kempenhaeghe, SEIN en Epilepsiefonds EpilesieNL (2024-2028) Titel: Impact van epilepsie, een value based healthcare project Rol: aanvrager en project coördinator
ZonMW Projectnummer: HMM2019020 (2020-2024) Project titel: Brain@home: real-world clinical neurophysiological and neurobehavioral markers as novel human measurement models for personalised treatment in epilepsy and migraine. Rol: mede aanvrager
Erasmus +. Projectnummer: 2018- 1-NL0 1-KA203-O39O7O (2018-2023). Projecttitel: European Partnership on Competencies for High Value COst COnscious CARE. Rol: aanvrager en project coördinator
Top ZonMW Dossier nr: 40-00812-98-17055 (2018-2023). Brain on a dish: development of innovative stem cell technologies for personalized medicine in epilepsy. Rol: mede aanvrager
Nationaal Epilepsiefonds (2018-2023). Towards personalized treatment of genetically classified refractory epilepsies using Human Induced Pluripotent Stem Cells (hIPSCs) as an ex-vivo tool. Rol: projectlid |
Geen |
Geen |
20-08-2025 |
Geen |
|
Klarenbeek |
Neuroloog Zuyderland MC Heerlen/Sittard, vrijgevestigd |
Ik heb afgelopen jaar een eenmalige speaker fee ontvangen van Angelini Pharma (Cenobamaat) voor een geaccrediteerde nascholing |
Geen |
Geen |
Geen |
Geen |
Geen |
20-08-2025 |
Geen |
|
Van Vliet |
Intensivist, Haaglanden Medisch Centrum te Den Haag |
Docent regionale opleiding ic-verpleegkundigen, LUMC (betaald) Docent Care Training Group, Ridderkerk (betaald) Bestuursvoorzitter MuzIC (onbetaald) |
Geen |
Geen |
Geen |
Geen |
Geen |
04-12-2025 |
Geen |
|
Dremmen |
Kinderradioloog met subspecialisatie kinderneuroradiologie Erasmus MC |
Een van de voorzitters van de richtlijn Radiologische diagnostiek acute trauma-opvang bij kinderen Expertisegroep richtlijn Traumatologie Uitgenodigd spreker op meerdere nationale en internationale cursussen en congressen |
Geen |
Geen |
Geen |
Geen |
Geen |
04-09-2025 |
Geen |
|
Delsman |
Kinderneuroloog/kinderarts MMC Veldhoven |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
09-12-2025 |
Geen |
|
M’rabet |
MT Kennis & Innovatie, EpilepsieNL |
-Int. Stuurgroep lid in 2025, emergency care UCB -Int. Stuurgroep lid, Seizure Freedom, Angelini Pharmaceuticals -Adviesraad St Medmij -Adviesraad Angelini Pahrmaceuticals Benelux -lid Epilepsy Alliance Europe |
geen |
zoon |
Prelude, Epicentrum, Slimme camera, TONI Jazz Pharmaceuricals; Prelude, Epilepsie en een verstandelijke beperking, PL nee ZonMW voor elkaar; Epicentrum: ontwikkeling vrijwilligers platform, PL nee Epicentrum: ontwikkeling vrijwilligers platform; Slimme Camera, video aanvalsdetectie Vriendenloterij; TONI, video aanvalsdetectie, PL Ja |
geen |
geen |
27-3-2025 |
Geen |
Tabel Gemelde (neven)functies en belangen betrokken expertisegroepleden
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Intellectuele belangen en reputatie |
Overige belangen |
Datum |
Restrictie |
|
Vlooswijk |
Neuroloog Maastricht Universitair Medisch Centrum; Academisch Centrum voor Epileptologie locatie Maastricht |
Bestuurslid Stichting Epilepsie Onderwijs Nederland Docent Stichting Epilepsie Onderwijs Nederland |
Geen |
Geen |
Geen |
Geen |
Geen |
10-10-2025 |
Geen |
|
Rouhl |
Neuroloog, Maastricht Universitair Medisch Centrum+ en Academisch Centrum voor Epileptologie Kempenhaeghe/MUMC+ |
Bestuurslid van de sectie wetenschappelijk onderzoek van de Nederlandse Liga tegen Epilepsie |
Eenmalig betaald advies aan Jazz Pharmaceuticals (Epidiolex/cannabidiol), 2023, afgesloten Enkele malen per jaar betaald advies aan Angelini Pharma (Ontozry/cenobamaat), ongoing; financiële bijdrage aan betaling reis en congresbezoek door Angelini Pharma (2023). Sprekersvergoedingen (incidenteel) door Eisai, Angelini Pharma |
Geen |
Geen |
Geen |
Geen |
13-11-2025 |
Geen |
|
Lamberts |
Neuroloog bij Academisch Centrum voor Epileptologie Kempenhaeghe, Maastricht UMC+ |
Geen |
Geen |
Nee |
Nee |
Niet van toepassing. |
Nee. |
9-12-2025 |
Geen |
|
de Vries |
Neuroloog Erasmus MC |
Geen |
Geen |
Geen |
Local principal investigator van de Cielo study, initiated by Roche. Cielo study (Phase III) – placebo-controlled multicentre RCT to evaluate the efficacy, safety, farm, projectleider. |
Geen |
Member of the European Reference Network for Rare Immunodeficiency, Autoinflammatory and Autoimmune Diseases–Project ID No 739543 (ERN-RITA; HCP Erasmus MC) |
4-12-2025 |
Geen |
Inbreng patiëntenperspectief
Kwalitatieve raming van mogelijke financiële gevolgen in het kader van de Wkkgz
Bij de richtlijnmodule voerden de clusterleden conform de Wet kwaliteit, klachten en geschillen zorg (Wkkgz) een kwalitatieve raming uit om te beoordelen of de aanbevelingen mogelijk leiden tot substantiële financiële gevolgen. Bij het uitvoeren van deze beoordeling is de richtlijnmodule op verschillende domeinen getoetst (zie het stroomschema bij Werkwijze).
|
Module |
Uitkomst raming |
Toelichting |
|
Immunotherapie |
Geen financiële gevolgen |
Uit de toetsing volgt dat de aanbeveling(en) niet breed toepasbaar zijn (<5.000 patiënten) en zal daarom naar verwachting geen substantiële financiële gevolgen hebben voor de collectieve uitgaven. |
Werkwijze
Voor meer details over de gebruikte richtlijnmethodologie verwijzen wij u naar de Werkwijze. Relevante informatie voor de ontwikkeling/herziening van deze richtlijnmodule is hieronder weergegeven.
Zoekverantwoording
Algemene informatie
|
Richtlijn: Epilepsie |
|
|
Uitgangsvraag: Immunologie - Immunotherapie |
|
|
Database(s): Pubmed/Medline, Embase (Ovid) |
Datum: 05-02-2025 |
|
Periode: 2024 |
Talen: Engels |
|
Literatuurspecialist: Irene Gijselhart |
|
|
Toelichting en opmerkingen:
|
|
|
Te gebruiken voor richtlijnen tekst: In de databases Embase (Ovid) en Pubmed/Medline is op 05-02-2025 met relevante zoektermen gezocht naar systematische reviews, RCTs en observationele studies over Immunologie - Immunotherapie. De literatuurzoekactie leverde 87 unieke treffers op. |
|
Zoekopbrengst
|
|
EMBASE |
Pubmed/MEDLINE |
Ontdubbeld |
|
SRs |
34 |
1 |
13 |
|
RCTs |
2 |
1 |
0 |
|
Observationele studies |
133 |
17 |
74 |
|
Overig |
|
|
|
|
Totaal |
169 |
19 |
87 |
Zoekstrategie
Embase (Ovid)
Database: Embase <1974 to 2025 Week 05>
Search Strategy:
|
1 (exp Epilepsy/ or exp Seizure/ or Landau Kleffner Syndrome/ or Lennox-Gastaut syndrome/ or severe myoclonic epilepsy in infancy/ or Infantile Spasm/ or (epilep* or seizure* or (continuous spikes and waves during sleep) or csws or landau-kleffner syndrome or lennox-gastaut syndrome or infant* spasm* or dravet* or "severe myoclonic epilepsy" or SMEI).ti,kf. or exp epileptic state/ or (status epilepticus or epilepsia partialis continua or cluster seizures or serial seizures or repetitive seizures).ti,kf.) and (expl antibodies/ or (antibod* or autoimmun*).ti,kf. or expl autoantibodies/ or autoantibod*.ti,kf. or expl limbic encephalitis/ or "limbic encephalitis".ti,kf. or exp n methyl dextro aspartic acid receptor/ or ("N-methyl-d-aspartate receptor*" or nmda).ti,kf. or ("leucine-rich glioma-inactivated protein-1" or lgi1 or "lgi 1").ti,kf. or exp 4 aminobutyric acid B receptor/ or "gaba b".ab,ti. or expl glycine receptor/ or glycine.ti,kf. or expl voltage gated potassium channel/ or ("voltage gated potassium channel*" or vgkc).ti,kf. or (caspr2 or "caspr 2" or "contactin-associated protein 2" or "contactin 2").ti,kf.) and (exp immunotherapy/ or immunotherapy.ti,kf. or exp immunosuppressive agent/ or immunosuppressi*.ti,kf. or (immunosuppressant* or immunomodulator* or immunoglobulin or immune globulin).ti,kf. or exp prednisolone/ or (prednisolone or methylprednisolone).ti,kf. or exp corticosterone/ or corticoster*.ti,kf. or exp plasmapheresis/ or plasmapheres*.ti,kf. or steroids/ or exp azathioprine/ or (azathioprine or immuran).ti,kf. or exp Mycophenolic acid/ or ("mycophenolic acid" or "mycophenolate mofetil" or cellcept or myfortic).ti,kf. or exp Rituximab/ or (rituximab or mabthera).ti,kf. or exp cyclophosphamide/ or (cuclophosphamide or endoxan).ab,ti,kf. or exp Dexamethasone/ or dexamethasone.ti,kf.) (4817) 2 1 not ((exp animal/ or exp animal experiment/ or exp animal model/ or exp nonhuman/) not exp human/) not (conference abstract or conference review or editorial or letter or note).pt. (3092) 3 limit 2 to yr="2023 -Current" (508) 4 limit 3 to english language (480) 5 exp Meta-Analysis/ or exp "Meta-Analysis as Topic"/ or exp Network Meta-Analysis/ or exp Systematic Review/ or exp "Systematic Reviews as Topic"/ or (networkmeta analy* or networkmetaanaly* or metaanaly* or meta analy* or metanaly* or prisma or prospero or metaanali* or meta anali* or metanali*).ti,ab,kf. or ((systemati* or scoping or umbrella or structured literature) adj3 (review* or overview*)).ti,ab,kf. or ((structured or systemic*) adj3 (review* or overview* or synth*) adj3 literature).ti,ab,kf. or (systemic* adj1 review*).ti,ab,kf. or ((systemati* or literature or database* or data base*) adj10 search*).ti,ab,kf. or ((structured or comprehensive* or systemic*) adj3 search*).ti,ab,kf. or ((literature adj3 (review* or overview*)) and (search* or database* or data base*)).ti,ab,kf. or ((data extraction* or data source*) and (study selection* or studies selection*)).ti,ab,kf. or (search strateg* and selection criteria*).ti,ab,kf. or (data source* and data synth*).ti,ab,kf. or (medline* or pubmed* or pub med* or embase or cochrane*).ti,ab,kf. or cochrane.jw. or ((critical* or rapid*) adj2 (review* or overview* or synth*)).ti. or (((critical* or rapid*) adj3 (review* or overview* or synth*)) and (search* or database* or data base*)).ab. or metasynth*.ti,ab,kf. or meta synth*.ti,ab,kf. (1113857) 6 4 and 5 (34) 7 exp randomized controlled trial/ or random*.ti,ab. or ((pragmatic or practical) adj clinical trial*).ti,ab. or ((non-inferiority or noninferiority or superiority or equivalence) adj3 trial*).ti,ab. (2275609) 8 (4 and 7) not 5 (2) 9 (Cohort analysis/ or case control study/ or longitudinal study/ or major clinical study/ or retrospective study/ or prospective study/ or (cohort* or case control or follow up study or follow up studies or observational study or observational studies or epidemiologic study or epidemiologic studies).ab,ti,kf.) not (case report/ or (case report or case study).ab,ti,kf.) (7605287) 10 (4 and 9) not (5 or 7) (133)
|
Pubmed/Medline
|
#10 |
||||||||||||||||
|
Search: #4 AND #9 NOT (#5 OR #7) Sort by: Most Recent |
04:08:49 |
|||||||||||||||
|
#9 |
||||||||||||||||
|
Search: ("Epidemiologic studies"[Mesh] OR "Case control studies"[Mesh] OR "Cohort studies"[Mesh] OR "Controlled Before-After Studies"[Mesh] OR case control*[TIAB] OR cohort*[TIAB] OR (Follow up[TIAB] AND (study[TIAB] OR studies[TIAB])) OR (observational[TIAB] AND (study[TIAB] OR studies[TIAB])) OR Longitudinal[TIAB] OR Retrospective*[TIAB] OR prospective*[TIAB] OR cross sectional[TIAB] OR "Cross-sectional studies"[Mesh] OR "Historically controlled study"[Mesh] OR "Interrupted time series analysis"[Mesh]) Sort by: Most Recent |
04:08:35 |
|||||||||||||||
|
#8 |
||||||||||||||||
|
Search: #4 AND #7 NOT #5 Sort by: Most Recent |
04:07:47 |
|||||||||||||||
|
#7 |
||||||||||||||||
|
Search: ("Randomized Controlled Trial" [Publication Type] OR random*[tiab] OR pragmatic clinical trial*[tiab] OR practical clinical trial*[tiab] OR non-inferiority trial*[tiab] OR noninferiority trial*[tiab] OR superiority trial*[tiab] OR equivalence clinical trial*[tiab]) Sort by: Most Recent |
04:07:37 |
|||||||||||||||
|
#6 |
||||||||||||||||
|
Search: #4 AND #5 Sort by: Most Recent |
04:06:33 |
|||||||||||||||
|
#5 |
||||||||||||||||
|
Search: "Meta-Analysis" [Publication Type] OR "Meta-Analysis as Topic"[Mesh] OR "Network Meta-Analysis" [Publication Type] OR "Systematic Review" [Publication Type] OR "Systematic Reviews as Topic"[Mesh] OR networkmeta analy*[tiab] OR networkmetaanaly*[tiab] OR metaanaly*[tiab] OR meta analy*[tiab] OR metanaly*[tiab] OR prisma[tiab] OR prospero[tiab] OR metaanali*[tiab] OR meta anali*[tiab] OR metanali*[tiab] OR "systematic review"[tiab:~3] OR "systematic overview"[tiab:~3] OR "scoping review"[tiab:~3] OR "scoping overview"[tiab:~3] OR "umbrella review"[tiab:~3] OR "umbrella overview"[tiab:~3] OR "structured literature review"[tiab:~3] OR "structured literature overview"[tiab:~3] OR ("structured review"[tiab:~3] AND literature[tiab]) OR ("structured overview"[tiab:~3] AND literature[tiab]) OR ("structured synthesis"[tiab:~3] AND literature[tiab]) OR "systemic overview"[tiab:~3] OR ("systemic synthesis"[tiab:~3] AND literature[tiab]) OR "systemic review"[tiab:~1] OR "systematic literature search"[tiab:~10] OR ("systematical search"[tiab:~10] AND literature[tiab]) OR ("systematically searched"[tiab:~10] AND literature[tiab]) OR "literature search"[tiab:~10] OR "literature searched"[tiab:~10] OR "data bases searched"[tiab:~10] OR "databases searched"[tiab:~10] OR ("structured search"[tiab:~3] AND (database*[tiab] OR literature[tiab])) OR ("structured searches"[tiab:~3] AND (database*[tiab] OR literature[tiab])) OR "comprehensive search"[tiab:~3] OR "comprehensive searches"[tiab:~3] OR ("systemic search"[tiab] AND (database*[tiab] OR literature[tiab])) OR ("systemic searches"[tiab] AND (database*[tiab] OR literature[tiab])) OR "systemically search"[tiab:~3] OR "systemically searches"[tiab:~3] OR (data extraction*[tiab] AND (study selection*[tiab] OR studies selection*[tiab])) OR (data source*[tiab] AND (study selection*[tiab] OR studies selection*[tiab])) OR (search strategy*[tiab] AND selection criteria*[tiab]) OR (data source*[tiab] AND data synth*[tiab]) OR (medline*[tiab] OR pubmed[tiab] OR "pub med"[tiab] OR embase*[tiab] OR cochrane[tiab]) OR "Cochrane Database Syst Rev"[Journal] OR (("critical review"[tiab:~3] OR "critical overview"[tiab:~3] OR "critical synthesis"[tiab:~3] OR "rapid review"[tiab:~3] OR "rapid overview"[tiab:~3] OR "rapid synthesis"[tiab:~3]) AND (search*[tiab] OR database*[tiab] OR "data base"[tiab] OR "data bases"[tiab])) OR metasynth*[tiab] OR meta synth*[tiab] Sort by: Most Recent |
04:06:23 |
|||||||||||||||
|
#4 |
||||||||||||||||
|
Search: #3 AND (2023[pdat]:2024[pdat]) Sort by: Most Recent |
04:06:08 |
|||||||||||||||
|
#3 |
||||||||||||||||
|
Search: #2 AND English[Language] Sort by: Most Recent |
04:05:48 |
|||||||||||||||
|
#2 |
||||||||||||||||
|
Search: #1 NOT (("Animals"[Mesh] OR "Animal Experimentation"[Mesh] OR "Models, Animal"[Mesh]) NOT "Humans"[Mesh]) NOT (letter[pt] OR comment[pt] OR editorial[pt]) Sort by: Most Recent |
04:05:36 |
|||||||||||||||
|
#1 |
||||||||||||||||
|
Search: ("Epilepsy"[MeSH] OR epilep*[Title] OR epilep*[OT] OR (continous[TW] AND spike*[TW] AND wave*[TW] AND sleep[TW]) OR "Landau-Kleffner syndrome"[Mesh] OR "landau-kleffner syndrome"[TW] OR "Lennox Gastaut syndrome"[Mesh] OR "lennox-gastaut syndrome"[TW] OR "Spasms, Infantile"[Mesh] OR infantile spasm*[TW] OR Dravet*[TW] OR "severe myoclonic epilepsy"[TW] OR SMEI[TW] OR "Seizures"[Mesh] OR seizures[Title] OR seizures[OT] OR seizure[Title] OR seizure[OT] OR "Status Epilepticus"[Mesh] OR "Status Epilepticus"[TW] OR "Epilepsia Partialis Continua"[Mesh] OR "cluster seizures"[TW] OR "serial seizures"[TW] OR "repetitive seizures"[TW]) AND ("Antibodies"[Mesh] OR antibod*[Title] OR antibod*[OT] OR autoimmun*[Title] OR autoimmun*[OT] OR "Autoantibodies"[Mesh] OR autoantibod*[Title] OR autoantibod*[OT] OR "Limbic Encephalitis"[Mesh] OR "limbic encephalitis"[Title] OR "limbic encephalitis"[OT] OR "Receptors, N-Methyl-D-Aspartate"[Mesh] OR N-methyl-d-aspartate receptor*[Title] OR N-methyl-d-aspartate receptor*[OT] OR nmda[Title] OR nmda[OT] OR "LGI1 protein, human"[Supplementary Concept] OR "leucine-rich glioma-inactivated protein-1"[Title] OR "leucine-rich glioma-inactivated protein-1"[OT] OR lgi1[Title] OR lgi1[OT] OR "lgi 1"[Title] OR "lgi 1"[OT] OR "Receptors, GABA-B"[Mesh] OR "gaba b"[Title] OR "gaba b"[OT] OR "Receptors, Glycine"[Mesh] OR glycine[Title] OR glycine[OT] OR "Potassium Channels, Voltage-Gated"[Mesh] OR voltage gated potassium channel*[Title] OR voltage gated potassium channel*[OT] OR vgkc[Title] OR vgkc[OT] OR caspr2[Title] OR caspr2[OT] OR "caspr 2"[Title] OR "caspr 2"[OT] OR "contactin-associated protein 2"[Title] OR "contactin-associated protein 2"[OT] OR "contactin 2"[Title] OR "contactin 2"[OT]) AND ("Immunotherapy"[Mesh] OR immunother*[Title] OR immunother*[OT] OR immunosuppressi*[Title] OR immunosuppressi*[OT] OR "Immunosuppressive agents"[Mesh] OR immunosuppressant*[Title] OR immunosuppressant*[OT] OR immunomodulator*[Title] OR immunomodulator*[OT] OR immunoglobulin[Title] OR immunoglobulin[OT] OR "immune globulin"[Title] OR "immune globulin"[OT] OR "Prednisolone"[Mesh] OR prednisolone[Title] OR prednisolone[OT] OR methylprednisolone[Title] OR methylprednisolone[OT] OR "Corticosterone"[Mesh] OR corticoster*[Title] OR corticoster*[OT] OR "Plasmapheresis"[Mesh] OR plasmapheres*[Title] OR plasmapheres*[OT] OR "Steroids"[Mesh:NoExp] OR "Azathioprine"[Mesh] OR Azathioprine[Title] OR Azathioprine[OT] OR immuran[Title] OR immuran[OT] OR "Mycophenolic Acid"[Mesh] OR "Mycophenolate Mofetil"[Title] OR "Mycophenolate Mofetil"[OT] OR cellcept[Title] OR cellcept[OT] OR myfortic[Title] OR myfortic[OT] OR "Rituximab"[Mesh] OR rituximab[Title] OR rituximab[OT] OR mabthera[Title] OR mabthera[OT] OR "Cyclophosphamide"[Mesh] OR cyclophosphamide[Title] OR cyclophosphamide[OT] OR endoxan[Title] OR endoxan[OT] OR "Dexamethasone"[Mesh] OR dexamethasone[Title] OR dexamethasone[OT]) Sort by: Most Recent |
04:0 |
|||||||||||||||