
Intraveneuze behandeling met tenecteplase
Uitgangsvraag
Wat is de effectiviteit en veiligheid van de behandeling met tenecteplase in vergelijking met alteplase als intraveneus trombolyticum bij patiënten met een acuut herseninfarct?
Aanbeveling
Gebruik tenecteplase 0.25 mg/kg voor patiënten met een acuut herseninfarct, zonder relevante contra-indicaties, bij wie behandeling binnen 4.5 uur na het begin van verschijnselen kan worden gestart.
Gebruik tenecteplase 0.25mg/kg voor patiënten met een acuut herseninfarct, zonder relevante contra-indicaties, en bij wie voldaan wordt aan de behandelcriteria conform module ´Behandeling na 4,5 uur of als het begintijdstip onbekend is´
Overwegingen
Balans tussen gewenste en ongewenste effecten
Er is een literatuuronderzoek verricht naar de effectiviteit en veiligheid van tenecteplase in vergelijking met alteplase als intraveneus trombolyticum bij patiënten met een acuut herseninfarct. Er werd één systematische review geïncludeerd (Palaiodimou, 2024), waarin alle tot op heden uitgevoerde gerandomiseerde klinische onderzoeken zijn opgenomen die tenecteplase vergeleken met alteplase in het vroege tijdsvenster (<4.5 uur). De meta-analyse includeerde 11 studies, waarvan 6 fase II studies en 5 fase III studies die alle een ‘non-inferiority design’ hadden. De meta-analyse toont ‘non-inferiority’ voor de cruciale uitkomstmaten functioneel herstel (mRS 0-2) en mortaliteit. Er is sprake van ‘superiority’ voor een uitstekende functionele uitkomst (mRS 0-1). Voor de belangrijke uitkomstmaat intracraniele bloedingen was er ook sprake van ‘non-inferiority’. De overall bewijskracht is ‘redelijk’ (i.t.t. hoog) vanwege imprecisie. Voor de belangrijke uitkomstmaat reperfusie werd geen bewijs gevonden in deze meta-analyse (maar wordt later in de paragraaf toegelicht). Op basis van deze uitkomsten lijkt tenecteplase non-inferieur vergeleken met alteplase wat betreft effectiviteit en veiligheid. Het gebruik van tenecteplase heeft de voorkeur met het oog op het gebruiksgemak en enige aanwijzingen voor hogere effectiviteit.
In het late tijdsvenster zijn geen gerandomiseerde studies verricht die het effect en de veiligheid van tenecteplase direct vergelijken met het gebruik van alteplase. Er is echter voldoende informatie over de veiligheid van tenecteplase in het late tijdsvenster. Er zijn zes studies die het toedienen van tenecteplase bij patiënten met een herseninfarct in het late tijdsvenster (zelfs tot 24 uur) vergeleken met standaard zorg, zonder dat er aanwijzingen waren voor een significant verhoogd bloedingsrisico (Roaldsen, 2023; Wang, 2023; Xiong, 2024; Albers, 2024; Chen, 2025; Cheng, 2025). Bovendien was de effectgrootte op functionele uitkomst vergelijkbaar met gerandomiseerde studies met alteplase in het late tijdsvenster (Ma, 2019; Xiong, 2024; Roaldsen, 2023). Twee recente fase III studies (TRACE-III, TIMELESS) randomiseerden patiënten met een herseninfarct o.b.v. een proximale intracraniële arteriële occlusie (a. carotis interna, a. cerebri media), een ´last-seen well´ tussen de 4.5 en 24 uur, en een aanwezige penumbra op perfusie beeldvorming, tussen tenecteplase (0.25mg/kg) en standaard zorg (Xiong, 2024; Albers, 2024). Het aandeel dat endovasculaire trombectomie (EVT) onderging verschilde aanzienlijk tussen beide studies. De TRACE-III had als studieopzet dat patiënten met een proximale intracraniële arteriële occlusie werden geïncludeerd, die vanwege een logistieke reden in China geen EVT konden ondergaan. In deze studie hadden meer patiënten in de tenecteplase groep (33%) dan in de controlegroep (24.2%) een uitstekend functioneel herstel (mRS 0-1; RR 1.37, 95% CI 1.04-1.81). Het risico op bloedingen was laag: 3% in de tenecteplase en 0.8% in de controlegroep. In de TIMELESS studie hadden alle patiënten een ACI, M1 of M2-occlusie en onderging 77.3% van de patiënten EVT. Uiteindelijk was in deze studie het functioneel herstel (OR 1.13; 95% 0.82-1.57) en het aantal symptomatische hersenbloedingen (3.2% versus 2.3%) hetzelfde in de tenecteplase en controlegroep. De studies laten echter wel zien dat het gebruik van tenecteplase veilig is bij patiënten met een herseninfarct en een LSW van 4.5 – 24 uur geleden. Derhalve is de werkgroep van mening dat patiënten ook in het late tijdsvenster (4.5 – 12 uur) middels tenecteplase behandeld kunnen worden conform de indicatiestelling in de module ´Behandeling na 4.5 uur of als het begintijdstip onbekend is' bij acuut herseninfarct.
Er zijn aanwijzingen dat het gebruik van een hogere dosering tenecteplase (0.4mg/kg) geassocieerd is met een hoger risico op hersenbloedingen als complicatie van de behandeling (Kvistad, 2022; Haley, 2010).
Eerdere studies konden geen non-inferioriteit aantonen voor het achterwege laten van intraveneuze trombolyse met alteplase vóór endovasculaire trombectomie (EVT) bij patiënten met een acuut herseninfarct die zich binnen 4.5 uur na het symptomen presenteerden (Majoie, 2023). De BRIDGE-TNK trial toonde echter aan dat patiënten die binnen 4.5 uur na het begintijdstip van symptomen zowel tenecteplase als EVT ontvingen, significant vaker een functioneel goed herstel hadden (mRS 0-2 bij 52.9%) t.o.v. patiënten die alleen EVT ondergingen (mRS 0-2 bij 44.1%; RR 1.2, 95% CI 1.01 – 1.43). Een hersenbloeding trad op bij 8.8% respectievelijk 6.7% van de patiënten. Patiënten die tenecteplase kregen voor EVT hadden vaker reperfusie voor de EVT (6.1%) dan patiënten zonder tenecteplase (1.1%). Opvallend is dat de mate van reperfusie net ná EVT net iets lager is in de tenecteplase groep (91.4%) ten opzichte van alleen EVT groep (94.1%).
De bevinding dat tenecteplase is geassocieerd met een hoger percentage van reperfusie voor EVT vergeleken met alteplase werd tevens in eerdere gerandomiseerde studies gezien (Muir, 2024; Campbell, 2015). In de EXTEND-IA TNK trial was de mate van reperfusie de primaire uitkomstmaat (Campbell, 2018). Patiënten met een herseninfarct en een proximale intracraniële arteriële occlusie werden gerandomiseerd tussen tenecteplase (0.25 mg/kg) en alteplase. Bij 22% van de patiënten die behandeld waren met tenecteplase, ten opzichte van 10% behandeld met alteplase (incidence ratio 2.2, 95% CI 1.1-4.4), was er reeds sprake van een reperfusie van ≥50% in het ischemische gebied van de geoccludeerde arterie bij angiografische beoordeling voor EVT (Campbell, 2018).
Kwaliteit van bewijs
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens/grenzen van klinische relevantie overschrijdt.
Waarden en voorkeuren van patiënten (en eventueel hun naasten/verzorgers)
Het is onzeker of de makkelijkere toedieningsmethode van tenecteplase ten opzichte van alteplase door de patiënt of diens naasten opgemerkt zal worden. Het verminderde aantal handelingen, en daarmee verlaagde risico op fouten, en de aanwijzingen voor een hogere kans op een uitstekende uitkomst na behandeling van tenecteplase is een vanzelfsprekend voordeel voor patiënten en diens naasten.
Kostenaspecten
De kosten van het gebruik van tenecteplase ten opzichte van alteplase hangt af van het gewicht van de patiënt. Er is een modelmatig kosteneffectiviteitsonderzoek verricht waaruit blijkt dat de overstap naar tenecteplase leidt tot betere uitkomsten (+0.05 QALY) en tevens tot (zeer beperkte) kostenbesparing (Nguyen, 2023).
Gelijkheid ((health) equity/equitable)
Er zijn geen aanwijzingen dat de veiligheid en effectiviteit van tenecteplase verschilt op basis van persoonlijke kenmerken, gebaseerd op de subgroep analyses uit de studies. Behandeling met tenecteplase valt onder ‘acute zorg’ en wordt daarmee voor iedereen beschikbaar gesteld.
Aanvaardbaarheid:
Er zijn geen ethische bezwaren tegen de behandeling met tenecteplase als alternatief voor alteplase.
Duurzaamheid
Behandeling middels tenecteplase heeft het voordeel dat er geen gebruik wordt gemaakt van een perfusor pomp. De overstap naar tenecteplase kan dus bijdragen aan een reductie van ‘medisch afval’. Overige duurzaamheidsaspecten zijn niet officieel onderzocht.
Haalbaarheid/ implementatie
Het gebruiksgemak van tenecteplase is een groot voordeel ten opzichte van alteplase. De toediening middels een enkele bolus is gemakkelijker, minder arbeidsintensief, minder belastend voor de patiënt en minder fout gevoelig.
Aangezien de contra-indicaties voor tenecteplase niet verschillen van alteplase zal de informatie voor de omscholing van het ‘stroke’ team beperkt zijn. Het gaat hierbij voornamelijk om de implementatie van het nieuwe doseerschema. Wel dient rekening te worden gehouden met het eventueel gebruik van alteplase in andere ziekenhuizen in het geval van overplaatsing.
Rationale van de aanbeveling: weging van argumenten voor en tegen de interventies
Vanwege het gebruiksgemak (eenmalige bolus ten opzichte van eenmalige bolus gevolgd door een continue infusiepomp) in combinatie met een vergelijkbare effectiviteit en veiligheid (met aanwijzingen voor een hogere kans op een uitstekende functionele uitkomst) verdient het gebruik van tenecteplase (in een dosering van 0.25mg/kg) de voorkeur boven alteplase.
Eindoordeel: Sterke aanbeveling voor.
Onderbouwing
Over the past 30 years, alteplase has been the cornerstone of acute ischemic stroke treatment. In 1995, the NINDS trial was the first to demonstrate that alteplase, when administered within 3 hours of stroke onset, improved functional outcomes (National Institute of Neurological Disorders and Stroke rt-PA Stroke Study Group, 1995). In 2008, the ECASS-III trial showed benefit up to 4.5 hours after symptom onset, leading to an extension of the treatment window (Hacke, 2008). More recently, the indications for alteplase have been further expanded. With the use of advanced imaging techniques, it is now possible to identify patients with a last-known-well time of up to 12 or even 24 hours, or with an unknown time of onset, in whom alteplase can be used safely and effectively (Thomalla, 2018; Ma, 2019; Zhou, 2025). However, alteplase has some limitations. The complex administration, consisting of an initial bolus and continuous infusion, and the modest fibrin specificity, prompted the search for an alternative drug. Tenecteplase, a genetically modified tissue plasminogen activator, has a greater fibrin specificity and may therefore achieve higher rates of recanalization. Tenecteplase has a longer half-life, allowing a single bolus administration. The combination of easier administration and the potential for higher efficacy makes tenecteplase an option for replacing alteplase in daily practice.
Summary of Findings
Population: Patients with acute stroke
Intervention: Treatment with IV tenecteplase
Comparator: Treatment with IV alteplase
|
Outcome Timeframe |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Conclusions |
|
|
Treatment with IV alteplase |
Treatment with IV tenecteplase |
||||
|
Functional recovery – excellent (crucial) |
Relative risk: 1.05 (CI 95% 1.01 - 1.10) Based on data from 7401 participants in 11 studies |
504 per 1000 |
529 per 1000 |
Moderate GRADE Due to serious imprecision1 |
Tenecteplase likely results in little to no difference in excellent functional recovery when compared with alteplase in patients with acute stroke. (Bivard, 2022; Campbell, 2018; Haley, 2010; Huang, 2015; Li, 2022; Meng, 2024; Menon, 2022; Muir, 2023; Parsons, 2012; Parsons, 2024; Wang, 2023) |
|
Difference: 25 more per 1000 (CI 95% 5 more – 50 more) |
|||||
|
Functional recovery – good (crucial) |
Relative risk: 1.03 (CI 95% 0.99 - 1.07) Based on data from 7400 participants in 11 studies |
671 per 1000 |
691 per 1000 |
Moderate GRADE Due to serious imprecision1 |
Tenecteplase likely results in little to no difference in good functional recovery when compared with alteplase in patients with acute stroke. (Bivard, 2022; Campbell, 2018; Haley, 2010; Huang, 2015; Li, 2022; Meng, 2024; Menon, 2022; Muir, 2023; Parsons, 2012; Parsons, 2024; Wang, 2023) |
|
Difference: 20 more per 1000 (CI 95% 7 fewer - 47 more) |
|||||
|
Mortality (crucial) |
Relative risk: 0.97 (CI 95% 0.82 - 1.15) Based on data from 7522 participants in 11 studies |
88 per 1000 |
85 per 1000 |
Low GRADE Due to very serious imprecision2 |
Tenecteplase may result in little to no difference in mortality when compared with alteplase in patients with acute stroke. (Bivard, 2022; Campbell, 2018; Haley, 2010; Huang, 2015; Li, 2022; Meng, 2024; Menon, 2022; Muir, 2023; Parsons, 2012; Parsons, 2024; Wang, 2023) |
|
Difference: 3 fewer per 1000 (CI 95% 16 fewer - 13 more) |
|||||
|
Symptomatic cerebral haemorrhage (important) |
Relative risk: 1.12 (CI 95% 0.83 - 1.53) Based on data from 7535 participants in 11 studies |
20 per 1000 |
22 per 1000 |
Low GRADE Due to very serious imprecision2 |
Tenecteplase may result in little to no difference in symptomatic cerebral haemorrhage when compared with alteplase in patients with acute stroke. (Bivard, 2022; Campbell, 2018; Haley, 2010; Huang, 2015; Li, 2022; Meng, 2024; Menon, 2022; Muir, 2023; Parsons, 2012; Parsons, 2024; Wang, 2023) |
|
Difference: 2 more per 1000 (CI 95% 3 fewer - 11 more) |
|||||
|
Reperfusion (important) |
- |
- |
No GRADE (no evidence was found) |
No evidence was found regarding the effect of treatment with tenecteplase on reperfusion when compared with treatment with alteplase in patients with acute stroke. |
|
1. Imprecision: serious. Due to overlap of the upper or lower limit of the 95% confidence interval with the minimal clinically important difference.
2. Imprecision: very serious. Due to overlap of the upper and lower limit of the 95% confidence interval with the minimal clinically important difference.
Description of studies
One systematic review was included in the analysis of the literature. Important study characteristics and results are summarized in table 2. The assessment of the risk of bias is summarized in the risk of bias tables (under the tab ‘Evidence tabellen’).
The systematic review and meta-analysis of Palaiodimou (2024) aimed to assess the efficacy and safety of tenecteplase (TNK) versus tissue plasminogen activator (TPA) during intravenous thrombolysis for acute ischemic stroke (AIS) within the first 4.5 hours after onset. The authors searched MEDLINE and Scopus for RCTs from inception to 16 May 2024. Studies involving adult patients with AIS who were eligible for intravenous thrombolysis within 4.5 hours of symptom onset, treated with 0.25 mg/kg TNK versus 0.9 mg/kg TPA, and reporting functional outcomes at follow-up were included. No restrictions on language or other criteria were imposed, and the reference lists of published articles and international conference abstracts were manually reviewed to ensure the bibliography was comprehensive. Observational cohort studies, uncontrolled studies, case series, case reports, commentaries, editorials, and narrative reviews were excluded. In total, 11 studies were included. Outcomes of interest were functional recovery, mortality, and symptomatic intracranial hemorrhage.
Table 2. Characteristics of included studies
|
Study |
Participants |
Comparison |
Follow-up |
Outcome measures |
Comments |
Risk of bias (per outcome measure)* |
|
Included in systematic review Palaiodimou, 2024 |
||||||
|
Menon, 2022 (AcT 2022) |
N at baseline Intervention: 806 Control: 771
Patients with AIS within 4.5 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase III in Canada 2019-2022
TNK regimen: original |
Some concerns |
|
Huang, 2015 (ATTEST 2015) |
N at baseline Intervention: 52 Control: 51
Patients with supratentorial AIS within 4.5 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase II in Scotland 2012-2013
TNK regimen: original |
Some concerns |
|
Muir, 2023 (ATTEST-2 2023) |
N at baseline Intervention: 885 Control: 891
Patients with AIS within 4.5 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase III in UK 2017-2023
TNK regimen: original |
Some concerns |
|
Campbell, 2018 (EXTEND-IA TNK 2018) |
N at baseline Intervention: 101 Control: 101
Patients with AIS within 4.5 h eligible for endovascular thrombectomy |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase II in Australia and New Zealand 2015-2017
TNK regimen: original |
Low |
|
Meng, 2024 (ORIGINAL 2024) |
N at baseline Intervention: 732 Control: 736
Patients with AIS within 4.5 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase III in China 2021-2023
TNK regimen: original |
Some concerns |
|
Parsons, 2012 (TAAIS 2012) |
N at baseline Intervention: 25 Control: 25
Patients with AIS within 6 h, and vessel occlusion on CT angiography and a perfusion lesion at least 20% greater than the infarct core on CT perfusion at baseline |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase IIb in Australia 2008-2011
TNK regimen: original |
Some concerns |
|
Parsons, 2024 (TASTE 2024) |
N at baseline Intervention: 339 Control: 341
Patients with AIS within 4.5 h with target mismatch criteria on CT perfusion, if not candidates for endovascular treatment |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase III – International 2014-2023
TNK regimen: original |
Some concerns |
|
Bivard, 2022 (TASTE-A 2022) |
N at baseline Intervention: 49 Control: 55
Patients with AIS on a Mobile Stroke Unit within 4.5 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase II in Australia 2019-2021
TNK regimen: original |
Low |
|
Haley, 2010 (TNK-S2B 2010) |
N at baseline Intervention: 31 Control: 31
Patients with AIS presenting within 3 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase IIb/III in US 2006-2008
TNK regimen: original |
Some concerns |
|
Li, 2022 (TRACE 2021) |
N at baseline Intervention: 57 Control: 59
Patients with AIS presenting within 3 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase II in China 2018-2020
TNK regimen: biosimilar |
Low |
|
Wang, 2023 (TRACE-2 2023) |
N at baseline Intervention: 710 Control: 707
Patients with AIS presenting within 4.5 h |
Intervention: Tenecteplase (TNK) Control: tissue plasminogen activator (alteplase) (TPA) |
3 months |
Functional outcome, mortality, symptomatic intracranial hemorrhage |
Phase III in China 2021-2022
TNK regimen: biosimilar |
Some concerns |
*For further details, see risk of bias table in the appendix
Results
1. Functional outcome (crucial)
1.1 Excellent functional recovery
Palaiodimou (2024) included eleven studies that reported excellent functional outcome at 3 months defined as a modified Rankin Scale (mRS) score ≤1 (Figure 1a). In total, 1980 of the 3722 patients (53.2%) who received tenecteplase had excellent functional outcome at 3 months as compared to 1855 of the 3679 patients (50.4%) who received alteplase (RR=1.05, 95%CI 1.01 to 1.10). This corresponded to an absolute risk difference of 0.02 (95%CI 0.00 to 0.04). This is non-inferior.
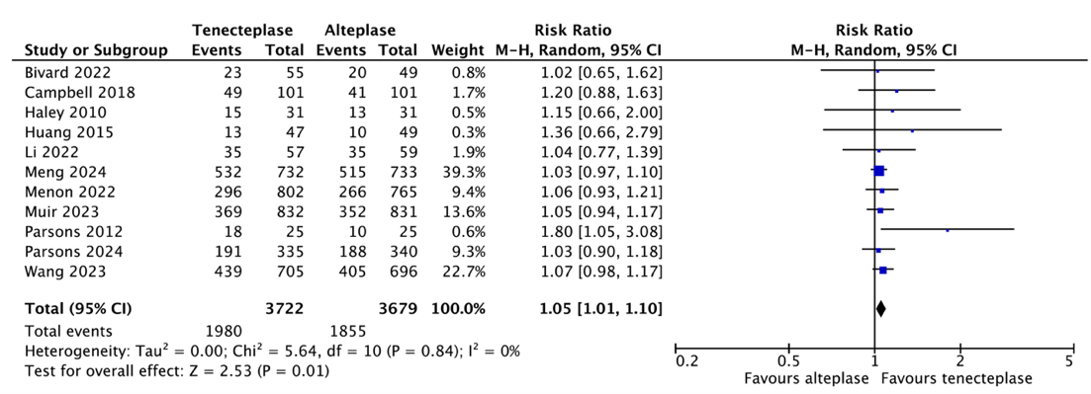
Figure 1a. Excellent functional recovery
1.2 Good functional outcome
Palaiodimou (2024) included eleven studies that reported good functional outcome at 3 months defined as mRS ≤2 (Figure 1b). In total, 2571 of the 3722 patients (69.1%) who received tenecteplase had good functional outcome at 3 months as compared to 2468 of the 3678 patients (67.1%) who received alteplase (RR=1.03, 95%CI 0.99 to 1.07). This corresponded to an absolute risk difference of 0.02 (95%CI -0.00 to 0.04). This is non-inferior.
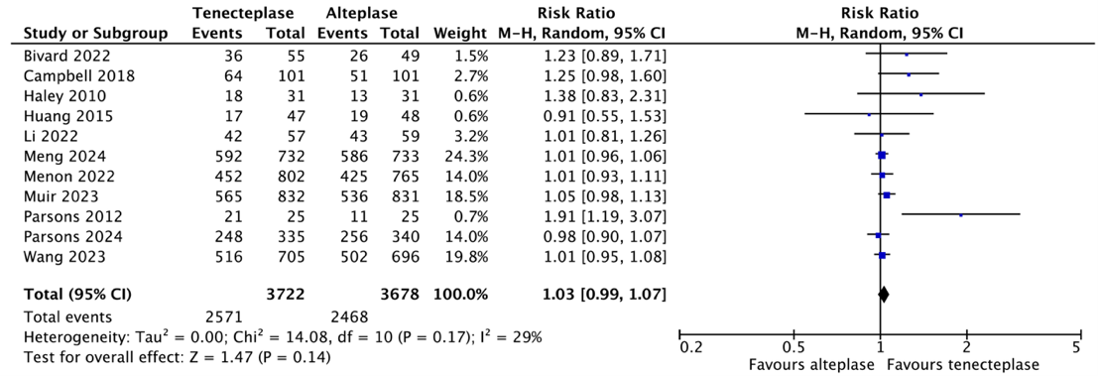
Figure 1b. Good functional outcome
2. Mortality (crucial)
Palaiodimou (2024) included eleven studies that reported mortality at 3 months (Figure 2). In total, 325 of the 3775 patients (8.6%) who received tenecteplase died as compared to 331 of the 3747 patients (8.8%) who received alteplase (RR=0.97, 95%CI 0.82 to 1.15). This corresponded to an absolute risk difference of -0.00 (95%CI -0.02 to 0.02).This is non-inferior.
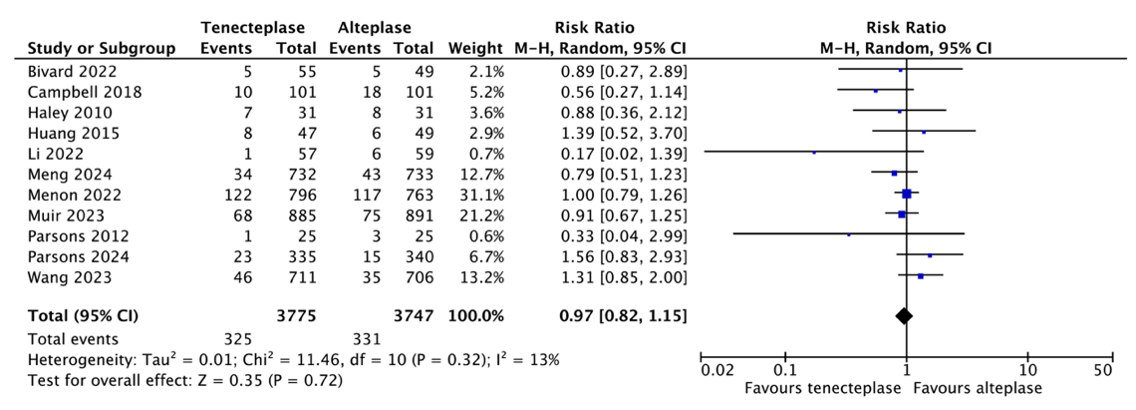
Figure 2. Mortality
3. Symptomatic Intracranial haemorrhage (important)
Palaiodimou (2024) included eleven studies that reported symptomatic intracranial haemorrhage (Figure 3). Eighty-five of the 3786 patients (2.2%) who received tenecteplase had symptomatic intracranial haemorrhage as compared to 75 of the 3749 (2.0%) who received alteplase (RR=1.12, 95%CI 0.83 to 1.53). This corresponded to an absolute risk difference of 0.01 (95%CI -0.02 to 0.05). This is non-inferior.
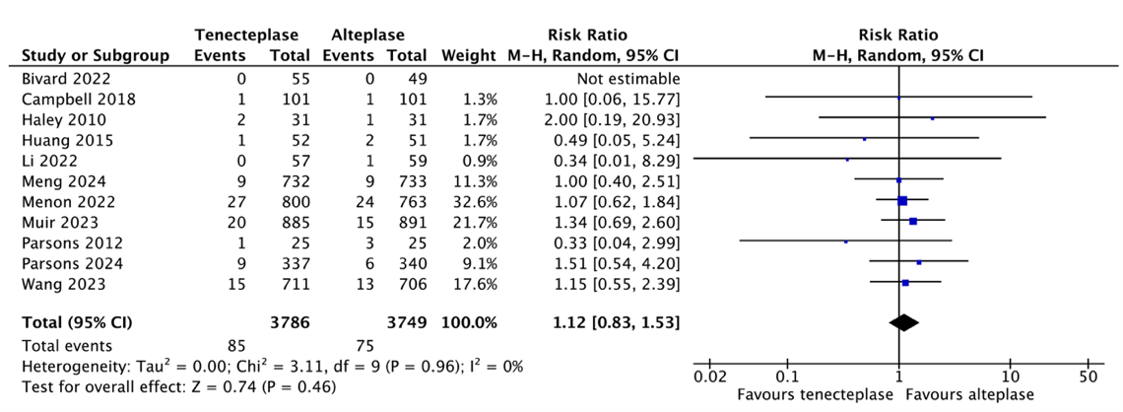
Figure 3. Symptomatic intracranial haemorrhage
4. Reperfusion (important)
Not reported.
A systematic review of the literature was performed to answer the following question(s):
- Is tenecteplase safe and effective as a thrombolytic compared to alteplase in patients with an acute ischaemic stroke <4.5 hours after the onset of symptoms?
- Is tenecteplase safe and effective as a thrombolytic compared to alteplase in patients with an acute ischaemic stroke 4.5-12 hours after the onset of symptoms, or if the time of onset is unknown, in patients selected with additional imaging?
Table 1. PICO
| Patients | Patients with acute stroke |
| Intervention | Treatment with IV tenecteplase |
| Control | Treatment with IV alteplase |
| Outcomes | Functional outcome, mortality rates, symptomatic intracranial haemorrhage, and degree of reperfusion |
| Other selection criteria | Study design: systematic reviews and randomized controlled trials |
Relevant outcome measures
The guideline panel considered functional outcome and mortality rates as critical outcome measures for decision making; and symptomatic intracranial hemorrhage and degree of reperfusion as an important outcome measure for decision making.
The guideline panel defined the outcome measures as follows:
- Functional outcome: excellent functional outcome (mRS 0-1) or good functional outcome (mRS 0-2) at 90 days.
- Mortality: death (mRS 6) at 90 days.
- Symptomatic intracranial haemorrhage (sICH) at 24–48 h.
- Degree of Reperfusion: defined as grade 2b or 3 on the modified Treatment in Cerebral Ischemia (mTICI) scale (reperfusion of greater than 50% in the involved ischaemic territory).
The guideline panel defined an absolute difference of 3% for functional outcome (RD <-0.03 or >0.03) and 1% for mortality, symptomatic intracranial haemorrhage and reperfusion (RD <-0.01 or >0.01) as a minimal clinically (patient) important difference. *Non-inferiority was concluded when the upper bound of the confidence interval remained below the prespecified limit.
*‘Non-inferiority design’ = een onderzoeksopzet waarbij het doel is om aan te tonen dat een nieuwe behandeling of interventie niet slechter is dan de bestaande standaardbehandeling, binnen een vooraf gedefinieerde marge.
Search and select (Methods)
A systematic literature search was performed by a medical information specialist using the following bibliographic databases: Embase.com and Ovid/Medline. Both databases were searched from 2018 to 6-6-2025 for systematic reviews and RCTs. Systematic searches were completed using a combination of controlled vocabulary/subject headings (e.g., Emtree-terms, MeSH) wherever they were available and natural language keywords. The overall search strategy was derived from the following primary search concepts: (1) brain infarction (2) Tenecteplase. Duplicates were removed using EndNote software. After deduplication a total of 313 records were imported for title/abstract screening. Initially, ten studies were selected based on title and abstract screening. After reading the full text, nine studies were excluded (see the exclusion table under the tab ‘Evidence tabellen’), and one systematic review was included.
- Albers GW, Jumaa M, Purdon B, Zaidi SF, Streib C, Shuaib A, Sangha N, Kim M, Froehler MT, Schwartz NE, Clark WM, Kircher CE, Yang M, Massaro L, Lu XY, Rippon GA, Broderick JP, Butcher K, Lansberg MG, Liebeskind DS, Nouh A, Schwamm LH, Campbell BCV; TIMELESS Investigators. Tenecteplase for Stroke at 4.5 to 24 Hours with Perfusion-Imaging Selection. N Engl J Med. 2024 Feb 22;390(8):701-711. doi: 10.1056/NEJMoa2310392. Epub 2024 Feb 8. PMID: 38329148.
- Campbell BCV, Mitchell PJ, Churilov L, Yassi N, Kleinig TJ, Dowling RJ, Yan B, Bush SJ, Dewey HM, Thijs V, Scroop R, Simpson M, Brooks M, Asadi H, Wu TY, Shah DG, Wijeratne T, Ang T, Miteff F, Levi CR, Rodrigues E, Zhao H, Salvaris P, Garcia-Esperon C, Bailey P, Rice H, de Villiers L, Brown H, Redmond K, Leggett D, Fink JN, Collecutt W, Wong AA, Muller C, Coulthard A, Mitchell K, Clouston J, Mahady K, Field D, Ma H, Phan TG, Chong W, Chandra RV, Slater LA, Krause M, Harrington TJ, Faulder KC, Steinfort BS, Bladin CF, Sharma G, Desmond PM, Parsons MW, Donnan GA, Davis SM; EXTEND-IA TNK Investigators. Tenecteplase versus Alteplase before Thrombectomy for Ischemic Stroke. N Engl J Med. 2018 Apr 26;378(17):1573-1582. doi: 10.1056/NEJMoa1716405. PMID: 29694815.
- Chen HS, Chen MR, Cui Y, Shen XY, Zhang H, Lu J, Zhao LW, Duan YJ, Li J, Wang YM, Min LQ, Zhao LH, Wan LS, Zhang ZH, Nguyen TN. Tenecteplase Plus Butyphthalide for Stroke Within 4.5-6 Hours of Onset (EXIT-BT): a Phase 2 Study. Transl Stroke Res. 2025 Jun;16(3):575-583. doi: 10.1007/s12975-024-01231-2. Epub 2024 Jan 19. PMID: 38238620.
- Cheng X, Hong L, Lin L, Churilov L, Ling Y, Yang N, Fu J, Lu G, Yue Y, Zhang J, Wang F, Wang Z, Zhao Y, Zhou X, Peng Z, Wu D, Zhao L, Zhai Q, Yu X, Fang Q, Shao X, Tang Y, Zhang D, Geng Y, Zhang Y, Fan B, Zhang B, Yin C, Chen Y, Zhang Y, Liu X, Li S, Yang L, Parsons M, Dong Q; CHABLIS-T II Collaborators. Tenecteplase Thrombolysis for Stroke up to 24 Hours After Onset With Perfusion Imaging Selection: The CHABLIS-T II Randomized Clinical Trial. Stroke. 2025 Feb;56(2):344-354. doi: 10.1161/STROKEAHA.124.048375. Epub 2025 Jan 2. PMID: 39744861.
- Hacke W, Kaste M, Bluhmki E, Brozman M, Dávalos A, Guidetti D, Larrue V, Lees KR, Medeghri Z, Machnig T, Schneider D, von Kummer R, Wahlgren N, Toni D; ECASS Investigators. Thrombolysis with alteplase 3 to 4.5 hours after acute ischemic stroke. N Engl J Med. 2008 Sep 25;359(13):1317-29. doi: 10.1056/NEJMoa0804656. PMID: 18815396.
- Haley EC Jr, Thompson JL, Grotta JC, Lyden PD, Hemmen TG, Brown DL, Fanale C, Libman R, Kwiatkowski TG, Llinas RH, Levine SR, Johnston KC, Buchsbaum R, Levy G, Levin B; Tenecteplase in Stroke Investigators. Phase IIB/III trial of tenecteplase in acute ischemic stroke: results of a prematurely terminated randomized clinical trial. Stroke. 2010 Apr;41(4):707-11. doi: 10.1161/STROKEAHA.109.572040. Epub 2010 Feb 25. PMID: 20185783; PMCID: PMC2860601.
- Kvistad CE, Næss H, Helleberg BH, Idicula T, Hagberg G, Nordby LM, Jenssen KN, Tobro H, Rörholt DM, Kaur K, Eltoft A, Evensen K, Haasz J, Singaravel G, Fromm A, Thomassen L. Tenecteplase versus alteplase for the management of acute ischaemic stroke in Norway (NOR-TEST 2, part A): a phase 3, randomised, open-label, blinded endpoint, non-inferiority trial. Lancet Neurol. 2022 Jun;21(6):511-519. doi: 10.1016/S1474-4422(22)00124-7. Epub 2022 May 4. PMID: 35525250.
- Ma H, Campbell BCV, Parsons MW, Churilov L, Levi CR, Hsu C, Kleinig TJ, Wijeratne T, Curtze S, Dewey HM, Miteff F, Tsai CH, Lee JT, Phan TG, Mahant N, Sun MC, Krause M, Sturm J, Grimley R, Chen CH, Hu CJ, Wong AA, Field D, Sun Y, Barber PA, Sabet A, Jannes J, Jeng JS, Clissold B, Markus R, Lin CH, Lien LM, Bladin CF, Christensen S, Yassi N, Sharma G, Bivard A, Desmond PM, Yan B, Mitchell PJ, Thijs V, Carey L, Meretoja A, Davis SM, Donnan GA; EXTEND Investigators. Thrombolysis Guided by Perfusion Imaging up to 9 Hours after Onset of Stroke. N Engl J Med. 2019 May 9;380(19):1795-1803. doi: 10.1056/NEJMoa1813046. Erratum in: N Engl J Med. 2021 Apr 1;384(13):1278. doi: 10.1056/NEJMx200014. PMID: 31067369.
- Majoie CB, Cavalcante F, Gralla J, Yang P, Kaesmacher J, Treurniet KM, Kappelhof M, Yan B, Suzuki K, Zhang Y, Li F, Morimoto M, Zhang L, Miao Z, Rinkel LA, Huang J, Otsuka T, Wang S, Davis S, Cognard C, Hong B, Coutinho JM, Song J, Chen W, Emmer BJ, Eker O, Zhang L, Dobrocky T, Nguyen HT, Bush S, Peng Y, LeCouffe NE, Takeuchi M, Han H, Matsumaru Y, Strbian D, Lingsma HF, Nieboer D, Yang Q, Meinel T, Mitchell P, Kimura K, Zi W, Nogueira RG, Liu J, Roos YB, Fischer U; IRIS collaborators. Value of intravenous thrombolysis in endovascular treatment for large-vessel anterior circulation stroke: individual participant data meta-analysis of six randomised trials. Lancet. 2023 Sep 16;402(10406):965-974. doi: 10.1016/S0140-6736(23)01142-X. Epub 2023 Aug 25. PMID: 37640037.
- Meng X, Li S, Dai H, Lu G, Wang W, Che F, Geng Y, Sun M, Li X, Li H, Wang Y. Tenecteplase vs Alteplase for Patients With Acute Ischemic Stroke: The ORIGINAL Randomized Clinical Trial. JAMA. 2024 Nov 5;332(17):1437-1445. doi: 10.1001/jama.2024.14721. PMID: 39264623; PMCID: PMC11393753.
- Menon BK, Buck BH, Singh N, Deschaintre Y, Almekhlafi MA, Coutts SB, Thirunavukkarasu S, Khosravani H, Appireddy R, Moreau F, Gubitz G, Tkach A, Catanese L, Dowlatshahi D, Medvedev G, Mandzia J, Pikula A, Shankar J, Williams H, Field TS, Manosalva A, Siddiqui M, Zafar A, Imoukhuede O, Hunter G, Demchuk AM, Mishra S, Gioia LC, Jalini S, Cayer C, Phillips S, Elamin E, Shoamanesh A, Subramaniam S, Kate M, Jacquin G, Camden MC, Benali F, Alhabli I, Bala F, Horn M, Stotts G, Hill MD, Gladstone DJ, Poppe A, Sehgal A, Zhang Q, Lethebe BC, Doram C, Ademola A, Shamy M, Kenney C, Sajobi TT, Swartz RH; AcT Trial Investigators. Intravenous tenecteplase compared with alteplase for acute ischaemic stroke in Canada (AcT): a pragmatic, multicentre, open-label, registry-linked, randomised, controlled, non-inferiority trial. Lancet. 2022 Jul 16;400(10347):161-169. doi: 10.1016/S0140-6736(22)01054-6. Epub 2022 Jun 29. PMID: 35779553.
- Muir KW, Ford GA, Ford I, Wardlaw JM, McConnachie A, Greenlaw N, Mair G, Sprigg N, Price CI, MacLeod MJ, Dima S, Venter M, Zhang L, O'Brien E, Sanyal R, Reid J, Sztriha LK, Haider S, Whiteley WN, Kennedy J, Perry R, Lakshmanan S, Chakrabarti A, Hassan A, Marigold R, Raghunathan S, Sims D, Bhandari M, Wiggam I, Rashed K, Douglass C; ATTEST-2 Investigators. Tenecteplase versus alteplase for acute stroke within 4·5 h of onset (ATTEST-2): a randomised, parallel group, open-label trial. Lancet Neurol. 2024 Nov;23(11):1087-1096. doi: 10.1016/S1474-4422(24)00377-6. PMID: 39424558.
- National Institute of Neurological Disorders and Stroke rt-PA Stroke Study Group. Tissue plasminogen activator for acute ischemic stroke. N Engl J Med. 1995 Dec 14;333(24):1581-7. doi: 10.1056/NEJM199512143332401. PMID: 7477192.
- Nguyen CP, Lahr MM, van der Zee DJ, van Voorst H, Roos YB, Uyttenboogaart M, Buskens E. Cost-effectiveness of tenecteplase versus alteplase for acute ischemic stroke. Eur Stroke J. 2023 Sep;8(3):638-646. doi: 10.1177/23969873231174943. Epub 2023 May 19. PMID: 37641549; PMCID: PMC10472948.
- Palaiodimou L, Katsanos AH, Turc G, Asimakopoulos AG, Mavridis D, Schellinger PD, Theodorou A, Lemmens R, Sacco S, Safouris A, Katan M, Sarraj A, Fischer U, Tsivgoulis G. Tenecteplase vs Alteplase in Acute Ischemic Stroke Within 4.5 Hours: A Systematic Review and Meta-Analysis of Randomized Trials. Neurology. 2024 Nov 12;103(9):e209903. doi: 10.1212/WNL.0000000000209903. Epub 2024 Oct 16. PMID: 39413337.
- Parsons MW, Yogendrakumar V, Churilov L, Garcia-Esperon C, Campbell BCV, Russell ML, Sharma G, Chen C, Lin L, Chew BL, Ng FC, Deepak A, Choi PMC, Kleinig TJ, Cordato DJ, Wu TY, Fink JN, Ma H, Phan TG, Markus HS, Molina CA, Tsai CH, Lee JT, Jeng JS, Strbian D, Meretoja A, Arenillas JF, Buck BH, Devlin MJ, Brown H, Butcher KS, O'Brien B, Sabet A, Wijeratne T, Bivard A, Grimley RS, Agarwal S, Munshi SK, Donnan GA, Davis SM, Miteff F, Spratt NJ, Levi CR; TASTE investigators. Tenecteplase versus alteplase for thrombolysis in patients selected by use of perfusion imaging within 4·5 h of onset of ischaemic stroke (TASTE): a multicentre, randomised, controlled, phase 3 non-inferiority trial. Lancet Neurol. 2024 Aug;23(8):775-786. doi: 10.1016/S1474-4422(24)00206-0. Epub 2024 Jun 13. PMID: 38880118.
- Roaldsen MB, Eltoft A, Wilsgaard T, Christensen H, Engelter ST, Indredavik B, Jatužis D, Karelis G, Kõrv J, Lundström E, Petersson J, Putaala J, Søyland MH, Tveiten A, Bivard A, Johnsen SH, Mazya MV, Werring DJ, Wu TY, De Marchis GM, Robinson TG, Mathiesen EB; TWIST Investigators. Safety and efficacy of tenecteplase in patients with wake-up stroke assessed by non-contrast CT (TWIST): a multicentre, open-label, randomised controlled trial. Lancet Neurol. 2023 Feb;22(2):117-126. doi: 10.1016/S1474-4422(22)00484-7. Epub 2022 Dec 19. PMID: 36549308.
- Thomalla G, Simonsen CZ, Boutitie F, Andersen G, Berthezene Y, Cheng B, Cheripelli B, Cho TH, Fazekas F, Fiehler J, Ford I, Galinovic I, Gellissen S, Golsari A, Gregori J, Günther M, Guibernau J, Häusler KG, Hennerici M, Kemmling A, Marstrand J, Modrau B, Neeb L, Perez de la Ossa N, Puig J, Ringleb P, Roy P, Scheel E, Schonewille W, Serena J, Sunaert S, Villringer K, Wouters A, Thijs V, Ebinger M, Endres M, Fiebach JB, Lemmens R, Muir KW, Nighoghossian N, Pedraza S, Gerloff C; WAKE-UP Investigators. MRI-Guided Thrombolysis for Stroke with Unknown Time of Onset. N Engl J Med. 2018 Aug 16;379(7):611-622. doi: 10.1056/NEJMoa1804355. Epub 2018 May 16. PMID: 29766770.
- Wang L, Dai YJ, Cui Y, Zhang H, Jiang CH, Duan YJ, Zhao Y, Feng YF, Geng SM, Zhang ZH, Lu J, Zhang P, Zhao LW, Zhao H, Ma YT, Song CG, Zhang Y, Chen HS. Intravenous Tenecteplase for Acute Ischemic Stroke Within 4.5-24 Hours of Onset (ROSE-TNK): A Phase 2, Randomized, Multicenter Study. J Stroke. 2023 Sep;25(3):371-377. doi: 10.5853/jos.2023.00668. Epub 2023 Aug 24. PMID: 37608533; PMCID: PMC10574303.
- Wang Y, Li S, Pan Y, Li H, Parsons MW, Campbell BCV, Schwamm LH, Fisher M, Che F, Dai H, Li D, Li R, Wang J, Wang Y, Zhao X, Li Z, Zheng H, Xiong Y, Meng X; TRACE-2 Investigators. Tenecteplase versus alteplase in acute ischaemic cerebrovascular events (TRACE-2): a phase 3, multicentre, open-label, randomised controlled, non-inferiority trial. Lancet. 2023 Feb 25;401(10377):645-654. doi: 10.1016/S0140-6736(22)02600-9. Epub 2023 Feb 9. Erratum in: Lancet. 2023 Apr 1;401(10382):1078. doi: 10.1016/S0140-6736(23)00627-X. PMID: 36774935.
- Xiong Y, Campbell BCV, Schwamm LH, Meng X, Jin A, Parsons MW, Fisher M, Jiang Y, Che F, Wang L, Zhou L, Dai H, Liu X, Pan Y, Duan C, Xu Y, Xu A, Zong L, Tan Z, Ye W, Wang H, Wang Z, Hao M, Cao Z, Wang L, Wu S, Li H, Li Z, Zhao X, Wang Y; TRACE-III Investigators. Tenecteplase for Ischemic Stroke at 4.5 to 24 Hours without Thrombectomy. N Engl J Med. 2024 Jul 18;391(3):203-212. doi: 10.1056/NEJMoa2402980. Epub 2024 Jun 14. PMID: 38884324.
- Zhou Y, He Y, Campbell BCV, et al. Alteplase for Acute Ischemic Stroke at 4.5 to 24 Hours: The HOPE Randomized Clinical Trial. JAMA. 2025;334(9):788–797. doi:10.1001/jama.2025.12063.
Risk of Bias tables
See systematic review of Palaiodimou (2024).
Table of excluded studies
|
Reference |
Reason for exclusion |
|
Almanna MA, Aloraini ZS, Regenhardt RW, Dmytriw AA, Bayounis MA, Bin-Mahfooz MA, Alghamdi YI, Bucklain YT, Alhoumaily AY, Alotaibi NM. Intravenous Tenecteplase versus Alteplase before Mechanical Thrombectomy in Patients with Large Vessel Occlusion Stroke: A Systematic Review and Meta-Analysis. Cerebrovasc Dis. 2025;54(1):42-52. doi: 10.1159/000536669. Epub 2024 Feb 15. PMID: 38359810. |
Review with more recent search date available; not only RCTs, about LVO. RCT also included in review of Palaiodimou. |
|
Kvistad CE, Næss H, Helleberg BH, Idicula T, Hagberg G, Nordby LM, Jenssen KN, Tobro H, Rörholt DM, Kaur K, Eltoft A, Evensen K, Haasz J, Singaravel G, Fromm A, Thomassen L. Tenecteplase versus alteplase for the management of acute ischaemic stroke in Norway (NOR-TEST 2, part A): a phase 3, randomised, open-label, blinded endpoint, non-inferiority trial. Lancet Neurol. 2022 Jun;21(6):511-519. doi: 10.1016/S1474-4422(22)00124-7. Epub 2022 May 4. PMID: 35525250. |
Wrong dose: 0.4 mg/kg |
|
Shahid S, Saeed H, Iqbal M, Batool A, Masood MB, Ahmad MH, Rehman AU, Aemaz Ur Rehman M, Sultan F. Comparative efficacy and safety of tissue plasminogen activators (tPA) in acute ischemic stroke: A systematic review and network meta-analysis of randomized controlled trials. J Stroke Cerebrovasc Dis. 2025 Mar;34(3):108230. doi: 10.1016/j.jstrokecerebrovasdis.2025.108230. Epub 2025 Jan 9. PMID: 39798629. |
Network meta-analysis; also studies with higher dose included |
|
Sheraz M, Asif N, Khan A, Khubaib Khan M, Maaz Bin Rehan M, Tayyab Amer Ch M, Sadain Khalid A, Oriana Alfieri C, Bouyarden E, Amine Ghenai M, Alareed A, Ahmed R, Ahmed M, Ehsan M. Tenecteplase versus alteplase in patients with acute ischemic stroke: An updated meta-analysis of randomized controlled trials. J Stroke Cerebrovasc Dis. 2025 Jun;34(6):108300. doi: 10.1016/j.jstrokecerebrovasdis.2025.108300. Epub 2025 Mar 27. PMID: 40157656. |
Same studies included as in review of Palaiodimou. |
|
Srisurapanont K, Uawithya E, Dhanasomboon P, Pollasen N, Thiankhaw K. Comparative efficacy and safety among different doses of tenecteplase for acute ischemic stroke: A systematic review and network meta-analysis. J Stroke Cerebrovasc Dis. 2024 Aug;33(8):107822. doi: 10.1016/j.jstrokecerebrovasdis.2024.107822. Epub 2024 Jun 17. PMID: 38897370. |
More recent review available. |
|
Sun LC, Li WS, Chen W, Ren Z, Li CX, Jiang Z, Wang L, Wang DL, Xie Q. Thrombolytic therapy for patients with acute ischemic stroke: systematic review and network meta-analysis of randomized trials. Front Neurol. 2025 Jan 7;15:1490476. doi: 10.3389/fneur.2024.1490476. PMID: 39839875; PMCID: PMC11746078. |
Network meta-analysis; also studies with higher dose included |
|
Tao M, Zhang XH, Yan LW, Mo DC, He RX, Wang T, Zeng YN, Huang RL, Liu HX, Luo M. Risk of intracerebral haemorrhage with tenecteplase versus alteplase in acute ischaemic stroke: a meta-analysis. J Neurol. 2025 Apr 10;272(5):334. doi: 10.1007/s00415-025-13081-5. PMID: 40208343. |
Only about intracranial hemorrhage |
|
Wang Y, Cai X, Fang Q, Zhu J. Efficacy and safety outcomes of Tenecteplase versus Alteplase for thrombolysis of acute ischemic stroke: A meta-analysis of 9 randomized controlled trials. J Neurol Sci. 2024 Mar 15;458:122912. doi: 10.1016/j.jns.2024.122912. Epub 2024 Feb 3. PMID: 38325064. |
More recent review available. |
|
Xiong Y, Wang L, Li G, Yang KX, Hao M, Li S, Pan Y, Wang Y. Tenecteplase versus alteplase for acute ischaemic stroke: a meta-analysis of phase III randomised trials. Stroke Vasc Neurol. 2024 Aug 27;9(4):360-366. doi: 10.1136/svn-2023-002396. PMID: 37640500; PMCID: PMC11420912. |
Better SR available. |
Beoordelingsdatum en geldigheid
Publicatiedatum : 25-09-2026
Beoordeeld op geldigheid : 25-09-2026
Algemene gegevens
Het Nederlands Huisartsen Genootschap heeft een verklaring van geenbezwaar afgegeven.
Samenstelling werkgroep
Voor het ontwikkelen van de richtlijnmodule is in 2022 een multidisciplinair cluster ingesteld. Het cluster Cerebrovasculaire ziekten bestaat uit meerdere richtlijnen (zie hier de actuele clusterindeling). De stuurgroep bewaakt het proces van modulair onderhoud binnen het cluster. De expertisegroepsleden brengen hun expertise in, indien nodig. De volgende personen uit het cluster zijn betrokken geweest bij de herziening van deze module:
Clusterstuurgroepleden
- dr. J.H. (Julia) van Tuijl, neuroloog, NVN
- dr. M.D.I. (Mervyn) Vergouwen, neuroloog, NVN
- dr. I.R. (Ido) van den Wijngaard, neuroloog, NVN
- dr. R. (René) van den Berg, interventie neuro-radioloog, NVvR
- A.M. (Annegien) Lips, ervaringsdeskundige, Hersenletsel
- dr. M. (Margriet) van der Werf, revalidatiearts, VRA
- dr. H.D. (Jeroen) Boogaarts, neurochirurg, NVvN
Betrokken clusterexpertisegroepleden
- dr. J.C. (Jeroen) de Jonge, neuroloog, NVN
- A. (Anne-France) Pirson, AIOS neurologie, NVN
- dr. M. (Maarten) Uyttenboogaart, neuroloog, NVN
Met ondersteuning van
- dr. M.L. (Marja) Molag, adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- L.C. (Laura) van Wijngaarden, junior adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- I. (Ingeborg) van Dusseldorp, senior informatiespecialist, Kennisinstituut van de Federatie Medisch Specialisten
Belangenverklaringen
Een overzicht van de belangen van de clusterleden en het oordeel over het omgaan met eventuele belangen vindt u in onderstaande tabel. De ondertekende belangenverklaringen zijn op te vragen bij het secretariaat van het Kennisinstituut van de Federatie Medisch Specialisten via secretariaat@kennisinstituut.nl.
Gemelde (neven)functies en belangen stuurgroepleden
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Intellectuele belangen en reputatie |
Overige belangen |
Datum |
Restrictie |
|
dr. J.H. (Julia) van Tuijl |
Neuroloog, ETZ Tilburg |
*Commissielid richtlijn epilepsie *Voorzitter focusgroep acute neurologie van de ROAZ Brabant |
Geen |
Geen |
Enkel deelname aan landelijke vasculaire trials zoals CASES en DIST |
Geen |
Geen |
25-03-2025 |
Geen |
|
dr. M.D.I. (Mervyn) Vergouwen |
Neuroloog, UMC Utrecht |
Geen |
Geen |
Geen |
*CSL Behring: deelname aan advisory board meeting, betaling aan UMC Utrecht *Bayer: onderzoeksgeld voor Investigator Initiated Research, betaling aan UMC Utrecht |
Geen |
Geen |
15-08-2023 |
Geen |
|
dr. I.R. (Ido) van den Wijngaard |
Neuroloog, Haaglanden MC |
Commissielid NVN richtlijn |
Geen |
Geen |
Geen |
Geen |
Geen |
02-08-2022 |
Geen |
|
dr. R. (René) van den Berg |
Interventie Neuro-radioloog, Amsterdam UMC, locatie AMC |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
15-08-2023 |
Geen |
|
A.M. (Annegien) Lips |
Patiëntvertegenwoordiger en ervaringsdeskundige NAH |
Deelname aan verschillende richtlijnclusters |
Geen |
Geen |
Geen |
Geen |
Geen |
18-09-2025 |
Geen |
|
dr. M. (Margriet) van der Werf |
Revalidatiearts, Rijndam revalidatie |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
27-10-2022 |
Geen |
|
dr. H.D. (Jeroen) Boogaarts |
Neurochirurg, Radboud UMC, Nijmegen |
Voorzitter stichting kwaliteitsbevordering neurochirurgie. |
Geen |
Geen |
Gecombineerde subsidie van Hartstichting, ZonMW en ook industrie binnen CONTRAST WP2 en 6 (https://www.contrast-consortium.nl/) (voor verbetering overleving stroke patienten door betere triage en aandacht veilige behandeling ; alsook registratie SAB patienten ZonMw; intracerebrale bloedingen trial (DIST) https://www.dutch-ich.nl/ |
Geen |
Consultant voor stryker neurovascular, inkomsten worden aan de afdeling Neurochirurgie van het Radboud UMC betaald. |
29-10-2024 |
Geen |
Gemelde (neven)functies en belangen betrokken expertisegroepleden
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Intellectuele belangen en reputatie |
Overige belangen |
Datum |
Restrictie |
|
dr. J.C. (Jeroen) de Jonge |
Neuroloog, St. Antonius ziekenhuis |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
15-07-2024 |
Geen |
|
A. (Anne-France) Pirson
|
AOIS neurologie, Haaglanden MC |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
20-11-2024 |
Geen |
|
dr. M. (Maarten) Uyttenboogaart
|
Neuroloog, UMC Groningen |
Geen |
Geen |
Geen |
Subsidie van ZonMW, KCE en hartstichting, ten behoeve van de CASES trial (over stent plaatsing bij proximale intra-arteriële oncclusies) waar ik de hoofdonderzoeker van ben. |
Geen |
Geen |
10-07-2024 |
Geen |
Inbreng patiëntenperspectief
Kwalitatieve raming van mogelijke financiële gevolgen in het kader van de Wkkgz
Bij de richtlijnmodule voerden de clusterleden conform de Wet kwaliteit, klachten en geschillen zorg (Wkkgz) een kwalitatieve raming uit om te beoordelen of de aanbevelingen mogelijk leiden tot substantiële financiële gevolgen. Bij het uitvoeren van deze beoordeling is de richtlijnmodule op verschillende domeinen getoetst (zie het stroomschema bij Werkwijze).
|
Module |
Uitkomst raming |
Toelichting |
|
Intraveneuze behandeling met tenecteplase |
Geen financiële gevolgen |
Hoewel uit de toetsing volgt dat de aanbevelingen breed toepasbaar zijn (>40.000 patiënten), volgt ook uit de toetsing dat het geen nieuwe manier van zorgverlening of andere organisatie van zorgverlening betreft. |
Werkwijze
Voor meer details over de gebruikte richtlijnmethodologie verwijzen wij u naar de Werkwijze. Relevante informatie voor de ontwikkeling/herziening van deze richtlijnmodule is hieronder weergegeven.
Zoekverantwoording
Algemene informatie
|
Cluster/richtlijn: Cluster cerebrovasculaire ziekten, richtlijn herseninfarct en hersenbloeding |
|
|
Uitgangsvraag/modules: Wat zijn de indicaties en contra-indicaties voor behandeling met iv tenecteplase bij patiënten met een herseninfarct? |
|
|
Database(s): Embase.com, Ovid/Medline |
Datum: 6-6-2025 |
|
Periode: vanaf 2018 |
Talen: geen restrictie |
|
Literatuurspecialist: Ingeborg van Dusseldorp |
Rayyan review: https://new.rayyan.ai/reviews/1487349/screening |
|
Toelichting: De 13 sleutelartikelen worden gevonden. Drie van de artikelen zijn ouder dan 2018 en worden om die reden niet gevonden in het resultaat. Ze worden wel gevonden in de set zonder limitatie op tijd. |
|
|
Te gebruiken voor richtlijntekst: A systematic literature search was performed by a medical information specialist using the following bibliographic databases: Embase.com and Ovid/Medline. Both databases were searched from 2018 to 6-6-2025 for systematic reviews and RCTs. Systematic searches were completed using a combination of controlled vocabulary/subject headings (e.g., Emtree-terms, MeSH) wherever they were available and natural language keywords. The overall search strategy was derived from the following primary search concepts: (1) brain infarction (2) Tenecteplase. Duplicates were removed using EndNote software. After deduplication a total of 313 records were imported for title/abstract screening |
|
Zoekopbrengst
|
|
EMBASE |
OVID/MEDLINE |
Ontdubbeld |
|
SR |
151 |
82 |
151 |
|
RCT |
155 |
117 |
162 |
|
Observationele studies |
|
|
|
|
Totaal |
306 |
199 |
313 |
*in Rayyan
Zoekstrategie
Embase.com
|
No. |
Query |
Results |
|
#1 |
'brain infarction'/exp OR 'brain ischemia'/exp OR 'cerebrovascular accident'/exp OR (((infarct* OR isch?emi*) NEAR/3 (brain OR cerebral OR stroke OR cerebrovascular OR hemispher* OR encephalopath*)):ti,ab,kw) OR stroke:ti,ab,kw |
865347 |
|
#2 |
'tenecteplase'/exp OR 'tnk tpa':ti,ab,kw OR 'tnkase':ti,ab,kw OR 'metalyse':ti,ab,kw OR 'tenecteplase':ti,ab,kw OR 'tenecterel':ti,ab,kw OR 'tnk therap*':ti,ab,kw |
4205 |
|
#3 |
#1 AND #2 |
1997 |
|
#4 |
#3 AND [2018-2025]/py NOT ('conference abstract'/it OR 'editorial'/it OR 'letter'/it OR 'note'/it OR ‘clinical trial’:dtype) NOT (('animal'/exp OR 'animal experiment'/exp OR 'animal model'/exp OR 'nonhuman'/exp) NOT 'human'/exp) |
720 |
|
#5 |
'meta analysis'/exp OR 'systematic review'/exp OR 'scoping review'/exp OR 'rapid review'/exp OR 'umbrella review'/exp OR 'cochrane database of systematic reviews'/jt OR 'network meta-analysis'/exp OR 'networkmeta analy*':ti,ab,kw OR 'networkmetaanaly*':ti,ab,kw OR metaanaly*:ti,ab,kw OR 'meta analy*':ti,ab,kw OR metanaly*:ti,ab,kw OR prisma:ti,ab,kw OR prospero:ti,ab,kw OR metaanali*:ti,ab,kw OR 'meta anali*':ti,ab,kw OR metanali*:ti,ab,kw OR (((systemati* OR scoping OR umbrella OR 'structured literature') NEAR/3 (review* OR overview*)):ti,ab,kw) OR (((structured OR systemic*) NEAR/3 (review* OR overview* OR synth*) NEAR/3 literature):ti,ab,kw) OR ((systemic* NEAR/1 review*):ti,ab,kw) OR (((systemati* OR literature OR database* OR 'data base*') NEAR/10 search*):ti,ab,kw) OR (((structured OR comprehensive* OR systemic*) NEAR/3 search*):ti,ab,kw) OR (((literature NEAR/3 (review* OR overview*)):ti,ab,kw) AND (search*:ti,ab,kw OR database*:ti,ab,kw OR 'data base*':ti,ab,kw)) OR (('data extraction*':ti,ab,kw OR 'data source*':ti,ab,kw) AND ('study selection*':ti,ab,kw OR 'studies selection*':ti,ab,kw)) OR ('search strateg*':ti,ab,kw AND 'selection criteria*':ti,ab,kw) OR ('data source*':ti,ab,kw AND 'data synth*':ti,ab,kw) OR medline*:ti,ab,kw OR pubmed*:ti,ab,kw OR 'pub med*':ti,ab,kw OR embase:ti,ab,kw OR cochrane*:ti,ab,kw OR (((critical* OR rapid*) NEAR/2 (review* OR overview* OR synth*)):ti) OR ((((critical* OR rapid*) NEAR/3 (review* OR overview* OR synth*)):ab) AND (search*:ab OR database*:ab OR 'data base*':ab)) OR metasynth*:ti,ab,kw OR 'meta synth*':ti,ab,kw OR 'review* of review*':ti,ab,kw |
1080937 |
|
#6 |
'randomized controlled trial'/exp OR (((pragmatic OR practical) NEAR/1 'clinical trial'):ti,ab) OR ((('non inferiority' OR noninferiority OR superiority OR equivalence) NEAR/3 trial):ti,ab) OR rct:ti OR randomly*:ti,ab OR randomi*:ti,ab OR 'random* control*':ti,ab |
2160886 |
|
#7 |
#4 AND #5 |
151 |
|
#8 |
#4 AND #6 NOT #7 |
162 |
|
#9 |
#7 OR #8 |
313 |
|
#10 |
'acute ischemic stroke within 4.5 hours: a systematic review and meta-analysis of randomized trials':ti |
1 |
|
#11 |
'tenecteplase for the treatment of acute ischemic stroke in the extended time window: a systematic review and meta-analysis':ti |
1 |
|
#12 |
'intravenous tenecteplase compared with alteplase for acute ischaemic stroke in canada (act): a pragmatic, multicentre, open-label, registry-linked, randomised, controlled, non-inferiority trial':ti |
1 |
|
#13 |
'alteplase versus tenecteplase for thrombolysis after ischaemic stroke (attest): a phase 2, randomised, open-label, blinded endpoint study':ti |
1 |
|
#14 |
'tenecteplase versus alteplase for acute stroke within':ti |
1 |
|
#15 |
'tenecteplase versus alteplase before thrombectomy for ischemic stroke':ti |
1 |
|
#16 |
'tenecteplase vs alteplase for patients with acute ischemic stroke: the original randomized clinical trial':ti |
1 |
|
#17 |
'a randomized trial of tenecteplase versus alteplase for acute ischemic stroke':ti AND parsons |
1 |
|
#18 |
'tenecteplase versus alteplase for stroke thrombolysis evaluation (taste): a multicentre, prospective, randomized, open-label, blinded-endpoint, controlled phase iii non-inferiority trial protocol':ti |
1 |
|
#19 |
'comparison of tenecteplase with alteplase for the early treatment of ischaemic stroke in the melbourne mobile stroke unit (taste-a): a phase 2, randomised, open-label trial':ti |
1 |
|
#20 |
'phase iib/iii trial of tenecteplase in acute ischemic stroke: results of a prematurely terminated randomized clinical trial':ti |
1 |
|
#21 |
'safety and efficacy of tenecteplase versus alteplase in patients with acute ischaemic stroke (trace): a multicentre, randomised, open label, blinded-endpoint (probe) controlled phase ii study':ti |
1 |
|
#22 |
'tenecteplase versus alteplase in acute ischaemic cerebrovascular events (trace-2): a phase 3, multicentre, open-label, randomised controlled, non-inferiority trial':ti |
1 |
|
#23 |
#10 OR #11 OR #12 OR #13 OR #14 OR #15 OR #16 OR #17 OR #18 OR #19 OR #20 OR #21 OR #22 |
13 |
|
#24 |
#9 AND #23 |
10 |
Ovid/Medline
|
# |
Searches |
Results |
|
1 |
exp Brain Ischemia/ or ((infarct* or isch?emi*) adj3 (brain or cerebral or stroke or cerebrovascular or hemispher* or encephalopath*)).ti,ab,kf. or stroke.ti,ab,kf. |
450941 |
|
2 |
Tenecteplase/ or (tenecteplase or tnkase or "tnk-tpa" or "tnk therap*").ti,ab,kf. |
1148 |
|
3 |
1 and 2 |
588 |
|
4 |
limit 3 to yr="2018 -Current" |
460 |
|
5 |
4 not ((exp animals/ or exp models, animal/) not humans/) not (letter/ or comment/ or editorial/) |
423 |
|
6 |
exp Meta-Analysis/ or exp Network Meta-Analysis/ or exp Systematic Review/ or (networkmeta analy* or networkmetaanaly* or metaanaly* or meta analy* or metanaly* or prisma or prospero or metaanali* or meta anali* or metanali*).ti,ab,kf. or ((systemati* or scoping or umbrella or structured literature) adj3 (review* or overview*)).ti,ab,kf. or ((structured or systemic*) adj3 (review* or overview* or synth*) adj3 literature).ti,ab,kf. or (systemic* adj1 review*).ti,ab,kf. or ((systemati* or literature or database* or data base*) adj10 search*).ti,ab,kf. or ((structured or comprehensive* or systemic*) adj3 search*).ti,ab,kf. or ((literature adj3 (review* or overview*)) and (search* or database* or data base*)).ti,ab,kf. or ((data extraction* or data source*) and (study selection* or studies selection*)).ti,ab,kf. or (search strateg* and selection criteria*).ti,ab,kf. or (data source* and data synth*).ti,ab,kf. or (medline* or pubmed* or pub med* or embase or cochrane*).ti,ab,kf. or cochrane.jw. or ((critical* or rapid*) adj2 (review* or overview* or synth*)).ti. or (((critical* or rapid*) adj3 (review* or overview* or synth*)) and (search* or database* or data base*)).ab. or metasynth*.ti,ab,kf. or meta synth*.ti,ab,kf. |
836634 |
|
7 |
exp randomized controlled trial/ or randomized controlled trials as topic/ or randomi*.ti,ab. or randomly.ti,ab. or rct?.ti,ab. or ((pragmatic or practical) adj "clinical trial*").ti,ab,kf. or ((non-inferiority or noninferiority or superiority or equivalence) adj3 trial*).ti,ab,kf. or "random* control*".ti,ab. |
1498857 |
|
8 |
5 and 6 |
82 |
|
9 |
(5 and 7) not 8 |
117 |
|
10 |
8 or 9 |
199 |