
Biologicals bij COPD
Uitgangsvraag
Wat zijn de effecten van een add-on behandeling met biologicals* op ziekte-stabiliteit en kwaliteit van leven bij patiënten met COPD die reeds optimaal medicamenteus zijn ingesteld?
Is er een subgroep COPD-patiënten te onderscheiden die, meer dan de gemiddelde populatie COPD-patiënten, profiteert van een behandeling met biologicals* m.b.t. klinische stabiliteit en kwaliteit van leven?
*Uitgewerkt voor zowel mepolizumab, benralizumab, reslizumab en dupilumab.
Aanbeveling
Schrijf geen benralizumab voor aan COPD patiënten, ongeacht het bloed-eosinofielenniveau.
Schrijf geen mepolizumab of dupilumab voor in de algemene COPD populatie (<300 eosinofielen/µl bloed).
Start mepolizumab of dupilumab bij COPD patiënten met ≥300 eosinofielen/µl bloed, na het doorlopen van alle hieronder genoemde startcriteria:
- Behandel uitsluitend patiënten met ongecontroleerde COPD ondanks optimale zorg (conform de richtlijn COPD).
- Beperk toepassing tot patiënten met 2 of meer longaanvallen en/of 1 of meer ernstige longaanval(len) per jaar.
- Optimaliseer eerst inhalatiemedicatie (LAMA + LABA + ICS), therapietrouw en inhalatietechniek.
- Rond een volledig optimalisatietraject van treatable traits af (medicamenteus en niet-medicamenteus), inclusief een stop-met-roken-traject, en sluit andere oorzaken van klachten uit.
- Beperk het gebruik van dupilumab tot patiënten met klachten passend bij chronische bronchitis ≥3 maanden in het voorafgaande jaar.
Procesaanbevelingen bij voorschrijven
- Bespreek de behandelindicatie in een regionaal MDO COPD, met kennis en ervaring treatable traits COPD of lokaal/regionaal MDO astma-COPD, met kennis en ervaring biologicals.
- Leg vooraf behandeldoelen vast in overleg met de patiënt en evalueer deze systematisch.
- Staak de behandeling na 4–6 maanden indien behandeldoelen niet worden bereikt.
Overwegingen
Er zijn geen studies naar effectiviteit reslizumab in COPD.
Balans tussen gewenste en ongewenste effecten
Benralizumab – 10 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 10 mg benralizumab bij patiënten met alle eosinofiele waarden.
Benralizumab – 10 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
In de literatuursamenvatting is een studie samengevat die het effect van 10 mg benralizumab of placebo in patiënten met een hoge eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD-exacerbaties, symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Er is waarschijnlijk geen duidelijk voordeel van 10 mg benralizumab op het gebied van COPD-exacerbaties (cruciaal), kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen en longfunctie. Ook is er geen voordeel van 10mg benralizumab op mortaliteit. Uit de literatuur wordt onvoldoende duidelijk wat de mogelijke voordelen zijn van 10 mg benralizumab op symptomen, omdat daarover niet is gerapporteerd.
Benralizumab – 30 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 30 mg benralizumab bij patiënten met alle eosinofiele waarden.
Benralizumab – 30 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
In de literatuursamenvatting zijn twee studies samengevat die het effect van 30 mg benralizumab of placebo in patiënten met hoge eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD-exacerbaties, symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Op basis van de literatuur is er waarschijnlijk geen voordeel van 30 mg benralizumab op COPD-exacerbaties (cruciaal), kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Uit de literatuur wordt onvoldoende duidelijk wat de mogelijke voordelen zijn van 30 mg benralizumab op symptomen, omdat daarover niet is gerapporteerd.
Benralizumab – 100 mg – alle eosinofiele waarden
In de literatuursamenvatting is een studie samengevat die het effect van 100 mg benralizumab of placebo in patiënten met alle eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD-exacerbaties, symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Er is waarschijnlijk geen voordeel van 100 mg benralizumab op COPD-exacerbaties (cruciaal). Ook is er uit de literatuur onvoldoende duidelijk wat de mogelijke voordelen zijn van 100 mg benralizumab op symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit, omdat daarover niet is gerapporteerd.
Benralizumab – 100 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
In de literatuursamenvatting zijn drie studies samengevat die het effect van 100 mg benralizumab of placebo in patiënten met hoge eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD-exacerbaties, symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Er is waarschijnlijk geen voordeel van 100 mg benralizumab voor COPD-exacerbaties (cruciaal), kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen en mortaliteit. Ook is er geen voordeel van 100 mg benralizumab voor longfunctie. Uit de literatuur wordt onvoldoende duidelijk wat de mogelijke voordelen zijn van 100 mg benralizumab op symptomen, omdat daarover niet is gerapporteerd.
Dupilumab – 300 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 300 mg dupilumab bij patiënten met alle eosinofiele waarden.
Dupilumab – 300 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
In de literatuursamenvatting zijn twee studies samengevat die het effect van 300 mg dupilumab of placebo in patiënten met hoge eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD-exacerbaties, symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Uit de literatuur is er een voordeel te zien voor 300 mg dupilumab op COPD-exacerbaties (cruciaal). Er is waarschijnlijk geen voordeel voor kwaliteit van leven en longfunctie. Uit de literatuur is er onvoldoende duidelijk over wat de mogelijke voordelen zijn van 300 mg dupilumab op symptomen, ernstige COPD-exacerbaties, bijwerkingen en mortaliteit, omdat daarover niet is gerapporteerd.
Mepolizumab – 100 mg - alle eosinofiele waarden
In de literatuursamenvatting zijn drie studies samengevat die het effect van 100 mg mepolizumab of placebo in patiënten met alle eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD exacerbaties, symptomen, kwaliteit van leven, ernstige COPD-exacerbaties, bijwerkingen, longfunctie en mortaliteit. Er is geen voordeel op symptomen en kwaliteit van leven. Er is waarschijnlijk geen voordeel op COPD-exacerbaties (cruciaal), ernstige COPD exacerbaties, bijwerkingen en mortaliteit. Uit de literatuur is er onvoldoende duidelijk over wat de mogelijke voordelen zijn van 100 mg mepolizumab op longfunctie, omdat daarover niet is gerapporteerd.
Mepolizumab – 100 mg - hoge eosinofiele waarden (≥ 300 cellen/µL)
In de literatuursamenvatting zijn drie studies samengevat die het effect van 100 mg mepolizumab of placebo in patiënten met hoge eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD exacerbaties, symptomen, kwaliteit van leven, ernstige COPD exacerbaties, bijwerkingen, longfunctie en mortaliteit.
Op basis van de literatuur is er een voordeel te zien van 100 mg mepolizumab op COPD exacerbaties (cruciaal). Op basis van de literatuur is er geen voordeel op symptomen, kwaliteit van leven en longfunctie. Ook is er waarschijnlijk geen voordeel van 100 mg mepolizumab op ernstige COPD exacerbaties, bijwerkingen en mortaliteit.
Mepolizumab – 300 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 300 mg mepolizumab bij patiënten met alle eosinofiele waarden.
Mepolizumab – 300 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
In de literatuursamenvatting is een studie samengevat die het effect van 300 mg mepolizumab of placebo in patiënten met hoge eosinofiele waarden vergelijken aan de hand van de uitkomsten COPD exacerbaties, symptomen, kwaliteit van leven, ernstige COPD exacerbaties, bijwerkingen, longfunctie en mortaliteit. Op basis van de literatuur is er een voordeel te zien van 300 mg mepolizumab op COPD exacerbaties (cruciaal). Er is geen voordeel van 300 mg mepolizumab op symptomen. Ook is er waarschijnlijk geen voordeel op kwaliteit van leven, ernstige COPD exacerbaties, bijwerkingen en mortaliteit. Verder is er uit de literatuur onvoldoende duidelijk wat de mogelijke voordelen zijn van 300 mg mepolizumab op longfunctie, omdat daarover niet is gerapporteerd.
Kwaliteit van bewijs
Benralizumab – 10 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 10 mg benralizumab bij patiënten met alle eosinofiele waarden.
Benralizumab – 10 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt en vanwege het niet bereiken van de optimale steekproefgrootte.
Benralizumab – 30 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 30 mg benralizumab bij patiënten met alle eosinofiele waarden.
Benralizumab – 30 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt en vanwege het niet bereiken van de optimale steekproefgrootte.
Benralizumab – 100 mg – alle eosinofiele waarden
De overall kwaliteit van bewijs is hoog. Dit betekent dat we zeer zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Benralizumab – 100 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt en vanwege het niet bereiken van de optimale steekproefgrootte.
Dupilumab – 300 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 300 mg dupilumab bij patiënten met alle eosinofiele waarden.
Dupilumab – 300 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt.
Mepolizumab – 100 mg - alle eosinofiele waarden
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt en vanwege het niet bereiken van de optimale steekproefgrootte.
Mepolizumab – 100 mg - hoge eosinofiele waarden (≥ 300 cellen/µL)
De overall kwaliteit van bewijs is hoog. Dit betekent dat we zeer zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt en vanwege het niet bereiken van de optimale steekproefgrootte.
Mepolizumab – 300 mg – alle eosinofiele waarden
Er zijn geen studies die hebben gerapporteerd over 300 mg mepolizumab bij patiënten met alle eosinofiele waarden.
Mepolizumab – 300 mg – hoge eosinofiele waarden (≥ 300 cellen/µL)
De overall kwaliteit van bewijs is redelijk. Dit betekent dat we redelijk zeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten.
Er is afgewaardeerd vanwege ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt en vanwege het niet bereiken van de optimale steekproefgrootte.
Waarden en voorkeuren van patiënten (en eventueel hun naasten/verzorgers)
Het doormaken van een longaanval is voor patiënten en hun naasten een impactvolle ervaring. Vaak volgt een ziekenhuisopname. Er is extra medicatie nodig in de vorm van antibiotica en/of prednisolon. Dit brengt veel bijwerkingen met zich mee. De conditie en kwaliteit van leven van een patiënt nemen af. Soms is dit zo erg, dat het eerdere niveau van functioneren niet meer wordt bereikt. Ook zijn met longaanvallen hoge zorgkosten gemoeid. Het is dus alleszins van belang deze longaanvallen zoveel als mogelijk te voorkomen. Het is van belang dat arts en patiënt samen de doelen van de behandeling vaststellen en de keuze voor behandeling met een biological daarop aanpassen, met daarbij als achtergrond dat gebruik van mepolizumab en dupilumab wel een voordeel laten zien voor aantal exacerbaties, maar niet op kwaliteit van leven, symptomen en mortaliteit.
Kostenaspecten
Biologicals kosten tussen de €10.000 en €15.000 per persoon per jaar en zijn aanmerkelijk duurder dan standaard inhalatie- of onderhoudsmedicatie. Het voorschrijven van biologicals voor de indicatie COPD kan daardoor leiden tot een sterke stijging van de medicatiekosten voor COPD. Naast de kosten voor het geneesmiddel zelf worden ook kosten gemaakt voor o.a. verstrekking, toediening en monitoring.
Wanneer biologicals op een juiste manier worden voorgeschreven kan dit het aantal longaanvallen en ernstige longaanvallen met ziekenhuisopnames verminderen. Tevens zou bij stabiel ingestelde patiënten het gebruik van inhalatiemedicatie kunnen afnemen. Verder is er mogelijk een effect op overige zorgkosten en op maatschappelijke kosten (bv arbeidsverzuim/productiviteitsverlies). De totale kosten van de COPD zorg zouden daardoor minder sterk zouden kunnen stijgen dan de prijs van de biologicals doet vermoeden.
Een zorgvuldige patiëntselectie (start-criteria) en hanteren van vooraf gedefinieerde stop-criteria zijn daarom belangrijk voor een doelmatige toepassing van biologicals bij patiënten met COPD.
Gelijkheid ((health) equity/equitable)
Het wel of niet starten met biologicals zal duidelijk omschreven moeten worden in alle richtlijnen. Uniformiteit tussen de verschillende richtlijnen en standaarden is een vereiste voor een succesvolle uitkomst.
Aanvaardbaarheid:
De interventie lijkt aanvaardbaar voor de betrokkenen. Ethische bezwaren zijn beperkt tot zorgen over de betaalbaarheid van de gezondheidszorg en die van dure geneesmiddelen in het bijzonder. Het adagium “duur waar het moet, goedkoop waar het kan” kan in deze lichtlijn gestalte krijgen door start- en stopcriteria nauwgezet te volgen.
Duurzaamheid
Elke aanvullende behandeling gaat gepaard met een extra belasting van het milieu. Een positieve bijdrage van het voorschrijven van biologicals zou kunnen zijn dat stabiel ingestelde patiënten mogelijk minder behoefte hebben aan het gebruik van inhalatiemedicatie, waaronder drijfgasbevattende dosisaerosolen. Verder kan het vermijden van onnodige of ineffectieve behandelingen bijdragen aan een duurzamere zorg.
Haalbaarheid
Gezien de ervaringen met biologicals bij ernstig astma en gezien de mogelijkheid voor zelftoediening thuis voorziet de werkgroep geen belemmeringen rondom praktische, technische, juridische, logistieke en organisatorische aspecten.
Voorwaarde voor toepassing van dupilumab en mepolizumab bij COPD is dat voor beide middelen een add-on indicatiecode wordt vastgesteld met vergoedingsstatus “ja”. Daarnaast dient de verzekeraar van de patiënt deze zorg in te kopen bij het ziekenhuis.
Rationale van de aanbeveling: weging van argumenten voor en tegen de interventies
Benralizumab
Er is waarschijnlijk geen voordeel van benralizumab (10 mg, 30 mg, of 100) op het voorkomen van COPD exacerbaties (cruciaal), zowel in de gehele COPD populatie als in de subgroep met hoge bloed eosinofiel waarden. Ook is er waarschijnlijk geen voordeel van benralizumab (10 mg, 30 mg, of 100) met betrekking op longfunctie, kwaliteit van leven (cruciaal), ziekenhuisopnames, en mortaliteit. M.b.t. de subgroep COPD patiënten met hoge bloed eosinofielwaarden wordt opgemerkt dat de TERRANOVA en GALATHEA studies een lagere cut-off hanteerden (> =220 eosinofielen per microliter), waarbij uit een persbericht van de, nog niet gepubliceerde RESOLUTE studie, bleek dat benralizumab ook niet effectief is in COPD patiënten met >= 300 eosinofielen per microliter.
Dupilumab
Er is geen bewijs voor effectiviteit dupilumab In de gehele COPD populatie.
In de subgroep COPD patiënten met hoge bloed eosinofiel waarden is er waarschijnlijk een voordeel voor dupilumab 300 mg op het voorkomen van COPD exacerbaties (cruciaal). Er is waarschijnlijk een klinisch niet relevante verbetering in longfunctie en kwaliteit van leven met dupilumab. Uit de literatuur is er onvoldoende duidelijkheid over wat de mogelijke voordelen van 300 mg dupilumab op symptomen zijn. Het effect van dupilumab op ernstige exacerbaties, bijwerkingen en mortaliteit is niet bekend omdat daarover niet is gerapporteerd.
Mepolizumab
In de gehele COPD populatie is er waarschijnlijk geen voordeel van mepolizumab (100 mg of 300 mg) op het voorkomen van COPD exacerbaties (cruciaal). Ook is er waarschijnlijk geen voordeel van mepolizumab met betrekking op longfunctie, kwaliteit van leven, ziekenhuisopnames, en mortaliteit in de gehele COPD populatie.
In de subgroep COPD patiënten met hoge bloed eosinofiel waarden is er waarschijnlijk een voordeel van mepolizumab (100 mg of 300 mg) op het voorkomen van COPD exacerbaties (cruciaal). Er is waarschijnlijk geen voordeel van mepolizumab met betrekking op het voorkomen van ernstige COPD exacerbaties. Ook is waarschijnlijk geen voordeel van mepolizumab (100 mg of 300 mg) op kwaliteit van leven en mortaliteit in COPD patiënten met hoge bloed eosinofiel waarden. Er is waarschijnlijk geen voordeel van mepolizumab 100 mg op de longfunctie bij COPD patiënten met hoge bloed eosinofiel waarden. Er is geen bewijs met betrekking tot effect mepolizumab 300 mg op longfunctie in COPD patiënten met hoge bloed eosinofiel waarden.
Reslizumab
Er zijn geen studies naar effectiviteit van reslizumab, zowel in de gehele COPD populatie als in de subgroep COPD patiënten met hoge bloed eosinofiel waarden.
Onderbouwing
COPD remains a leading cause of morbidity and mortality worldwide. As our understanding of COPD pathogenesis evolves, particularly the role of inflammation, immune dysregulation, and distinct COPD phenotypes, biological therapies offer a new avenue for a more targeted treatment that may lead to improved outcomes in patients with COPD.
Benralizumab 10 mg – All patients (low and high counts)
No paper reported on 10 mg Benralizumab in all patients.
Benralizumab 10 mg– Patients with a high blood eosinophil count
|
Outcome |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
|
|
Placebo |
Benralizumab |
||||
|
COPD Exacerbations (Critical) |
Rate difference: -0.18 Based on data from 765 participants in one study Follow up 52 weeks |
1170 |
995 |
Moderate Due to serious imprecision1 |
Benralizumab 10 mg likely results in little to no difference in COPD exacerbations when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
Difference: 175 fewer per 1000 |
|||||
|
Symptoms
|
|
|
|
No evidence was found regarding the effect of Benralizumab 10 mg on symptoms when compared with placebo in patients with a high eosinophil count |
|
|
Quality of life (Important) |
Measured by: SGRQ-C questionnaire Scale: 0 - 40 Lower better Based on data from 680 participants in one study Follow up 52 weeks |
Difference: MD -0.87 (CI 95% -3.23 to 1.49) |
Moderate
Due to serious imprecision 2 |
Benralizumab 10 mg likely results in little to no difference in QoL when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
|
Severe exacerbations (Important) |
Rate difference: -0.06 (CI 95% -0.11 to 0.03) Based on data from 765 participants in one study Follow up 52 weeks
|
250 per 1000 |
188 per 1000 |
Moderate
Due to serious imprecision 3 |
Benralizumab 10 mg likely results in little to no difference in severe exacerbations when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
Difference: 62 fewer per 1000
|
|||||
|
Side Effects- AE |
Risk difference: -0.01 (CI 95% -0.06 to 0.04) Based on data from 1334 participants in one study Follow up 52 weeks |
714 per 1000 |
708 per 1000 |
Moderate
Due to serious imprecision 4 |
Benralizumab 10 mg likely results in little to no difference in AE’s when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
Difference: 6 fewer per 1000
|
|||||
|
Side Effects – SAE |
Risk difference: -0.02 (CI 95% -0.07 to 0.03) Based on data from 1129 participants in one study Follow up 52 weeks |
278 per 1000 |
256 per 1000 |
Moderate
Due to serious imprecision 5 |
Benralizumab 10 mg likely results in little to no difference in SAE’s when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
Difference: 22 fewer per 1000
|
|||||
|
Lung function (Important)
|
Scale: High better Based on data from 669 participants in one study Follow up 52 weeks |
Difference: MD 0.01 lower (CI 95% -0.04 to 0.05) |
Moderate
Due to serious imprecision 6 |
Benralizumab 10 mg likely results in little to no difference in lung function when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
|
Mortality (Important) |
Rate difference: 0.00 Based on data from 1129 participants in one study Follow up 52 weeks |
33 per 1000 |
30 |
High |
Benralizumab 10 mg results in little to no difference in mortality when compared with placebo in patients with a high eosinophil count.
(Criner – TERRANOVA, 2019) |
|
Difference: 3 fewer per 1000
|
|||||
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
Benralizumab 30 mg – All patients (low and high eosinophil counts)
No paper reported on 30 mg Benralizumab in all patients.
Benralizumab 30 mg– Patients with a high blood eosinophil count
|
Outcome |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
||
|
Placebo |
Benralizumab |
|||||
|
COPD Exacerbations (Critical) |
Rate difference: GALATHEA: -0.06 Based on data from 1523 participants in 2 studies Follow up 52 weeks |
TERRANOVA: 1205 per 1000 GALATHEA: 1205 |
TERRANOVA: 1253 per 1000 GALATHEA: 1145 |
Moderate Due to serious imprecision7 |
Benralizumab 30 mg likely results in little to no difference in COPD exacerbations when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: TERRANOVA: 48 more per 1000 GALATHEA: 60 fewer per 1000 |
||||||
|
Symptoms
|
|
|
|
No evidence was found regarding the effect of Benralizumab 30 mg on symptoms when compared with placebo in patients with a high eosinophil count.
|
||
|
Quality of life (Important) |
Measured by: SGRQ-C questionnaire Scale: 0 - 40 Lower better Based on data from 1333 participants in 2 studies Follow up 52-56 weeks |
Difference: TERRANOVA: MD -1.81 GALATHEA: MD -1.11
|
Moderate Due to serious imprecision8 |
Benralizumab 30 mg likely results in little to no difference in QoL when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
||
|
Severe exacerbations (Important) |
Rate difference: TERRANOVA: -0.03 GALATHEA: 0.05 Based on data from 1523 participants in 2 studies Follow up 52 weeks
|
TERRANOVA: 230 per 1000 GALATHEA: 230 |
TERRANOVA: 202 per 1000 GALATHEA: 276 |
Moderate Due to serious imprecision9 |
Benralizumab 30 mg likely results in little to no difference in severe exacerbations when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: TERRANOVA: 28 fewer per 1000 GALATHEA: 46 more per 1000 |
||||||
|
Side Effects- AE |
Risk difference: GALATHEA: 0.01 Based on data from 2235 participants in 2 studies Follow up 52 weeks |
TERRANOVA: 740 per 1000 GALATHEA: 740 |
TERRANOVA: 777 per 1000 GALATHEA: 748 |
Moderate Due to serious imprecision10 |
Benralizumab 30 mg likely results in little to no difference in AE’s when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: TERRANOVA: 37 more per 1000 GALATHEA: 8 more per 1000 |
||||||
|
Side Effects – SAE |
Risk difference: GALATHEA: -0.04 Based on data from 2333 participants in 2 studies Follow up 52 weeks |
TERRANOVA: 299 per 1000 GALATHEA: 299 |
TERRANOVA: 338 per 1000 GALATHEA: 263 |
Moderate Due to serious imprecision11 |
Benralizumab 30 mg likely results in little to no difference in SAE’s when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: TERRANOVA: 39 more per 1000 GALATHEA: 36 fewer per 1000 |
||||||
|
Lung function (Important) |
Scale: High better Based on data from 1322 participants in 2 studies Follow up 52 weeks |
Difference: TERRANOVA: MD -0.01 GALATHEA: MD 0.00
|
Moderate Due to serious imprecision12 |
Benralizumab 30 mg likely results in little to no difference in lung function when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
||
|
Mortality (Important) |
Risk difference: GALATHEA: 0.00 Based on data from 2333 participants in 2 studies Follow up 52 weeks |
TERRANOVA: 29 per 1000 GALATHEA: 29 |
TERRANOVA: 32 per 1000 GALATHEA: 33 |
Moderate Due to serious imprecision13 |
Benralizumab 30 mg likely results in little to no difference in mortality when compared with placebo in patients with a high eosinophil count.
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: TERRANOVA: 2 more per 1000 GALATHEA: 3 more per 1000 |
||||||
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients
Benralizumab 100 mg– All patients (low and high eosinophil counts)
|
Outcome |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
||
|
Placebo |
Benralizumab |
|||||
|
COPD exacerbations |
Rate difference: -0.06 (CI 95% -0.19 to 0.09) Based on data from 2232 participants in two studies Follow up 52 weeks
|
1170 |
1100 |
Moderate
Due to serious imprecision 14
|
Benralizumab 100 mg likely results in little to no difference in COPD exacerbation when compared with placebo in patients with all eosinophil counts (high and low)
(Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: 70 fewer per 1000
|
||||||
|
Symptoms |
|
|
|
|
No evidence was found regarding the effect of Benralizumab 100 mg on symptoms when compared with placebo in patients with all eosinophil counts (high and low) |
|
|
QoL |
|
No evidence was found regarding the effect of Benralizumab 100 mg on QoL when compared with placebo in patients with all eosinophil counts (high and low) |
||||
|
|
||||||
|
Severe exacerbations (Important) |
|
|
|
|
No evidence was found regarding the effect of Benralizumab 100 mg on severe exacerbations when compared with placebo in patients with all eosinophil counts (high and low) |
|
|
Side Effects- AE |
|
No evidence was found regarding the effect of Benralizumab 100 mg on AE’s when compared with placebo in patients with all eosinophil counts (high and low) |
||||
|
|
||||||
|
Side Effects – SAE |
|
|
|
|
No evidence was found regarding the effect of Benralizumab 100 mg on SAE’s when compared with placebo in patients with all eosinophil counts (high and low) |
|
|
|
||||||
|
Lung function
|
|
No evidence was found regarding the effect of Benralizumab 100 mg on lung function when compared with placebo in patients with all eosinophil counts (high and low) |
||||
|
Mortality |
|
|
|
No evidence was found regarding the effect of Benralizumab 100 mg on mortality when compared with placebo in patients with all eosinophil counts (high and low) |
||
- Imprecision: serious. due to the low number of patients.
Benralizumab 100 mg – Patients with high eosinophil counts
|
Outcome |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
||
|
Placebo |
Benralizumab |
|||||
|
COPD Exacerbations (Critical) |
Rate difference: -0.12 Based on data from 1512 participants in 3 studies Follow up 52-56 weeks |
1170 |
1041 |
Moderate Due to serious imprecision15 |
Benralizumab 100 mg likely results in little to no difference in COPD exacerbations when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: 129 fewer per 1000 |
||||||
|
Symptoms
|
|
|
|
No evidence was found regarding the effect of Benralizumab 100 mg on symptoms when compared with placebo in patients with a high eosinophil count |
||
|
Quality of life (Important) |
Measured by: SGRQ-C questionnaire Scale: 0 - 40 Lower better Based on data from 1351 participants in 3 studies Follow up 52-56 weeks |
Difference: MD -1.56 (CI 95% -5.10 to 1.97) |
Moderate Due to serious imprecision16 |
Benralizumab 100 mg likely results in little to no difference in QoL when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
||
|
Severe exacerbations (Important) |
Rate difference: -0.09 (CI 95% -0.11 to -0.03) Based on data from 1594 participants in 3 studies Follow up 52 weeks
|
230 per 1000 |
230 per 1000 |
Moderate
Due to serious imprecision 17 |
Benralizumab 100 mg likely results in little to no difference in severe exacerbations when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: 85 fewer per 1000
|
||||||
|
Side Effects- AE |
Risk difference: 0.02 (CI 95% -0.02 to 0.06) Based on data from 2036 participants in 3 studies Follow up 52 weeks |
765 per 1000 |
788 per 1000 |
High |
Benralizumab 100 mg results in little to no difference in AE’s when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: 23 more per 1000
|
||||||
|
Side Effects – SAE |
Risk difference: 0.003 (CI 95% -0.14 to 0.29) Based on data from 2333 participants in 3 studies Follow up 52 weeks |
278 per 1000 |
281 per 1000 |
Moderate Due to serious imprecision18
|
Benralizumab 100 mg likely results in little to no difference in SAE’s when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: 23 more per 1000
|
||||||
|
Lung function
|
Scale: High better Based on data from 1334 participants in 2 studies Follow up 52-56 weeks |
Difference: MD 0.05 lower (CI 95% -0.15 to 0.26) |
High |
Benralizumab 100 mg results in little to no difference in lung function when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
||
|
Mortality (Important) |
Risk difference: 0.00 (CI 95% -0.01 to 0.01) Based on data from 2333 participants in 3 studies Follow up 52 weeks |
24 |
22 |
Moderate Due to serious imprecision19
|
Benralizumab 100 mg likely results in little to no difference in mortality when compared with placebo in patients with a high eosinophil count
(Brightling, 2014; Criner - GALATHEA, 2019, Criner – TERRANOVA, 2019) |
|
|
Difference: 2 fewer per 1000 |
||||||
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
Dupilumab 300 mg - All patients (low and high eosinophil counts)
No paper reported on 300 mg Dupilumab in all patients.
Dupilumab 300mg - Patients with high eosinophil counts
|
Outcome |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
|
|
Placebo |
Dupilumab |
||||
|
COPD Exacerbations
|
Rate difference: NOTUS: -0.41 Based on data from 1874 participants in 2 studies Follow up 52 weeks |
BOREAS: 1200 per 1000 NOTUS: 1200 |
BOREAS: 840 per 1000 NOTUS: 792 |
Moderate Due to serious imprecision20 |
Dupilumab 300 mg likely reduces COPD exacerbations when compared to placebo in patients with a high eosinophil count.
(Bhatt, 2023; Bhatt 2024) |
|
Difference:
|
|||||
|
Symptoms |
|
|
|
No evidence was found regarding the effect of Dupilumab 300 mg on symptoms when compared with placebo in patients with a high eosinophil count. |
|
|
Quality of life (Important) |
Measured by: SGRQ-C questionnaire Scale: 0 - 100 Lower better Based on data from 1660 participants in 2 studies Follow up 52 weeks
|
Difference: BOREAS: MD -3.30 NOTUS: MD -3.40
|
Moderate Due to serious imprecision21 |
Dupilumab 300 mg may result in little to no difference in QoL when compared to placebo in patients with a high eosinophil count.
(Bhatt, 2023; Bhatt 2024) |
|
|
Severe exacerbations (Important) |
|
|
|
No evidence was found regarding the effect of Dupilumab 300 mg on severe exacerbations when compared with placebo in patients with a high eosinophil count. |
|
|
Side Effects- AE |
|
No evidence was found regarding the effect of Dupilumab 300 mg on AE’s when compared with placebo in patients with a high eosinophil count. |
|||
|
Side Effects- SAE |
|
|
|
No evidence was found regarding the effect of Dupilumab 300 mg on SAE’s when compared with placebo in patients with a high eosinophil count. |
|
|
Lung function (Important) |
Scale: High better Based on data from 1660 participants in 2 studies Follow up 52 weeks |
Difference: BOREAS: MD 0.08 NOTUS: MD 0.06
|
High |
Dupilumab 300 mg results in little to no difference in lung function when compared to placebo in patients with a high eosinophil count.
(Bhatt, 2023; Bhatt 2024) |
|
|
Mortality |
|
|
|
No evidence was found regarding the effect of Dupilumab 300 mg on mortality when compared with placebo in patients with a high eosinophil count.
|
|
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
Mepolizumab 100 mg – All patients (low and high eosinophil counts)
|
Outcome
|
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
||
|
Placebo |
Mepolizumab |
|||||
|
COPD Exacerbations
|
Rate difference: -0.03 (CI 95% -0.23 to 0.18) Based on data from 836 participants in one study Follow up 52 weeks |
1520 per 1000 |
1490 per 1000 |
Moderate Due to serious imprecision22 |
Mepolizumab 100 mg may result in little to no difference in COPD exacerbations when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
|
|
Difference: 30 fewer per 1000
|
||||||
|
Symptoms
|
Measured by: CAT questionnaire Scale: 0 - 40 High better Based on data from 836 participants in one study Follow up 52 weeks |
Difference: MD -0.6 (CI 95% -1.5 - 0.4) |
High |
Mepolizumab 100 mg results in little to no difference in symptoms when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
||
|
Quality of life
|
Measured by: SGRQ-C questionnaire Scale: 0 - 100 Lower better Based on data from 836 participants in one study Follow up 48 - 52 weeks |
Difference: MD 0.7 (CI 95% -1.5 to 2.9) |
High |
Mepolizumab 100 mg results in little to no difference in QoL when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
||
|
Severe exacerbations (Important) |
Rate difference: 0.03 Based on data from 836 participants in one study Follow up 52 weeks |
260 per 1000 |
286 per 1000 |
Moderate
Due to serious imprecision 23
|
Mepolizumab 100 mg likely results in little to no difference in severe exacerbations when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
|
|
Difference: 26 fewer per 1000
|
||||||
|
Side Effects -Adverse events (Important) |
Risk difference: -0.02 Based on data from 836 participants in one study Follow up 52 weeks |
816 per 1000 |
800 per 1000 |
Moderate Due to serious imprecision24
|
Mepolizumab 100 mg likely results in little to no difference in AE’s when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
|
|
Difference: 16 fewer per 1000
|
||||||
|
Side Effects -Serious adverse events (Important) |
Risk difference: -0.04 Based on data from 836 participants in one study Follow up 52 weeks |
313 |
275 |
Moderate Due to serious imprecision25
|
Mepolizumab 100 mg likely results in little to no difference in SAE’s when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
|
|
Difference: 38 fewer per 1000
|
||||||
|
|
||||||
|
Lung function (Important) |
|
|
|
No evidence was found regarding the effect of Mepolizumab 100 mg on lung function when compared with placebo in patients with all eosinophil count (high and low).
(Pavord – METREX, 2017) |
||
|
Mortality (Important) |
Rate difference: 0.00 Based on data from 836 participants in one study Follow up 52 weeks |
40 per 1000 |
39 per 1000 |
Moderate Due to serious imprecision26
|
Mepolizumab 100 mg likely results in little to no difference in mortality when compared to placebo in patients with all eosinophil counts (high and low).
(Pavord – METREX, 2017) |
|
|
Difference: 1 fewer per 1000
|
||||||
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
Mepolizumab 100 mg – Patients with high eosinophil counts
|
Outcome
|
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
||
|
Placebo |
Mepolizumab |
|||||
|
COPD Exacerbations
|
Rate difference: -0.30 (CI 95% -0.36 to -0.24) Based on data from 1785 participants in 3 studies Follow up 52 weeks |
1505 per 1000 |
1204 per 1000 |
Moderate
Due to serious imprecision 27
|
Mepolizumab 100 mg likely reduces COPD Exacerbations when compared to placebo in patients with a high eosinophil count.
(Pavord – METREO, 2017; Pavord – METREX, 2017; Sciurba, 2025) |
|
|
Difference: 301 fewer per 1000
|
||||||
|
Symptoms |
Measured by: CAT questionnaire Scale: 0 - 40 High better Based on data from 1953 participants in 4 studies Follow up 48-52 weeks |
Difference: MD -0.47 (CI 95% -1.68 to 0.74) |
High |
Mepolizumab 100 mg results in little to no difference in symptoms when compared to placebo in patients with a high eosinophil counts.
(Flynn, 2025; Pavord – METREO, 2017; Pavord – METREX, 2017; Sciurba, 2025) |
||
|
Quality of life (Important) |
Measured by: SGRQ-C questionnaire Scale: 0 - 100 Lower better Based on data from 2778 participants in 4 studies Follow up 48 - 52 weeks |
Difference: MD -1.09 (CI 95% -3.28 to 1.11) |
High |
Mepolizumab 100 mg results in little to no difference in QoL when compared to placebo in patients with a high eosinophil counts.
(Flynn, 2025; Pavord – METREO, 2017; Pavord – METREX, 2017; Sciurba, 2025) |
||
|
Severe exacerbations (Important) |
Rate difference: -0.06 Based on data from 1715 participants in 3 studies Follow up 52 weeks |
260 per 1000 |
200 per 1000 |
Moderate Due to serious imprecision28
|
Mepolizumab 100 mg likely results in little to no difference in severe exacerbations when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017; Pavord – METREX, 2017; Sciurba, 2025) |
|
|
Difference: 60 fewer per 1000
|
||||||
|
|
||||||
|
Side Effects- Adverse events
|
Risk difference: Based on data from 911 participants in 2 studies Follow up 52 weeks |
METREO: 821 per 1000 |
METREO: 863 per 1000 |
Moderate Due to serious imprecision29
|
Mepolizumab 100 mg likely results in little to no difference in AE’s when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017; Pavord – METREX, 2017) |
|
|
Difference: METREO: 42 more per 1000
|
||||||
|
Side Effects – Serious adverse events
|
Risk difference: Based on data from 911 participants in 2 studies Follow up 52 weeks |
METREO: 325 per 1000 |
METREO: 276 per 1000 |
Moderate Due to serious imprecision30
|
Mepolizumab 100 mg likely results in little to no difference in SAE’s when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017; Pavord – METREX, 2017) |
|
|
Difference:
|
||||||
|
Lung function (Important) |
Measured by: Scale: - High better Based on data from 804 participants in 1 studies Follow up 52 weeks |
33.6 Mean |
24.6 Mean |
High |
Mepolizumab 100 mg results in little to no difference in lung function when compared to placebo in patients with a high eosinophil counts.
(Sciurba, 2025) |
|
|
Difference: MD -9.0 (CI 95% 60.1 to 42.1 ) |
||||||
|
|
||||||
|
Mortality
|
Risk difference: -0.01 Based on data from 1086 participants in 3 studies Follow up 52 weeks |
40 per 1000 |
27 per 1000 |
Moderate Due to serious imprecision31
|
Mepolizumab 100 mg likely results in little to no difference in mortality when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017; Pavord – METREX, 2017; Sciurba, 2025) |
|
|
Difference: 13 fewer per 1000
|
||||||
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
Mepolizumab 300 mg – All patients (low and high eosinophil counts)
No paper reported on 300 mg Mepolizumab in all patients.
Mepolizumab 300 mg – Patients with high eosinophil counts
|
Outcome
|
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
||
|
Placebo |
Mepolizumab |
|||||
|
COPD Exacerbations
|
Rate difference: -0.21 (CI 95% -0.45 to 0.07) Based on data from 451 participants in one study Follow up 52 weeks |
1490 per 1000 |
1281 per 1000 |
Moderate Due to serious imprecision32 |
Mepolizumab 300 mg likely reduces COPD exacerbations when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
|
|
Difference: 209 fewer per 1000
|
||||||
|
Symptoms |
Measured by: CAT questionnaire Scale: 0 - 40 High better Based on data from 836 participants in one study Follow up 52 weeks |
Difference: MD -0.4 (CI 95% -1.5 to 0.8) |
High |
Mepolizumab 300 mg results in little to no difference in symptoms when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
||
|
Quality of life (Important) |
Measured by: SGRQ-C questionnaire Scale: 0 - 100 Lower better Based on data from 451 participants in one study Follow up 48 - 52 weeks |
Difference: MD -0.1 (CI 95% -2.8 to 2.6) |
Moderate
|
Mepolizumab 300 mg likely results in little to no difference in QoL when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
||
|
Severe exacerbations (Important) |
Rate difference: -0.19 Based on data from 451 participants in one study Follow up 52 weeks |
260 per 1000 |
232 per 1000 |
Moderate |
Mepolizumab 300 mg likely results in little to no difference in QoL when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
|
|
Difference: 28 fewer per 1000
|
||||||
|
Side Effects- Adverse events
|
Risk difference: 0.02 Based on data from 836 participants in one study Follow up 52 weeks |
819 per 1000 |
835 per 1000 |
Moderate |
Mepolizumab 300 mg likely results in little to no difference in AE’s when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
|
|
Difference: 16 more per 1000
|
||||||
|
Side Effects – Serious adverse events
|
Risk difference: -0.03 Based on data from 836 participants in one study Follow up 52 weeks |
301 per 1000 |
268 per 1000 |
Moderate |
Mepolizumab 300 mg likely results in little to no difference in SAE’s when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
|
|
Difference:
|
||||||
|
Lung function (Important) |
|
|
|
No evidence was found regarding the effect of Mepolizumab 300 mg on lung function when compared with placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
||
|
Mortality
|
Risk difference: 0.00 Based on data from 1086 participants in one study Follow up 52 weeks |
40 per 1000 |
35 per 1000 |
Moderate |
Mepolizumab 300 mg likely results in little to no difference in mortality when compared to placebo in patients with a high eosinophil counts.
(Pavord – METREO, 2017) |
|
|
Difference: 5 fewer per 1000
|
||||||
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the confidence interval crossing one border of clinical relevance.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patients.
- Imprecision: serious. due to the low number of patient
Description of studies
A total of five studies were included in the analysis of the literature. Important study characteristics are summarized in table 3. The assessment of the risk of bias is summarized in the risk of bias tables (under the tab ‘Evidence tabellen’).
Bhatt (2023) reported an RCT (BOREAS trial) that was performed at 275 sites in 24 countries to evaluate 300mg dupilumab as add-on therapy or matching placebo once every 2 weeks for 52 weeks in COPD patients. Patients included in the study had COPD with a blood eosinophil count of at least 300 cells/μl and at least two moderate exacerbations or at least one severe exacerbation within the year before screening.
Bhatt (2024) reported a phase 3, randomized, double-blind, placebo-controlled trial (NOTUS) that was conducted at 276 centers across 28 countries to evaluate dupilumab 300 mg or placebo administered subcutaneously every 2 weeks for 52 weeks in patients with moderate-to-severe COPD, a history of exacerbations despite triple inhaled therapy, and a blood eosinophil count ≥300 cells/μl.
Donovan (2020) performed a systematic review of RCTs comparing anti-IL-5 therapies with placebo in patients with a diagnosis of COPD. Comparisons for mepolizumab (two studies reported in one paper) and benralizumab (three studies, reported in two papers) were relevant for the current summary of literature. The search was performed in September 2020. No studies evaluating reslizumab and dupilumab were included.
Flynn (2025) reported a phase 2b randomized, double-blind, placebo-controlled trial (COPD-HELP) that was conducted at a single center in the United Kingdom to evaluate mepolizumab 100 mg or placebo administered subcutaneously every 4 weeks for 48 weeks in AECOPD patients after hospitalization with an acute exacerbation and a blood eosinophil count ≥300 cells/μl at any time in the preceding 12 months.
Sciurba (2025) reported a phase 3, double-blind, randomized, placebo-controlled trial (MATINEE) conducted at 344 centers in 25 countries to evaluate mepolizumab 100 mg or placebo administered subcutaneously every 4 weeks for 52 to 104 weeks in patients with COPD, a history of exacerbations, and a blood eosinophil count ≥300 cells/μl who were receiving background triple inhaled therapy.
Results
Benralizumab
COPD-exacerbations
Criner (2019) and Brightling (2014) reported the annual rate of moderate and severe COPD-exacerbations for patients receiving 10, 30 or 100mg Benralizumab versus placebo.
All patients (low and high eosinophil counts)
In figure 1, a meta-analysis is performed for 100mg Benralizumab versus placebo in patients with low and high eosinophil counts. The pooled rate ratio for all type (high and low eosinophil counts) of patients, based on Criner (2019) (n experimental group 1114; n control group 1118), was 0.94 (95%CI 0.81 to 1.09), the rate difference was -0.06 (95%CI -0.19 to 0.09). This difference was not clinically relevant.
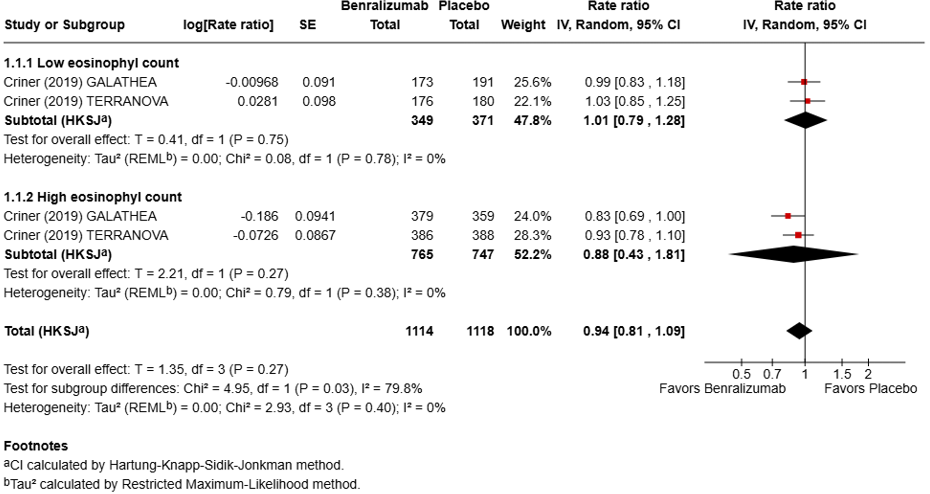
Figure 1: COPD-exacerbation in patients with a high and low eosinophil phenotype, meta-analysis for benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher. A low eosinophil phenotype was defined as a blood eosinophil count of less than 220 cells per cubic mm or a sputum eosinophil count of less than 3%.
Patients with high eosinophil counts (>220 blood count per cubic mm or >3% sputum count)
Criner reported subgroup analyses in patients with high eosinophil counts at baseline (for which was stratified during randomization) for 10, 30 and 100 mg Benralizumab versus placebo. Results are reported in table 4 (high eosinophil counts).
For benralizumab 10mg, based on the TERRANOVA trial (Criner, 2019) the annual rate in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
For benralizumab 30mg, based on the TERRANOVA and GALATHEA trials (Criner, 2019) the annual rate in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
In figure 2, a meta-analysis is performed for Benralizumab 100mg, based on the study by Brightling (2014), and the GALATHEA trial and TERRANOVA trials (Criner, 2019). The pooled rate ratio for patients with high eosinophil counts (n experimental group 805; n control group 789) was 0.89 (95% CI 0.73 to 1.10) and the rate difference was -0.12 (95% CI -0.30 to 0.11). This difference was not clinically relevant.
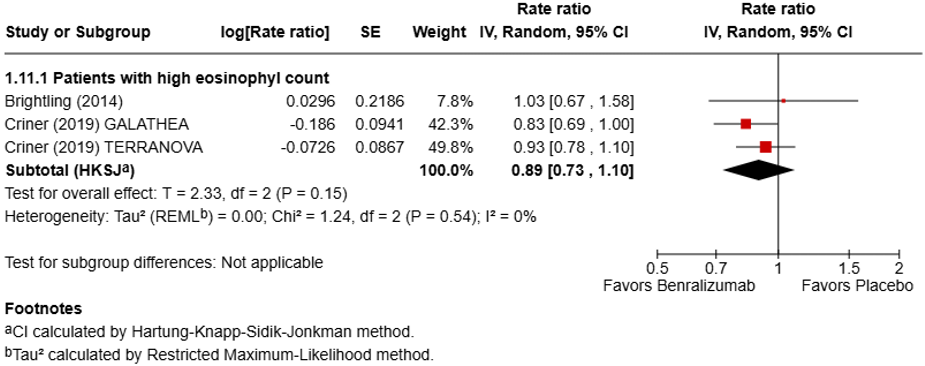
Figure 2: COPD-exacerbation in patients with a high eosinophil phenotype, meta-analysis for benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
Table 4: COPD-exacerbations in patients with Blood Eosinophil Counts of 220 per Cubic Millimeter or more or a sputum eosinophil count of 3% or higher.
|
|
Annual rate (95%CI) |
N |
Annual rate |
N |
Rate ratio (95%CI) |
Rate difference (95%CI) |
|
|
Benralizumab 10mg |
Placebo |
|
|
||
|
Criner (2019) |
0.99 (0.87 to 1.13)1 |
377 |
1.17 (1.04 to 1.32)1 |
388 |
0.85 (0.71 to 1.01)2 |
-0.18 (-0.35 to 0.01)3 |
|
|
Benralizumab 30mg |
Placebo |
|
|
||
|
Criner (2019) |
1.21 (1.08 to 1.37)1 |
394 |
1.17 (1.04 to 1.32)1 |
388 |
1.04 (0.88 to 1.22)2 |
0.05 (-0.14 to 0.27)3 |
|
Criner (2019) |
1.19 (1.04 to 1.36)1 |
382 |
1.24 (1.08 to 1.42)1 |
359 |
0.95 (0.79 to 1.14)2 |
-0.06 (-0.25 to 0.17)3 |
|
|
Benralizumab 100mg |
Placebo |
|
|
||
|
Criner (2019) |
1.09 (0.96 to 1.23)1 |
386 |
1.17 (1.04 to 1.32)1 |
388 |
0.93 (0.79 to 1.11)2 |
-0.08 (-0.25 to 0.13)4 |
|
Criner (2019) |
1.03 (0.90 to 1.19)1 |
379 |
1.24 (1.08 to 1.42)1 |
359 |
0.83 (0.69 to 1.00)2 |
-0.20 (-0.37 to 0.00)4 |
|
Brightling (2014) |
0.92 (0.67 to 1.25) |
40 |
0.95 (0.68 to 1.29) |
42 |
1.03 (0.67 to 1.58 |
-0.03 (-0.31 to 0.55)4 |
|
1 Estimated: Number of Exacerbations * 365.25 / (Last Follow-up Date − Visit 4 Date + 1) 2 Based on a binomial model with adjustments for treatment group, eosinophil-count stratum, geographic region, background therapy or triple therapy and number of previous exacerbations 3 Calculated from rate ratio and median annual rate in control groups TERRANOVA and GALATHEA 4 Calculated from rate ratio and median annual rate in control groups Brightling, TERRANOVA and GALATHEA |
||||||
Symptoms
No paper reported on symptoms after benralizumab treatment.
Quality of life
Criner (2019) and Brightling (2014) reported on the change in Quality of life in patients with a high eosinophil count receiving 10, 30 and 100mg Benralizumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on quality of life after benralizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (>220 blood count per cubic mm or >3% sputum count)
Criner (2019) and Brightling (2014) reported the change in Quality of life (SGRQ-score) after 56 and 52 weeks in patients with a high eosinophil count receiving 10, 30 and 100mg benralizumab versus placebo. Results are reported in figure 3 and table 5.
For benralizumab 10mg, based on the TERRANOVA trial (Criner, 2019), the decrease in SGRQ-score in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
For benralizumab 30mg, based on the TERRANOVA and GALATEA trial (Criner, 2019), the decrease in SGRQ-score in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
Table 5: Change in SGRQ in patients with blood eosinophil Counts of 220 per Cubic Millimeter or more or a sputum eosinophil count of 3% or higher.
|
|
Mean change from baseline (SD) |
N |
Mean change from baseline (SD) |
N |
MD (95%CI) |
|
|
Benralizumab 10mg |
Placebo |
|
||
|
Criner (2019) |
-7.73 (15.0) |
331 |
-6.86 (16.34) |
349 |
-0.87 (-3.23 to 1.49) |
|
|
Benralizumab 30mg |
Placebo |
|
||
|
Criner (2019) |
-8.67 (17.91) |
329 |
-6.86 (16.34) |
349 |
-1.81 (-4.33 to 0.71) |
|
Criner (2019) |
-5.03 (14.68) |
338 |
-3.91 (15.04) |
317 |
-1.11 (-3.39 to 1.17) |
|
|
Benralizumab 100mg |
Placebo |
|
||
|
Criner (2019) |
-7.26 (15.99) |
354 |
-6.86 (16.34) |
349 |
-0.39 (-2.78 to 2.00) |
|
Criner (2019) |
-6.72 (15.72) |
331 |
-3.91 (15.04) |
317 |
-2.81 (-5.18 to -0.44) |
|
Brightling (2014) |
-5.51 (16.64) |
37 |
-4.43 (11.71) |
42 |
-1.08 (-7.51 to 5.35) |
A meta-analysis is performed, based on Brightling (2014), the TERRANOVA and GALATEA trial (Criner, 2019), for 100mg benralizumab versus placebo in patients with low and high eosinophil counts. The pooled mean difference in SGRQ-score (n experimental group 722; n control group 708) was -1.56 (95%CI -5.10 to 1.97). This difference was not clinically relevant.
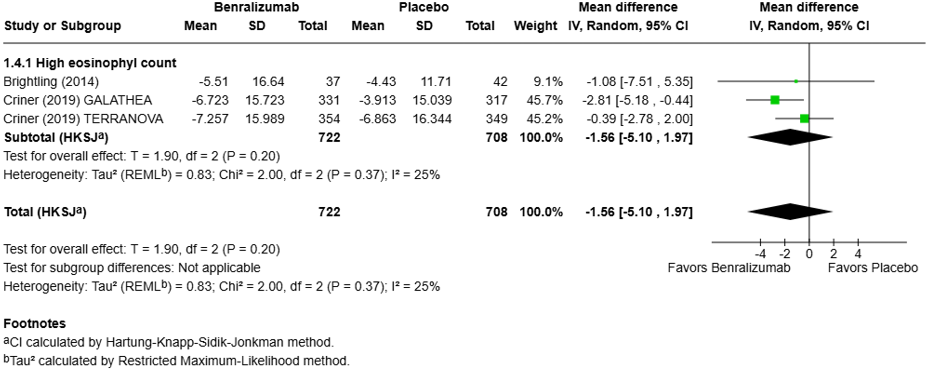
Figure 3: SGRQ in patients with a high eosinophil phenotype, meta-analysis for benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
Severe exacerbations
Criner (2019) and Brightling (2014) reported the annual rate and number of severe COPD-exacerbations requiring hospital admission for patients receiving 10, 30 or 100mg benralizumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on number of severe COPD-exacerbations requiring hospital admission after Benralizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (>220 blood count per cubic mm or >3% sputum count)
Criner (2019) and Brightling (2014) reported the annual rate and number severe of COPD-exacerbations requiring hospital admission for patients with a high eosinophil count receiving 10, 30 or 100mg benralizumab versus placebo. Results are reported in table 6 and 7.
For benralizumab 10mg, based on the TERRANOVA trial (Criner, 2019), the annual rate ratio of severe COPD-exacerbations in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
For benralizumab 30mg, based on the TERRANOVA and GALATEA trial (Criner, 2019), the annual rate ratio of severe COPD-exacerbations in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
For benralizumab 100mg, based on Brightling (2014), the TERRANOVA and GALATEA trial (Criner, 2019), the risk and rate difference of severe COPD-exacerbations the intervention groups were not clinically relevant different compared to the control group in patients with a high eosinophil counts at baseline.
Table 6: Severe COPD exacerbations requiring hospital admission in patients with Blood Eosinophil Counts of 220 per Cubic Millimeter or more
|
|
Annual rate (95%CI) |
N |
Annual rate |
N |
Rate ratio (95%CI) |
Rate difference (95%CI) |
|
|
Benralizumab 10mg |
Placebo |
|
|
||
|
Criner (2019) |
0.18 (0.14 to 0.25)1 |
377 |
0.25 (0.19 to 0.32)1 |
388 |
0.75 (0.51 to 1.11)2 |
-0.06 (-0.11 to 0.03)3 |
|
|
Benralizumab 30mg |
Placebo |
|
|
||
|
Criner (2019) |
0.22 (0.17 to 0.28)1 |
394 |
0.25 (0.19 to 0.32)1 |
388 |
0.88 (0.61 to 1.27)2 |
-0.03 (-0.09 to 0.06)3 |
|
Criner (2019) |
0.25 (0.19 to 0.33)1 |
382 |
0.21 (0.15 to 0.28)1 |
359 |
1.20 (0.80 to 1.80)2 |
0.05 (-0.05 to 0.18)3 |
|
|
Benralizumab 100mg |
Placebo |
|
|
||
|
Criner (2019) |
0.17 (0.13 to 0.22)1 |
386 |
0.25 (0.19 to 0.32)1 |
388 |
0.68 (0.46 to 1.00)2 |
-0.07 (-0.12 to 0)3 |
|
Criner (2019) |
0.12 (0.08 to 0.17)1 |
379 |
0.21 (0.15 to 0.28)1 |
359 |
0.57 (0.36 to 0.91)2 |
-0.10 (-0.15 to -0.02)3 |
|
1 Estimated: Number of Exacerbations * 365.25 / (Last Follow-up Date − Visit 4 Date + 1) 2 Based on a binomial model with adjustments for treatment group, eosinophil-count stratum, geographic region, background therapy or triple therapy and number of previous exacerbations 3 Calculated from rate ratio and median annual rate in control groups TERRANOVA and GALATHEA |
||||||
Table 7: Severe COPD exacerbations requiring hospital admission in patients with a sputum eosinophil count of 3% or higher.
|
|
Events |
N |
Events |
N |
Risk ratio (95%CI) |
Risk difference (95%CI) |
|
|
Benralizumab 100mg |
Placebo |
|
|
||
|
Brightling |
2 |
40 |
5 |
42 |
0.42 (0.09 to 2.04)1 |
-0.07 (-0.11 to 0.12)2 |
|
1Based on a binomial model. 2Calculated from risk ratio and median baseline risk from the control group of Brightling. |
||||||
Side effects
Criner (2019) and Brightling (2014) reported the number of patients reporting adverse events and serious adverse events in patients receiving 10, 30 and 100mg benralizumab versus placebo.
All patients (low and high eosinophil counts)- Adverse events
No paper reported on number of events AE’s after Benralizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts- Adverse events (>220 blood count per cubic mm or >3% sputum count)
Criner (2019) and Brightling (2014) reported the number of patients reporting adverse events and serious adverse events in all patients receiving 10, 30 and 100mg benralizumab versus placebo. Results are reported in figure 4 and table 8.
For benralizumab 10mg, based on the TERRANOVA, the risk difference of the adverse events in the intervention group was not clinically relevant different compared to the placebo group.
For benralizumab 30mg, based on the TERRANOVA and GALATEA trial (Criner, 2019), the risk difference of the adverse events in the intervention group was not clinically relevant different compared to the placebo group.
In figure 4, a meta-analysis is performed for adverse events in patients treated with 100mg benralizumab or placebo. The pooled risk ratio for all type (high and low eosinophil counts) of patients, based on the TERRANOVA and GALATEA (Criner, 2019) and Brightling (2014) (n experimental group 1165; n control group 1168), was 1.03 (95% CI 0.98 to 1.08) with a risk difference of 0.02 (95% CI -0.02 to 0.06). This difference was not clinically relevant.
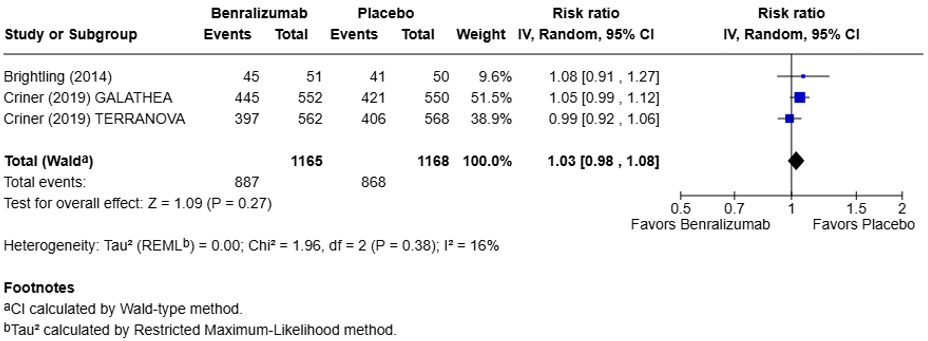
Figure 4: Number of patients with a high eosinophil eosinophil phenotype reporting an adverse event, meta-analysis for Benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
Table 8: Number of patients with a high eosinophil count reporting an adverse event.
|
|
Patients with an AE (%) |
N |
Patients with an AE (%) |
N |
Risk ratio (95% CI) |
Risk difference (95%CI) |
|
|
Benralizumab 10mg |
Placebo |
|
|
||
|
Criner (2019) |
395 (70.4) |
561 |
406 (71.5) |
568 |
0.99 (0.91 to 1.06) |
-0.01 (-0.06 to 0.04)1 |
|
|
Benralizumab 30mg |
Placebo |
|
|
||
|
Criner (2019) |
424 (75.3) |
563 |
406 (71.5) |
568 |
1.05 (0.98 to 1.13) |
0.04 (-0.02 to 0.10) 1 |
|
Criner (2019) |
427 (77.1) |
554 |
421 (76.5) |
550 |
1.01 (0.94 to 1.07) |
0.01 (-0.04 to 0.05) 1 |
|
|
Benralizumab 100mg |
Placebo |
|
|
||
|
Criner (2019) |
397 (70.6) |
562 |
406 (71.5) |
568 |
0.99 (0.92 to 1.06) |
0.01 (-0.06 to 0.05) 1 |
|
Criner (2019) |
445 (80.6) |
552 |
421 (76.5) |
550 |
1.05 (0.99 to 1.12) |
0.04 (-0.01 to 0.09) 1 |
|
Brightling (2014) |
45 (88) |
51 |
41 (82) |
50 |
1.08 (0.91 to 1.27) |
0.06 (-0.07 to 0.22) 1 |
|
1Calulated form the risk ratio and median baseline rate in control groups TERRANOVA, GALATHEA and Brightling. |
||||||
All patients (low and high eosinophil counts)- Serious adverse events
No paper reported on number of SAE’s after benralizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts - Serious adverse events (>220 blood count per cubic mm or >3% sputum count)
Criner (2019) and Brightling (2014) reported the number of patients reporting serious adverse events in all patients receiving 10, 30 and 100mg benralizumab versus placebo. Results are reported in figure 5 and table 9.
For benralizumab 10mg, based on the TERRANOVA, the risk difference of the serious adverse events in the intervention group was not clinically relevant different compared to the placebo group.
For benralizumab 30mg, based on the TERRANOVA and GALATEA trial (Criner, 2019), the risk difference of the serious adverse events in the intervention group was not clinically relevant different compared to the placebo group.
In figure 5, a meta-analysis is performed for 100mg benralizumab versus placebo in patients. The pooled mean change of the serious adverse events in patients with a high eosinophil count (n experimental group 1165; n control group 1168) was 0.94 (95% CI 0.57 to 156) with risk difference of 0.003 (95% CI -0.14 to 0.29). This difference was not clinically relevant.
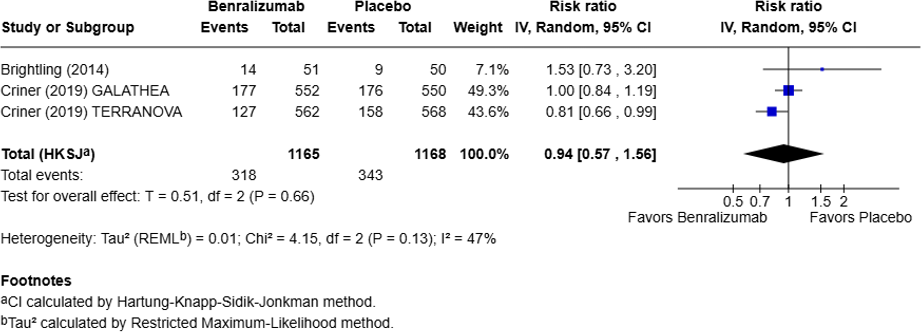
Figure 5: Number of patients with a high eosinophil phenotype reporting a serious adverse event, meta-analysis for benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
Table 9: Serious adverse events in patients with a high eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
|
|
Patients with an AE (%) |
N |
Patients with an AE (%) |
N |
Risk ratio (95% CI) |
Risk Difference (95% CI) |
|
|
Benralizumab 10mg |
Placebo |
|
|
||
|
Criner (2019) |
144 (25.7) |
561 |
158 (27.8) |
568 |
0.92 (0.76 to 1.12) |
-0.02 (-0.07 to 0.03)1 |
|
|
Benralizumab 30mg |
Placebo |
|
|
||
|
Criner (2019) |
177 (31.4) |
563 |
158 (27.8) |
568 |
1.13 (0.94 to 1.35) |
0.04 (-0.02 to 0.10)1 |
|
Criner (2019) |
151 (27.3) |
554 |
176 (32) |
550 |
0.88 (0.66 to 0.99) |
-0.04 (-0.10 to -0.00)1 |
|
|
Benralizumab 100mg |
Placebo |
|
|
||
|
Criner (2019) |
127 (22.6) |
562 |
158 (27.8) |
568 |
0.81 (0.66 to 0.99) |
-0.06 (-0.11 to -0.00)1 |
|
Criner (2019) |
177 (32.1) |
552 |
176 (32) |
550 |
1.00 )0.84 to 1.19) |
0 (-0.05 to 0.06)1 |
|
Brightling (2014) |
14 (27) |
51 |
9 (18) |
50 |
1.53 (0.73 to 3.20) |
0.15 (-0.08 to 0.62)1 |
|
1Calulated form the risk ratio and median baseline rate in control groups TERRANOVA, GALATHEA and Brightling. |
||||||
Lung function (FEV1)
Criner (2019) and Brightling (2014) reported the change in FEV1 after 56 and 52 weeks in patients receiving 10, 30 and 100mg Benralizumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on lung function after Benralizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (>220 blood count per cubic mm or >3% sputum count)
Criner (2019) and Brightling (2014) reported the change in FEV1 after 56 and 52 weeks in patients with a high eosinophil count receiving 10, 30 and 100mg benralizumab versus placebo. Results are reported in table 10 and figure 6.
For benralizumab 10mg, based on the TERRANOVA, the increase in FEV1 in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
For benralizumab 30mg, based on the TERRANOVA and GALATEA trial (Criner, 2019), the change in FEV1 in the intervention group was not clinically relevant different compared to the intervention group.
Table 10: FEV1 in patients with a high Eosinophil Count. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
|
|
Mean change from baseline in Liters (SD) |
N |
Mean change from baseline in Liters (SD) |
N |
MD in Liters (95%CI) |
|
|
Benralizumab 10mg |
Placebo |
|
||
|
Criner (2019) |
0.021 (0.346) |
325 |
0.016 (0.292) |
344 |
0.01 (-0.04 to 0.05) |
|
|
Benralizumab 30mg |
Placebo |
|
||
|
Criner (2019) |
0.011 (0.289) |
344 |
0.016 (0.292) |
344 |
-0.01 (-0.05 to 0.04) |
|
Criner (2019) |
0.014 (0.282) |
317 |
0.01 (0.275) |
317 |
0.00 (-0.04 to 0.05) |
|
|
Benralizumab 100mg |
Placebo |
|
||
|
Criner (2019) |
0.033 (0.291) |
347 |
0.016 (0.292) |
344 |
0.02 (-0.03 to 0.06) |
|
Criner (2019) |
0.031 (0.294) |
326 |
0.01 (0.275) |
317 |
0.02 (-0.02 to 0.06) |
|
Brightling (2014) |
0.13 (0.41) |
45 |
-0.06 (0.24) |
46 |
0.19 (0.05 to 0.33) |
In figure 6, a meta-analysis is performed for 100mg Benralizumab versus placebo. Based on Brightling, the TERRANOVA trial and GALATEA trial (Criner, 2019), the pooled mean change in FEV1 for all type of patients (n experimental group 718; n control group 707) was 0.05 (95%CI -0.15 to 0.26). This difference was not clinically relevant.
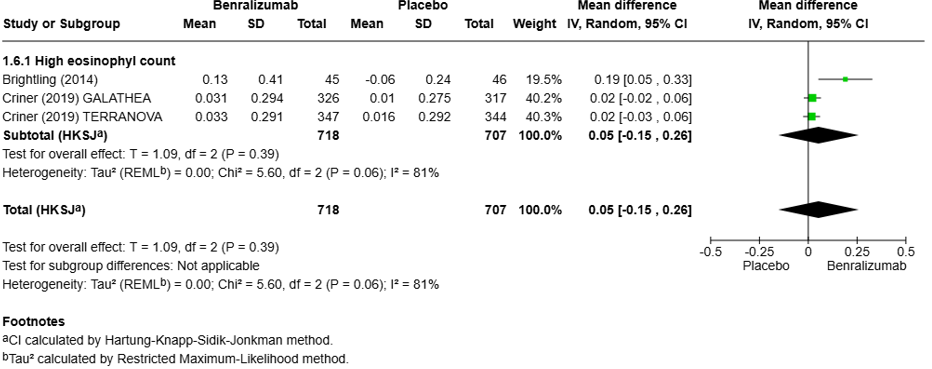
Figure 6: FEV1 in patients with a high eosinophil count, meta-analysis for benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
Mortality
Criner (2019) and Brightling (2014) reported mortality after 56 and 52 weeks in patients receiving 10, 30 and 100mg benralizumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on mortality after benralizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (>220 blood count per cubic mm or >3% sputum count)
Criner (2019) and Brightling (2014) reported mortality after 56 and 52 weeks in patients with a high eosinophil count receiving 10, 30 and 100mg Benralizumab versus placebo. Results are reported in table 11. In figure 7, a meta-analysis is performed for 100mg Benralizumab versus placebo.
For benralizumab 10mg, based on the TERRANOVA, mortality in the intervention group was not clinically relevant different compared to the control group.
For benralizumab 30mg, based on the TERRANOVA and GALATEA trial (Criner, 2019), mortality in the intervention group was not clinically relevant different compared to the control group.
For benralizumab 100mg, based on Brightling (2014), the TERRANOVA trial and GALATEA trial (Criner, 2019), in all types of patients, the meta-analysis showed that 31 of 1165 (2.7%) patients in the experimental group compared to 33 of 1168 (2.8%) patients in the control group died. The pooled mortality risk ratio was 0.94 (95%CI 0.58 to 1.53) and the risk difference was 0.00 (95%CI -0.01 to 0.01). This was not clinically relevant different.
Table 11: mortality in all patients
|
|
Events |
N |
Events |
N |
Risk ratio (95%CI) |
Risk difference (95%CI) |
|
|
Benralizumab 10mg |
Placebo |
|
|
||
|
Criner (2019) |
17 |
561 |
19 |
568 |
0.91 (0.48 to 1.72) |
0.00 (-0.01 to 0.02) 1 |
|
|
Benralizumab 30mg |
Placebo |
|
|
||
|
Criner (2019) |
21 |
563 |
19 |
568 |
1.12 (0.61 to 2.05) |
0.00 (-0.01 to 0.02) 1 |
|
Criner (2019) |
15 |
554 |
13 |
550 |
1.15 (0.55 to 2.38) |
0.00 (-0.01 to 001) 1 |
|
|
Benralizumab 100mg |
Placebo |
|
|
||
|
Criner (2019) |
17 |
562 |
19 |
568 |
0.90 (0.47 to 1.72) |
-0.00 (-0.01 to 0.02)1 |
|
Criner (2019) |
12 |
552 |
13 |
550 |
0.92 (0.42 to 2.00) |
-0.00 (-0.01 to 0.02)1 |
|
Brightling (2014) |
2 |
51 |
1 |
50 |
1.96 (0.18 to 20.94 |
0.02 (-0.02 to 0.47)1 |
|
1Calulated form the risk ratio and median baseline rate in control groups TERRANOVA, GALATHEA and Brightling. |
||||||
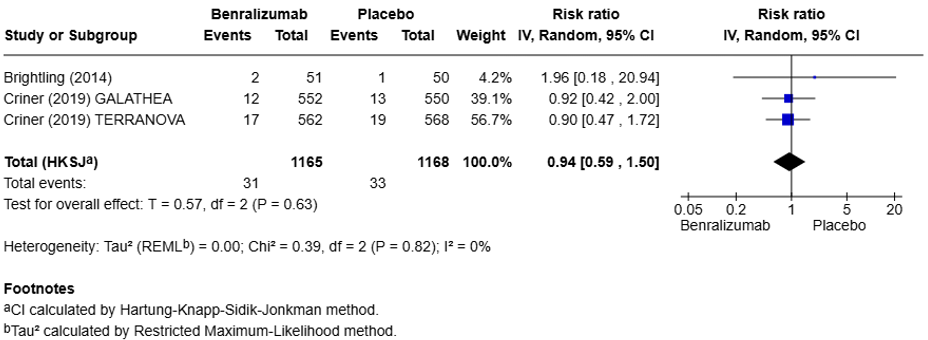
Figure 7: Mortality in patients with a high eosinophil count, meta-analysis for benralizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 220 per cubic mm or greater or a sputum eosinophil count of 3% or higher.
Dupilumab
COPD-exacerbations
Bhatt 2023 and Bhatt 2024 reported on the annual rate of moderate to severe COPD-exacerbations for patients receiving 300 mg dupilumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on COPD exacerbations after dupilumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (≥300 blood count per cubic mm)
Bhatt 2023 and Bhatt 2024 reported on the annual rate of moderate to severe COPD-exacerbations for patients with a high eosinophil count receiving 300 mg dupilumab versus placebo. Results are reported in table 12. Both studies report clinically relevant lower rate differences in favor of the intervention in comparison to the placebo group.
Table 12: COPD-exacerbations in patients with a high blood eosinophil count (Blood Eosinophil Counts of 300 per Cubic Millimeter or more)
|
|
Annual rate (95%CI) |
N |
Annual rate (95%CI) |
N |
Rate ratio (95%CI) |
Rate difference (95%CI) |
|
|
Dupilumab 300mg |
Placebo |
|
|
||
|
Bhatt (2023) BOREAS |
0.78 (0.64 to 0.93) |
468 |
1.10 (0.93 to 1.30) |
471 |
0.70 (0.58 to 0.86)1 |
-0.36 (-0,5 to -0.17)2 |
|
Bhatt (2024) |
0.86 (0.70 to 1.06) |
470 |
1.30 (1.05 to 1.60) |
465 |
0.66 (0.54 to 0.82) 1 |
-0.41 (-0.55 to 0.22)2 |
|
1 Based on a negative binomial model with adjustment for treatment group, eosinophil-count stratum, region, background therapy and number of exacerbations in the previous year. 2 Calculated from rate ratio and median annual rate in control groups BOREAS and NOTUS. |
||||||
Symptoms
No paper reported on symptoms after dupilumab treatment.
Quality of life (SGRQ)
Bhatt 2023 and Bhatt 2024 reported the change in Quality of life (SGRQ-score) after 52 weeks in patients receiving 300mg dupilumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on COPD exacerbations after dupilumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (≥300 blood count per cubic mm)
Bhatt 2023 and Bhatt 2024 reported the change in Quality of life (SGRQ-score) after 52 weeks in patients with a high eosinophil count receiving 300mg dupilumab versus placebo. Results are reported in table 13. The mean change in both intervention groups was not clinically relevant different compared to the control group.
Table 13: Change in SGRQ in patients with Blood Eosinophil Counts of 300 per Cubic Millimeter or more.
|
|
Mean change from baseline (SD) |
N |
Mean change from baseline (SD) |
N |
MD (95%CI) |
|
|
Dupilumab 300mg |
Placebo |
|
||
|
Bhatt (2023) BOREAS |
-9.7 (-11.3 to -8.1)1 |
468 |
-6.4 (-8.0 to -4.8) 1 |
471 |
-3.30 (-5.56 to -1.04) 1 |
|
Bhatt (2024) |
-9.8 (-11.6 to -8.0) |
362 |
-6.4 (-8.3 to -4.6) |
359 |
-3.40 (-5.98 to -0.82)1 |
|
1 least square mean changes |
|||||
Severe exacerbations
No paper reported on severe exacerbations after dupilumab treatment.
Side effects
No paper reported on side effects after dupilumab treatment.
Lung function (FEV1)
Bhatt 2023 and Bhatt 2024 reported the change in FEV1 after 52 weeks in patients receiving 300mg dupilumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on lung function after dupilumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (≥300 blood count per cubic mm)
Bhatt 2023 and Bhatt 2024 reported the change in FEV1 after 52 weeks in patients with a high blood eosinophil count receiving 300mg dupilumab versus placebo. Results are reported in table 14. Both studies report no clinically relevant differences between the intervention and the control group.
Table 14: FEV1 in patients with Blood Eosinophil Counts of 300 per Cubic Millimeter or more.
|
|
Mean change from baseline in liters (95% CI) |
N |
Mean change from baseline in liters (95% CI) |
N |
MD in liters (95%CI) |
|
|
Dupilumab 300mg |
Placebo |
|
||
|
Bhatt (2023) BOREAS |
0.15 (0.12 to 0.19)1 |
468 |
0.07 (0.03 to 0.11) 1 |
471 |
0.08 (0.04 to 0.13) 1 |
|
Bhatt (2024) NOTUS |
0.12 (0.08 to 0.16) |
362 |
0.05 (0.01 to 0.09) |
359 |
0.06 (0.01 to 0.11)1 |
|
1 least square mean changes |
|||||
Mortality
No paper reported on mortality after Dupilumab treatment.
Mepolizumab
COPD-exacerbations
Pavord (2017) and Sciurba (2025) reported the annual rate of moderate and severe COPD-exacerbations for patients receiving 100mg or 300mg mepolizumab versus placebo.
All patients (low and high eosinophil counts)
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg mepolizumab versus placebo. The results are reported in table 15. The rate difference was not clinically relevant.
Table 15: COPD-exacerbations in all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Annual rate (95%CI) |
N |
Annual rate (95%CI) |
N |
Rate ratio (95%CI) |
Rate difference (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREX |
1.49 (NR) |
417 |
1.52 (NR) |
419 |
0.98 (0.85 to 1.12)1 |
-0.03 (-0.23 to 0.18)2 |
|
1 Based on a negative binomial model with adjustment for smoking status, number of moderate or severe exacerbations in the previous year, baseline disease severity and geographic region. In addition, the natural log of time was included as an offset variable. 2 Calculated from rate ratio and median annual rate in control group in METREX. |
||||||
Patients with high eosinophil counts (≥150 blood count at screening or ≥300 in previous year)
Pavord (2017) and Sciurba (2025) reported the annual rate of moderate and severe COPD-exacerbations for patients receiving 100mg or 300mg mepolizumab versus placebo in patients with high eosinophil counts at baseline (for which was stratified during randomization). Results are reported in table 16. In figure 8, a meta-analysis is performed for 100mg mepolizumab versus placebo.
For mepolizumab 100mg, based on the METREO and METREX trial (Pavord, 2017) and Sciurba (2025), the pooled rate ratio for patients with a high eosinophil count (n experimental group 849; n control group 926) was 0.80 (95% CI 0.76 to 0.84) in the intervention group. The rate difference is -0.30 (95% CI -0.36 to -0.24). This difference is clinically relevant.
For mepolizumab 300mg, based on the METREO trial (Pavord, 2017) the rate difference in the intervention group was clinically relevant compared to the control group in patients with a high eosinophil count at baseline -0.21 (95% CI -0.45 to 0.07).
Table 16. COPD-exacerbations in patients with a high blood Eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Annual rate (95%CI or SD) |
N |
Annual rate (95%CI or SD) |
N |
Rate ratio (95%CI) |
Rate difference (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREO |
1.19 (NR) |
223 |
1.49 (NR) |
226 |
0.80 (0.65 to 0.98)1 |
-0.30 (-0.52 to -0.03)3 |
|
Pavord (2017) |
1.40 (NR) |
233 |
1.71 (NR) |
299 |
0.82 (0.68 to 0.98) 1 |
-0.27 (-0.48 to -0.03) 3 |
|
Sciurba (2025) |
0.80 (0.70 to 0.91) |
403 |
1.01 (0.89 to 1.15) |
401 |
0.79 (0.66 to 0.94)2 |
-0.31 (-0.51 to -0.09) 3 |
|
|
Mepolizumab 300 mg |
Placebo |
|
|
||
|
Pavord (2017) METREO |
1.27 (NR) |
225 |
1.49 (NR) |
226 |
0.86 (0.70 to 1.05) 1 |
-0.21 (-0.45 to 0.07) 3 |
|
1 Based on a negative binomial model with adjustment for smoking status, number of moderate or severe exacerbations in the previous year, baseline disease severity and geographic region. In addition, the natural log of time was included as an offset variable. 2 Based on a negative binomial model with adjustment for smoking status, number of exacerbations in the previous year, baseline severity of airflow obstruction, and geographic region, with the natural log of time included as offset variable. 3 Calculated from rate ratio and median annual rate in control groups METREO, METREX and Sciurba. |
||||||
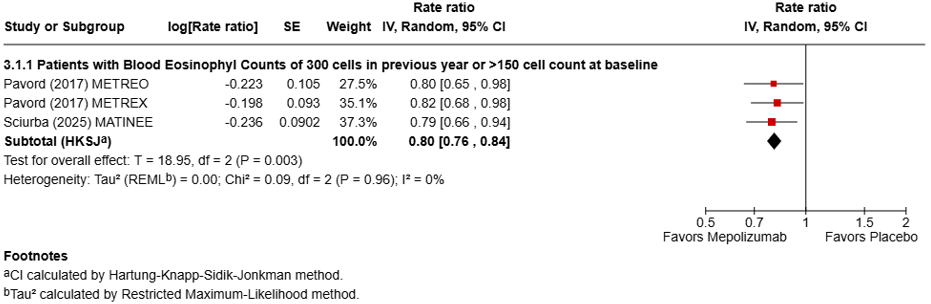
Figure 8: COPD-exacerbations in patients with a high blood Eosinophil count, meta-analysis for mepolizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
Symptoms
Pavord (2017), Flynn (2025) and Sciurba (2025) reported the mean difference of symptoms for patients receiving 100mg or 300mg Mepolizumab versus placebo.
All patients (low and high eosinophil counts)
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg mepolizumab versus placebo. The results are reported in table 17. The mean difference is not clinically relevant.
Table 17: Change in CAT scores in all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Mean change from baseline (SD) |
N |
Mean change from baseline (SD) |
N |
MD (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
||
|
Pavord (2017) METREX |
-1.0 (0.3) |
417 |
-0.4 (0.4) |
419 |
-0.6 (-1.5 to 0.4) |
Patients with high eosinophil counts (≥150 blood count at screening or ≥300 in previous year)
Flynn (2025), Sciurba (2025), Pavord (2017) reported symptoms after 52 weeks in patients high a high eosinophil count receiving 100 and 300mg mepolizumab versus placebo. Results are reported in table 18. In figure 9, a meta-analysis is performed for 100mg Mepolizumab versus placebo.
For mepolizumab 100mg, in patients with a high eosinophil count at baseline (n experimental group 978; n control group 975), the pooled mean difference was -0.47 (95% CI -1.68 to 0.74). This is not clinically relevant different.
For Mepolizumab 300mg, the decrease in CAT-score in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
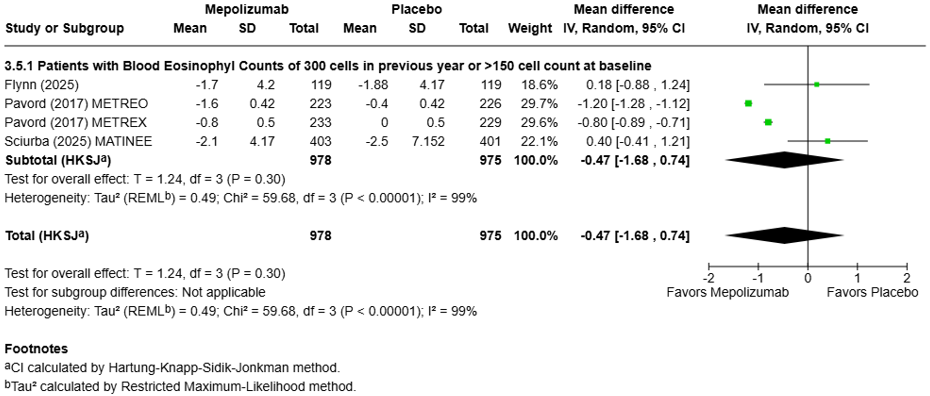
Figure 9: CAT scores in patients with high eosinophil count at baseline and in all patients, meta-analysis for mepolizumab 100mg.
Table 18: Change in CAT scores in patients with a high blood Eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Mean change from baseline (95% CI or SD) |
N |
Mean change from baseline (95% CI or SD) |
N |
MD (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
||
|
Pavord (2017) METREO |
-1.6 (0.42) |
223 |
-0.4 (0.42) |
226 |
-1.1 (-2.3 to 0.0) |
|
Pavord (2017) |
-0.8 (0.5) |
233 |
0.0 (0.5) |
229 |
-0.8 (-2.0 to 0.5) |
|
Flynn (2025) |
-1.7 (-2.45 to -0.94) |
119 |
-1.88 (-2.63) to -1.13) |
119 |
0.19 (-0.88 to 1.25) |
|
Sciurba (2025) |
-2.1 (-2.7 to -1.4) |
403 |
-2.5 (-3.2 to -1.8) |
401 |
-0.2 (-0.05 to 1.4) |
|
|
Mepolizumab 300 mg |
Placebo |
|
||
|
Pavord (2017) METREX |
-0.8 (0.42) |
225 |
-0.4 (0.42) |
226 |
-0.4 (-1.5 to 0.8) |
Quality of life (SGRQ)
Pavord (2017), Flynn (2025) and Sciurba (2025) reported the mean difference of Quality of life for patients receiving 100mg or 300mg Mepolizumab versus placebo.
All patients (low and high eosinophil counts)
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg Mepolizumab versus placebo. The results are reported in table 19. The mean difference was not clinically relevant.
Table 19: Change in SGRQ scores in all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Mean change from baseline (SD) |
N |
Mean change from baseline (SD) |
N |
MD (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
||
|
Pavord (2017) METREX |
-3.2 (0.8) |
417 |
-4.0 (0.8) |
419 |
0.7 (-1.5 to 2.9) |
Patients with high eosinophil counts (≥150 blood count at screening or ≥300 in previous year)
Flynn (2025), Sciurba (2025), the trial METREO and trial METREX (Pavord, 2017) reported mortality after 52 weeks in patients with high eosinophil counts receiving 100 and 300mg mepolizumab versus placebo. Results are reported in table 20. In figure 10, a meta-analysis is performed for 100mg Mepolizumab versus placebo.
For mepolizumab 100mg, based on Flynn (2025), Sciurba (2025), the METREO trial and the METREX trial (Criner, 2019) in patients with a high eosinophil count at baseline, the pooled mean difference was -1.09 (95% CI -3.28 to 1.11) and is not clinically relevant.
For mepolizumab 300mg, based on the METREO trial (Pavord, 2017), the decrease in SGRQ-score in the intervention group was not clinically relevant different compared to the control group in patients with a high eosinophil count at baseline.
Table 20: Change in SGRQ in patients with a high blood eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Mean change from baseline (SD) |
N |
Mean change from baseline (SD) |
N |
MD (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
||
|
Pavord (2017) |
-5.0 (1.0) |
223 |
-3.1 (1.0) |
225 |
-1.8 (-4.5 to 0.8) |
|
Pavord (2017) |
-2.8 (1.1) |
233 |
-3.0 (1.1) |
229 |
0.2 (-2.8 to 3.2) |
|
Flynn (2025) |
-5.74 (-8.04 to -3.43) |
119 |
-6.31 (-8.55 to -4.07) |
119 |
0.57 (-2.63 to 3.78) |
|
Sciurba (2025) |
-8.0 (-9.7 to -6.3) |
403 |
-5.7 (-7.4 to -4.0) |
401 |
-2.3 (-4.6 to 0.1) |
|
|
Mepolizumab 300mg |
Placebo |
|
||
|
Pavord METREO |
-3.3 (1.0) |
225 |
-3.1 (1.0) |
226 |
-0.1 (-2.8 to 2.6) |
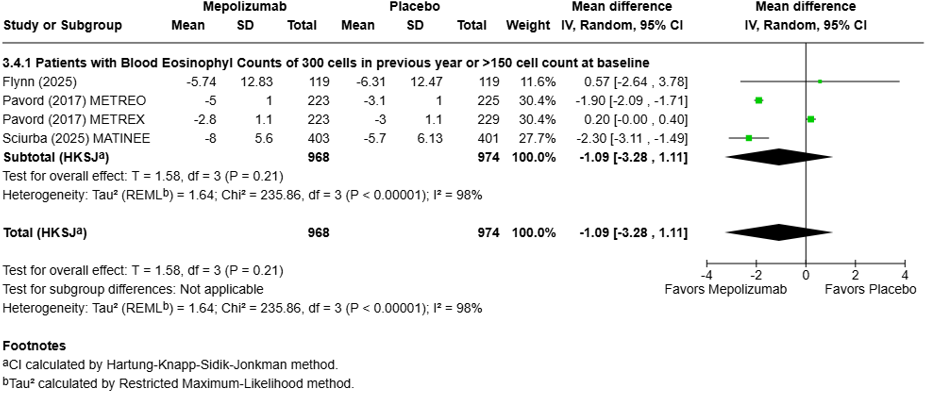
Figure 10: SGRQ scores in patients with high eosinophil count at baseline, meta-analysis for mepolizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
Severe exacerbations
Pavord (2017) and Sciurba (2025) reported the rate difference of severe COPD exacerbations requiring hospital admissions for patients receiving 100mg or 300mg mepolizumab versus placebo.
All patients (low and high eosinophil counts)
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg mepolizumab versus placebo. The results are reported in table 21. The rate difference was not clinically relevant.
Table 21: Severe COPD exacerbations requiring hospital admissions for all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Annual rate (95%CI or SD) |
N |
Annual rate (95%CI or SD) |
N |
Rate Ratio (95%CI) |
Rate difference (95% CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREX |
0.29 |
417 |
0.26 |
419 |
1.10 (0.81 to 1.49)1 |
0.03 (-0.05 to 0.13)2 |
|
1 Based on a negative binomial model with adjustment for smoking status, number of moderate or severe exacerbations in the previous year, baseline disease severity and geographic region. In addition, the natural log of time was included as an offset variable. 2 Calculated from rate ratio and median annual rate in control group of METREX. |
||||||
Patients with high eosinophil counts (≥150 blood count at screening or ≥300 in previous year)
Sciurba (2025) and the trials METREO and METREX (Pavord, 2017) reported on patients with severe COPD exacerbations after 52 weeks receiving 100 and 300mg mepolizumab versus placebo. Results are reported in table 22. In figure 11, a meta-analysis is performed for 100mg Mepolizumab versus placebo.
For mepolizumab 100mg, in patients with a high eosinophil count at baseline (n experimental group 859; n control group 856), the pooled rate ratio was 0.77 (95% CI 0.31 to 1.92). The rate difference was -0.06 (-0.18 to 0.24) and was not clinically relevant.
For mepolizumab 300mg, based on the METREO trial (Pavord, 2017), the rate difference for hospitalization in the mepolizumab group was not clinically relevant in patients with a high eosinophil count at baseline.
Table 22: Severe COPD exacerbations requiring hospital admissions in patients with a high blood eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Annual rate (95%CI or SD) |
N |
Annual rate (95%CI or SD) |
N |
Rate Ratio (95%CI) |
Rate difference (95% CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREO |
0.17 (NR) |
223 |
0.28 (NR) |
226 |
0.59 (0.35 to 0.98)1 |
-0.11 (-0.17 to -0.01)3 |
|
Pavord (2017) |
0.30 (NR) |
233 |
0.26 (NR) |
229 |
1.16 (0.77 to 1.75) 1 |
0.04 (-0.06 tofee 0.20)3 |
|
Sciurba (2025) |
0.13 (0.10 to 0.18) |
403 |
0.20 (0.15 to 0.27) |
401 |
0.65 (0.43 to 0.96)2 |
-0.09 (-0.15 to -0.01)3 |
|
|
Mepolizumab 300 mg |
Placebo |
|
|
||
|
Pavord (2017) METREO |
0.23 (NR) |
225 |
0.28 (NR) |
226 |
0.83 (0.51 to 1.34) 1 |
-0.19 (-0.68 to 0.30)4 |
|
1 Based on a negative binomial model with adjustment for smoking status, number of moderate or severe exacerbations in the previous year, baseline disease severity and geographic region. In addition, the natural log of time was included as an offset variable. 2 Based on a negative binomial model with adjustment for smoking status, number of exacerbations in the previous year, baseline severity of airflow obstruction, and geographic region, with the natural log of time included as offset variable. 3 Calculated from rate ratio and median annual rate in control groups METREO, METREX and Sciurba. 4 Calculated from rate ratio and annual rate in control group METREO. |
||||||
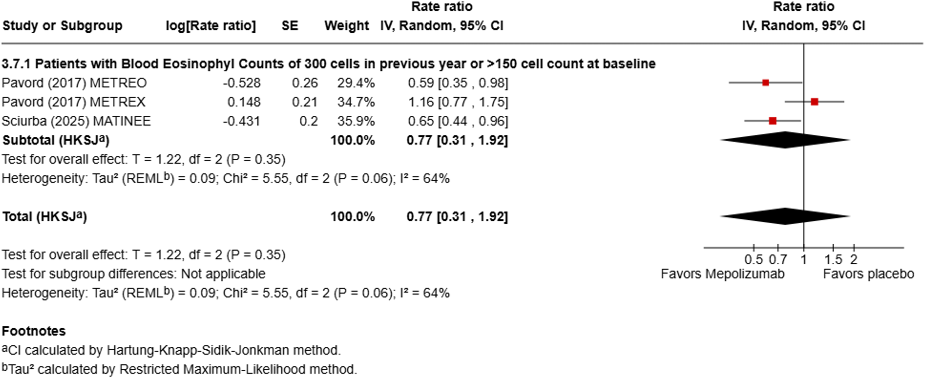
Figure 11: Severe COPD exacerbations in patients with high eosinophil count at baseline and in all patients, meta-analysis for mepolizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm or greater or evidence of 300 per cubic mm or greater in the previous year.
Side effects
Pavord (2017) reported the number of patients reporting adverse events and serious adverse events for patients receiving 100mg or 300mg mepolizumab versus placebo.
All patients (low and high eosinophil counts) – Adverse events
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg Mepolizumab versus placebo. The results are reported in table 23. The risk difference was not clinically relevant.
Table 23: Number of AE for all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Patients with an AE (%) |
N |
Patients with an AE (%) |
N |
Risk Ratio (95% CI) |
Risk difference (95% CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREX |
332 (80) |
417 |
342 (82) |
419 |
0.98 (0.91 to 1.04) |
-0.02 (-0.07 to 0.03)1 |
|
1 Calculated from rate ratio and median annual rate in control group of METREX. |
||||||
Patients with high eosinophil counts- Adverse events - (≥150 blood count at screening or ≥300 in previous year)
Pavord (2017) reported on number of adverse events patients after 52 weeks receiving 100 and 300mg mepolizumab versus placebo. Results are reported in table 24.
For mepolizumab 100mg, in patients with a high eosinophil count at baseline the risk difference was not clinically relevant.
For mepolizumab 300mg, in patients with a high eosinophil count at baseline the risk difference was not clinically relevant.
Table 24: Number of AE in patients with a high blood eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Patients with an AE (%) |
N |
Patients with an AE (%) |
N |
Risk ratio (95% CI) |
Risk difference (95% CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) |
191 (86) |
223 |
185 (82) |
226 |
1.05 (0.96 to 1.14) |
0.04 (-0.03 to 0.12)1 |
|
Pavord (2017) |
190 (82) |
233 |
189 (83) |
229 |
0.99 (0.91 to 1.08) |
-0.01 (-0.07 to 0.07)1 |
|
Sciurba (2025) |
299 (74) |
403 |
307 (77) |
401 |
0.97 (0.90 to 1.05) |
-0.02 (-0.08 to 0.04)1 |
|
|
Mepolizumab 300mg |
Placebo |
|
|
||
|
Pavord METREO |
196 (87) |
225 |
185 (82) |
226 |
1.02 (0.94 to 1.05) |
0.02 (-0.05 to 0.04)1 |
|
1Calculated from rate ratio and median annual rate in control groups METREO, METREX and Sciurba. |
||||||
All patients (low and high eosinophil counts) – Serious adverse events
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg mepolizumab versus placebo. The results are reported in table 25. The rate difference was not considred clinically relevant.
Table 25: Number of SAE for all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Patients with an AE (%) |
N |
Patients with an AE (%) |
N |
Risk Ratio (95% CI) |
Risk difference (95%) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREX |
115 (28) |
417 |
131 (31) |
419 |
0.88 (0.71 to 1.09) |
-0.04 (-0.09 to 0.01)1 |
|
1Calculated from rate ratio and median annual rate in control group of METREX. |
||||||
Patients with high eosinophil counts- Serious adverse events (≥150 blood count at screening or ≥300 in previous year)
The METREO and METREX trial (Pavord, 2017) reported on patients with high eosinophil counts at baseline (for which was stratified during randomization) for 100 mg and 300 mg mepolizumab versus placebo. The results are reported in table 26.
For Mepolizumab 100mg, based on the METREO and METREX trial (Pavord, 2017) in patients with a high eosinophil count at baseline, the risk difference was not clinically relevant.
For Mepolizumab 300mg, based on the METREO trial (Pavord, 2017), the risk difference for patients reporting serious adverse events in the intervention group was not clinically relevant.
Table 26: Number of SAE in patients with a high blood Eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Patients with an AE (%) |
N |
Patients with an AE (%) |
N |
Risk ratio (95% CI) |
Risk difference (95% CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) |
57 (26) |
223 |
68 (30) |
226 |
0.85 (0.63 – 1.15) |
-0.05 (-0.13 to 0.04)1 |
|
Pavord (2017) |
65 (28) |
233 |
80 (35) |
229 |
0.80 (0.61 – 1.05) |
-0.07 (-0.15 to 0.01)1 |
|
|
Mepolizumab 300mg |
Placebo |
|
|
||
|
Pavord METREO |
60 (27) |
225 |
68 (82) |
226 |
0.89 (0.66 to 1.19) |
-0.03 (-0.12 to 0.05)1 |
|
1Calculated from rate ratio and median annual rate in control groups METREO and METREX. |
||||||
Lung function (FEV1)
Sciurba (2025) reported the change in FEV1 in patients receiving 100mg Mepolizumab versus placebo.
All patients (low and high eosinophil counts)
No paper reported on lung function after mepolizumab treatment in all patients (high and low eosinophil counts).
Patients with high eosinophil counts (≥150 blood count at screening or ≥300 in previous year)
Sciurba (2025) reported on lung function after 52 weeks in patients with a high eosinophil count receiving 100 mepolizumab versus placebo. Results are reported in table 27. The mean difference was not clinically relevant.
Figure 27: Lung function in patients with high a blood eosinophil count of >300 cells in previous year or >150 cells at baseline
|
|
Mean change from baseline in ml(95% CI) |
N |
Mean change from baseline in ml(95% CI) |
N |
MD in ml (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
||
|
Sciurba (2025) |
24.6 (-11.5 to 60.7) |
403 |
33.6 ml (-2.5 to 69.7) |
401 |
-9.0 (-60.1 to 42.1) |
Mortality
Flynn (2025), the METREO trial and the METREX trial (Pavord,2017) reported mortality for patients receiving 100mg or 300mg mepolizumab versus placebo.
All patients (low and high counts of eosinophil counts) – Adverse events
The METREX trial (Pavord, 2017) reported on patients with high and low eosinophil counts at baseline (for which was stratified during randomization) for 100 mg mepolizumab versus placebo. The results are reported in table 28. The rate difference was not clinically relevant.
Table 28: Mortality in all patients (high and low eosinophil count). A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year. A low eosinophil phenotype was defined as a blood eosinophil count of 150 cells or less per cubic mm at screening and no evidence of 300 per cubic mm or greater in the previous year.
|
|
Events (%) |
N |
Events (%) |
N |
Risk Ratio (95% CI) |
Rate difference (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) METREX |
16 (4) |
417 |
17(4) |
419 |
0.95 (0.48 to 1.85) |
-0.002 (-0.02 to 0.03)1 |
|
1Calculated from rate ratio and median annual rate in control group of METREX. |
||||||
Patients with high eosinophil counts (≥150 blood count at screening or ≥300 in previous year)
Flynn (2025), METREO (2017) and METREX (2017) reported mortality after 52 weeks in patients with a high eosinophil count receiving 100 and 300mg mepolizumab versus placebo. Results are reported in table 29. In figure 12, a meta-analysis is performed for 100mg Mepolizumab versus placebo.
For mepolizumab 100mg in patients with a high eosinophil count at baseline, the meta-analysis showed that 19 of 543 (3.5%) patients in the experimental group compared to 28 of 543 (4.2%) patients in the control group died. The pooled mortality risk ratio was 0.69 (95%CI 0.39 to 1.22) and the risk difference was -0.01 (95%CI -0.02 to 0.01). This difference was not considred clinically relevant.
For mepolizumab 300 mg in patients with high eosinophil count, mortality in the intervention group was not clinically relevant different compared to the control group.
Table 29: Mortality in patients with a high blood eosinophil count. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
|
|
Events (%) |
N |
Events (%) |
N |
Risk ratio (95% CI) |
Rate difference (95%CI) |
|
|
Mepolizumab 100mg |
Placebo |
|
|
||
|
Pavord (2017) |
4 (2) |
223 |
9 (4) |
226 |
0.45 (0.14 to 1.44) |
-0.02 (-0.03 to 0.018)1 |
|
Pavord (2017) |
6 (3) |
233 |
8 (3) |
229 |
0.74 (0.26 to 2.09) |
-0.01 (-0.03 to 0.04) |
|
Flynn (2025) |
9 (10) |
87 |
11 (12.5) |
88 |
0.83 (0.36 to 1.90) |
-0.006 (-0.03 to 0.04)1 |
|
|
Mepolizumab 300mg |
Placebo |
|
|
||
|
Pavord METREO |
8 (4) |
225 |
9 (4) |
226 |
0.89 (0.35 to 2.27) |
-0.004 (-0.03 to 0.05)1 |
|
1Calculated from rate ratio and median annual rate in control groups METREO, METREX and Flynn. |
||||||
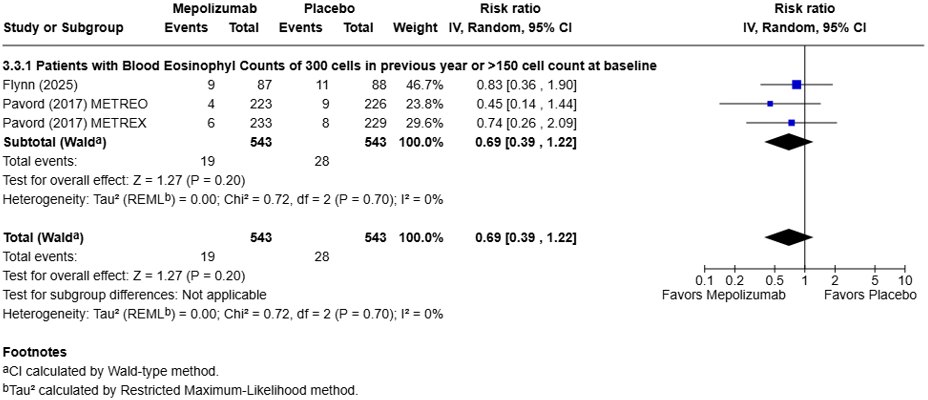
Figure 12: Mortality in patients with high eosinophil count at baseline and in all patients, meta-analysis for mepolizumab 100mg. A high eosinophil phenotype was defined as a blood eosinophil count of 150 per cubic mm at or greater at screening or evidence of 300 per cubic mm or greater in the previous year.
A systematic review of the literature was performed to answer the following question(s):
What is the effect of biologicals in patients with COPD who have frequent exacerbations despite optimized pharmacologic treatment and in a subgroup of patients with eosinophil inflammation and/or elevated fraction of exhaled nitrix oxide.
Table 1. PICO
|
Patients |
|
|
Intervention |
Add-on treatment with monoclonal antibodies IL-5 or IL4/13 (mepolizumab, benralizumab, reslizumab or dupilumab). |
|
Control |
Placebo, usual care (no monoclonal antibodies) |
|
Outcomes |
Crucial: (Severe + Moderate) COPD-exacerbations, Important: Symptoms, Quality of life, |
|
Other selection criteria |
Study design: systematic reviews and randomized controlled trials |
Relevant outcome measures
The guideline panel considered (Severe + moderate) COPD-exacerbations as critical outcome measures for decision making; and symptoms and quality of life, severe exacerbations, side effects, FEV1 and mortality as important outcome measures for decision making.
The guideline panel defined the outcome measures and minimal clinically (patient) important differences as shown in table 2.
Table 2. Minimally clinically important differences per outcome.
|
Outcome |
Definition |
minimal clinically (patient) important difference |
|
COPD-exacerbations
|
Annual rate of moderate or severe exacerbations Exacerbations: episodes characterized by increase in symptoms of shortness of breath, cough, requiring a course of systemic corticoids.
Moderate: without hospital admission
|
Rate Difference ≥ 20% |
|
Symptoms |
COPD symptoms measured with CAT or CCQ |
CAT: Mean Difference > 2 units CCQ: Mean Difference > 0.4 units |
|
Quality of life |
St. George’s Respiratory Questionnaire (SGRQ) (score 0-100, lower is better) |
Mean Difference ≥ 4 units |
|
Severe exacerbations |
Exacerbations: episodes characterized by increase in symptoms of shortness of breath, cough, requiring a course of systemic corticoids.
Severe: with hospital admission.
|
Rate Difference ≥ 20% |
|
Side effects |
Adverse events (definition as used in the studies)
Serious adverse events (definitions as used in the studies) |
Adverse events: Risk Difference ≥ 25%
Serious adverse events: Risk Difference ≥ 10%
|
|
Lung function (FEV1) |
Forced expiratory volume in second (l/sec) |
Mean Difference≥ 100ml/s |
|
Mortality |
Mortality at 12 months |
Risk Difference ≥ 10% |
Search and select (Methods)
A systematic literature search was performed by a medical information specialist using the following bibliographic databases: Embase.com and Ovid/Medline. Both databases were searched from 2000 to the 8th of May 2025 for systematic reviews and RCTs. Systematic searches were completed using a combination of controlled vocabulary/subject headings (e.g., Emtree-terms, MeSH) wherever they were available and natural language keywords. The overall search strategy was derived from two primary search concepts: (1) chronic obstructive lung disease; (2) monoclonal antibody. Duplicates were removed using EndNote software. After deduplication a total of 586 records were imported for title/abstract screening. Initially, 34 studies were selected based on title and abstract screening. After reading the full text, 29 studies were excluded (see the exclusion table under the tab ‘Evidence tabellen’), and five studies were included.
- Bhatt, S. P. and Rabe, K. F. and Hanania, N. A. and Vogelmeier, C. F. and Bafadhel, M. and Christenson, S. A. and Papi, A. and Singh, D. and Laws, E. and Patel, N. and Yancopoulos, G. D. and Akinlade, B. and Maloney, J. and Lu, X. and Bauer, D. and Bansal, A. and Abdulai, R. M. and Robinson, L. B. Dupilumab for COPD with Blood Eosinophil Evidence of Type 2 Inflammation. New England Journal of Medicine. 2024; 390 (24) :2274-2283
- Bhatt, S. P. and Rabe, K. F. and Hanania, N. A. and Vogelmeier, C. F. and Cole, J. and Bafadhel, M. and Christenson, S. A. and Papi, A. and Singh, D. and Laws, E. and Mannent, L. P. and Patel, N. and Staudinger, H. W. and Yancopoulos, G. D. and Mortensen, E. R. and Akinlade, B. and Maloney, J. and Lu, X. and Bauer, D. and Bansal, A. and Robinson, L. B. and Abdulai, R. M. Dupilumab for COPD with Type 2 Inflammation Indicated by Eosinophil Counts. New England Journal of Medicine. 2023; 389 (3) :205-214
- Donovan T, Milan SJ, Wang R, Banchoff E, Bradley P, Crossingham I. Anti-IL-5 therapies for chronic obstructive pulmonary disease. Cochrane Database Syst Rev. 2020 Dec 8;12(12):CD013432. doi: 10.1002/14651858.CD013432.pub2. PMID: 33295032; PMCID: PMC8106745.
- Flynn, Cara A. and McAuley, Hamish J. C. and Elneima, Omer and Aung, Hnin W. W. and Ibrahim, Wadah and Ward, Thomas J. C. and Bourne, Michelle and Thornton, Tracey D. and Mistry, Vijay and Gilbert, Hannah R. and Waheed, Ghazala and Wright, Adam K. A. and Evans, Rachel A. and Steiner, Michael C. and Brookes, Cassandra L. and Brightling, Christopher E. and Greening, Neil J. Mepolizumab for COPD with Eosinophilic Phenotype following Hospitalization. NEJM evidence. 2025; :EVIDoa2500012
- Sciurba, Frank C. and Criner, Gerard J. and Christenson, Stephanie A. and Martinez, Fernando J. and Papi, Alberto and Roche, Nicolas and Bourbeau, Jean and Korn, Stephanie and Bafadhel, Mona and Han, MeiLan K. and Kolterer, Stefanie and Miller, Karen and Mouneimne, Dalal and Fletcher, Joanne and Mayer, Bhabita and Min, Jeff and Pavord, Ian D. Mepolizumab to Prevent Exacerbations of COPD with an Eosinophilic Phenotype. The New England journal of medicine. 2025; 392 (17) :1710-1720
Table 3. Characteristics of included studies
|
Study |
Participants |
Comparison |
Follow-up |
Outcome measures |
Comments |
Risk of bias (per outcome measure)* |
|
|
Included in systematic review Donovan (2020) |
|||||||
|
Brightling (2014) |
N at baseline I: 51 C: 50
Age (mean, SD) I: 62.9 (8.2) C: 64.6 (7.5)
Sex (n, % females) I: 16 (31.4%) C: 21 (42%)
Blood eosinophil (mean, SD)
Exacerbations in previous 12 months (mean, SD) |
Intervention:
Control: Placebo matched to benralizumab (MEDI-563)
In both intervention and control arms of the study: injection subcutaneously every 4 weeks for the first 3 doses and then every 8 weeks for the next 5 doses (Day 1, 29, 57, 113, 169, 225, 281, and 337). |
56 weeks |
COPD exacerbations
Quality of Life
Severe exacerbations
Side effects Lung function (FEV1) |
Inclusion criteria:
Principal Investigator: Rene van der Merwe, MBChB: MedImmune LLC
Sponsor: MedImmune LLC.
Collaborator: AstraZeneca |
Low |
|
|
Criner (2019) GALATHEA |
N at baseline I a: 554 I b: 552 C: 550
Age (mean, SD) I a: 65.9 (7.77) I b: 65.3 (8.05) C: 65.2 (8.22)
Sex (n, % females) I a: 172 (31.0%) I b: 180 (32.6%) C: 175 (31.8%)
Blood eosinophil (mean cells/mm3, SD) I b: 458.5 (276.6) C: 449.8 (283.4)
Exacerbations in previous 12 months (mean, SD) I b: 2.33 (1.15) C: 2.35 (1.42)
|
Intervention a: benralizumab 30mg
Intervention b: benralizumab 100mg
Control: Placebo
Overall: Each participant received 30 mg or 100 mg benralizumab or placebo subcutaneously on study week 0 until study week 48 inclusive. Participants were randomised to receive benralizumab 30 mg or 100 mg or placebo by SC injection every 8 weeks throughout the 56-week study. |
56 weeks |
COPD exasperations Quality of Life
Side effects
Lung function (FEV1)
|
Inclusion criteria:
Patients were enrolled 2:1 based on blood eosinophil count (≥220 cells per μL vs <220 cells per μL) and were allocated 1:1:1 to receive benralizumab or matching placebo solution.
Sponsor: AstraZeneca. |
Low |
|
|
Criner (2019)
|
N at baseline I a: 562 I b: 562 I c: 562 C: 568
Age (mean, SD) I a: 64.7 (8.47) I b: 65.6 (8.61) I c: 65.0 (8.23) C: 65.3 (8.44)
Sex (n, % females) I a: 196 (34.9%) I b: 194 (34.5%) I c: 207 (36.8%) C: 209 (36.8%)
Blood eosinophil s (mean cells/mm3, SD) I b: 503.2 (388.6) C: 492.9 (359.6)
Exacerbations in previous 12 months (mean, SD) I b: 2.22 (0.98) C: 2.34 (1.04)
|
Intervention a: benralizumab 10mg
Intervention b: benralizumab 30mg
Intervention c: benralizumab 100mg
Control: Placebo
Overall: week 0 until study week 48 inclusive. Participants were randomized to receive benralizumab 10 mg, benralizumab 30 mg, benralizumab 100 mg, or placebo by SC injection every 8 weeks throughout the 56-week study.
|
56 weeks |
COPD exacerbations
Quality of Life
Side effects
Lung function (FEV1) |
Inclusion criteria:
Patients were enrolled 2:1 based on blood eosinophil count (≥220 cells per μL vs <220 cells per μL) and were allocated 1:1:1:1 to receive benralizumab or matching placebo solution.
Sponsor: AstraZeneca. |
Low |
|
|
Pavord (2017) |
N at baseline I a: 225 I b: 223 C: 226
Age (mean, SD) I a: 64.8 (8.96) I b: 64.8 (9.06) C: 65.8 (8.64)
Sex (n, % females) I a: 67 (29.8%) I b: 91 (40.8%) C : 70 (31%)
Blood eosinophil count ≥150/mm3 at screening (no, %) I a: 179 (80) I b: 182 (82) C: 184 (81)
Blood eosinophil count ≥300/mm3 in 12 months before screening (no, %) I b: 101 (45) C: 108 (48)
Moderate to severe exacerbations in previous 12 months (mean, SD) I b: 2.7 (1.4) C: 2.6 (1.4)
|
Intervention a: Mepolizumab 300mg
Intervention b: Mepolizumab 100mg
Control: Placebo
Each participant received 100 mg or 300 mg mepolizumab SC injection or placebo every 4 weeks (13 administrations during 52-week treatment period) along with their baseline standard of care COPD medication. Placebo: sterile 0.9% sodium chloride solution Salbutamol MDI was issued for use as rescue medication throughout the study. |
52 weeks |
COPD exacerbations
Symptoms
Quality of Life
Severe exacerbations
Side effects
Mortality
|
Inclusion criteria:
Sponsor: GlaxoSmithKline |
Low |
|
|
Pavord (2017) |
N at baseline I a: 223 I b: 184 C a: 230 C b: 190
Age (mean, SD) I a: 65.2 (8.36) I b: 66.1 (9.14) C a: 65.3 (8.53) C b: 65.2 (8.62)
Sex (n, % females) I a: 84 (36.1) I b: 76 (41.3) C a: 79 (34.5) C b: 77 (40.5)
Blood eosinophil count ≥150/mm3 at screening (no, %) I a: 220 (94) I b: 220 (53) C a: 228 (>99)
Blood eosinophil count ≥300/mm3 in 12 months before screening (no, %) I b: 38 (17) C a: 44 (11)
No. of moderate to severe exacerbations in previous 12 months (mean, SD) I b: 2.5 (1.2) C a: 2.5 (1.1) C b: 2.5 (1.2)
|
Intervention a: Mepolizumab 100mg – subgroup eosinophilic phenotype
Intervention b: Mepolizumab 100mg – subgroup non eosinophilic phenotype
Control a: Placebo – subgroup eosinophilic phenotype
Control b: Placebo – subgroup non eosinophilic phenotype
Mepolizumab 100 mg versus placebo. Each participant received 100 mg mepolizumab SC injection or placebo every 4 weeks (13 administrations during 52-week treatment period) along with optimized standard of care background therapy. Placebo: sterile 0.9% sodium chloride solution Salbutamol MDI was issued for use as rescue medication throughout the study.
|
52 weeks |
COPD exasperations Symptoms
Quality of Life
Severe exacerbations
Side effects
Mortality
|
Inclusion criteria:
Sponsor: GlaxoSmithKline |
Low |
|
|
Individual studies |
|||||||
|
Study |
Participants |
Intervention: |
Follow-up |
Outcome measures
|
Inclusion criteria/comments |
Risk of bias (per outcome measure)* |
|
|
Bhatt (2023) BOREAS |
N at baseline I: 468 C: 471
Age (mean, SD) I: 65.0 (8.0) C: 65.2 (8.1)
Sex (n, % males) I: 298 (63,7) C: 322 (68,4)
Blood eosinophil count µL (mean, SD) C: 2.3 (1.0) |
Intervention:
Control: Matching placebo once every two weeks
|
52 weeks |
COPD exacerbations
Side effects |
Inclusion criteria:
Sponsor: Sanofi and Regeneron Pharmaceuticals.
|
Low |
|
|
Bhatt (2024) |
N at baseline I: 470 C: 465
Age (mean, SD) I: 65.2 (8.1) C: 64.9 (8.5)
Sex (n, % males) I: 320 (68.1) C: 312 (67.1)
Blood eosinophil count µL (mean, SD) C: 2.1 (0.7) |
Intervention: Dupilumab 300 mg every 2 weeks
Control: Matching placebo once every 2 weeks
|
52-week |
COPD exacerbations
QoL
Lung function (FEV1) |
Inclusion criteria:
Sponsor: Sanofi and Regeneron Pharmaceuticals.
|
Low |
|
|
Flynn (2025) |
N at baseline I: 119 C: 119
Age (mean, SD) I: 69.5 (8.9) C: 68.7 (9.1)
Sex (n, % females) I: 61 (51.3%) C: 60 (50,4%)
Highest eosinophil count in previous 12 months
No. of moderate or severe COPD exacerbations in previous yr (mean, SD) |
Intervention Mepolizumab: 100mg once every four weeks
Control: Matching placebo once every four weeks
|
48 weeks
|
Symptoms (CAT)
QoL
Severe exacerbations
Mortality
|
Inclusion criteria:
Funding: GSK Sponsor van de trial: University of Leicester |
Low |
|
|
Sciurba (2025) |
N at baseline I: 403 C: 401
Age (mean, SD) I: 66.4 (8.1) Control: 66.0 (7.9)
Sex (n, % females) I: 127 (32%) C: 126 (31%)
Highest eosinophil count in previous 12 months, log SD
No. of moderate or severe COPD exacerbations within previous 12 m(mean, SD) |
Intervention Mepolizumab: 100mg once every four weeks
Control: Matching placebo once every four weeks
|
52 to 104 weeks |
COPD exacerbations
Symptoms (CAT)
QoL
Severe exacerbations
Lung function (FEV1) |
Inclusion criteria:
Sponsor: GSK |
Low |
|
|
*For further details, see risk of bias table in the appendix
|
|||||||
|
Study reference |
Was the allocation sequence adequately generated?
|
Was the allocation adequately concealed?
|
Blinding: Was knowledge of the allocated interventions adequately prevented?
Were patients blinded?
Were healthcare providers blinded?
Were data collectors blinded?
Were outcome assessors blinded?
Were data analysts blinded? |
Was loss to follow-up (missing outcome data) infrequent?
|
Are reports of the study free of selective outcome reporting? |
Was the study apparently free of other problems that could put it at a risk of bias?
|
Overall risk of bias If applicable/necessary, per outcome measure
LOW Some concerns HIGH
|
|
Bhatt (2023) |
Definitely yes
Reason: |
Definitely yes
|
Definitely yes
Reason: will remain blinded to study treatment” |
Definitely yes the dupilumab group and 93.4% of those in the placebo group completed the 52-week trial period.” |
Definitely yes |
Probably no
|
Low
|
|
Brightling (2014) |
Definitely yes;
Reason: “Participants were randomly assigned (1:1), via computer-generated permuted block randomisation (block size of 4) with a central telephone and web-based system, to receive 100 mg benralizumab or matched placebo, subcutaneously” |
Definitely yes;
Reason: “All other study site personnel, participants, and sponsors, including data analysts, were masked to treatment allocation”. |
Definitely yes;
Reason: “Participants and personnel were blinded (clearly stated in clinicaltrials. gov/ct2/show/nct01227278).” |
Definitely yes;
Reason: “Incomplete outcome data were comprehensively reported.” |
Definitely yes;
Reason: “No apparent indication of selective outcome reporting.” |
Probably no
Reason: Sponsored by MedImmune LLC with collaboration from AstraZeneca, but published outcome not clearly in favor of sponsor |
Low
|
|
Criner (2019)
|
Unclear
Reason: |
Unclear
Reason; “Unable to find confirmation on this point in the trial reports.” |
Definitely yes
Reason: NCT02138916.” |
Definitely yes
Reason: “As detailed in clinicaltrials.gov/ct2/show/NCT02138916.” |
Definitely yes
Reason: |
Probably no
Reason: Sponsored by AstraZeneca with collaboration from MedImmune LLC, but published outcome not clearly in favor of sponsor |
Low |
|
Criner (2019)
|
Unclear
Reason: |
Unclear
Reason; “Unable to find confirmation on this point in the trial reports.” |
Definitely yes
Reason: NCT02155660)..” |
Definitely yes
Reason: “As indicated in clinical trial information (clinicaltrials.gov/ct2/show/ NCT02155660)..” |
Definitely yes
Reason: |
Probably no
Reason: Sponsored by AstraZeneca with collaboration from MedImmune LLC, but published outcome not clearly in favor of sponsor |
Low |
|
Pavord (2017) RoB assessment according to Donovan (2020))
|
Definitely yes
Reason: ”Randomisation was performed using a centralised, computer-generated, permuted- block design with fixed block size of 6; separate schedules were generated for each country.” |
Probably yes
Reason: It is highly likely that the allocation concealment was adequate, but no details provided in the trial report. |
Definitely yes
Reason: Participant, investigator, and outcomes assessor were masked (confirmed in clinicaltrials.gov/ct2/show/results/NCT02105961). |
Definitely yes
Reason: “Missing data sensitivity analyses conducted indicating robustness of primary efficacy results”. |
Definitely yes
Reason: |
Probably no
Reason: Sponsored by GSK, but published outcome not clearly in favor of sponsor |
Low |
|
Pavord (2017) RoB assessment according to Donovan (2020))
|
Definitely yes
Reason: ”Randomization was performed using a centralised, computer-generated, permuted- block design with fixed block size of 6; separate schedules were generated for each country.” |
Probably yes
Reason: It is highly likely that the allocation concealment was adequate, but no details provided in the trial report. |
Definitely yes
Reason: Participant, investigator, outcomes assessor masked (confirmed in clinicaltrials. gov/ct2/show/results/NCT02105948). |
Definitely yes
Reason: “Missing data sensitivity analyses conducted indicating robustness of primary efficacy results”. |
Definitely yes
Reason: |
Probably no
Reason: Sponsored by GSK, but published outcome not clearly in favor of sponsor |
Low |
|
Bhatt (2024) |
Probably yes
Unclear how randomization was performed. |
Probably yes
“Oversight of the trial was provided by an external independent data and safety monitoring committee, the members of which were unaware of group assignments.” |
Probably yes
“Oversight of the trial was provided by an external independent data and safety monitoring committee, the members of which were unaware of group assignments.”
The experiment was double-blinded
|
Probably yes
Sensitivity data analysis has been performed and the data remained consistent.
“Missing data handling: Intercurrent event(s) handling strategy and missing data handling were as follows: • Primary endpoint: for discontinuation of the study intervention before week 52, offstudy treatment data up to week 52 were included in the analysis.”
“Continuous secondary endpoints (change from baseline at week 12 or 52 for FEV1, SGRQ and E-RS): for discontinuation of the study intervention prior to week 12 or week 52, all data collected after discontinuation were used in the analysis.” |
Definitely yes
Study includes all outcomes |
Probably no
|
Low |
|
Flynn (2025) |
Definitely yes
“A web based randomisation system from a third party (Sealed Envelope Ltd.). Participants will be randomised in a 1:1 ratio to mepolizumab or placebo.” |
Definitely yes
“A web based randomisation system from a third party (Sealed Envelope Ltd.) was used to allocate the patients treatment. “ |
Definitely yes
“Participants, investigators, and all involved in trial conduct, sample analysis, or with any other interest in this trial will remain blind to the randomised treatment assignments until after final analysis is complete. The exception(s) to this are as follows; • The trial statistician will have access to the web based randomisation database of all randomised participants in order to prepare the unblinded DMC to make safety decisions and complete end of trial analyses. • The Pharmacy team will be unblinded and have responsibility for storing and dispensing IMP and placebo. • Unblinded trial personnel from the Respiratory BRC will have responsibility for reconstituting the IMP/placebo and dosing the participants” |
Probably yes
The Sensitivity Analysis of the data indicated that imputing missing data did not alter the interpretation. |
Definitely yes
Reason: study design and outcome measures reported are the same. |
Probably yes
Reason: |
Low |
|
Sciurbia (2025) |
Definitely yes
“All patients were centrally randomized using an Interactive Web Response System (IWRS)”
“The randomization schedule was generated by PPD (ThermoFisher Scientific, USA) using validated randomization SAS Software Version 9.4 (Proc Plan) and a fixed block size of 4. Randomization was performed using interactive response technology.” |
Definitely yes
“All patients were centrally randomized using an Interactive Web Response System (IWRS)” |
Probably yes
“The randomization team shuffled the schedules by randomly numbering treatment and kit (i.e., no sequential ordering or grouping of treatment and kit) to maintain the blinding.”
“Placebo injection were matched to mepolizumab in appearance and administration schedule to maintain blinding.”
|
Definitely yes
“Missing data sensitivity analyses conducted indicating robustness of primary efficacy results” |
Definitely yes
“No apparent indication of selective outcome reporting” |
Probably no
Sponsored by GSK with PPD as operational partner, but published outcome not clearly in favor of sponsor |
Low |
Table of excluded studies
|
Reference |
Reason for exclusion |
|
A Randomized, Double-blind, Placebo-controlled, Parallel-group, 52-week Pivotal Study to Assess the Efficacy, Safety, and Tolerability of Dupilumab in Patients With Moderate-to-severe Chronic Obstructive Pulmonary Disease (COPD) With Type 2 Inflammation
|
A protocol, not a peer reviewed paper |
|
Bhatt, S. P. and Rabe, K. F. and Hanania, N. A. and Vogelmeier, C. F. and Bafadhel, M. and Christenson, S. A. and Papi, A. and Singh, D. and Laws, E. and Dakin, P. and Maloney, J. and Lu, X. and Bauer, D. and Bansal, A. and Abdulai, R. M. and Robinson, L. B. Dupilumab for chronic obstructive pulmonary disease with type 2 inflammation: a pooled analysis of two phase 3, randomised, double-blind, placebo-controlled trials. The Lancet Respiratory Medicine. 2025; 13 (3) :234-243
|
Post-hoc subgroep analyses |
|
Bhatt, S. P. and Rabe, K. F. and Hanania, N. A. and Vogelmeier, C. F. and Bafadhel, M. and Christenson, S. A. and Papi, A. and Singh, D. and Laws, E. and Dakin, P. and Maloney, J. and Lu, X. and Bauer, D. and Bansal, A. and Robinson, L. B. and Abdulai, R. M. Dupilumab reduces exacerbations and improves lung function in patients with chronic obstructive pulmonary disease and emphysema: Phase 3 randomized trial (BOREAS). Respiratory Medicine. 2025; 236 :107846
|
Post-hoc subgroep analyses |
|
Bhatt SP, Rabe KF, Hanania NA, Vogelmeier CF, Bafadhel M, Christenson SA, Papi A, Singh D, Laws E, Dakin P, Maloney J, Lu X, Bauer D, Bansal A, Abdulai RM, Robinson LB. Effect of Dupilumab on Health-Related Quality of Life and Respiratory Symptoms in Patients With COPD and Type 2 Inflammation: BOREAS and NOTUS. Chest. 2025 Jul;168(1):56-66. doi: 10.1016/j.chest.2025.01.029. Epub 2025 Jan 31. PMID: 39894389. |
Does not address the correct outcome. |
|
Brightling, C. E. and Bleecker, E. R. and Panettieri Jr, R. A. and Bafadhel, M. and She, D. and Ward, C. K. and Xu, X. and Birrell, C. and van der Merwe, R. Benralizumab for chronic obstructive pulmonary disease and sputum eosinophilia: a randomised, double-blind, placebo-controlled, phase 2a study. The Lancet Respiratory Medicine. 2014; :891-901
|
Is included in Donovan SR |
|
Criner, Gerard J. and Celli, Bartolome R. and Brightling, Christopher E. and Agusti, Alvar and Papi, Alberto and Singh, Dave and Sin, Don D. and Vogelmeier, Claus F. and Sciurba, Frank C. and Bafadhel, Mona and Backer, Vibeke and Kato, Motokazu and Ramirez-Venegas, Alejandra and Wei, Yu-Feng and Bjermer, Leif and Shih, Vivian H. and Jison, Maria and O'Quinn, Sean and Makulova, Natalya and Newbold, Paul and Goldman, Mitchell and Martin, Ubaldo J. Benralizumab for the Prevention of COPD Exacerbations. The New England journal of medicine. 2019; 381 (11) :1023-1034
|
Is included in Donovan SR |
|
Criner, Gerard J. and Celli, Bartolome R. and Singh, Dave and Agusti, Alvar and Papi, Alberto and Jison, Maria and Makulova, Natalya and Shih, Vivian H. and Brooks, Laura and Barker, Peter and Martin, Ubaldo J. and Newbold, Paul Predicting response to benralizumab in chronic obstructive pulmonary disease: analyses of GALATHEA and TERRANOVA studies. The Lancet. Respiratory medicine. 2020; 8 (2) :158-170
|
Post-hoc subgroep analyses |
|
Dekhuijzen, P. N. R. and Levy, M. L. and Corrigan, C. J. and Hadfield, R. M. and Roche, N. and Usmani, O. S. and Barnes, P. J. and Scullion, J. E. and Lavorini, F. and Corbetta, L. and Kocks, J. W. H. and Cosio, B. G. and Buhl, R. and Pedersen, S. E. Is Inhaler Technique Adequately Assessed and Reported in Clinical Trials of Asthma and Chronic Obstructive Pulmonary Disease Therapy? A Systematic Review and Suggested Best Practice Checklist. Journal of Allergy and Clinical Immunology: In Practice. 2022; 10 (7) :1813-1824.e1
|
No relevant papers included |
|
Freund O, Wand O, Kutzkel S, Tiran B, Pumin I, Friedman Regev I, Levy L, Bar-Shai A. Real-World and Patient-Reported Outcomes of Dupilumab and Other Biological Drugs for Chronic Obstructive Pulmonary Disease-A Systematic Review. Diagnostics (Basel). 2024 Oct 26;14(21):2390. doi: 10.3390/diagnostics14212390. PMID: 39518358; PMCID: PMC11545442. |
Systematic review - Cochrane review available including relevant studies for benralizumab and mepolizumab. Not enough individual study results reported to be able to update the meta-analysis for dupilimab. Bhat 2023 and 2024 included infividually |
|
Haldar K, Mistry V, Richardson M, Hamblet C, Jison M, Barer MR, McCrae C, Brightling CE. Effect of benralizumab treatment on the airway microbiome in COPD. ERJ Open Res. 2025 Apr 7;11(2):00802-2024. doi: 10.1183/23120541.00802-2024. PMID: 40196715; PMCID: PMC11973710. |
Post-hoc analysis |
|
Hu, Khai-Chi and Chuang, Min-Hsiang and Lai, Chih-Cheng and Liao, Kuang-Ming Meta-Analysis of Randomized, Controlled Trials Assessing the Effectiveness and Safety of Biological Treatments in Chronic Obstructive Pulmonary Disease Patients. Clinical therapeutics. 2025; 47 (3) :226-234
|
Systematic review - Cochrane review available including relevant studies for benralizumab and mepolizumab; Bhatt 2023 included individually. |
|
Jaroenpuntaruk, V. and Pongdee, T. A Phase 3 Trial of Dupilumab for People With Chronic Obstructive Pulmonary Disease and Elevated Peripheral Blood Eosinophil Counts. Journal of Allergy and Clinical Immunology: In Practice. 2024; 12 (5) :1394-1396
|
Description of Bhatt 2023
|
|
Lan, Shao-Huan and Lai, Chih-Cheng and Chang, Shen-Peng and Hsu, Chun-Chun and Chen, Cheng-Hsin and Wang, Ya-Hui and Huang, Yueh Lan and Wang, Cheng-Yi and Lin, You-Shuei Efficacy and safety of anti-interleukin-5 therapy in patients with chronic obstructive pulmonary disease: A meta-analysis of randomized, controlled trials. Journal of microbiology, immunology, and infection = Wei mian yu gan ran za zhi. 2022; 55 (1) :26-35
|
Systematic review - Cochrane review available including relevant studies
|
|
Long, G. and Wall, J. Precision medicine in COPD: Review of mepolizumab for eosinophilic COPD. Breathe. 2018; 14 (4) :338-341
|
Comment on pavord 2017
|
|
Maltais, F. and Dennis, N. and Chan, C. K. N. Rationale for earlier treatment in COPD: A systematic review of published literature in mild-to-moderate COPD. COPD: Journal of Chronic Obstructive Pulmonary Disease. 2013; 10 (1) :79-103
|
No relevant papers included
|
|
Mohamed, M. M. G. and Kamel, G. and Charbek, E. Role of Monoclonal Antibodies in the Management of Eosinophilic COPD: A Meta-analysis of Randomized Controlled Trials. Annals of the American Thoracic Society. 2024; :768-775
|
Systematic review - Cochrane review available including relevant studies for benralizumab and mepolizumab. Bhat 2023 and 2024 included individually
|
|
Ohnishi, Hiroshi and Eitoku, Masamitsu and Yokoyama, Akihito A systematic review and integrated analysis of biologics that target Type 2 inflammation to treat COPD with increased peripheral blood eosinophils. Heliyon. 2022; 8 (6) :e09736 Pavord, I. D. and Chapman, K. R. and Bafadhel, M. and Sciurba, F. C. and Bradford, E. S. and Harris, S. S. and Mayer, B. and Rubin, D. B. and Yancey, S. W. and Paggiaro, P. Mepolizumab for eosinophil-associated copd: Analysis of metrex and metreo. International Journal of COPD. 2021; 16 :1755-1770
|
Systematic review - Cochrane review available including relevant studies
|
|
Pavord, I. D. and Chapman, K. R. and Bafadhel, M. and Sciurba, F. C. and Bradford, E. S. and Harris, S. S. and Mayer, B. and Rubin, D. B. and Yancey, S. W. and Paggiaro, P. Mepolizumab for eosinophil-associated copd: Analysis of metrex and metreo. International Journal of COPD. 2021; 16 :1755-1770
|
Systematic review - Cochrane review available including relevant studies
|
|
Pavord, Ian D. and Chanez, Pascal and Criner, Gerard J. and Kerstjens, Huib A. M. and Korn, Stephanie and Lugogo, Njira and Martinot, Jean-Benoit and Sagara, Hironori and Albers, Frank C. and Bradford, Eric S. and Harris, Stephanie S. and Mayer, Bhabita and Rubin, David B. and Yancey, Steven W. and Sciurba, Frank C. Mepolizumab for Eosinophilic Chronic Obstructive Pulmonary Disease. The New England journal of medicine. 2017; 377 (17) :1613-1629
|
In Donovan SR |
|
Pitre, T. and Lupas, D. and Mah, J. and Stanbrook, M. and Blazer, A. and Zeraatkar, D. and Ho, T. Biologic Therapies for Chronic Obstructive Pulmonary Disease: A Systematic Review and Network Meta-Analysis of Randomized Controlled Trials. COPD: Journal of Chronic Obstructive Pulmonary Disease. 2025; 22 (1) :2449889
|
Systematic review - Cochrane review available including relevant studies for benralizumab and mepolizumab. Not enough individual study results reported to be able to update the meta-analysis for dupilimab. Bhat 2023 and 2024 included infividually
|
|
Ramakrishnan, S. and Russell, R. E. K. and Mahmood, H. R. and Krassowska, K. and Melhorn, J. and Mwasuku, C. and Pavord, I. D. and Bermejo-Sanchez, L. and Howell, I. and Mahdi, M. and Peterson, S. and Bengtsson, T. and Bafadhel, M. Treating eosinophilic exacerbations of asthma and COPD with benralizumab (ABRA): a double-blind, double-dummy, active placebo-controlled randomised trial. The Lancet Respiratory Medicine. 2025; 13 (1) :59-68
|
Very large percentage of patients with asthma instead of COPD included.
|
|
Rogliani, P. and Matera, M. G. and Puxeddu, E. and Mantero, M. and Blasi, F. and Cazzola, M. and Calzetta, L. Emerging biological therapies for treating chronic obstructive pulmonary disease: A pairwise and network meta-analysis. Pulmonary Pharmacology and Therapeutics. 2018; 50 :28-37
|
Systematic review - Cochrane review available including relevant studies
|
|
Sciurba FC, Criner GJ, Christenson SA, Martinez FJ, Papi A, Roche N, Bourbeau J, Korn S, Bafadhel M, Han MK, Kolterer S, Miller K, Mouneimne D, Fletcher J, Mayer B, Min J, Pavord ID; MATINEE StudyA Multi-center, Randomized, Double-blind, Parallel-group, Placebo-controlled Study of Mepolizumab 100 mg SC as add-on Treatment in Participants With COPD Experiencing Frequent Exacerbations and Characterized by Eosinophil Levels (Study 208657) |
Not a peer reviewed article |
|
Singh, Dave and Criner, Gerard J. and Agusti, Alvar and Bafadhel, Mona and Soderstrom, Johan and Luporini Saraiva, Gabriela and Song, Yue and Licaj, Idlir and Jison, Maria and Martin, Ubaldo J. and Psallidas, Ioannis Benralizumab Prevents Recurrent Exacerbations in Patients with Chronic Obstructive Pulmonary Disease: A Post Hoc Analysis. International journal of chronic obstructive pulmonary disease. 2023; 18 :1595-1599
|
Post-hoc subgroup analyses |
|
Vogelmeier, C. F. and Rabe, K. F. and Bhatt, S. P. and Hanania, N. A. and Bafadhel, M. and Christenson, S. A. and Papi, A. and Singh, D. and Laws, E. and Maloney, J. and Dakin, P. and Lu, X. and Bauer, D. and Bansal, A. and Robinson, L. B. and Abdulai, R. M. Dupilumab reduces acute exacerbations and improves lung function in patients with COPD with type 2 inflammation irrespective of body mass index, airflow obstruction, dyspnea, and exercise capacity index scores. Respiratory Medicine. 2025; 241 :108015
|
Post-hoc subgroup analyses
|
|
Wang Y, Luo J, Huang R, Xiao Y. Factors Influencing the Efficacy and Safety of Monoclonal Antibody Biologics in Chronic Obstructive Pulmonary Disease: A Meta-analysis of Randomized Controlled Trials. Lung. 2025 Mar 14;203(1):46. doi: 10.1007/s00408-025-00795-6. PMID: 40407934. |
Systematic review - Cochrane review available including relevant studies for benralizumab and mepolizumab. Not enough individual study results reported to be able to update the meta-analysis for dupilimab. Bhat 2023 and 2024 included infividually. |
|
Wu, Y. and Huang, M. and Zhong, J. and Lu, Y. and Gan, K. and Yang, R. and Liu, Y. and Li, J. and Chen, J. The clinical efficacy of type 2 monoclonal antibodies in eosinophil-associated chronic airway diseases: a meta-analysis. Frontiers in Immunology. 2023; 14 :1089710
|
Systematic review - Cochrane review available including relevant studies
|
|
Xiong, Yu and Hu, Jia-Qiang and Tang, Hui-Lin and Zhao, Zhi-Xia and Liu, Li-Hong Network meta-analysis of the efficacy and safety of monoclonal antibodies and traditional conventional dichotomous agents for chronic obstructive pulmonary disease. Frontiers in medicine. 2024; 11 :1334442
|
Systematic review - Cochrane review available including relevant studies for benralizumab and mepolizumab; Bhatt 2023 included individually
|
|
Zhang, C. and Wang, Y. and Zhang, M. and Su, X. and Lei, T. and Yu, H. and Liu, J. Monoclonal Antibodies Targeting IL-5 or IL-5Rα in Eosinophilic Chronic Obstructive Pulmonary Disease: A Systematic Review and Meta-Analysis. Frontiers in Pharmacology. 2021; 12 :754268
|
Systematic review - Cochrane review available including relevant studies.
|
Beoordelingsdatum en geldigheid
Publicatiedatum : 01-10-2026
Beoordeeld op geldigheid : 01-10-2026
Samenstelling werkgroep
Voor het ontwikkelen van de richtlijnmodule is in 2024 een multidisciplinair cluster ingesteld. Het cluster Astma & COPD bestaat uit meerdere richtlijnen (zie hier de actuele clusterindeling). De stuurgroep bewaakt het proces van modulair onderhoud binnen het cluster. De expertisegroepsleden brengen hun expertise in, indien nodig. De volgende personen uit het cluster zijn betrokken geweest bij de herziening van deze module:
Clusterstuurgroepleden
- Dhr. dr. F. (Folkert) Brijker, voorzitter cluster Astma & COPD, longarts, Spaarne Gasthuis te Haarlem, NVALT
- Dhr. dr. G.J. (Gert-Jan) Braunstahl, vicevoorzitter cluster Astma & COPD longarts, Franciscus Gasthuis & Vlietland, NVALT
- Mevr. C.L.Y. (Chantal) Knoops, longarts, VieCuri medisch centrum, NVALT
- Mevr. dr. E. (Eline) bij de Vaate, longarts, Merem medisch revalidatie NVALT
- Mevr. M.C. (Myrthe) van der Burg, longarts, Jeroen Bosch Ziekenhuis, NVALT
- Mevr. drs. P.M.G.A. (Pascale) Lubbers-van Tuynn, beleidsmedewerker, Longfonds
- Mevr. dr. M.C. (Marloes) Minnaard, huisarts/wetenschappelijk medewerker NHG
Betrokken clusterexpertisegroepleden
- Dhr. prof. dr. M. (Maarten) van den Berge, longarts, UMCG, NVALT
- Dhr. dr. E.C. (Erwin) Vasbinder, ziekenhuisapotheker, Franciscus Gasthuis & Vlietland, NVZA
Met ondersteuning van
- Mevr. M (Marieke) Schultink, junior adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- Mevr. dr. J. (Jose) Maas, senior adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- Mevr. dr. A.N. (Nynke) Kampstra, adviseur, Kennisinstituut van de Federatie Medisch Specialisten
- Mevr. E. (Esther) van der Bijl, medisch informatiespecialist, Kennisinstituut van de Federatie Medisch Specialisten
Belangenverklaringen
Clusterstuurgroepleden
Tabel 5 Gemelde (neven)functies en belangen stuurgroep
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Overige belangen |
Restrictie |
|
dr. Folkert Brijker (vz.) |
Longarts, Spaarne Gasthuis |
Geen |
Laatste 3 jaar adviesraden en presentaties verzorgd voor AstraZeneca, Chiesi, GSK, Sanofi, Sananet |
Geen |
Geen |
Geen |
Geen |
|
dr. Gert-Jan Braunstahl (vicevoorzitter) |
Longarts Franciscus Gasthuis & Vlietland |
Geen |
In laatste 3 jaar advieswerk gedaan voor GSK, Sanofi, AstraZeneca en ALK ABello. |
Geen |
* Astra Zeneca - Studie naar astma-exacerbaties - Projectleider |
Geen |
Geen |
|
Chantal Knoops |
Longarts, VieCuri Medisch Centrum Noord Limburg |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Eline Droppers - bij de Vaate |
Longarts, Merem Medische Revalidatie |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Myrthe van der Burg |
AIOS Longziekten in het Jeroen Bosch Ziekenhuis |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Yvonne Kappe |
Projectleider Longfonds |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Marloes Minnaarrd |
Huisarts en wetenschappelijk medewerker afdeling richtlijnontwikkeling. Nederlands Huisartsen Genootschap (NHG) |
Huisarts-redacteur Thuisarts (8u betaald) |
Geen |
Geen |
Geen |
Geen |
Geen |
|
Pascale Lubbers-van Tuyn |
Beleidsadviseur, Longfonds, betaalde functie |
Geen |
Geen |
Geen |
Geen |
Geen |
Geen |
Betrokken clusterexpertisegroepleden
Tabel 6 Gemelde (neven)functies en belangen expertisegroep
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Overige belangen |
Restrictie |
|
prof. dr. Maarten van den Berge |
Universitair Medeisch Centrum Groningen UMCG |
Lid Advisory Boards Sanofi, GlaxoSmithKline, Astra Zeneca, incomes paid to University Medical Center Groningen |
Geen |
Geen |
Research grants from Chiesi, Roche, Genentech, Sanofi, GlaxoSmithKline, Astra Zeneca, all paid to University Medical Center Groningen |
Geen |
Restricties op besluitvorming over biologicals (en formulering aanbevelingen) |
|
dr. Erwin Vasbinder |
Ziekenhuisapotheker, Franciscus Gasthuis & Vlietland |
Algemene farmaceutische klinisch dienstverlening, aandachtsgebieden: logistiek/assortimentsbeheer, opleider AIOS ziekenhuisfarmacie, farmaceutisch onderwijs, investigator initiated onderzoek vanuit de apotheek. |
Geen |
Geen |
Deelname aan en initiatie van verschillende investigator initiated onderzoeken financieel gesteund door AstraZeneca, Pfizer, TEVA, GSK: |
Geen |
Geen |
Inbreng patiëntenperspectief
Het patiëntenperspectief is ingebracht door deelname van Longfonds aan het cluster.
Kwalitatieve raming van mogelijke financiële gevolgen in het kader van de Wkkgz
Bij de richtlijnmodule voerden de clusterleden conform de Wet kwaliteit, klachten en geschillen zorg (Wkkgz) een kwalitatieve raming uit om te beoordelen of de aanbevelingen mogelijk leiden tot substantiële financiële gevolgen. Bij het uitvoeren van deze beoordeling is de richtlijnmodule op verschillende domeinen getoetst (zie het stroomschema bij Werkwijze).
|
Module |
Uitkomst raming |
Toelichting |
|
Module biologicals COPD |
Geen substantiële financiële gevolgen. |
Hoewel uit de toetsing volgt dat de aanbeveling(en) breed toepasbaar zijn (>40.000 patiënten), volgt ook uit de toetsing dat het geen nieuwe manier van zorgverlening of andere organisatie van zorgverlening betreft, het geen toename in het aantal in te zetten voltijdsequivalenten aan zorgverleners betreft en het geen wijziging in het opleidingsniveau van zorgpersoneel betreft. Er worden daarom geen substantiële financiële gevolgen verwacht.
|
Werkwijze
Voor meer details over de gebruikte richtlijnmethodologie verwijzen wij u naar de Werkwijze. Relevante informatie voor de ontwikkeling/herziening van deze richtlijnmodule is hieronder weergegeven.
Zoekverantwoording
Algemene informatie
|
Database(s): Embase.com, Ovid/Medline |
Datum: 8 mei 2025 |
|
Periode: vanaf 2000 |
Talen: geen restrictie |
|
BMI-zoekblokken: voor verschillende opdrachten wordt (deels) gebruik gemaakt van de zoekblokken van BMI-Online https://blocks.bmi-online.nl/ Deduplication: voor het ontdubbelen is gebruik gemaakt van http://dedupendnote.nl/ |
|
Zoekopbrengst 8 mei 2025
|
|
EMBASE |
OVID/MEDLINE |
Ontdubbeld |
|
SR |
255 |
28 |
257 |
|
RCT |
253 |
135 |
329 |
|
Totaal |
508 |
163 |
586* |
*in Rayyan
Zoekstrategie Embase.com 8 mei 2025
|
No. |
Query |
Results |
|
#1 |
'chronic obstructive lung disease'/exp OR ((chronic* NEAR/3 obstruct* NEAR/3 (airflow OR 'air flow' OR airway OR 'air way' OR lung* OR pulmon* OR bronchopulmon* OR respirator*)):ti,ab,kw) OR copd:ti,ab,kw OR 'chronic bronchit*':ti,ab,kw OR emphysema:ti,ab,kw OR aecopd:ti,ab,kw |
274136 |
|
#2 |
'monoclonal antibody'/exp OR 'mepolizumab'/exp OR 'benralizumab'/exp OR 'reslizumab'/exp OR 'dupilumab'/exp OR 'tezepelumab'/exp OR 'astegolimab'/exp OR (((clonal* OR hybridoma* OR monoclonal* OR 'mono clonal*') NEAR/3 (antibod* OR 'anti bod*')):ti,ab,kw) OR 'bat 2606':ti,ab,kw OR 'bat2606':ti,ab,kw OR 'bosatria':ti,ab,kw OR 'mepolizumab':ti,ab,kw OR 'nucala':ti,ab,kw OR 'sb 240563':ti,ab,kw OR 'sb-240563':ti,ab,kw OR 'sb240563':ti,ab,kw OR 'benralizumab':ti,ab,kw OR 'biw 8405':ti,ab,kw OR 'biw8405':ti,ab,kw OR 'fasenra':ti,ab,kw OR 'khk 4563':ti,ab,kw OR 'khk4563':ti,ab,kw OR 'medi 563':ti,ab,kw OR 'medi563':ti,ab,kw OR 'cep 38072':ti,ab,kw OR 'cep38072':ti,ab,kw OR 'cinqaero':ti,ab,kw OR 'cinqair':ti,ab,kw OR 'dcp 835':ti,ab,kw OR 'dcp835':ti,ab,kw OR 'reslizumab':ti,ab,kw OR 'sch 55700':ti,ab,kw OR 'sch55700':ti,ab,kw OR 'bat 2406':ti,ab,kw OR 'bat2406':ti,ab,kw OR 'dupilumab':ti,ab,kw OR 'dupixent':ti,ab,kw OR 'regn 668':ti,ab,kw OR 'regn668':ti,ab,kw OR 'sar 231893':ti,ab,kw OR 'sar231893':ti,ab,kw OR 'amg 157':ti,ab,kw OR 'amg157':ti,ab,kw OR 'medi 9929':ti,ab,kw OR 'medi9929':ti,ab,kw OR 'tezepelumab':ti,ab,kw OR 'tezepelumab ekko':ti,ab,kw OR 'tezepelumab-ekko':ti,ab,kw OR 'tezspire':ti,ab,kw OR 'amg 282':ti,ab,kw OR 'amg282':ti,ab,kw OR 'astegolimab':ti,ab,kw OR 'mstt 1041a':ti,ab,kw OR 'mstt1041a':ti,ab,kw OR 'rg 6149':ti,ab,kw OR 'rg6149':ti,ab,kw OR 'ro 7187807':ti,ab,kw OR 'ro7187807':ti,ab,kw |
959146 |
|
#3 |
#1 AND #2 |
5776 |
|
#4 |
#3 AND [2000-2025]/py NOT ('conference abstract'/it OR 'editorial'/it OR 'letter'/it OR 'note'/it) NOT (('animal'/exp OR 'animal experiment'/exp OR 'animal model'/exp OR 'nonhuman'/exp) NOT 'human'/exp) |
3958 |
|
#5 |
'meta analysis'/exp OR 'systematic review'/exp OR 'scoping review'/exp OR 'rapid review'/exp OR 'umbrella review'/exp OR 'cochrane database of systematic reviews'/jt OR 'network meta-analysis'/exp OR 'networkmeta analy*':ti,ab,kw OR 'networkmetaanaly*':ti,ab,kw OR metaanaly*:ti,ab,kw OR 'meta analy*':ti,ab,kw OR metanaly*:ti,ab,kw OR prisma:ti,ab,kw OR prospero:ti,ab,kw OR metaanali*:ti,ab,kw OR 'meta anali*':ti,ab,kw OR metanali*:ti,ab,kw OR (((systemati* OR scoping OR umbrella OR 'structured literature') NEAR/3 (review* OR overview*)):ti,ab,kw) OR (((structured OR systemic*) NEAR/3 (review* OR overview* OR synth*) NEAR/3 literature):ti,ab,kw) OR ((systemic* NEAR/1 review*):ti,ab,kw) OR (((systemati* OR literature OR database* OR 'data base*') NEAR/10 search*):ti,ab,kw) OR (((structured OR comprehensive* OR systemic*) NEAR/3 search*):ti,ab,kw) OR (((literature NEAR/3 (review* OR overview*)):ti,ab,kw) AND (search*:ti,ab,kw OR database*:ti,ab,kw OR 'data base*':ti,ab,kw)) OR (('data extraction*':ti,ab,kw OR 'data source*':ti,ab,kw) AND ('study selection*':ti,ab,kw OR 'studies selection*':ti,ab,kw)) OR ('search strateg*':ti,ab,kw AND 'selection criteria*':ti,ab,kw) OR ('data source*':ti,ab,kw AND 'data synth*':ti,ab,kw) OR medline*:ti,ab,kw OR pubmed*:ti,ab,kw OR 'pub med*':ti,ab,kw OR embase:ti,ab,kw OR cochrane*:ti,ab,kw OR (((critical* OR rapid*) NEAR/2 (review* OR overview* OR synth*)):ti) OR ((((critical* OR rapid*) NEAR/3 (review* OR overview* OR synth*)):ab) AND (search*:ab OR database*:ab OR 'data base*':ab)) OR metasynth*:ti,ab,kw OR 'meta synth*':ti,ab,kw OR 'review* of review*':ti,ab,kw |
1109361 |
|
#6 |
'randomized controlled trial'/exp OR random*:ti,ab OR (((pragmatic OR practical) NEAR/1 'clinical trial*'):ti,ab) OR ((('non inferiority' OR noninferiority OR superiority OR equivalence) NEAR/3 trial*):ti,ab) OR rct:ti,ab,kw |
2385099 |
|
#7 |
#4 AND #5 - SR |
255 |
|
#8 |
#4 AND #6 NOT #7 – RCT |
253 |
|
#9 |
#7 OR #8 - Totaal |
508 |
Zoekstrategie Ovid/Medline 8 mei 2025
|
# |
Searches |
Results |
|
1 |
exp Pulmonary Disease, Chronic Obstructive/ or (chronic* adj3 obstruct* adj3 (airflow or air flow or airway or air way or lung* or pulmon* or bronchopulmon* or respirator*)).ti,ab,kf. or copd.ti,ab,kf. or chronic bronchit*.ti,ab,kf. or emphysema.ti,ab,kf. or aecopd.ti,ab,kf. |
136836 |
|
2 |
exp Antibodies, Monoclonal/ or ((clonal* or hybridoma* or monoclonal* or mono clonal*) adj3 (antibod* or anti bod*)).ti,ab,kf. or bat 2606.ti,ab,kf. or bat2606.ti,ab,kf. or bosatria.ti,ab,kf. or mepolizumab.ti,ab,kf. or nucala.ti,ab,kf. or sb 240563.ti,ab,kf. or sb-240563.ti,ab,kf. or sb240563.ti,ab,kf. or benralizumab.ti,ab,kf. or biw 8405.ti,ab,kf. or biw8405.ti,ab,kf. or fasenra.ti,ab,kf. or khk 4563.ti,ab,kf. or khk4563.ti,ab,kf. or medi 563.ti,ab,kf. or medi563.ti,ab,kf. or cep 38072.ti,ab,kf. or cep38072.ti,ab,kf. or cinqaero.ti,ab,kf. or cinqair.ti,ab,kf. or dcp 835.ti,ab,kf. or dcp835.ti,ab,kf. or reslizumab.ti,ab,kf. or sch 55700.ti,ab,kf. or sch55700.ti,ab,kf. or bat 2406.ti,ab,kf. or bat2406.ti,ab,kf. or dupilumab.ti,ab,kf. or dupixent.ti,ab,kf. or regn 668.ti,ab,kf. or regn668.ti,ab,kf. or sar 231893.ti,ab,kf. or sar231893.ti,ab,kf. or amg 157.ti,ab,kf. or amg157.ti,ab,kf. or medi 9929.ti,ab,kf. or medi9929.ti,ab,kf. or tezepelumab.ti,ab,kf. or tezepelumab ekko.ti,ab,kf. or tezepelumab-ekko.ti,ab,kf. or tezspire.ti,ab,kf. or amg 282.ti,ab,kf. or amg282.ti,ab,kf. or astegolimab.ti,ab,kf. or mstt 1041a.ti,ab,kf. or mstt1041a.ti,ab,kf. or rg 6149.ti,ab,kf. or rg6149.ti,ab,kf. or ro 7187807.ti,ab,kf. or ro7187807.ti,ab,kf. |
397778 |
|
3 |
1 and 2 |
620 |
|
4 |
limit 3 to yr="2000 -Current" |
560 |
|
5 |
4 not (comment/ or editorial/ or letter/) not ((exp animals/ or exp models, animal/) not humans/) |
497 |
|
6 |
exp Meta-Analysis/ or exp Network Meta-Analysis/ or exp Systematic Review/ or (networkmeta analy* or networkmetaanaly* or metaanaly* or meta analy* or metanaly* or prisma or prospero or metaanali* or meta anali* or metanali*).ti,ab,kf. or ((systemati* or scoping or umbrella or structured literature) adj3 (review* or overview*)).ti,ab,kf. or ((structured or systemic*) adj3 (review* or overview* or synth*) adj3 literature).ti,ab,kf. or (systemic* adj1 review*).ti,ab,kf. or ((systemati* or literature or database* or data base*) adj10 search*).ti,ab,kf. or ((structured or comprehensive* or systemic*) adj3 search*).ti,ab,kf. or ((literature adj3 (review* or overview*)) and (search* or database* or data base*)).ti,ab,kf. or ((data extraction* or data source*) and (study selection* or studies selection*)).ti,ab,kf. or (search strateg* and selection criteria*).ti,ab,kf. or (data source* and data synth*).ti,ab,kf. or (medline* or pubmed* or pub med* or embase or cochrane*).ti,ab,kf. or cochrane.jw. or ((critical* or rapid*) adj2 (review* or overview* or synth*)).ti. or (((critical* or rapid*) adj3 (review* or overview* or synth*)) and (search* or database* or data base*)).ab. or metasynth*.ti,ab,kf. or meta synth*.ti,ab,kf. |
828744 |
|
7 |
exp clinical trial/ or randomized controlled trial/ or exp clinical trials as topic/ or randomized controlled trials as topic/ or Random Allocation/ or Double-Blind Method/ or Single-Blind Method/ or (clinical trial, phase i or clinical trial, phase ii or clinical trial, phase iii or clinical trial, phase iv or controlled clinical trial or randomized controlled trial or multicenter study or clinical trial).pt. or random*.ti,ab. or (clinic* adj trial*).tw. or ((singl* or doubl* or treb* or tripl*) adj (blind$3 or mask$3)).tw. or Placebos/ or placebo*.tw. |
2886769 |
|
8 |
5 and 6 - SR |
28 |
|
9 |
(5 and 7) not 8 – RCT |
135 |
|
10 |
8 or 9 - Totaal |
163 |