
Orthokeratologie
Uitgangsvraag
Wat is het effect van de myopie remmende orthokeratologie lenzen ten opzichte van reguliere lenzen of brillenglazen op progressieve myopie?
Aanbeveling
Bespreek de impact van leefstijl voordat je start met een farmacologische of optische interventie om de progressie van myopie te vertragen.
Bespreek met het kind en de ouders de mogelijke opties ter beperking van progressieve myopie bij een indicatie voor progressieve myopie, waaronder optische en medicamenteuze interventies. Leg de voor- en nadelen van deze opties uit en bepaal samen met het kind en de ouders welke interventie de voorkeur heeft.
Bied kinderen die de voorkeur geven aan het dragen van contactlenzen de mogelijkheid aan tot een interventie met myopieremmende contactlenzen (orthokeratologie of myopieremmende zachte lenzen) in plaats van reguliere contactlenzen om de progressie van myopie te verminderen.
Bespreek bij de nadelen dat het dragen van ortho-k lenzen bij kinderen een hogere kans op microbiële keratitis met zich mee brengt ten opzichte van zachte contactlenzen. Bespreek hygiënevoorschriften en bied de interventie alleen aan als ouders en kind deze zorgvuldig kunnen naleven.
Behandel geen kinderen met een sterkte hoger dan S-5.00 dpt en C-1.50 met orthokeratologie. Orthokeratologie kan overwogen worden vanaf een minimumleeftijd van 8 jaar; voor de leeftijdsgroep 8 tot 12 jaar geldt echter dat voorschrijven alleen op strikte indicatie plaatsvindt. Goede compliance en goede hygiëne zijn voor alle leeftijden van essentieel belang.
Overwegingen
Waarom deze aanbeveling?
Ortho-k is effectief gebleken in het verminderen van de progressie van myopie bij kinderen, met een klinisch relevante afname in groei van de aslengte. Omdat sommige studies een iets hoger risico op complicaties laat zien, dient voor de veiligheid van deze interventie goede hygiëne en ouderlijk toezicht gewaarborgd te zijn. De meeste geïncludeerde studies zijn uitgevoerd bij kinderen vanaf 8 jaar. Om die reden kan ortho-k vanaf deze leeftijd worden overwogen, waarbij behandeling bij kinderen van acht tot twaalf jaar alleen op strikte indicatie plaatsvindt. Dit vraagt om een zorgvuldige individuele afweging, waarbij patiëntgebonden factoren, de situatie van het kind en de mogelijkheid tot goede naleving van hygiëne- en compliancevoorwaarden worden meegewogen. De interventie biedt praktische voordelen, zoals scherp zicht overdag zonder gebruik van brillen of lenzen, maar vraagt om zorgvuldige therapietrouw en monitoring. De kosten en beperkingen bij hogere sterktes vormen echter aandachtspunten. Deze overwegingen vormen de basis voor het overwegen van ortho-k als een mogelijke optie voor myopie management, waarbij de individuele omstandigheden en voorkeuren meegewogen moeten worden om tot een goed geïnformeerd besluit van ouders en kind te komen.
Eindoordeel aanbeveling: Conditionele aanbeveling voor.
Balans tussen gewenste en ongewenste effecten
Er is literatuuronderzoek verricht naar het effect van ortho-k lenzen ten opzichte van reguliere lenzen of brillen bij kinderen met progressieve myopie. Er werd één systematische review en vier losse studies geïncludeerd in de analyse waarbij de langste follow-up duur van de geïncludeerde RCT twee jaar was. Voor de cruciale uitkomstmaat aslengte werd een klinisch relevant verschil gevonden in het voordeel van de patiënten die ortho-k lenzen droegen. De remmende werking van de interventie was het sterkst in het eerste jaar van de onderzoeken die uiteindelijk in totaal twee jaar zijn uitgevoerd (figuur 1). Waarbij de studies van Cho (2012), Charm (2013) en Choi (2023) het eerste jaar gemiddeld een remming van 0,19 mm/jaar liet zien, nam dit af in het tweede jaar tot ongeveer 0,08 mm/jaar. Gezien de constante resultaten van de studies in het remmende effect van ortho-k op aslengte groei, kan de kwaliteit van het bewijs voor aslengte als consistent worden beschouwd. Voor de uitkomstmaten bijwerkingen en therapietrouw werden verschillen gevonden in het voordeel van de patiënten die reguliere brillen of lenzen droegen. De kwaliteit van het bewijs voor deze twee uitkomstmaten was echter laag tot zeer laag. Daar ortho-k direct de refractie corrigeert is de refractie toename over de tijd alleen te bepalen na een washout (stoppen met het dragen van de lenzen) van enkele weken. Dit is niet gangbaar in een onderzoek setting of in de klinische praktijk.
Veiligheid
De veiligheid van het lange tijd dragen van ortho-k lenzen werd onderzocht in een observationele studie met een follow-up van tien jaar (Hiraoka, 2018). De complicaties beschreven in medische dossiers van kinderen jonger dan zestien jaar die ortho-k lenzen (ortho-k groep: 104 ogen van 53 kinderen) hadden gedragen als myopiecontrole werden vergeleken met complicaties beschreven bij kinderen die zachte contactlenzen (controlegroep 78 ogen van 39 kinderen) hadden gedragen (tabel 3). De meest voorkomende bijwerkingen waren allergische conjunctivitis en cornea punctata (aankleuring), maar die kwamen bij beiden in ongeveer gelijke mate voor. Cornea erosies kwamen in beide groepen weinig voor, cornea infiltraten waren alleen beschreven bij de ortho-k groep, en blepharitis, hordeolum en chalazion alleen bij de zachte contactlens groep. In deze studie was het totale aantal complicaties niet significant verschillend tussen de groepen, waren de complicaties niet visus bedreigend en werd er geen microbiële keratitis gerapporteerd. Een studie van Bullimore (2013) onderzocht de incidentie van microbiële keratitis onder 1494 patiënten met ortho-k. Er werden 2 gevallen van keratitis gevonden, beiden bij kinderen, zonder uiteindelijke visusdaling. De studie van Stapleton (2008) laat het verschil in risico op ernstige complicaties zien zoals het krijgen van een microbiële keratitis bij verschillende contactlensmodaliteiten. Risico op visusdaling kwam in 0,6 van de 10.000 lensdragers voor (Stapleton, 2008). Deze incidentie is heel laag, maar uit de studie van Jung (2024) blijkt dat keratitis een adverse event is met risico op onomkeerbare visusverandering.
De effectiviteit van ortho-k is ook aangetoond voor myope refractie waarden van meer dan -5.50 dpt, maar de refractie correctie door ortho-k is dan in veel gevallen niet toereikend en behoeft additionele correctie door een bril (Zhou, 2015; Lyu 2020). Bij refractiecorrectie door ortho-k van -6.00 dpt wordt bij 28% corneale aankleuring beschreven (Lyu 2020), hoewel dat in de helft van de gevallen tijdelijk blijkt te zijn (Charm 2013).
Een punt van aandacht is de kans op cornea vervorming door ortho-k en daardoor optische aberraties. In een studie van Sun (2017) werden bij 49 ogen van 26 10-jarige kinderen na het dragen van ortho-k, de parameters van de vorm van de cornea gemeten. Hoewel de refractieafwijking goed verbeterde, werden veranderingen aan de vorm van de cornea en hoger-order, vooral sferische aberraties en verticale coma beschreven. Decentratie van de contactlens kan hierbij een rol spelen.
Tabel 3. Aantal en typen bijwerkingen
|
Bijwerking |
Ortho-k |
Zachte contactlenzen |
P Waarde |
|
Acute conjunctivitis |
25 (2,4%) |
23 (2,7%) |
0.74 |
|
Allergische conjunctivitis |
48 (4,6%) |
29 (3,4%) |
0.10 |
|
Phlyctenulaire conjunctivitis |
2 (0,2%) |
0 (0,0%) |
0.50 |
|
Oppervlakkige punctata keratopathie |
32 (3,1%) |
33 (3,8%) |
0.29 |
|
Hoornvlieserosie |
1 (0,1%) |
1 (0,1%) |
1.00 |
|
Hoornvliesinfiltratie en keratitis |
8 (0,8%) |
0 (0,0%) |
0.009 |
|
Blefaritis (ooglidontsteking) |
0 (0,0%) |
3 (0,3%) |
0.009 |
|
Hordeolum |
0 (0,0%) |
8 (0,9%) |
0.001 |
|
Chalazion (ooglidcyste) |
0 (0,0%) |
5 (0,6%) |
0.018 |
|
Andere |
3 (0,3%) |
1 (0,1%) |
0.63 |
|
Totaal |
119 (11,4%) |
103 (12,0%) |
0.72 |
Uit Hiraoka (2018)
Tabel 4. Risico op microbiële keratitis ten opzichte van verschillende contactlensmodaliteiten
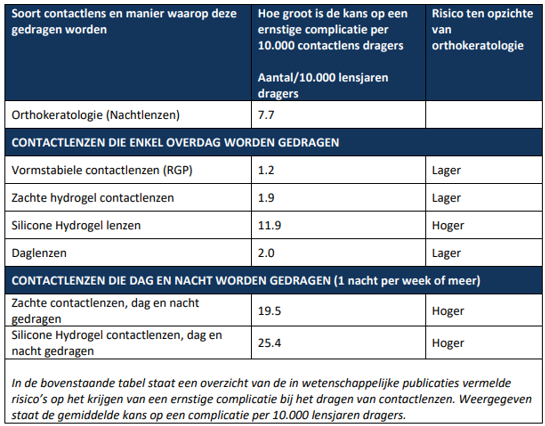
Uit Stapleton (2008)
Drop-outs
Acceptatie van ortho-k is onderzocht door Li (2016). Het percentage drop-outs was 0-54% in de ortho-k groep en 0-38% in de controlegroep die een enkelvoudige bril droeg. De meta-analyse vond geen significant verschil in drop-outs tussen de 2 groepen (p = 0.64) wat suggereert dat ortho-k in het algemeen goed door kinderen wordt geaccepteerd.
Lange termijn effecten
In een studie van Santodomingo-Rubido (2025) werden na een initiële onderzoeksperiode van twee jaar, de aslengte van de onderzoeks- en controlegroep (enkelvoudige bril) na vijf en zeven jaar later weer gemeten. Na een totale interventieduur van elf jaar was de aslengte van de onderzoeksgroep tot wel 0,69 mm korter dan die van de controlegroep, wat kan pleiten voor de langtermijneffecten van ortho-k op de remming van de aslengte groei. Het afvlakken van de progressie van beide onderzoeksgroepen kan worden verklaard door vertraagde groei van de aslengte op latere leeftijd.
Door het dragen van ortho-k vindt er afvlakking van de cornea plaats. Deze verandering ten opzichte van de totale aslengte kan als minimaal worden beschouwd. Er is geen significante invloed op het voorste oogsegment en de gemeten aslengte weerspiegelt de werkelijke groei van het oog (Cheung, 2013; Cho, 2005; González-Mesa, 2013).
Effectiviteit mate van myopie
In een niet-gerandomiseerde, prospectieve studie van Lu (2024) werden drie interventies bij kinderen van zeven tot vierteen jaar oud met lage en matige myopie vergeleken met: reguliere enkelvoudige brillenglazen (n=180), myopie remmende brillenglazen (DIMS) (n=180) en ortho-k lenzen (n=180). De uitkomstmaat groei van aslengte werd in mm gerapporteerd. De gemiddelde groei was na een jaar respectievelijk 0,38±0,19 mm, 0,30±0,22 mm en 0,20±0,18 mm (P < 0.001). De studie heeft echter ook gekeken naar het verschil in progressie onder de verschillende mate van myopie. In de groep lage myopie (<1.50 dpt) lieten de DIMS en de ortho-k groep gelijke remming in aslengtegroei zien en beiden minder hoog dan de controlegroep (P = 0.001). In de groep matige (<-3.50 dpt) en hoge myopie (<5.00 dpt) liet de ortho-k lens de minste aslengte progressie zien (P < 0.001).
Ook in de niet-gerandomiseerde, prospectieve studie van Lai (2024) werden drie interventies bij kinderen van zeven tot dertien jaar oud met lage myopie vergeleken: reguliere brillenglazen (n=50), myopie remmende brillenglazen (HAL) (n=50) en ortho-k lenzen (n=50). De uitkomstmaat groei van aslengte in mm werd gerapporteerd. De gemiddelde groei was na een jaar respectievelijk 0,516±0,190 mm, 0,163±0,113 mm en 0,280±0,170 mm (P < 0.001). De studie concludeert dat, na één jaar, ortho-k lenzen effectiever zijn dan reguliere lenzen in het reguleren van de groei van aslengte in kinderen met lage myopie. In verhouding met de resultaten uit de geïncludeerde RCTs voor deze richtlijn laat dit dezelfde effectieve effecten op de remming van de aslengte groei zien.
In de studie van Lai (2024) deden de myopieremmende glazen het iets beter in remming van de aslengte dan de ortho-k lenzen (met name lage myopie in baseline meting) en in de studie van Lu (2024) was gemiddeld gezien de ortho-k lens het effectiefst (meer verschillende baseline refracties). In beide artikelen wordt het verschil in effectiviteit van de interventies verklaard door het effect van perifere defocus. Bij myopieremmende brillenglazen kan in de perifere zone een hogere additie worden toegepast, terwijl de werking van ortho-k onder andere afhankelijk is van de corneakromming, pupilgrootte en refractie van de individuele patiënt. Het onderliggende mechanisme van deze verschillen is gerelateerd aan perifere defocus (Queirós, 2025).
Noord-Europese studies
Uit de literatuur search zijn er met name Aziatische studies naar voren gekomen. De studie van Jakobsen (2025) heeft Noord-Europese kinderen in de leeftijd van zes tot twaalf jaar geïncludeerd en gevolgd over een periode van drie jaar waarbij er elke zes maanden de aslengte is vervolgd. De aslengte progressie werd verminderd met 0,123 mm ten opzichte van de controlegroep die een enkelvoudige bril droeg. Daarnaast vergeleek het onderzoek de aslengte veranderingen tijdens de eerste 18 maanden van ortho-k gebruik tussen jongere en iets oudere kinderen. Hierbij werden geen statistisch significante verschillen gevonden. Verder deden er zich tijdens dit onderzoek geen ernstige bijwerkingen voor. Het artikel van Santodomingo (2024) includeerde Zuid-Europese kinderen van zes tot tien jaar over een periode van twee jaar waarbij een verschil van 0,24 mm aan het eind van de studie gemeten was ten opzichte van de controlegroep die een enkelvoudige bril droeg.
De meta-analyse van Tang (2023) heeft deze studie ook opgenomen. Myopie ontwikkelt zich bij kinderen in Azië sneller op een jongere leeftijd, wat maakt dat myopie management nog belangrijker is voor Oost-Aziatische kinderen dan voor Europese kinderen. Hoewel het potentieel van ortho-k voor myopiemanagement in Europa door studies ondersteund wordt, is er nog steeds een beperkt aantal studies met Noord-Europese kinderen (Tang 2023).
Non-responders
Op individueel niveau zal de aslengte progressie bij het ene kind sneller gaan dan bij het andere, ook wanneer ortho-k wordt toegepast. Dit kan onder andere te maken hebben met leeftijd, onset van de myopie en pupilgrootte. Wanneer de progressie van de aslengte sneller is ondanks gebruik van ortho-k is te overwegen om de optische zone van de lens waar mogelijk te verkleinen (Zhou, 2024) en/of de interventie te combineren met atropine (Tang, 2024; Tsai, 2022; Xu, 2023). Voor de volledige overwegingen en aanbevelingen, zie richtlijnmodule multi-modale myopieremming.
Stoppen
Indien wordt gestopt met het dragen van ortho-k lenzen, moet rekening worden gehouden met het risico dat de aslengte opnieuw kan toenemen. In de studie van Cho (2017) werd het effect onderzocht van het onderbreken en later hervatten van ortho-k.
Het is onduidelijk of het myopie remmend effect van ortho-k volledig verdwijnt na het stoppen van de interventie, waarbij er gelet zou moeten worden op het reboundeffect. Dit kan betekenen dat de aslengte alsnog toeneemt tot het niveau dat verwacht zou zijn zonder interventie, of in het ongunstigste geval zelfs sneller toeneemt dan wanneer er nooit een interventie was toegepast. Cho (2017) toonde aan dat de aslengtegroei weer versnelde wanneer er na 2 jaar werd gestopt met het dragen van ortho-k. De snelheid van de groei was vergelijkbaar met die van de controlegroep die tijdens de initiële 2 jaar van het onderzoek een enkelvoudige bril droeg. Dit suggereert dat de ogen na het stoppen van het dragen van ortho-k mogelijk weer doorgroeien volgens het verwachte fysiologische patroon van myopen die geen interventie ontvangen, zonder versnelde progressie. Op basis van de beschikbare literatuur, waar een relatief korte interventieduur is, kunnen er geen definitieve uitspraken gedaan worden over het optreden van rebound bij optische interventie zoals het dragen van myopie remmende zachte contactlenzen. Bullimore (2024) benadrukt dat rebound vaak een artefact van studiedesign is. In de klinische praktijk, waar interventie over het algemeen jarenlang wordt voortgezet en meestal geleidelijk wordt afgebouwd op een leeftijd waarop de fysiologische progressie al vertraagt, wordt over het algemeen geen klinisch relevante rebound gezien.
Kwaliteit van bewijs
De overall kwaliteit van bewijs is laag. Dit betekent dat we onzeker zijn over het gevonden geschatte effect van de cruciale uitkomstmaten. Vanuit klinisch oogpunt betekent een lage bewijskracht niet dat er geen effect is, maar wel dat we voorzichtig moeten zijn in de interpretatie, transparantie naar patiënten en ouders, en bereid moeten zijn om onze keuzes bij te stellen zodra sterker bewijs beschikbaar komt.
Er is afgewaardeerd vanwege ernstige:
- Risk of Bias: methodologische beperkingen: verborgen allocatie, blindering (alleen bij subjectieve uitkomstmaten), missende data.
- Indirectheid: indirectheid van bewijs, door verschillen in populatie.
Voor de belangrijke uitkomstmaten werd ook afgewaardeerd voor ernstige:
- Imprecisie: onnauwkeurigheid, omdat het betrouwbaarheidsinterval de grens van klinische relevantie overschrijdt.
Waarden en voorkeuren van patiënten (en eventueel hun naasten/verzorgers)
Het is belangrijk om de verschillende opties voor het remmen van de progressie van de myopie met zowel de ouders als het kind te bespreken. Hierbij dienen leefstijlinterventies altijd terug te blijven komen naast het starten van andere interventies. Of alle opties mogelijk zijn hangt af van de persoonlijke voorkeur van de ouders en het kind, de financiële haalbaarheid, de uitgangswaarden en de coöperativiteit.
Het vertragende effect op de progressie van de aslengte is duidelijk bewezen. Ortho-k biedt daarnaast het voordeel van scherp zicht overdag zonder dat het dragen van een bril of contactlenzen nodig is. Een bijkomend voordeel is dat kinderen hun lenzen alleen thuis gebruiken, zodat de ouders bij het in- en uitzetten van de lenzen aanwezig kunnen zijn en/of kunnen assisteren en kunnen controleren of de hygiëne in acht wordt genomen. Evenals bij de zachte contactlens module dienen kinderen waar nodig met de hygiëne ondersteund te worden door ouder(s)/verzorger(s). Het wordt geadviseerd om bij de start van de interventie met ortho-k alle voor- en nadelen met de ouders en het kind te bespreken en in de vorm van een informed consent vast te leggen en gedurende de interventieperiode strikte controle momenten aan te houden bij de optometrist en/of contactlensspecialist. Van groot belang is de cyclometing bij het eerste consult, waardoor dat eerste consult altijd bij een oogarts/optometrist/orthoptist plaats dient te vinden. Ook is het van belang om de interventie langdurig te handhaven. Vroegtijdig stoppen kan de effectiviteit van de interventie verminderen (Cho, 2017).
Het nadeel van ortho-k is dat het niet voor iedere myope correctie toepasbaar is (Hu, 2021). Ook in Nederland houden we over het algemeen een maximumsterkte van S-5.00 dioptrie aan en een maximale cilinder van C-1.50. Voor meer details en aanpasadviezen kan de OVN richtlijn “Vooronderzoek en controle bij cosmetische contactlenzen” geraadpleegd worden. Het is belangrijk dat hygiëne en onderhoudsinstructies zowel door de ouders als het kind in acht worden genomen. Het vergt vaardigheid om deze lenzen in- en uit te kunnen zetten en discipline om er hygiënisch mee om te kunnen gaan. Tevens brengt het dragen van contactlenzen altijd het risico op complicaties met zich mee. Daarnaast zijn de hogere kosten van de lenzen en het ontbreken van vergoedingen uit de (basis) zorgverzekering een belangrijk bezwaar voor ouders. Het is dan ook essentieel om samen met ouders en kinderen een weloverwogen beslissing te maken, waarbij rekening wordt gehouden met hun voorkeuren, motivatie en financiële mogelijkheden.
Kostenaspecten
De interventie levert meer kosten ten opzichte van het niet beperken van myopieprogressie. Dit weegt wel op tegen het verschil in effectiviteit. Het dragen van ortho-k lenzen is over het algemeen iets duurder dan het dragen van een enkelvoudige bril of contactlenzen en vergelijkbaar met de kosten van andere myopie remmende interventies. De kosten van ortho-k wordt niet vergoed vanuit de basisverzekering. Daardoor is het van belang in gesprek te gaan met ouders of de kosten gedragen kunnen worden van de interventie.
Gelijkheid ((health) equity/equitable)
De interventie leidt tot een mogelijke afname van gezondheidsgelijkheid, omdat ortho-k momenteel niet worden vergoed vanuit de (basis) zorgverzekering. Dit betekent dat de toegang tot deze interventie afhankelijk is van de financiële situatie van ouder(s)/verzorger(s). In gezinnen met een lagere sociaaleconomische status of zonder aanvullende verzekering kan dit leiden tot het niet kunnen kiezen voor deze optie, ondanks de klinisch relevante gezondheidswinst. Atropine is de enige vergoede optie op dit moment. Het is belangrijk om in de spreekkamer bewust stil te staan bij deze ongelijkheid en samen met ouders te bespreken welke opties haalbaar zijn binnen hun context.
Aanvaardbaarheid:
Ethische aanvaardbaarheid
De interventie lijkt aanvaardbaar voor de betrokkenen mits alle voor- en nadelen zijn afgewogen. Er zijn geen ethische bezwaren. De studies benadrukken de relatieve veiligheid van ortho-k ten opzichte van zachte contactlenzen. Het is een ethisch verantwoorde interventie als de nadruk licht op veiligheid, geïnformeerde toestemming en bij het naleven van de richtlijnen. Er zijn geen statistisch significante verschillen in bijwerkingen tussen ortho-k en controlegroepen gevonden. De enkele bijwerkingen die werden gemeld waren over het algemeen mild en omkeerbaar met sporadisch ernstigere bijwerkingen. Een ethische zorg kan een hoog percentage drop-outs zijn waarbij of de lens niet geaccepteerd/verdragen wordt door het kind of niet de juiste scherpte behaald wordt.
Duurzaamheid
Het dragen van ortho-k contactlenzen is niet specifiek meer of minder duurzaam dan reguliere contactlenzen of brillenglazen. De geadviseerde vervangtermijn van ortho-k lenzen zit op 6-maandelijks tot jaarlijks. Zachte contactlenzen voor myopie management worden over het algemeen dagelijks of maandelijks vervangen. Bij zowel ortho-k als zachte maandlenzen zijn contactlensvloeistoffen nodig. Bij daglenzen heb je meer (verpakkings)materiaal nodig maar geen vloeistoffen. Brillenglazen en monturen gaan bij kinderen gemiddeld 1-2 jaar mee, ook afhankelijk van hoe snel de sterkte aangepast moet worden en er dus nieuwe glazen nodig zijn.
Haalbaarheid
De veiligheid van ortho-k is, zeker bij jonge kinderen, een aandachtspunt waardoor haalbaarheid belemmerd kan worden. De leeftijd waarop ortho-k gestart werd was in 2 studies vanaf zes jaar maar de overige klinische trials was dit vanaf acht jaar of ouder; het is redelijk om de leeftijd vanaf acht jaar als ondergrens te handhaven. Deze interventie vergt discipline wat betreft het schoonhouden, in- en uitdoen van de lenzen en regelmatige controle. Indien hiervan afgeweken wordt kan de kans op complicaties toenemen. Daarentegen is ook duidelijk dat hoe jonger kinderen zijn, hoe sneller het oog groeit, en hoe effectiever een interventie kan zijn.
Daarnaast onderscheidt Nederland zich van andere landen wat betreft contactlens aanpassingen. In de meeste landen maken ortho-k lenzen gemiddeld 1.2% deel uit van alle contactlensaanpassingen. In Nederland is dit percentage echter 6.0%. Dit komt waarschijnlijk doordat het in Nederland al lange tijd gewoon is om vormstabiele contactlenzen aan te passen. Ortho-k maken hier onderdeel van uit. Tevens zijn producenten lokaal in Nederland gevestigd en zijn op maat gemaakte ontwerpen mogelijk (Morgan, 2016; Morgan, 2019).
In de dagelijkse praktijk zal niet iedere behandelaar het volledige assortiment aan optische interventies mogelijk kunnen aanbieden. Praktijken moeten vaak afspraken maken met leveranciers waardoor er voorkeuren ontstaan. Er is behoefte aan meer wetenschappelijk onderzoek naar de effectiviteit van de verschillende producten in dezelfde productcategorie.
Onderbouwing
Orthokeratology lenses (ortho-k) is a non-surgical method in which specially designed contact lenses are worn overnight to temporarily correct myopia. During the day, this eliminates the need for additional refractive correction. In the Netherlands, these lenses are prescribed by optometrists and contact lens specialists both for refractive correction and with the aim of slowing myopia progression in children. There are several products on the market with some sort of regulatory approval especially for myopia management. In this module, the current literature on the effect of myopia-controlling ortho-k lenses on axial length in progressive myopia is examined.
Summary of Findings
Population: Children with progressive myopia
Intervention: Ortho-k lenses (worn during the night)
Comparator: Regular lenses or spectacle lenses (worn during the day)
|
Outcome Timeframe |
Study results and measurements |
Absolute effect estimates |
Certainty of the evidence (Quality of evidence) |
Summary |
|
|
SVS |
ortho-k |
||||
|
Axial length elongation 1 year |
Measured by: Scale: - Lower better Based on data from 945 participants in 9 studies Follow up 1 year |
Mean |
Mean |
Low door ernstige risico op bias, door ernstige indirectheid1 |
Ortho-k zal mogelijk axial length elongation verminderen |
|
Difference: MD 0.14 lower (CI 95% 0.16 lower - 0.12 lower) |
|||||
|
Adverse events |
Relative risk: 4.44 (CI 95% 0.97 – 20.25) Based on data from 274 participants in 5 studies
Swarbrick (2014) reported a RR of 0.33 (95% CI 0.01 – 7.89) for ortho-k vs. RGP |
7 per 1000 |
32 per 1000 |
Very low door ernstige risico op bias, door ernstige indirectheid, door zeer ernstige onnauwkeurigheid2 |
We zijn onzeker of ortho-k adverse events zal verhogen of verlagen |
|
Difference: 24.7 more per 1000 (CI 95% 0 fewer - 141 more) |
|||||
|
Compliance/ adherence to therapy
|
Relative risk: 1.62 (CI 95% 0.96 - 2.74) Based on data from 638 participants in 6 studies
|
113 per 1000 |
183 per 1000 |
Very low door ernstige risico op bias, door ernstige indirectheid, door ernstige onnauwkeurigheid3 |
We zijn onzeker of ortho-k compliance/adherence to therapy zal verhogen of verlagen |
|
Difference: 70.2 more per 1000 (CI 95% 5 fewer - 196 more) |
|||||
1. Risk of Bias: serious. Inadequaat verbergen van allocatie tijdens het randomisatieproces, wat resulteert in selectievertekening, Onvoldoende blindering/ ontbreken van blindering van de deelnemers en onderzoekers, waardoor mogelijk vertekening ontstaat, Onvoldoende blindering/ ontbreken van uitkomstassessoren, waardoor mogelijk detectievertekening ontstaat; Indirectness: serious. Differences between the target population and the group being studied.
2. Risk of Bias: serious. Inadequaat verbergen van allocatie tijdens het randomisatieproces, wat resulteert in selectievertekening, Onvoldoende blindering/ ontbreken van blindering van de deelnemers en onderzoekers, waardoor mogelijk vertekening ontstaat, Onvoldoende blindering/ ontbreken van uitkomstassessoren, waardoor mogelijk detectievertekening ontstaat, Onvolledige data en/of veel uitval van participanten (loss to follow up); Indirectness: serious. Differences between the target population and the group being studied. Imprecision: very serious. Brede betrouwbaarheidsintervallen.
3. Risk of Bias: serious. Inadequaat verbergen van allocatie tijdens het randomisatieproces, wat resulteert in selectievertekening, Onvoldoende blindering/ ontbreken van blindering van de deelnemers en onderzoekers, waardoor mogelijk vertekening ontstaat, Onvoldoende blindering/ ontbreken van uitkomstassessoren, waardoor mogelijk detectievertekening ontstaat, Onvolledige data en/of veel uitval van participanten (loss to follow up); Indirectness: serious. Differences between the target population and the group being studied. Imprecision: serious.
Description of studies
A total of one systematic review and four individual studies were included in the analysis of the literature. Important study characteristics and results are summarized in table 2. The assessment of the risk of bias is summarized in the risk of bias tables (under the tab ‘Evidence tabellen’).
Tang (2023) performed a systematic review and meta-analysis. RCTs included myopic children up to eighteen years old and compared ortho-k with controls (single-vision spectacles or contact lenses). The outcome was axial length elongation, adverse events, and drop-outs. Seven RCTs were included in the analysis. Five RCTs included patients with a Chinese ethnicity, one RCT included patients with East Asian ethnicity and one RCT included patients with Scandinavian ethnicity.
Choi (2023) performed a single-blind, randomized trial comparing ortho-k with single vision spectacles after 2 years. The inclusion criteria were spherical refractive error of -4.0 to -1.0 D, astigmatic error half of the spherical error, and the best-corrected visual acuity of LogMAR 0.10 or better in both eyes. All procedures were conducted in the Optometry Research Clinic of The Hong Kong Polytechnic University. The RCT included children with a Chinese ethnicity aged 8-12 years.
Zhu (2023) performed a randomized prospective trial comparing ortho-k with single-vision spectacles at 1 year. The inclusion criteria were: spherical equivalent -5.0 D to -1.0 D, conforming corneal astigmatism less than 1.50 D, Inverse corneal astigmatism less than 0.75 D, corneal topography, the minimum curvature of the cornea (D) minus the expected reduction greater than 36 D, corneal diameter of 10.9 - 12.5 mm, best-corrected visual acuity (BCVA) > 0.0 logMAR, myopic children, eight to twelve years old, willing to participate in 13-month observation. The procedures were conducted in the Department of Ophthalmology, the First Affiliated Hospital of Kunming Medical University and the Department of Pediatric Ophthalmology, the Affiliated Hospital of Yunnan University in China. The RCT was performed in China.
Fang (2022) performed a prospective single-blind, randomized clinical trial comparing ortho-k with single vision spectacles at 1 year. The inclusion criteria were children aged seven to fifteen, cycloplegic spherical refraction measurements between -8.0 D and -1.0 D, astigmatism of ≤1.00 D, myopia progression of ≥0.75 D in the last year or ≥0.50 D in the last 6 months, ability to complete a follow-up of at least 12 months, ability to understand the purpose of the trial, and voluntarily participate. The procedures were conducted in two centers: The First and the Fourth Affiliated Hospital, Zhejiang University School of Medicine. The RCT was performed in China.
Table 2. Characteristics of included studies
|
Study |
Participants |
Comparison |
Follow-up |
Outcome measures |
Comments |
Risk of bias (per outcome measure)* |
|
Included in systematic review Tang, 2023 |
||||||
|
Bian, 2020 |
N at baseline I: 100 C: 100
Age (mean ± SD) T: 12.2 years (range 8-14)
Gender (boys/girls) T: 96/104 |
Intervention: ortho-k Control: Single vision lenses |
12 months |
Change in axial length from baseline
Adverse events
Dropout rates |
Funding not reported, no declarations of interest reported.
One eye measured. |
Some concerns (allocation concealment unclear, blinding of participants, selective reporting) |
|
Charm, 2013 |
N at baseline I: 26 C: 26
Age (median ± SD) T: 10 years (range 8-11)
Gender (boys/girls) NR |
Intervention: ortho-k (partial reduction OK contact lenses of target 4.00 D) Control: Single vision lenses |
2 years |
Change in axial length
Adverse events
Dropout rates |
Funding: supported by a Collaborative Research Agreement between the Hong Kong Polytechnic University and Procornea Nederland BV and a Niche Area Funding from PolyU. Conflicts of interest: authors have no proprietary interest in any of the products.
Unit of analysis: child-based (right eye) |
HIGH (random sequence generation and allocation concealment unclear, blinding of participants, incomplete outcome data, selective reporting) |
|
Cho, 2012 |
N at baseline I: 51
Age (mean) T: 9 years
Gender (boys/girls) NR |
Intervention: ortho-k Control: Single vision spectacles |
24 months |
Axial length elongation
Adverse events
Dropout rates |
Funding: Menicon , NKL contactlenzen, Alcon Hong Kong, Bausch & Lomb Hong Kong, Skyview Optical Co. Ltd., Hong Kong, and Hong Kong Optical Lens Co., Ltd |
Some concerns (allocation concealment unclear, blinding of participants, selective reporting) |
|
Jakobsen, 2022 |
N at baseline I: 30 C: 30
Age (mean) T: 9.97 years (range 6-12)
Gender (boys/girls) T: 26/34 |
Intervention: ortho-k Control: Single vision lenses |
18 months |
Change in axial length from baseline
QoL
Adverse events
Dropout rates
|
Funding: grants from the Region of Southern Denmark; The Danish Eye Research Foundation; Fight for Sight, Denmark, no conflicts of interest declared.
Average of two eyes measured. |
Some concerns (allocation concealment unclear, blinding of participants, incomplete outcome data) |
|
Swarbrick, 2015 |
N at baseline I: 32
Age (mean ± SD): T: 13.4 years ± 1.9 Range 8-16
Gender (boys/girls) NR |
Intervention: ortho-k Control: Rigid gas-permeable lenses |
12 months |
Axial length elongation
Adverse events
Dropout rates |
Funding: Capricornia Conact Lens Pty Ltd |
Some concerns (allocation concealment unclear, blinding of participants, blinding of outcome assessment) |
|
Wei, 2017 |
N at baseline I: 50
Age mean na Range 8-14
Gender (boys/girls) NR |
Intervention: ortho-k Control: Single vision spectacles |
12 months |
Axial length elongation
Adverse events
Dropout rates |
|
Some concerns (allocation concealment and selective reporting unclear, blinding of participants) |
|
Individual studies |
||||||
|
Choi, 2023 |
N at baseline I: 52
Age (mean ± SD) I: 9.8 ± 1.3 C: 9.5 ± 1.4
Gender (boys/girls) T: 50/41 |
Intervention: ortho-k Control: Single vision spectacles |
24 months |
Axial length elongation
|
Funded by the Collaborative Research Fund, Seed Itd no conflicts of interest.
Data from the right eye was analysed. |
HIGH (allocation concealment, blinding, loss to follow-up, other bias) |
|
Fang, 2022 |
N at baseline I: 29
Age (mean ± SD) I: 12.5 ± 0.2 C: 13.0 ± 0.2
Gender (boys/girls) I: 17/12 C: 18/8 |
Intervention: ortho-k contact lenses Control: Single vision spectacles |
12 months |
Axial length changes
|
Supported by the Science and Technology program of Jnhua Science and Technology Bureau. No conflicts of interest.
Data from the right eye was analysed. |
HIGH (allocation concealment, blinding, loss to follow-up, other bias) |
|
Zhu, 2023 |
N at baseline I: 154
Age (mean ± SD) I: 9.18 ± 1.29 C: 9.23 ± 1.68
Gender (boys/girls) I: 70/72 C: 68/69 |
Intervention: ortho-k Control: Single vision spectacles |
13 months |
Axial length
|
Supported by Science and Technology Innovation Team of Ophthalmology of Kunming Medical University and Yunnan High-Level Talents Training Project of Famous Doctor Special Program. No competing interests. |
HIGH (allocation sequence and concealment, blinding, loss to follow-up, other bias) |
*For further details, see risk of bias table in the appendix Legenda: N = Number of patients; I = Intervention group; C = Control group; SD = Standard Deviation NR = Not Reported; T = total; na = not available
Results
Efficacy on axial length (critical)
One systematic review and three studies reported the outcome measure axial length at different follow-up durations (Choi, 2023; Fang, 2022; Tang, 2023; Zhu, 2023).
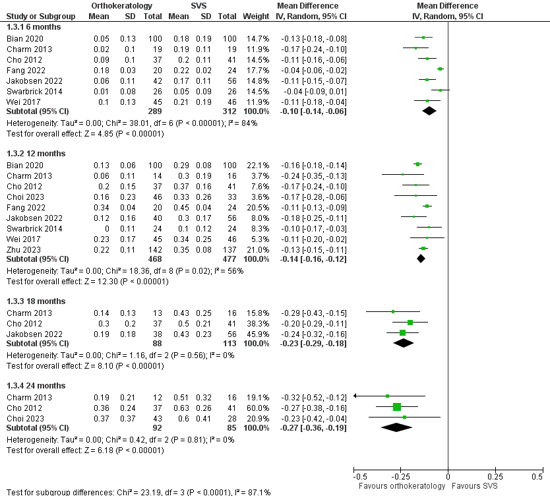
Figure 1. Efficacy on axial length in patients receiving ortho-k lenses versus regular contact lenses or spectacle lenses
Z: p-value of overall effect; df: degrees of freedom; I2: statistical heterogeneity; CI: confidence interval
Six months
Axial length elongation/change in axial length was reported at six months by Tang (2023) and Fang (2022). In total, 289 patients received ortho-k and 312 patients received single vision spectacles or lenses (Figure 1). The mean difference was -0.10 (95% CI -0.14 to -0.06), in favour of the patients that received ortho-k. This difference is considered clinically relevant.
Twelve months
Axial length elongation/change in axial length was reported at twelve months by Tang (2023), Choi (2023), Fang (2022), and Zhu (2023). In total, 468 patients received ortho-k and 477 patients received single vision spectacles or lenses (Figure 1). The mean difference was -0.14 (95% CI -0.16 to -0.12), in favour of the patients who received ortho-k. This difference is considered clinically relevant.
Eighteen months
Axial length elongation was reported at eighteen months by Tang (2023). In total, 88 patients received ortho-k and 113 patients received single vision spectacles or lenses (Figure 1). The mean difference was -0.23 (95% CI -0.29 to -0.18), in favour of the patients who received ortho-k. This difference is considered clinically relevant.
Twenty-four months
Axial length elongation was reported at twenty-four months by Choi (2023) and Tang (2023). In total, 92 patients received ortho-k and 85 patients received single vision spectacles or lenses (Figure 1). The mean difference was -0.27 (95% CI -0.36 to -0.19), in favour of the patients who received ortho-k. This difference is considered clinically relevant for the total of twenty-four months. If a closer look is taken at the different distribution of years, the greatest inhibition is seen the first year. In the second year the axial elongation reduction was for Cho (2012) 0.10 mm, in Charm (2013) 0.08 mm and in Cho (2012) 0.06 mm.
Adverse events (important)
Tang (2023) reported the outcome measure adverse events. In total, eight of the 137 patients who received ortho-k (5.8%) experienced an adverse event, compared with one of the 137 patients who received single vision spectacles (0.7%). No serious (vision-threatening) adverse events occurred in the RCTs included in the analysis. The main adverse events in the ortho-k group were reversible like corneal staining, corneal epithelial injury, and conjunctival hyperemia. The risk ratio was 4.44 (95% CI 0.97 to 20.25), in favour of the patients who received single vision spectacles. This difference is considered clinically relevant. However, when compared to other rigid gas-permeable (RGP) contact lenses, the risk of adverse events with ortho-k appears to be lower, which suggests that the increased risk may be less significant within the broader context of contact lens wear.
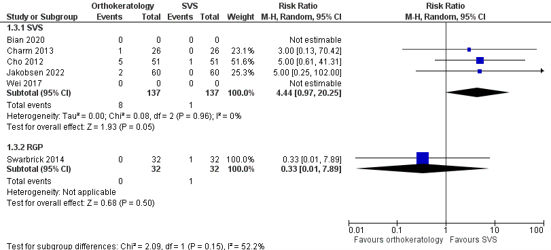
Figure 2. Adverse events in patients receiving ortho-k lenses versus regular contact lenses or spectacle lenses
Z: p-value of overall effect; df: degrees of freedom; I2: statistical heterogeneity; CI: confidence interval
One study compared ortho-k lenses to rigid gas permeable lenses (Swarbrick, 2014). None of the 32 patients who received ortho-k (0%) experienced an adverse event, compared with one of the 32 patients who received rigid gas permeable lenses (3.1%). The risk ratio was 0.33 (95% CI 0.01 to 7.89), and the risk difference was -0.03 (-0.11 to 0.05). Which means adverse events were three times less frequent to occur in favour of the patients who received ortho-k. This difference is not considered clinically relevant. The study of Li (2015) also showed that adverse events were generally non-significant and resolved quickly after treatment or discontinuation of wearing lenses, with no permanent corneal damage reported.
Compliance/adherence to therapy (important)
Tang (2023) reported the outcome measure dropout rates. In total, 63 of the 319 who received ortho-k (19.7%) dropped out, compared with 36 of the 319 patients who received single vision spectacles (11.2%). The risk ratio was 1.62 (95% CI 0.96 to 2.74), in favour of the patients who received single vision spectacles. This difference is considered clinically relevant. Acceptability of ortho-k was also evaluated through dropout rates in the study of Li (2015), which were 0–54% in the ortho-k group and 0–38% in the control group. The meta-analysis found no statistically significant difference in dropout rates between the two groups (p = 0.64), suggesting that ortho-k is generally well-accepted by children and their parents.
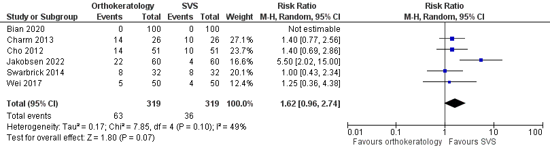
Figure 3. Dropout rates
Z: p-value of overall effect; df: degrees of freedom; I2: statistical heterogeneity; CI: confidence interval
A systematic review of the literature was performed to answer the following question(s):
What is the effect of myopia progression inhibiting ortho-k compared to regular lenses or spectacle lenses on the inhibition of progressive myopia in children aged eighteen years and under?
Table 1. PICO
| Patients | Children (aged 18 years and under) with progressive myopia |
| Intervention | Orthokeratology lenses (worn during the night) |
| Control | Regular contact lenses or spectacle lenses (worn during the day) |
| Outcomes | Short term and long term: efficacy on axial length, adverse events (for example keratitis, reduced accommodation, reduced reading vision), compliance/adherence to therapy |
| Other selection criteria | Study design: systematic reviews and randomized controlled trials |
Relevant outcome measures
The guideline panel considered efficacy on axial length as a critical outcome measure for decision-making; and adverse events, and compliance/adherence to therapy as important outcome measures for decision-making. The outcome measure refraction was not taken into account in this literature analysis, since refraction after wearing ortho-k lenses is not an accurate measure for evaluation of myopia progression over time.
A priori, the guideline panel did not define the outcome measures listed above but used the definitions used in the studies.
The guideline panel defined the following differences as a minimal clinically (patient) important difference:
- Axial length: 0.1 mm.
- Adverse events: 10% (RR < 0.9 and RR > 1.1).
- Compliance/adherence: 10% (RR < 0.9 and RR > 1.1).
Search and select (Methods)
A systematic literature search was performed by a medical information specialist using the following bibliographic databases: Embase.com and Ovid/Medline. Both databases were searched up to July 16th 2024 for systematic reviews, RCTs and observational studies. Systematic searches were completed using a combination of controlled vocabulary/subject headings (e.g., Emtree-terms, MeSH) wherever they were available and natural language keywords. The overall search strategy was derived from three primary search concepts: (1) children with progressive myopia; (2) wearing ortho-k lenses; (3) or wearing regular lenses or spectacles. Duplicates were removed using EndNote software. After deduplication a total of 945 records were imported for title/abstract screening. Studies were selected based on the criteria described in Table 1. Titles and abstracts were screened using the ASReview software version 1.6.2. The settings TF-IDF and Naïve bayes were used. One study was used as prior knowledge for inclusion (Jakobsen, 2022), and one study was used as prior knowledge for exclusion (Sánchez-García, 2024).
The first 10% of references were screened by the working group and the guideline methodologist. The remaining articles were subsequently screened by the guideline methodologist, using the following stopping rule: stop after 95 subsequent exclusions (10% of total number of references.
Initially, 106 studies were selected based on title and abstract screening using ASreview software. After reading the full text, 102 studies were excluded (see the exclusion table under the tab ‘Evidence tabellen’), and four studies were included.
- Agyekum, S., Chan, P. P., Zhang, Y., Huo, Z., Yip, B. H., Ip, P., ... & Yam, J. C. (2023). Cost-effectiveness analysis of myopia management: A systematic review. Frontiers in Public Health, 11, 1093836.
- Bian, S., Liu, H., & Lin, J. (2020). A randomized-controlled clinical study of one-year outcome between orthokeratology contact lens wear and glasses wear in myopic children. Chinese Journal of Experimental Ophthalmology, 121-127.
- Brennan NA, Toubouti YM, Cheng X, Bullimore MA. Efficacy in myopia control. Prog Retin Eye Res. 2021 Jul;83:100923. doi: 10.1016/j.preteyeres.2020.100923. Epub 2020 Nov 27. PMID: 33253901.
- Bullimore MA, Sinnott LT, Jones-Jordan LA. The risk of microbial keratitis with overnight corneal reshaping lenses. Optom Vis Sci. 2013 Sep;90(9):937-44. doi: 10.1097/OPX.0b013e31829cac92. PMID: 23892491.
- Bullimore MA, Brennan NA. Efficacy in myopia control-The impact of rebound. Ophthalmic Physiol Opt. 2025 Jan;45(1):100-110. doi: 10.1111/opo.13403. Epub 2024 Oct 8. PMID: 39377894.
- Charm J, Cho P. High myopia-partial reduction ortho-k: a 2-year randomized study. Optom Vis Sci. 2013 Jun;90(6):530-9. doi: 10.1097/OPX.0b013e318293657d. PMID: 23645372.
- Cheung SW, Cho P. Validity of axial length measurements for monitoring myopic progression in orthokeratology. Invest Ophthalmol Vis Sci. 2013 Mar 5;54(3):1613-5. doi: 10.1167/iovs.12-10434. PMID: 23361504.
- Cho P, Cheung SW, Edwards M. The Longitudinal Orthokera-tology Research In Children (LORIC) in Hong Kong. A pilot study on refractive changes and myopic control. Curr Eye Res. 2005;30:71–80.
- Cho P, Cheung SW. Retardation of myopia in Orthokeratology (ROMIO) study: a 2-year randomized clinical trial. Invest Ophthalmol Vis Sci. 2012 Oct 11;53(11):7077-85. doi: 10.1167/iovs.12-10565. PMID: 22969068.
- Cho, P., & Cheung, S. W. (2017). Discontinuation of orthokeratology on eyeball elongation (DOEE). Contact Lens and Anterior Eye, 40(2), 82-87.
- Choi KY, Cheung JKW, Wong GTK, Li PH, Chan SSH, Lam TC, Chan HHL. Myopia Control Efficacy and Long-Term Safety of a Novel Orthokeratology Lens (MESOK Study)-A Randomized Controlled Clinical Trial Combining Clinical and Tear Proteomics Data. J Clin Med. 2023 Apr 29;12(9):3210. doi: 10.3390/jcm12093210. PMID: 37176650; PMCID: PMC10179394.
- Fang J, Huang Z, Long Y, Zhu M, Wu Q, Chen X, Xv W, Du C. Retardation of Myopia by Multifocal Soft Contact Lens and Orthokeratology: A 1-Year Randomized Clinical Trial. Eye Contact Lens. 2022 Aug 1;48(8):328-334. doi: 10.1097/ICL.0000000000000911. Epub 2022 Jun 3. PMID: 35877183; PMCID: PMC9298149.
- González-Mesa, A., Villa-Collar, C., Lorente-Velázquez, A., & Nieto-Bona, A. (2013). Anterior Segment Changes Produced in Response to Long-Term Overnight Orthokeratology. Current Eye Research, 38(8), 862–870. https://doi.org/10.3109/02713683.2013.790977
- Hemert van, D.J., Sehayian, A., Polling, J.R., Tideman, J.W.L., Kievit, W., & Klaver, C.C.W. (2025). Evaluating costs and utilities of myopia across treatment scenarios in The Netherlands. Acta Opthalmologica
- Hiraoka T, Sekine Y, Okamoto F, Mihashi T, Oshika T. Safety and efficacy following 10-years of overnight orthokeratology for myopia control. Ophthalmic Physiol Opt. 2018 May;38(3):281-289. doi: 10.1111/opo.12460. PMID: 29691927.
- Hu, P., Zhao, Y., Chen, D., & Ni, H. (2021). The safety of orthokeratology in myopic children and analysis of related factors. Contact Lens and Anterior Eye, 44(1), 89-93.
- Jakobsen, T. M., Høeg, K. B., & Møller, F. (2025). Myopia control with orthokeratology lenses. A 3‐year follow‐up study including a cross‐over design: Clinical study Of Near‐sightedness; TReatment with Orthokeratology Lenses 2 (CONTROL2 study). Acta Ophthalmologica, 103(2), 186-195.
- Jung, S., Eom, Y., Song, J. S., Hyon, J. Y., & Jeon, H. S. (2024). Clinical Features and Visual Outcome of Infectious Keratitis Associated with Orthokeratology Lens in Korean Pediatric Patients. Korean journal of ophthalmology: KJO, 38(5), 399.
- Lai W, Diao C, Li H, Zhang Y, Jia Y, Wu X. Three optical intervention methods for low myopia control in children: a one-year follow-up study. BMC Ophthalmol. 2024 Jul 31;24(1):319. doi: 10.1186/s12886-024-03598-0. Erratum in: BMC Ophthalmol. 2024 Aug 27;24(1):377. doi: 10.1186/s12886-024-03638-9. PMID: 39085810; PMCID: PMC11293150.
- Li, S. M., Kang, M. T., Wu, S. S., Liu, L. R., Li, H., Chen, Z., & Wang, N. (2016). Efficacy, safety And acceptability of orthokeratology on slowing axial elongation in myopic children by meta-analysis. Current eye research, 41(5), 600-608.
- Lin W, Li N, Liu J, Zhang B, Wei R. Relative corneal refractive power shift and inter-eye differential axial growth in children with myopic anisometropia treated with bilateral orthokeratology. Graefes Arch Clin Exp Ophthalmol. 2024 Apr;262(4):1203-1213. doi: 10.1007/s00417-023-06301-z. Epub 2023 Nov 6. PMID: 37930444; PMCID: PMC10994874.
- Lu, W., Ji, R., Jiang, D., Shi, L., Ding, W., Tian, Y., ... & Leng, L. (2024). Different efficacy in myopia control: comparison between orthokeratology and defocus-incorporated multiple segment lenses. Contact Lens and Anterior Eye, 47(2), 102122.
- Morgan, P. (2016). Orthokeratology: Postcard from the Netherlands.
- Morgan, P. B., Efron, N., Woods, C. A., Santodomingo-Rubido, J., & International Contact Lens Prescribing Survey Consortium. (2019). International survey of orthokeratology contact lens fitting. Contact Lens and Anterior Eye, 42(4), 450-454.\
- Queirós, A., Pinheiro, I., & Fernandes, P. (2025). Peripheral Defocus in Orthokeratology Myopia Correction: Systematic Review and Meta-Analysis. Journal of Clinical Medicine, 14(3), 662. https://doi.org/10.3390/jcm14030662
- Santodomingo-Rubido J, Cheung SW, Villa-Collar C; ROMIO/MCOS/TO-SEE Groups. A new look at the myopia control efficacy of orthokeratology. Cont Lens Anterior Eye. 2024 Oct;47(5):102251. doi: 10.1016/j.clae.2024.102251. Epub 2024 Jun 21. PMID: 38906728.
- Sánchez-García A, Molina-Martin A, Ariza-Gracia MÁ, Piñero DP. Analysis of Treatment Discontinuation in Orthokeratology: Studying Efficacy, Safety, and Patient Adherence Over Six Months. Eye Contact Lens. 2024 Sep 1;50(9):395-400. doi: 10.1097/ICL.0000000000001110. Epub 2024 Jun 18. PMID: 38886923.
- Swarbrick HA. Orthokeratology review and update. Clin Exp Optom. 2006 May;89(3):124-43. doi: 10.1111/j.1444-0938.2006.00044.x. PMID: 16637967.
- Swarbrick HA, Alharbi A, Watt K, Lum E, Kang P. Myopia control during orthokeratology lens wear in children using a novel study design. Ophthalmology. 2015 Mar;122(3):620-30. doi: 10.1016/j.ophtha.2014.09.028. Epub 2014 Nov 6. PMID: 25439432.
- Santodomingo-Rubido, J., Cheung, S. W., & Villa-Collar, C. (2024). A new look at the myopia control efficacy of orthokeratology. Contact Lens and Anterior Eye, 47(5), 102251.
- Santodomingo-Rubido, Jacinto PhD, FAAO1,*; Villa-Collar, César PhD, FAAO2,3; Gutiérrez-Ortega, Ramón PhD, MD2; Sugimoto, Keiji BSc1; Nishimura, Sachiko BSc, MPhil1; Newman, Steve1. Eleven years of orthokeratology contact lens wear for slowing myopia progression in children. Optometry and Vision Science ():10.1097/OPX.0000000000002255, April 21, 2025. | DOI: 10.1097/OPX.0000000000002255.
- Stapleton, F., Keay, L., Edwards, K., Naduvilath, T., Dart, J. K., Brian, G., & Holden, B. A. (2008). The incidence of contact lens–related microbial keratitis in Australia. Ophthalmology, 115(10), 1655-1662.
- Sun, Y., Wang, L., Gao, J., Yang, M., & Zhao, Q. (2017). Influence of overnight orthokeratology on corneal surface shape and optical quality. Journal of Ophthalmology, 2017(1), 3279821.
- Tang T, Lu Y, Li X, Zhao H, Wang K, Li Y, Zhao M. Comparison of the long-term effects of atropine in combination with Orthokeratology and defocus incorporated multiple segment lenses for myopia control in Chinese children and adolescents. Eye (Lond). 2024 Jun;38(9):1660-1667. doi: 10.1038/s41433-024-02987-5. Epub 2024 Feb 28. PMID: 38418604; PMCID: PMC11156845.
- Tang K, Si J, Wang X, Lu X, Bi H. Orthokeratology for Slowing Myopia Progression in Children: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Eye Contact Lens. 2023 Sep 1;49(9):404-410. doi: 10.1097/ICL.0000000000001006. Epub 2023 Jun 6. PMID: 37284749.
- Tsai HR, Wang JH, Huang HK, Chen TL, Chen PW, Chiu CJ. Efficacy of atropine, orthokeratology, and combined atropine with orthokeratology for childhood myopia: A systematic review and network meta-analysis. J Formos Med Assoc. 2022 Dec;121(12):2490-2500. doi: 10.1016/j.jfma.2022.05.005. Epub 2022 Jun 7. PMID: 35688780.
- Wang, D. D., & Zhou, P. (2025). Myopia: Pathogenesis and Intervention.
- Wei, S., Li, S., Sun, Y., Kang, M., Wang, J., Ran, A., & Zhang, F. (2017). Effects of orthokeratology lenses on ocular biometric parameters in children with low to moderate myopia. Chin J Optom Ophthalmol Vis Sci, 19, 548-553.
- Xu S, Li Z, Zhao W, Zheng B, Jiang J, Ye G, Feng Z, Long W, He L, He M, Hu Y, Yang X. Effect of atropine, orthokeratology and combined treatments for myopia control: a 2-year stratified randomised clinical trial. Br J Ophthalmol. 2023 Nov 22;107(12):1812-1817. doi: 10.1136/bjo-2022-321272. PMID: 36229177.
- Zhang Y, Sun X, Chen Y. Controlling anisomyopia in children by orthokeratology: A one-year randomised clinical trial. Cont Lens Anterior Eye. 2023 Feb;46(1):101537. doi: 10.1016/j.clae.2021.101537. Epub 2021 Nov 14. PMID: 34785153.
- Zhou Y, Li H, Hao J, Pan W, Yang Z, Lan W. The efficacy of orthokeratology lenses with smaller back optic zone diameter in myopia control. A meta-analysis. Ophthalmic Physiol Opt. 2024 Sep;44(6):1215-1223. doi: 10.1111/opo.13347. Epub 2024 Jun 16. PMID: 38881171.
- Zhou J, Xie P, Wang D, Guo X, Yang L. [The long-term clinical effects of orthokeratology in high myopia children]. Zhonghua Yan Ke Za Zhi. 2015 Jul;51(7):515-9. Chinese. PMID: 26310255.
- Zhu Q, Yin J, Li X, Hu M, Xue L, Zhang J, Zhou Y, Zhang X, Zhu Y, Zhong H. Effects of Long-Term Wear and Discontinuation of Orthokeratology Lenses on the Eyeball Parameters in Children with Myopia. Int J Med Sci. 2023 Jan 1;20(1):50-56. doi: 10.7150/ijms.79496. PMID: 36619230; PMCID: PMC9812803.
Risk of bias tabel
|
Study reference
(first author, publication year) |
Was the allocation sequence adequately generated?
Definitely yes Probably yes Probably no Definitely no |
Was the allocation adequately concealed?
Definitely yes Probably yes Probably no Definitely no |
Blinding: Was knowledge of the allocated interventions adequately prevented?
Were patients/healthcare providers/data collectors/outcome assessors/data analysts blinded?
Definitely yes Probably yes Probably no Definitely no |
Was loss to follow-up (missing outcome data) infrequent?
Definitely yes Probably yes Probably no Definitely no |
Are reports of the study free of selective outcome reporting?
Definitely yes Probably yes Probably no Definitely no |
Was the study apparently free of other problems that could put it at a risk of bias?
Definitely yes Probably yes Probably no Definitely no |
Overall risk of bias If applicable/necessary, per outcome measure
LOW Some concerns HIGH
|
|
Choi, 2023 |
Definitely yes
Reason: The randomization was performed using a computer-generated random sequence. |
Probably no
Reason: No information. |
Definitely no
Reason: Only experimenters performing efficacy and safety assessments during follow-up visits were masked. |
Definitely no
Reason: Loss-to-follow-up was more than 10% in both groups. |
Definitely yes
Reason: All relevant outcomes were reported. |
Definitely no
Reason: Subject allocation ratio. |
HIGH
|
|
Fang, 2022 |
Definitely yes
Reason: An online resource was used to generate the random group allocation sequence. |
Probably no
Reason: No information. |
Definitely no
Reason: Participants were not masked, one investigator was unmasked for enrolling the patients, generating the random allocation sequence, grouping, lens fitting, clinical aftercare, evaluating lens condition and recording data. The investigating optometrists were masked. |
Definitely no
Reason: Loss-to-follow-up was more than 10% in the intervention group, and less than 10% in the control group. |
Probably yes
Reason: No information in Methods section about reported outcome measures. |
Definitely no
Reason: Difference in baseline genders, the study is associated with inability to measure the refraction of the Ortho-K group, relatively short research cycle of 1 year, relatively small sample size. |
HIGH |
|
Zhu, 2023 |
No information |
Probably no
Reason: No information. |
Definitely no
Reason: The study was not double blinded. |
Definitely no
Reason: Loss-to-follow-up was less than 10% in the intervention group, and more than 10% in the control group. |
Definitely yes
Reason: All relevant outcomes were reported. |
Definitely no
Reason: Duration of 12 months, no long-term withdrawal period, further investigation needed to confirm rebound effect, anxiety among Chinese parents/unwillingness to join the investigation. |
HIGH |
Exclusietabel
|
Reference |
Reason for exclusion |
|
BIAN, S., LIU, H., & LIN, J. (2020). A randomized-controlled clinical study of one-year outcome between orthokeratology contact lens wear and glasses wear in myopic children. Chinese Journal of Experimental Ophthalmology, 121-127. |
Included in SR |
|
Bullimore MA, Liu M. Efficacy of the Euclid orthokeratology lens in slowing axial elongation. Cont Lens Anterior Eye. 2023 Oct;46(5):101875. doi: 10.1016/j.clae.2023.101875. Epub 2023 Jun 24. PMID: 37365049. |
Not conform PICO: untreated control group |
|
Cho P, Cheung SW. Retardation of myopia in Orthokeratology (ROMIO) study: a 2-year randomized clinical trial. Invest Ophthalmol Vis Sci. 2012 Oct 11;53(11):7077-85. doi: 10.1167/iovs.12-10565. PMID: 22969068. |
Included in SR |
|
Cui Y, Li L, Wu Q, Zhao J, Chu H, Yu G, Wei W. Myopia correction in children: a meta-analysis. Clin Invest Med. 2017 Jun 26;40(3):E117-E126. doi: 10.25011/cim.v40i3.28391. PMID: 28653613. |
Not conform PICO: wrong outcome measures |
|
Guan M, Zhao W, Geng Y, Zhang Y, Ma J, Chen Z, Peng M, Li Y. Changes in axial length after orthokeratology lens treatment for myopia: a meta-analysis. Int Ophthalmol. 2020 Jan;40(1):255-265. doi: 10.1007/s10792-019-01167-9. Epub 2020 Jan 8. PMID: 31916062. |
Observational studies included in SR |
|
Huang J, Wen D, Wang Q, McAlinden C, Flitcroft I, Chen H, Saw SM, Chen H, Bao F, Zhao Y, Hu L, Li X, Gao R, Lu W, Du Y, Jinag Z, Yu A, Lian H, Jiang Q, Yu Y, Qu J. Efficacy Comparison of 16 Interventions for Myopia Control in Children: A Network Meta-analysis. Ophthalmology. 2016 Apr;123(4):697-708. doi: 10.1016/j.ophtha.2015.11.010. Epub 2016 Jan 27. PMID: 26826749. |
More recent SR available |
|
Jakobsen TM, Møller F. Control of myopia using orthokeratology lenses in Scandinavian children aged 6 to 12 years. Eighteen-month data from the Danish Randomized Study: Clinical study Of Near-sightedness; TReatment with Orthokeratology Lenses (CONTROL study). Acta Ophthalmol. 2022 Mar;100(2):175-182. doi: 10.1111/aos.14911. Epub 2021 Jul 7. PMID: 34233094; PMCID: PMC9292027. |
CONTROL Study included in SR. |
|
Jakobsen TM, Søndergaard AP, Møller F. Peripheral refraction, relative peripheral refraction, and axial growth: 18-month data from the randomised study-Clinical study Of Near-sightedness; TReatment with Orthokeratology Lenses (CONTROL study). Acta Ophthalmol. 2023 Feb;101(1):e69-e80. doi: 10.1111/aos.15217. Epub 2022 Aug 8. PMID: 35941831; PMCID: PMC10087546. |
CONTROL Study included in SR, wrong outcome measures. |
|
Koffler BH, Sears JJ. Myopia control in children through refractive therapy gas permeable contact lenses: is it for real? Am J Ophthalmol. 2013 Dec;156(6):1076-1081.e1. doi: 10.1016/j.ajo.2013.04.039. PMID: 24238200. |
Wrong study design: literature review |
|
Lau JK, Wan K, Cho P. Orthokeratology lenses with increased compression factor (OKIC): A 2-year longitudinal clinical trial for myopia control. Cont Lens Anterior Eye. 2023 Feb;46(1):101745. doi: 10.1016/j.clae.2022.101745. Epub 2022 Aug 19. PMID: 35995721. |
Not conform PICO: no control group |
|
Lawrenson JG, Shah R, Huntjens B, Downie LE, Virgili G, Dhakal R, Verkicharla PK, Li D, Mavi S, Kernohan A, Li T, Walline JJ. Interventions for myopia control in children: a living systematic review and network meta-analysis. Cochrane Database Syst Rev. 2023 Feb 16;2(2):CD014758. doi: 10.1002/14651858.CD014758.pub2. PMID: 36809645; PMCID: PMC9933422. |
Methodological limitations: no individual study data reported |
|
Li H, Xu Y, Li L. Efficacy and Safety of Orthokeratology Lenses for the Management of Adolescent Myopia: A Meta-Analysis. Altern Ther Health Med. 2023 Oct;29(7):172-177. PMID: 37471657. |
SR which included observational studies, no RCTs |
|
Li SM, Kang MT, Wu SS, Liu LR, Li H, Chen Z, Wang N. Efficacy, Safety and Acceptability of Orthokeratology on Slowing Axial Elongation in Myopic Children by Meta-Analysis. Curr Eye Res. 2016 May;41(5):600-8. doi: 10.3109/02713683.2015.1050743. Epub 2015 Aug 3. PMID: 26237276. |
More recent SR available |
|
Lin W, Li N, Liu J, Zhang B, Wei R. Relative corneal refractive power shift and inter-eye differential axial growth in children with myopic anisometropia treated with bilateral orthokeratology. Graefes Arch Clin Exp Ophthalmol. 2024 Apr;262(4):1203-1213. doi: 10.1007/s00417-023-06301-z. Epub 2023 Nov 6. PMID: 37930444; PMCID: PMC10994874. |
Not conform PICO: wrong population (anisometropia) |
|
Logan NS, Bullimore MA. Optical interventions for myopia control. Eye (Lond). 2024 Feb;38(3):455-463. doi: 10.1038/s41433-023-02723-5. Epub 2023 Sep 22. PMID: 37740053; PMCID: PMC10858277. |
Book |
|
Lu W, Ji R, Jiang D, Shi L, Ding W, Tian Y, Zhao C, Leng L. Different efficacy in myopia control: Comparison between orthokeratology and defocus-incorporated multiple segment lenses. Cont Lens Anterior Eye. 2024 Apr;47(2):102122. doi: 10.1016/j.clae.2024.102122. Epub 2024 Jan 13. PMID: 38220497. |
Wrong study design: no randomization |
|
Lyu T, Wang L, Zhou L, Qin J, Ma H, Shi M. Regimen Study of High Myopia-Partial Reduction Orthokeratology. Eye Contact Lens. 2020 May;46(3):141-146. doi: 10.1097/ICL.0000000000000629. PMID: 31361656. |
Not conform PICO: two intervention groups |
|
Meng Z, Shuo G, Guohu D, Wei Z, Jingyi L, Yuanchao C, Zhaodong L, Changhong Y. Difference in the effect of orthokeratology on slowing teen myopia with different years of follow-up. J Fr Ophtalmol. 2022 Sep;45(7):718-727. doi: 10.1016/j.jfo.2022.02.003. Epub 2022 May 13. PMID: 35577700. |
Full text not available. More recent SR available. |
|
Sarkar S, Khuu S, Kang P. A systematic review and meta-analysis of the efficacy of different optical interventions on the control of myopia in children. Acta Ophthalmol. 2024 May;102(3):e229-e244. doi: 10.1111/aos.15746. Epub 2023 Aug 14. PMID: 37578349. |
Included studies comparable to SR |
|
Shi JH, Zhao YP, Liu G, Huang XY, Lang LL, Jia WC, Chen JL. Changes of retinal vessel density in low to moderate myopic eyes with orthokeratology evaluated by optical coherence tomography angiography. Int J Ophthalmol. 2023 Sep 18;16(9):1512-1520. doi: 10.18240/ijo.2023.09.19. PMID: 37724280; PMCID: PMC10475625. |
Wrong study design: observational study |
|
Si JK, Tang K, Bi HS, Guo DD, Guo JG, Wang XR. Orthokeratology for myopia control: a meta-analysis. Optom Vis Sci. 2015 Mar;92(3):252-7. doi: 10.1097/OPX.0000000000000505. PMID: 25599338. |
More recent SR available |
|
Sun Y, Xu F, Zhang T, Liu M, Wang D, Chen Y, Liu Q. Orthokeratology to control myopia progression: a meta-analysis. PLoS One. 2015 Apr 9;10(4):e0124535. doi: 10.1371/journal.pone.0124535. Erratum in: PLoS One. 2015 Jun 11;10(6):e0130646. doi: 10.1371/journal.pone.0130646. PMID: 25855979; PMCID: PMC4391793. |
More recent SR available |
|
Swarbrick HA, Alharbi A, Watt K, Lum E, Kang P. Myopia control during orthokeratology lens wear in children using a novel study design. Ophthalmology. 2015 Mar;122(3):620-30. doi: 10.1016/j.ophtha.2014.09.028. Epub 2014 Nov 6. PMID: 25439432. |
Included in SR |
|
TIAN, Q., LIU, X. D., & WAN, J. M. (2023). Comparison of the effect between night-wearing orthokeratology lens and frame glasses on the treatment of juvenile myopia. International Eye Science, 660-664. |
Wrong study design: no randomization |
|
VanderVeen DK, Kraker RT, Pineles SL, Hutchinson AK, Wilson LB, Galvin JA, Lambert SR. Use of Orthokeratology for the Prevention of Myopic Progression in Children: A Report by the American Academy of Ophthalmology. Ophthalmology. 2019 Apr;126(4):623-636. doi: 10.1016/j.ophtha.2018.11.026. Epub 2018 Nov 23. PMID: 30476518. |
Wrong study design: report |
|
Walline JJ, Lindsley K, Vedula SS, Cotter SA, Mutti DO, Twelker JD. Interventions to slow progression of myopia in children. Cochrane Database Syst Rev. 2011 Dec 7;(12):CD004916. doi: 10.1002/14651858.CD004916.pub3. Update in: Cochrane Database Syst Rev. 2020 Jan 13;1:CD004916. doi: 10.1002/14651858.CD004916.pub4. PMID: 22161388; PMCID: PMC4270373. |
More recent SR available |
|
Walline JJ, Lindsley KB, Vedula SS, Cotter SA, Mutti DO, Ng SM, Twelker JD. Interventions to slow progression of myopia in children. Cochrane Database Syst Rev. 2020 Jan 13;1(1):CD004916. doi: 10.1002/14651858.CD004916.pub4. PMID: 31930781; PMCID: PMC6984636. |
More recent SR available |
|
Wei, S., LI, S., Sun, Y., Kang, M., Meng, B., Ran, A., ... & Wang, N. (2017). A randomized controlled clinical trial on the effects of wearing orthokeratology and spectacles on ocular peripheral refraction in myopic children. Chinese Journal of Experimental Ophthalmology, 930-935. |
Included in SR |
|
Wen D, Huang J, Chen H, Bao F, Savini G, Calossi A, Chen H, Li X, Wang Q. Efficacy and Acceptability of Orthokeratology for Slowing Myopic Progression in Children: A Systematic Review and Meta-Analysis. J Ophthalmol. 2015;2015:360806. doi: 10.1155/2015/360806. Epub 2015 Jun 11. PMID: 26221539; PMCID: PMC4475749. |
More recent SR available |
|
Xiao J, Pan X, Hou C, Wang Q. Changes in Subfoveal Choroidal Thickness after Orthokeratology in Myopic Children: A Systematic Review and Meta-Analysis. Curr Eye Res. 2024 Jul;49(7):683-690. doi: 10.1080/02713683.2024.2310618. Epub 2024 Feb 2. PMID: 38305231. |
Observational studies included in SR |
|
Yang G, Tang S, Li Q, Xu L, Liu S. The Effect of Orthokeratology Lens on the Axial Length of Globe in Children with Myopia in Asia. J Coll Physicians Surg Pak. 2022 Nov;32(11):1459-1464. doi: 10.29271/jcpsp.2022.11.1459. PMID: 36377015. |
Observational studies included in SR |
|
Zhang G, Jiang J, Qu C. Myopia prevention and control in children: a systematic review and network meta-analysis. Eye (Lond). 2023 Nov;37(16):3461-3469. doi: 10.1038/s41433-023-02534-8. Epub 2023 Apr 27. PMID: 37106147; PMCID: PMC10630522. |
Not conform PICO: Control not specified |
|
Zhang Y, Sun X, Chen Y. Controlling anisomyopia in children by orthokeratology: A one-year randomised clinical trial. Cont Lens Anterior Eye. 2023 Feb;46(1):101537. doi: 10.1016/j.clae.2021.101537. Epub 2021 Nov 14. PMID: 34785153. |
More recent SR available |
|
Zhang, Z. J., HU, Q. Z., Shu, M., Zhang, L. L., & Lan, K. (2018). Efficacy and safety of orthokeratology to control myopia in Asia children: A Meta-analysis. International Eye Science, 248-251. |
Article in Chinese |
Beoordelingsdatum en geldigheid
Publicatiedatum : 26-08-2026
Beoordeeld op geldigheid : 26-08-2026
Het cluster Oog is als houder van deze richtlijn de eerstverantwoordelijke voor de actualiteit van deze richtlijn.
Algemene gegevens
De ontwikkeling van deze richtlijn werd ondersteund door het Kennisinstituut van de Federatie Medisch Specialisten (www.demedischspecialist.nl/kennisinstituut) en werd gefinancierd door de Stichting Kwaliteitsgelden Medisch Specialisten (SKMS). Patiëntenparticipatie bij deze richtlijn werd medegefinancierd uit de Kwaliteitsgelden Patiënten Consumenten (SKPC) binnen het programma Kwaliteit, Inzicht en Doelmatigheid in de medisch specialistische Zorg (KIDZ). De financier heeft geen enkele invloed gehad op de inhoud van de richtlijnmodule.
Samenstelling werkgroep
Voor het ontwikkelen van de richtlijnmodule is in 2023 een multidisciplinaire werkgroep ingesteld, bestaande uit vertegenwoordigers van alle relevante specialismen (zie hiervoor de Samenstelling van de werkgroep) die betrokken zijn bij de zorg voor patiënten met kinderen met progressieve myopie.
Werkgroep
Dr. M. (Martha) Tjon-Fo-Sang, oogarts, Het Oogziekenhuis Rotterdam, Rotterdam (voorzitter), NOG
Prof. Dr. C.C.W. (Caroline) Klaver, oogarts, Erasmusmc, Rotterdam & Radboudumc, Nijmegen, NOG
Dr. J.W.L. (Willem) Tideman, oogarts, Martini Ziekenhuis Groningen; Post-doc, Erasmusmc, Rotterdam, NOG
Prof. Dr. M.M. (Mies) van Genderen, oogarts, Bartiméus, Zeist & UMC Utrecht, Utrecht, NOG,
Dhr. G.J. (Gerlof) du Bois, patiëntvertegenwoordiger, Voorzitter patiëntengroep
Hoge Myopie (Oogvereniging)
Mevr. K.E.M. (Karin) van Hees – Teuben, optometrist, Lens Optiek, OVN
Drs. D. (Daisy) Laan, orthoptist en optometrist, Flevoziekenhuis, Almere, NVVO
Drs. H. (Marieke) Schut, gedragskundige, Bartimeus, Utrecht, NVO
Klankbordgroep
Drs. V. (Vasanthi) Iyer, arts M+G/jeugdarts, AJN Jeugdartsen Nederland, AJN
Mevr. E. (Esmee) Bennen, optometrist, Visser Contactlenzen, OVN
Mevr. C.W.M. (Corlien) Stoop, orthoptist, Catharina ziekenhuis, Eindhoven, NVVO
Met ondersteuning van
Dr. R. (Romy) Zwarts-van de Putte, adviseur, Kennisinstituut van de Federatie Medisch Specialisten
Drs. E.R.L. (Evie) Verweg, junior adviseur, Kennisinstituut van de Federatie Medisch Specialisten
Drs. B.L. (Babette) Gal-de Geest, adviseur, Kennisinstituut van de Federatie Medisch Specialisten
A. (Alies) Oost, medisch informatiespecialist, Kennisinstituut van de Federatie Medisch Specialisten
Belangenverklaringen
Een overzicht van de belangen van werkgroepleden en het oordeel over het omgaan met eventuele belangen vindt u in onderstaande tabel. De ondertekende belangenverklaringen zijn op te vragen bij het secretariaat van het Kennisinstituut van de Federatie Medisch Specialisten via secretariaat@kennisinstituut.nl.
Gemelde (neven)functies en belangen werkgroep
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Intellectuele belangen en reputatie |
Overige belangen |
Datum |
Restrictie |
|
Tjon Fo Sang |
Oogarts, Oogziekenhuis Rotterdam |
Geen |
nvt |
nvt |
nvt |
nvt |
nvt |
29-10-2023 |
Geen restricties |
|
Van Genderen |
Oogarts, hoogleraar oogheelkunde, Stichting Bartiméus, o,6 FTE, betaald |
Adviescomissies: |
nvt |
nvt |
ja, gefinancierd door Bartiméus Fonds, ZonMW, Wishdom Foundation) |
nvt |
nvt |
17-10-2023 |
Geen restricties |
|
Laan |
Optometrist en Orthoptist bij het Flevoziekenhuis in Almere |
Bestuurslid Nederlandse Vereniging van Orthoptisten |
nvt |
nvt |
nvt |
nvt |
nvt |
4-10-2023 |
Geen restricties |
|
Du Bois |
Voorzitter patiëntengroep Hoge Myopie - Oogvereniging |
Geen |
nvt |
nvt |
nvt |
nvt |
nvt |
28-10-2023 |
Geen restricties |
|
Tideman |
Oogarts martini ziekenhuis Groningen |
Geen andere werkzaamheden |
nvt |
nvt |
Topcon heeft Generation R gesponsord om de groeicurve te kunnen gebruiken |
We hebben de groeicurve ontwikkeld voor goed myopie management. Deze zijn open source beschikbaar in Acta Ophthalmologica |
nvt |
31-10-2023 |
Geen restricties |
|
Van Hees-Teuben |
Optometrist, Lens Optiek |
Auteur voor een aantal vakbladen (tegen auteursvergoeding) |
nvt |
nvt |
nvt |
nvt |
nvt |
7-11-2023 |
Geen restricties |
|
Schut |
Gedragsdeskundige bij Bartiméus (gedragsdeskundige kind & jeugd, 24 uur per week, betaald) |
Supervisor en docent bij RINO Utrecht bij OG-opleiding en GZ-opleiding (opleidingsinstelling, gemiddeld 2 uur per week, betaald) |
nvt |
nvt |
nvt |
nvt |
nvt |
5-12-2023 |
Geen restricties |
|
Klaver |
Hoogleraar OHK Erasmus MC 0,6 fte |
Sporadisch advies functies farmaceutische industrie t.b.v. (maculadegeneratie) |
nvt |
nvt |
Epidemiologie myopie |
Word regelmating uitgenodigd voor internationale congressen als Key Opinion Leader in het myopie veld. |
nvt |
16-7-2026 |
Geen restricties |
Gemelde (neven)functies en belangen klankbordgroep
|
Naam |
Hoofdfunctie |
Nevenwerkzaamheden |
Persoonlijke financiële belangen |
Persoonlijke relaties |
Extern gefinancierd onderzoek |
Intellectuele belangen en reputatie |
Overige belangen |
Datum |
Restrictie |
|
Iyer |
AJN Ambassadeur Visus Inzicht (onbetaald) Officieel werkzaam als instituutsopleider bij TNO 0,5 fte |
Lobbywerkzaamheden in huidige rol van voorzitter Stichting Netwerk Zicht op Buiten;; het netwerk houdt zich bezig met de gevolgen voor de fysieke gezondheid vanwege o.a. leefstijl/de toegenomen schermgebruik bij de jeugd. |
Geen financieel voordeel |
nee |
Publicatiekosten beschikbaar gesteld; verder niet gefinancierd |
Boegbeeldfunctie bij beroepsvereniging, AJN ambassadeur Visus Inzicht en voorzitter van de Stichting Netwerk Zicht op Buiten |
nee |
24-10-2025 |
Geen restricties |
|
Stoop |
Orthopist, Catharina ziekenhuis Eindhoven |
Per september 2025 (na het afronden van de module myopie remmende glazen) toegetreden tot de medical advice board van Hoya (brillenglazen fabrikant). Tot op heden is er een bijeenkomst geweest, De bedoeling van de bijeenkomst (maximaal 2 á 3) is om de kennis van het behandelen van de myopie tot een hoger niveau te brengen in Nederland. En hoe zorg je dat alle spelers op de markt (orthoptist, optometrist, opticien, contactlensspecilialist en oogarts) beter samenwerken tbv de patienten. Onkosten vergoeding 75 euro per uur en reiskosten 0.21 euro/km.
|
nvt |
nvt |
nvt |
nvt |
nvt |
13-7-2026 |
Geen restricties |
|
Bennen |
Optometrist, Visser Contactlenzen |
Geen |
nvt |
nvt |
nvt |
nvt |
nvt |
13-1-2025 |
Geen restricties |
Inbreng patiëntenperspectief
Inbreng patiëntenperspectief
De werkgroep besteedde aandacht aan het patiëntenperspectief door het uitnodigen van de Oogvereniging voor de invitational conference en een afgevaardigde vanuit deze patiëntenorganisatie in de werkgroep. De verkregen input is meegenomen bij het opstellen van de uitgangsvragen, de keuze voor de uitkomstmaten en bij het opstellen van de overwegingen van de verschillende richtlijnmodules. De conceptrichtlijn is tevens voor commentaar voorgelegd aan de Oogvereniging en de eventueel aangeleverde commentaren zijn bekeken en verwerkt.
Kwalitatieve raming van mogelijke financiële gevolgen in het kader van de Wkkgz
Bij de richtlijnmodule voerde de werkgroep conform de Wet kwaliteit, klachten en geschillen zorg (Wkkgz) een kwalitatieve raming uit om te beoordelen of de aanbevelingen mogelijk leiden tot substantiële financiële gevolgen. Bij het uitvoeren van deze beoordeling is de richtlijnmodule op verschillende domeinen getoetst (zie het stroomschema bij Werkwijze).
|
Module |
Uitkomst raming |
Toelichting |
|
geen financiële gevolgen |
Hoewel uit de toetsing volgt dat de aanbeveling(en) breed toepasbaar zijn (>40.000 patiënten), volgt uit de toetsing dat [het overgrote deel (±90%) van de zorgaanbieders en zorgverleners al aan de norm voldoet OF het geen nieuwe manier van zorgverlening of andere organisatie van zorgverlening betreft, het geen toename in het aantal in te zetten voltijdsequivalenten aan zorgverleners betreft en het geen wijziging in het opleidingsniveau van zorgpersoneel betreft]. Er worden daarom geen financiële gevolgen verwacht. |
Werkwijze
Voor meer details over de gebruikte richtlijnmethodologie (GRADE) verwijzen wij u naar de Werkwijze. Relevante informatie voor de ontwikkeling van deze richtlijn is hieronder weergegeven.
Zoekverantwoording
Algemene informatie
|
Cluster/richtlijn: NOG De behandeling van progressieve myopie op kinderleeftijd |
|
|
Uitgangsvraag/modules: Module 5 Wat is het effect van de myopie progressie remmende orthokeratologie ten opzichte van reguliere lenzen of brillenglazen op de remming van progressieve myopie |
|
|
Database(s): Embase.com, Ovid/Medline |
Datum: 16 juli 2024 |
|
Periode: geen restrictie |
Talen: geen restrictie |
|
Literatuurspecialist: Alies Oost |
|
|
BMI-zoekblokken: voor verschillende opdrachten wordt (deels) gebruik gemaakt van de zoekblokken van BMI-Online https://blocks.bmi-online.nl/ Deduplication: voor het ontdubbelen is gebruik gemaakt van http://dedupendnote.nl/ |
|
|
Toelichting: Voor deze vraag is gezocht op de elementen:
De sleutelartikelen worden gevonden met deze search, m.u.v. de artikelen van Bullimore (Eye and Contact Lens 2021 47:7 (420-425), Pediatric Microbial Keratitis with Overnight Orthokeratology in Russia) en Stapleton (Ophthalmology 2008 115:10 (1655-1662), The Incidence of Contact Lens-Related Microbial Keratitis in Australia). In overleg met de adviseur is besloten dat deze mogen worden gemist omdat ze niet aan de PICO voldoen. In overleg met de adviseur is ervoor gekozen om geen limitering voor kinderen toe te passen. Er zal worden gescreend met behulp van ASreview. |
|
|
Te gebruiken voor richtlijntekst: In de databases Embase.com en Ovid/Medline is op 16 juli 2024 systematisch gezocht naar systematische reviews, RCTs en observationele studies over orthokeratologie bij myopie. De literatuurzoekactie leverde 945 unieke treffers op. |
|
Zoekopbrenst
|
|
EMBASE |
OVID/MEDLINE |
Ontdubbeld |
|
SR |
88 |
65 |
|
|
RCT |
313 |
180 |
|
|
Observationele studies |
438 |
393 |
|
|
Totaal |
839 |
638 |
945 |
Zoekstrategie
Embase.com
|
No. |
Query |
Results |
|
#1 |
'myopia'/exp OR 'high myopia'/exp OR myopia*:ti,ab,kw OR myopy:ti,ab,kw OR myopic:ti,ab,kw OR nearsight*:ti,ab,kw OR shortsight*:ti,ab,kw OR (((near OR short) NEAR/3 sight*):ti,ab,kw) OR 'refraction error'/de OR (((refraction OR refractive) NEAR/3 (error* OR disorder*)):ti,ab,kw) |
60637 |
|
#2 |
'orthokeratology lens'/exp OR 'reverse geometry contact lens'/exp OR 'corneal reshaping contact lens'/exp OR orthokeratolog*:ti,ab,kw OR 'ortho k':ti,ab,kw OR orthok:ti,ab,kw OR 'ok lens*':ti,ab,kw OR (((overnight* OR night*) NEAR/4 (lens* OR contactlens* OR softlens* OR cl OR cls OR scl OR scls OR 'corneal reshap*')):ti,ab,kw) OR (('corneal refractive' NEAR/3 (therap* OR lens*)):ti,ab,kw) OR ((corneal NEAR/3 (reshap* OR 're shap*')):ti,ab,kw) OR (('reverse geometr*' NEAR/3 (lens* OR contactlens* OR softlens* OR cl OR cls OR scl OR scls)):ti,ab,kw) |
2106 |
|
#3 |
#1 AND #2 NOT ('conference abstract'/it OR 'editorial'/it OR 'letter'/it OR 'note'/it) NOT (('animal'/exp OR 'animal experiment'/exp OR 'animal model'/exp OR 'nonhuman'/exp) NOT 'human'/exp) |
1154 |
|
#4 |
'meta analysis'/exp OR 'meta analysis (topic)'/exp OR metaanaly*:ti,ab OR 'meta analy*':ti,ab OR metanaly*:ti,ab OR 'systematic review'/de OR 'cochrane database of systematic reviews'/jt OR prisma:ti,ab OR prospero:ti,ab OR (((systemati* OR scoping OR umbrella OR 'structured literature') NEAR/3 (review* OR overview*)):ti,ab) OR ((systemic* NEAR/1 review*):ti,ab) OR (((systemati* OR literature OR database* OR 'data base*') NEAR/10 search*):ti,ab) OR (((structured OR comprehensive* OR systemic*) NEAR/3 search*):ti,ab) OR (((literature NEAR/3 review*):ti,ab) AND (search*:ti,ab OR database*:ti,ab OR 'data base*':ti,ab)) OR (('data extraction':ti,ab OR 'data source*':ti,ab) AND 'study selection':ti,ab) OR ('search strategy':ti,ab AND 'selection criteria':ti,ab) OR ('data source*':ti,ab AND 'data synthesis':ti,ab) OR medline:ab OR pubmed:ab OR embase:ab OR cochrane:ab OR (((critical OR rapid) NEAR/2 (review* OR overview* OR synthes*)):ti) OR ((((critical* OR rapid*) NEAR/3 (review* OR overview* OR synthes*)):ab) AND (search*:ab OR database*:ab OR 'data base*':ab)) OR metasynthes*:ti,ab OR 'meta synthes*':ti,ab |
1045576 |
|
#5 |
'clinical trial'/exp OR 'randomization'/exp OR 'single blind procedure'/exp OR 'double blind procedure'/exp OR 'crossover procedure'/exp OR 'placebo'/exp OR 'prospective study'/exp OR rct:ab,ti OR random*:ab,ti OR 'single blind':ab,ti OR 'randomised controlled trial':ab,ti OR 'randomized controlled trial'/exp OR placebo*:ab,ti |
4069542 |
|
#6 |
'major clinical study'/de OR 'clinical study'/de OR 'case control study'/de OR 'family study'/de OR 'longitudinal study'/de OR 'retrospective study'/de OR 'prospective study'/de OR 'comparative study'/de OR 'cohort analysis'/de OR ((cohort NEAR/1 (study OR studies)):ab,ti) OR (('case control' NEAR/1 (study OR studies)):ab,ti) OR (('follow up' NEAR/1 (study OR studies)):ab,ti) OR (observational NEAR/1 (study OR studies)) OR ((epidemiologic NEAR/1 (study OR studies)):ab,ti) OR (('cross sectional' NEAR/1 (study OR studies)):ab,ti) |
8318599 |
|
#7 |
'case control study'/de OR 'comparative study'/exp OR 'control group'/de OR 'controlled study'/de OR 'controlled clinical trial'/de OR 'crossover procedure'/de OR 'double blind procedure'/de OR 'phase 2 clinical trial'/de OR 'phase 3 clinical trial'/de OR 'phase 4 clinical trial'/de OR 'pretest posttest design'/de OR 'pretest posttest control group design'/de OR 'quasi experimental study'/de OR 'single blind procedure'/de OR 'triple blind procedure'/de OR (((control OR controlled) NEAR/6 trial):ti,ab,kw) OR (((control OR controlled) NEAR/6 (study OR studies)):ti,ab,kw) OR (((control OR controlled) NEAR/1 active):ti,ab,kw) OR 'open label*':ti,ab,kw OR (((double OR two OR three OR multi OR trial) NEAR/1 (arm OR arms)):ti,ab,kw) OR ((allocat* NEAR/10 (arm OR arms)):ti,ab,kw) OR placebo*:ti,ab,kw OR 'sham-control*':ti,ab,kw OR (((single OR double OR triple OR assessor) NEAR/1 (blind* OR masked)):ti,ab,kw) OR nonrandom*:ti,ab,kw OR 'non-random*':ti,ab,kw OR 'quasi-experiment*':ti,ab,kw OR crossover:ti,ab,kw OR 'cross over':ti,ab,kw OR 'parallel group*':ti,ab,kw OR 'factorial trial':ti,ab,kw OR ((phase NEAR/5 (study OR trial)):ti,ab,kw) OR ((case* NEAR/6 (matched OR control*)):ti,ab,kw) OR ((match* NEAR/6 (pair OR pairs OR cohort* OR control* OR group* OR healthy OR age OR sex OR gender OR patient* OR subject* OR participant*)):ti,ab,kw) OR ((propensity NEAR/6 (scor* OR match*)):ti,ab,kw) OR versus:ti OR vs:ti OR compar*:ti OR ((compar* NEAR/1 study):ti,ab,kw) OR (('major clinical study'/de OR 'clinical study'/de OR 'cohort analysis'/de OR 'observational study'/de OR 'cross-sectional study'/de OR 'multicenter study'/de OR 'correlational study'/de OR 'follow up'/de OR cohort*:ti,ab,kw OR 'follow up':ti,ab,kw OR followup:ti,ab,kw OR longitudinal*:ti,ab,kw OR prospective*:ti,ab,kw OR retrospective*:ti,ab,kw OR observational*:ti,ab,kw OR 'cross sectional*':ti,ab,kw OR cross?ectional*:ti,ab,kw OR multicent*:ti,ab,kw OR 'multi-cent*':ti,ab,kw OR consecutive*:ti,ab,kw) AND (group:ti,ab,kw OR groups:ti,ab,kw OR subgroup*:ti,ab,kw OR versus:ti,ab,kw OR vs:ti,ab,kw OR compar*:ti,ab,kw OR 'odds ratio*':ab OR 'relative odds':ab OR 'risk ratio*':ab OR 'relative risk*':ab OR 'rate ratio':ab OR aor:ab OR arr:ab OR rrr:ab OR ((('or' OR 'rr') NEAR/6 ci):ab))) |
15242050 |
|
#8 |
#3 AND #4 - SR |
88 |
|
#9 |
#3 AND #5 NOT #8 - RCT |
313 |
|
#10 |
#3 AND (#6 OR #7) NOT (#8 OR #9) - observationeel |
438 |
|
#11 |
#8 OR #9 OR #10 |
839 |
Ovid/medline
|
# |
Searches |
Results |
|
1 |
exp Myopia/ or myopia*.ti,ab,kf. or myopy.ti,ab,kf. or myopic.ti,ab,kf. or nearsight*.ti,ab,kf. or shortsight*.ti,ab,kf. or ((near or short) adj3 sight*).ti,ab,kf. or Refractive Errors/ or ((refraction or refractive) adj3 (error* or disorder*)).ti,ab,kf. |
44394 |
|
2 |
exp Orthokeratologic Procedures/ or orthokeratolog*.ti,ab,kf. or 'ortho k'.ti,ab,kf. or orthok.ti,ab,kf. or 'ok lens*'.ti,ab,kf. or ((overnight* or night*) adj4 (lens* or contactlens* or softlens* or cl or cls or scl or scls or 'corneal reshap*')).ti,ab,kf. or ('corneal refractive' adj3 (therap* or lens*)).ti,ab,kf. or (corneal adj3 (reshap* or 're shap*')).ti,ab,kf. or ('reverse geometr*' adj3 (lens* or contactlens* or softlens* or cl or cls or scl or scls)).ti,ab,kf. |
1489 |
|
3 |
(1 and 2) not (comment/ or editorial/ or letter/) not ((exp animals/ or exp models, animal/) not humans/) |
957 |
|
4 |
meta-analysis/ or meta-analysis as topic/ or (metaanaly* or meta-analy* or metanaly*).ti,ab,kf. or systematic review/ or cochrane.jw. or (prisma or prospero).ti,ab,kf. or ((systemati* or scoping or umbrella or "structured literature") adj3 (review* or overview*)).ti,ab,kf. or (systemic* adj1 review*).ti,ab,kf. or ((systemati* or literature or database* or data-base*) adj10 search*).ti,ab,kf. or ((structured or comprehensive* or systemic*) adj3 search*).ti,ab,kf. or ((literature adj3 review*) and (search* or database* or data-base*)).ti,ab,kf. or (("data extraction" or "data source*") and "study selection").ti,ab,kf. or ("search strategy" and "selection criteria").ti,ab,kf. or ("data source*" and "data synthesis").ti,ab,kf. or (medline or pubmed or embase or cochrane).ab. or ((critical or rapid) adj2 (review* or overview* or synthes*)).ti. or (((critical* or rapid*) adj3 (review* or overview* or synthes*)) and (search* or database* or data-base*)).ab. or (metasynthes* or meta-synthes*).ti,ab,kf. |
760293 |
|
5 |
exp clinical trial/ or randomized controlled trial/ or exp clinical trials as topic/ or randomized controlled trials as topic/ or Random Allocation/ or Double-Blind Method/ or Single-Blind Method/ or (clinical trial, phase i or clinical trial, phase ii or clinical trial, phase iii or clinical trial, phase iv or controlled clinical trial or randomized controlled trial or multicenter study or clinical trial).pt. or random*.ti,ab. or (clinic* adj trial*).tw. or ((singl* or doubl* or treb* or tripl*) adj (blind$3 or mask$3)).tw. or Placebos/ or placebo*.tw. |
2752155 |
|
6 |
Epidemiologic studies/ or case control studies/ or exp cohort studies/ or Controlled Before-After Studies/ or Case control.tw. or cohort.tw. or Cohort analy$.tw. or (Follow up adj (study or studies)).tw. or (observational adj (study or studies)).tw. or Longitudinal.tw. or Retrospective*.tw. or prospective*.tw. or consecutive*.tw. or Cross sectional.tw. or Cross-sectional studies/ or historically controlled study/ or interrupted time series analysis/ [Onder exp cohort studies vallen ook longitudinale, prospectieve en retrospectieve studies] |
4778227 |
|
7 |
Case-control Studies/ or clinical trial, phase ii/ or clinical trial, phase iii/ or clinical trial, phase iv/ or comparative study/ or control groups/ or controlled before-after studies/ or controlled clinical trial/ or double-blind method/ or historically controlled study/ or matched-pair analysis/ or single-blind method/ or (((control or controlled) adj6 (study or studies or trial)) or (compar* adj (study or studies)) or ((control or controlled) adj1 active) or "open label*" or ((double or two or three or multi or trial) adj (arm or arms)) or (allocat* adj10 (arm or arms)) or placebo* or "sham-control*" or ((single or double or triple or assessor) adj1 (blind* or masked)) or nonrandom* or "non-random*" or "quasi-experiment*" or "parallel group*" or "factorial trial" or "pretest posttest" or (phase adj5 (study or trial)) or (case* adj6 (matched or control*)) or (match* adj6 (pair or pairs or cohort* or control* or group* or healthy or age or sex or gender or patient* or subject* or participant*)) or (propensity adj6 (scor* or match*))).ti,ab,kf. or (confounding adj6 adjust*).ti,ab. or (versus or vs or compar*).ti. or ((exp cohort studies/ or epidemiologic studies/ or multicenter study/ or observational study/ or seroepidemiologic studies/ or (cohort* or 'follow up' or followup or longitudinal* or prospective* or retrospective* or observational* or multicent* or 'multi-cent*' or consecutive*).ti,ab,kf.) and ((group or groups or subgroup* or versus or vs or compar*).ti,ab,kf. or ('odds ratio*' or 'relative odds' or 'risk ratio*' or 'relative risk*' or aor or arr or rrr).ab. or (("OR" or "RR") adj6 CI).ab.)) |
5738806 |
|
8 |
3 and 4 - SR |
65 |
|
9 |
(3 and 5) not 8 - RCT |
180 |
|
10 |
(3 and (6 or 7)) not (8 or 9) - observationeel |
393 |
|
11 |
8 or 9 or 10 |
638 |